TOPIC
HEALTH CARE DELIVERY SYSTEM
NATIONAL,STATE,DISTRICT AND LOCAL
LEVEL
SUBMITED BY SUBMITED TO
Mr. NARESH KATIJA DR. SUMOL C. ABRAHAM
MSC PREVIOUS YEAR HOD (DEPT. OF C H N)
GOVT. COLLEGE OF NSG.
UDAIPUR
Introduction
• Constitutionally every individual in India has the right of availing health services to
protect his/her basic right of being healthy.
• To this effect govt. of India have developed health administration machinery and
Mechanism to plan, Organize and Deliver health care service to the people in rural
and urban area
• India comprise the 28 state and 9 union territories. Union territories are administered by
the president of India through chief commissioner or Lieutenant governor.
• Each state and union territories is divided in to district. There are 732 district in the
country. District under administrative control of collector.
• Health care services are rendered by the government through a network of health
centres from the grass root areas to the block level in the rural areas and through
hospital , dispensaries, maternal , child health and family welfare centres in the urban
areas. The hospital in the sub division / taluks level , district level etc. provide referral
services to the infrastructure in the rural area. There are also voluntary and private
agencies which are functioning to deal with the health problems of the people.
• To know about health care delivery system of India, we must know about some term like
Health-
Acc. To WHO health is a state of complete physical, mental, social, and spiritual well being and
not merely absence of disease or infirmity.
Illness-
Illness is a state in which a person physical, emotional, social or spiritual functioning is diminished or
impaired.
Health care-
health care is multitude of services rendered to individual or communities the agents of health
services or professional for the purpose of – promoting restoring and maintaining health.
Health care delivery system-
Health care delivery system is defined as the aggregate of institution, organization and person who
enter, the health care system, who has responsibility that, include the promotion of health,
prevention of illness, detection and treatment of disease and rehabilitation.
Determinants
• Factor which would determine health care delivery system are.
1. Consumer of health care - The people to whom health care
services are to be rendered.
2. provider of health care – Health manpower who are authorized
and responsible to provide health care Services to people.
3. Funding factor-
Components of health care delivery system-
1. structure of health system
2. Process of health care delivery
consist of two part
a. behavior of professional
b. participation of people
3. outcomes of health care
4. flow of the patients in health care system
HEALTH CARE DELIVERY SYSTEM IN INDIA
The health care delivery system in India has four levels. That are-
1. National level
2. State level
3. District level
4. Local level
NATIONAL LEVEL
• The official ‘organ’ of health system at national level are
1.Union ministry of health and family welfare.
2.The directorate general of health services
3.The central council of health
Union ministry of health and family welfare
• formed- 1976 Formed
• Headquarter – cabinet secretariat Raisina hill new Delhi.
• Annual budget – Rs 69,000 crore allocated for health sector in budget
2020.
• Union ministry of health and family welfare is headed by cabinet health
minister.
• Members of union ministry of health and family welfare are state health
minister and deputy health minister.
• DR. HARSH VARDHAN is our present union health minister.
• For all administrative purpose, ministry seek the help to health secretariat
• Union ministry of health and family welfare comprised two department
• The department of health-
• The department of health deals with health care, including awareness
campaigns, immunization 1campaigns, preventive medicine,
and public health.
• The department of family welfare-
• The department of family welfare (FW) is responsible for aspects
relating to family welfare, especially in reproductive health, maternal
health, pediatrics, information, education and communications;
cooperation with NGOs and international aid groups; and rural health
services.
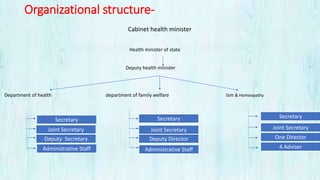
Organizational structure-
Cabinet health minister
Health minister of state
Deputy health minister
Department of health department of family welfare Ism & Homeopathy
Secretary
Joint Secretary
Deputy Secretary
Administrative Staff
Secretary
Joint Secretary
Deputy Director
Administrative Staff
Secretary
Joint Secretary
One Director
4 Adviser
Functions-
•Union list-
1. Maintenance of international health relations,
administration of port Health and quarantine laws.
2. Administration of central health institutions, training
colleges and hospitals.
3. Promotion and maintenance of appropriate standards
of education health medicine, nursing, dental,
pharmaceutical.
4.Promotion of medical and public health researches
through the Indian council of medical research and
other research institutions and bodies.
5. Regulation and development of medical, dental,
nursing and pharmaceutical professions.
6. Establishment and maintenance of drug standards.
7.Census and collection and publication of other
statically data.
8. Immigration and emigration
9.Regulation of labour working in mines and oil fields
10 . Co-ordination with states and other ministry for
promotion of health.
•
Concurrent list-
1. Prevention of extension of communicable disease from one unit to
another
2. Prevention of adulteration on of food stuff
3. Control of drug and poisons.
4. Vital statics
5. Labour welfare
6. Regulation of ports and other majors
7. Economic and social planning.
8. Population control and family welfare and family planning.
The directorate general of health services-
The directorate general of health services is repository of technical
knowledge concerning public health, medical education and health
care.
• It is attached organization of health and family welfare.
• The directorate general of health services is headed by general
director of health services.
• Ms. Bindu Tiwari our present general director of health services.
• The directorate general of health services is renders technical advice
in all medical and public health matters to ministry of health and
family welfare
Organizational structure
Director general of health services
Additional director general of health services
Deputy DGHS Deputy DGHS Deputy DGHS
Medical care Public health general administration
Functions-
1. General function
• Survey
• Planning
• Coordination
• Programming and appraisal of all health matters
Specific Function
A. International health relation
B. Medical store depot
C. Control of drug standards.
D. Post graduate training
E. Medical research
F. Medical education
G. Central govt. Health scheme
H. Implementation of national health programmes
I. Administration of certain medical collage es in India
Central council of health family welfare
• This ‘organ’ was set up to help promote a working relationship between the
center and the states in implementation of all health programs and provide a
forum for co-operation.
• The constitution provides for consultation between the various state government
and central government. As a result the central council of health has been formed
in august 1952 under article 263 of the constitution.
• CCHFW is composed of union health minister as chairman, health ministers of all
states and union territories as members.
• It meets once a year and decides what needs to be done in the areas of family
planning, health, medical education and research.
• There are also zonal health councils in the - central, northern, western, eastern,
and southern zone.
• Each zonal council perform the same function as that of central health council at
the zonal level
Organization chart
Union health minister ( Chairperson )
State health minister ( members )
The functions of the council are
• Promoting co-operation and co-ordination between the health organizations
at the central and state levels
• Formulating broad policy and program outlines for the provision of medical
relief and health care and also for training of health personnel
• Proposing suitable legislations in public health matters
• Recommending a framework for appropriate distribution of grants-in-aid to
states for health purposes
• Reviews the health work done in the past one year.
STATE LEVEL
• The official ‘organ’ of health system at state level are-
• (a) State ministry of health and family welfare.
• (b) State directorate general of health
• (c) State health secretaria
( a ) State ministry of health and family welfare
• State ministry of health and family welfare headed by state health
minister and deputy health minister.
• Present health minister of Rajasthan is Dr. Raghu sharma.(MLA kekdi
Ajmer )
• Present state health minister of Rajasthan is subhash garg
• State ministry of health and family welfare perform both activities
that are political and administrative activities.
• Ministers have political responsibilities toward their constituencies as
per their political agenda and responsibilities for administration and
management of health and family welfare services in their state.
The functions of state ministry of health and family
welfare are:
• Support and safeguard the policies.
• Bring the all the bill to his department for approval.
• Policy implementation.
(b) State directorate general of health
• State directorate general of health headed by director of health and
family welfare
• Present director of health and family welfare of Rajasthan is Dr. R.S
Chhipi.
• State directorate general of health is principle advisor of state govt.
On all medicine and public health matters.
• It is a technical wing of mohfw
• fore independence medical & public health services at state level like
at the Centre administered by two separate department
The functions of state ministry of health and family
welfare are:
• A. providing adequate medical care in rural and urban area.
• B. Arrangement of medical education and research.
• C. Implementation of national health programs.
• D. Make provision for personal and impersonal health services.
• E. Control food and drug adulteration
• F. Control over ESI scheme.
• G. Supervision and control of local bodies.
(c) State health secretariat -
• State health secretariat is official organ of state health ministry.
• State health secretariat keep records of policies.
• State health secretariat headed by state health secretary.
• Present state health secretary of Rajasthan is Shri Rohit Kumar Singh.
The functions of state health secretariat are:
• A. Assist in forming and modification of policies.
• B. Control, supervision and co-ordinate policies..
• C. Budgeting.
• D. Maintain contact with central and other state govts..
• E. Observe administrative machinery
DISTRICT LEVEL
• The principle unit of administration in India is the district under a collector.
• There are total 732 district in India.
• There are total 33 district in Rajasthan
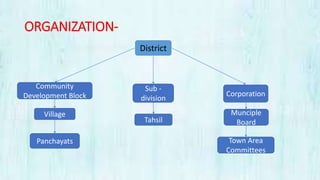
• There are six type of administrative area in a district-
1. Sub-division
2. Tahsils
3. Community developmental blocks
4. Municipalities and corporations.

5. Villages.

6. Panchayats.

ORGANIZATION-
District
Sub -
division
Tahsil
Community
Development Block
Village
Panchayats
Corporation
Munciple
Board
Town Area
Committees
LOCAL LEVEL
 Rural local self government work with its
three constitutions-
I)Gram Panchayat
II)Gram Sabha
III)Nyaya panchayat
Health care system.
•In India, health care delivery system is represented by
five major sectors.
1 Public health sector
• Primary health care
• Sub centers
• Hospitals/health centers
• Community health centers
• Rural hospitals
• District hospital
• Specialist hospitals
• Teaching hospitals
•Health insurance schemes
• Employees state insurance
• Central govt. health system
•Other agencies
• Defense services
• Health care of railway employees
2.Private sector
a.Private hospitals, polyclinic, nursing
homes and dispensaries
b.General practitioners
3.Indigenous system of medicine
a. Ayurveda and siddha
b. Unani
c. Homeopathy
d. Unregistered practitioners
4. Voluntary health agencies
5. National health programme
A.Primary health services
1. Village level
To implement this policies at the village level the following schemes are in
operation.
a. Village health guide
b.ASHA scheme ( accredited social health activist )
1. Must be resident of the village a women
(married / widow / divorced )
2. 25 - 45 year of age
3. 8th class pass
4. One ASHA for 1000 population.
• Function of ASHA –
1. Take steps to create awareness and provide information to community
of health such as.
- Nutrition
- basic sanitation and hygienic practice.
- healthy living and working condition
- information on existing health services
- timely utilization of health and family welfare
services
2. Counsel women for –
- Safe delivery
- breast feeding
- complementary feeding
- immunization
- contraception
- prevention of common infection – UTI
- STD etc.
3. ASHA will mobilize the community and facilitate them in
health and health related servicesa vailable at – aganwadi
- SC, PHC such as – immunization
- ANC, PNC etc.
4. she will work with village health and sanitation committee of gram panchayat to
develop village health plan.
5. provide primary medical care for minor ailment.
6. Act as depot holder for – ORS , pills, condoms etc.
7. Inform about the birth and death in her village or any unusual health problem
disease.
8. Provide construction of house hold toilet under total sanitation campaign.
C. Anganwadi worker –
- under ICDS programme start in 1975 with 33 block & 4891 centers
- one Anganwadi worker for 400 – 800 people.
- 100 workers in each ICDS block
- 7067 ICDS block functioning in country.
- four month training
- 7500 Rs salary per month
- more than 1.3 million ( 13.73 lakh ) anganwadi centres in India.
- 12.8 lakh anganwadi workers in country.
- 11.6 lakh helpers
- at present total 54677 centers functioning in Rajasthan
-2977 anganwadi centers functioning in Udaipur.
- budget for 2020. 35600 crore
- govt. gave 6 lakh anganwadi workers smartphones in this budget.
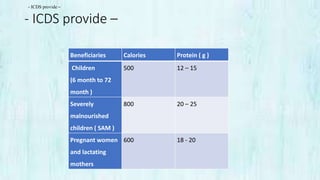
- ICDS provide –
Beneficiaries Calories Protein ( g )
Children
(6 month to 72
month )
500 12 – 15
Severely
malnourished
children ( SAM )
800 20 – 25
Pregnant women
and lactating
mothers
600 18 - 20
- ICDS provide –
Financial norms for supplementary nutrition under
ICDS
Category Cost norms per beneficiary per day
Children
(6 month to 72 month )
Rs. 6
Severely malnourished children ( SAM ) Rs. 9
Pregnant women and lactating mothers Rs. 7
d. Local dias
- training of dias initiated during 2001-02
- the scheme was implemented in 156 district in 18 states / UTs of the country.
- the district selected were on the basis of the safe delivery rate being less than 30 %
- the scheme was extended to all the district of EAG ( Empowered Action Group )state.
- the aim was to train at least one dias in every village with objectives of making
delivery safe
Rural health care system in India
• The health care infrastructure in rural areas has been developed as a
three tire system and is based on the population norms.
Health facility Population norms
Plain area Hilly / Tribal
/ Difficult area
Sub – center 5000 3000
Primary Health center 30,000 20,000
Community health
center
1,20,000 80,000
Sub center level
• Categories of sub centers
Type A Type B
1. Provide all recommended services except
that the facilities for conducting delivery
will not be available here.
1. The sub-centers in the following situation
may be included in this categories
A. Sub centers not having adequate space
and physical infrastructure for
conducting deliveries due to which
providing labor room facilities and
equipment at these subcenters not
possible.
A. Subcenters situated in the vicinity of
other higher health facilities like
PHC / CHC / FRU / Hospital where
deliveries facilities are available.
A. Subcenters in headquarter area .
B. Subcenters where present no deliveries
or occasional delivery may be taking
place.
This would include following type of subcenters
A. Centrally or betters located subcenters with good
connectivity to catchment area
B. They have good physical infrastructure preferable with
own building , adequate space residential
accommodation and labour room facilities.
C. They already have good case load of deliveries from
catchment area
D. There are no nearby higher level deliveries facilities.
Services provided at subcenters
1. maternal and child health services – ANC , Intranatal , PNC etc.
2. family planning and contraceptive
3. counseling – MTP, abortion etc.
4. adolescent health care
5. assistance to school health services
6. water quality monitoring
7. promotion of sanitation including use of toilet and appropriate garbage disposal
8. field visit for - disease surveillance , family welfare service including STI, RTI,
awareness
9. community need assessment
10. curative services for minor ailment
11. training of TBA (Trained Birth Attendant ) and ASHA
12. cooperative services of anganwadi workers ,ASHA, village health and sanitation
committee etc.
13. disease surveillance
14. national health programme
15. promotion of medical herbs
16. records of vital events
17. coordination and monitoring
18. outreach services.
Manpower
Type of Scs A B
ANM / Health worker
(female)
1(E) + 1(D) 2
Health worker (Male) 1 1
Staff nurse 1 (no. of deliveries more than
2 or more in month)
Safai karmchari 1 (part time) 1 (full time)
Primary health centers level
• - The bhore committee in 1946 gave the concept of the of PHCs
• - PHC is the first contact point between village community and medical officer.
• - it act as a referral unit of 6 subcenters and refer out cases to CHCs
• - it cover population of 30,000 in plain and 20,000 in hilly and tribal area
• - as on 31 march 2019 – 24,855 in country
• - 2066 in Rajasthan
• - it has 4- 6 beds for patients
• - From services delivery angle PHCs may be of two type depending upon the delivery case load.
•
• Type A – PHCs with less than 20 deliveries per month
• Type B – PHCs with 20 or more deliveries per month
Function of PHCs
1. medical care
2. MCH including family planning
3. Safe water supply and basic sanitation
4. Prevention & control of local endemic disease
5. Collection and reporting of vital statistics
6. Education about health
7. National health programme
8. Referral services
• Training of health guides , health workers , local dais , and health assistance
• Basic laboratory services
• Selected surgical procedure
• Mainstreaming of AYUSH
• PMR
• Maternal death review
• Functional linkage with sub centers
• Monitoring & supervision
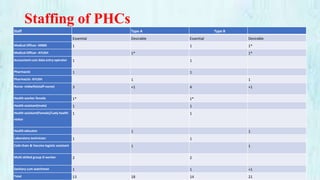
Staffing of PHCs
Staff Type A Type B
Essential Desirable Essential Desirable
Medical Officer- MBBS 1 1 1*
Medical Officer- AYUSH 1* 1*
Accountant cum data entry operator 1 1
Pharmacist 1 1
Pharmacist- AYUSH 1 1
Nurse- midwife(staff-nurse) 3 +1 4 +1
Health worker female 1* 1*
Health assistant(male) 1 1
Health assistant(Female)/Lady health
visitor
1 1
Health educator 1 1
Laboratory technician 1 1
Cold chain & Vaccine logistic assistant 1 1
Multi skilled group-D worker 2 2
Sanitary cum watchman 1 1 +1
Total 13 18 14 21
Community health centers
• - these were established by upgrading the primary health centers
• - CHCs are being established and maintained by the state govt.
• - each community health centers cover 80,000 population in rural area & 1,20,000 population in plain
area
• - it is manned by four medical specialist i.e. Surgeon , Physician , Gynecologist , Pediatrician . and 21
paramedical & other staff.
- It has 30 indoor beds with one OT, X-ray , labour room , and laboratory facilities.
- It serve as a referral center for 4 PHCs .
First referral unit - Criteria – emergency obstetric care including surgical intervention like CS
- New born care
- Blood storage facility on 24 hours
Function of CHCs
• Care of routine and emergency cases in surgery
• Care of routine and emergency cases in medicine
• Maternal health
• New born care and child health
• Family planning
• All national health programme delivered through CHCs
• School health services
• Blood storage facility
• Essential laboratory
• Referral (transport services )
• Maternal death review ( MDR )
Health and wellness centers
• The national health policy 2017 recommended strengthening the delivery system of primary health care through
establishment of health and wellness centers as the platform to deliver comprehensive primary health care.
- Govt. of India is committed toward creation of 150000 health & wellness centers by transforming existing
subcenters and PHCs as basic pillar of Ayushman bharat to deliver comprehensive primary health care.
- As on 31 march 2019 there are -157411 SCs
• - 24855 PHCs
• - 5335 CHCs which are functioning in the country.
- Further there are 7821 SCs which are upgraded as health and wellness centers – sub centers ( HWC- SCs ) as of
total 157411 and
- 8242 health & wellness centers – primary health centers ( HWC -PHCs ) has been upgraded out of 24855.
Hospitals
a.Rural hospital – cover 5 lakh population
b.District hospital –
Hospital differ from a health centers
1. In a hospital services provided are mostly curative in nature. in a health
centers the services are preventive, promotive and curative.
2. Hospital has no catchment area i.e. it has no definite area of responsibility.
Patient may be drawn from many part of the country. A health centers and on
the other hand is responsible for a definite area and population
Health insurance
1. Employees state insurance scheme – introduced by an act of
parliament in 1948.
2. Central government health scheme – introduce in 1954 for central
govt. employee.
Other agencies
1. Defense medical services – medical care to defense personal under
care the banner AFMS (Armed Forces Medical Services )
2. Health care of railway employee
. Private agencies
. Indigenous system of medicine - AYUSH
. Voluntary health agencies –
1. Indian red cross society – 1920 - 400 branches in India
2. Hindu kusht nivaran singh – 1950
3. Indian council for child welfare – 1950
4. Tuberculosis association of India 1939
5. Bharat sevak samaj – 1952
6. Central social welfare board – 1953
•
7 The Kasturba memorial fund – 1944
8. Family planning association of India – 1949
9. All India women conference – 1926
10. All India blind relief society – 1946
11. Professional bodies – TNAI , IMA ete.
12. International agencies – 1. The Rockefeller foundation
2. Ford foundation
3. CARE ( Cooperative for Assistance & Relief Every
Health care Delivery System in India