Overview of
Common Genetic Tests
DR. CHAKSHU CHAUDHRY
SENIOR RESIDENT
GENETIC METABOLIC UNIT
PGIMER
8/6/21
Chromosomes Genes
• “Coloured bodies”
• Chromosomes are thread-like structures
• Composed mainly of chromatin - that carries highly
ordered sequence of linked gene
• Resides in Nucleus of Eukaryotic cells
• Exist in pairs. Human cells contain 23 such pairs or 46
chromosomes. – Tjio and Levan in 1956
Chromosomes
Chromosomal disorders
When to suspect a
Chromosomal disorder? / How
to identify?
What are types of
Chromosomal disorders?
What are the tests available for
testing chromosomal
disorders?
Indications
Technique
Advantages
Limitations
Antenatal
• Antenatally detected
cystic hygroma or
increased NFT
• Multiple Soft markers
• +/- Advanced
Maternal age
When to suspect a
Chromosomal disorder? / How
to identify?
Children
• Constellation of clinical
features consistent with
known disorder
• Dysmorphism with or
without behavioral problems
• Unexplained ID
Newborns
• Multiple congenital
malformations
• Significant symmetrical
growth restriction and
microcephaly
• Facial Dysmorphism
• Disorders of sexual
development
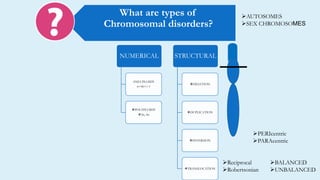
What are types of
Chromosomal disorders?
NUMERICAL
ANEUPLOIDY
n=46+/-1
POLYPLOIDY
3n, 4n
STRUCTURAL
DELETION
DUPLICATION
INVERSION
TRANSLOCATION
AUTOSOMES
SEX CHROMOSOMES
PERIcentric
PARAcentric
BALANCED
UNBALANCED
Reciprocal
Robertsonian
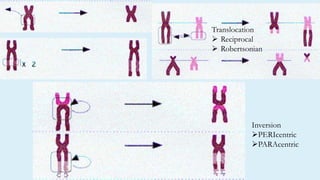
Inversion
PERIcentric
PARAcentric
Translocation
 Reciprocal
 Robertsonian
What are the tests available for
testing chromosomal
disorders?
Non Targeted
• KARYOTYPE
• CMA/aCGH
Targeted
• FISH
• MLPA
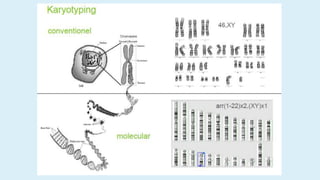
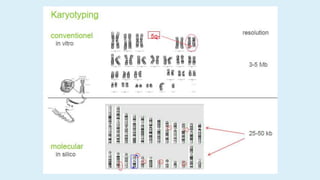
Karyotyping
Banding
Techniques
FISH
MLPA
Comparative
Genomic
Hybridization
• Karyotype: A chromosome complement of a cell or species
• Karyogram / Ideogram : A pictorial display of metaphase
chromosomes from a mitotic cell
• Cytogenetics: Study of chromosomes and inheritance
• Molecular Cytogenetics: Techniques that deal with the entire genome
or specific DNA sequences to analyse genomic structural and
behavioural variations at chromosomal or subchromosomal level
Karyotype and Cytogenetics
Procedure of Karyotyping
Karyotype is based on
- Size
- Centromeric position
- Banding pattern
Large metacentric:1-3 Large submetacentric : 4-5
Medium Submetacentric : 6-12 + X
Large Acrocentric : 13-15
Small Submetacentric : 16-18
Small metacentric : 19-20 Small Acrocentric : 21-22 + Y
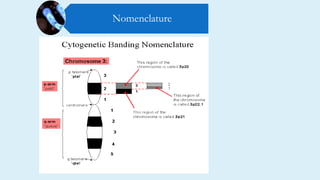
Nomenclature
High and Low resolution
Karyotype designation
• Suspected known chromosomal syndrome
• Disorders of sexual development
• Short stature in a prepubertal female
• Unexplained Intellectual disability especially when
associated with
• Multiple organ malformations
• Facial dysmorphism
• Growth retardation
Indications
• Infertility
• Recurrent pregnancy losses
• Parents of a child with structural chromosomal
abnormality
• For prenatal diagnosis if one of the parent is
carrier of balanced translocation
• Malignancies
• Special Chromosomal studies – chromosomal
breakage syndrome
Indications
• Low resolution limited to 5-10Mb
• Labour intensive
• Requirement of skilled operator
• Takes 4-7 days for cells to culture
• Cheaper than most other tests
• Easy accessibility
• Can detect balanced translocations,
Inversions, Mosaicism
Advantages Limitations
Karyotype
• Array CGH is able to detect copy number changes at a level of 5–10 kb
DNA.
• It is faster and more sensitive than conventional metaphase analysis for
the identification of constitutional rearrangements.
• Microarray chip – A high density miniaturized array of oligonucleotides
spotted onto a glass slide. Identify cryptic Deletions and Duplications.
Array CGH (Microarray-based
comparative genomic
hybridization)
Step 1-3: patient and control DNA are
labelled with fluorescent dyes and
applied to the microarray which has
human genome
Step 4: patient and control compete to
attach or hybridize to the microarray
Step 5: the microarray scanner
measures the fluorescent signals ( red,
green, yellow)
Step 6: computer analyses the data and
generate a plot
Technique of
microarray
• The first-line test in the investigation of patients with
severe developmental delay
learning difficulties
congenital abnormalities
prenatal testing of fetus
when abnormalities are detected by ultrasound scanning.
Suspicion of a chromosomal disorder based on maternal serum markers levels
Indications
Limitations
• High cost
• Cannot detect
• Balanced
translocations
• Inversions
• Del/dup across all chromosomes
• Regions of LOH- s/o AR disorders
• UPD- long stretch of LOH
• Yield is better than traditional
chromosomal analysis/ karyotyping
• May detect mosaicism
Advantages
Array CGH
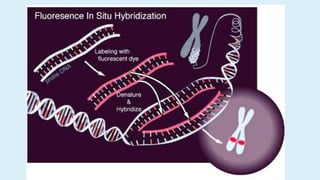
• FISH is a method that can be used to detect small deletions and
duplications that are not visible using microscope analysis.
• It can also be used to detect how many chromosomes of a certain type
are present in each cell and to confirm rearrangements that are suspected
after microscope analysis.
FISH (Fluorescence in situ
hybridization)
(a) The basic elements of FISH are a DNA probe and a target
sequence.
(b) Before hybridization the DNA probe is fluorescently labelled
via the incorporation of a fluorophore
(c) The labeled probe and the target DNA are denatured.
(d) Combining the denatured probe and target allows the
annealing of complementary DNA sequences.
(e) Finally, the signals are evaluated by fluorescence microscopy
Technique
(a) Chromosomal Aneuploidies
(b) Chromosomal Deletion – 4p-, 5p-
(c) Chromosomal microdeletion syndromes – 22q11Del,
7q11Del, 15q11Del
(d) Translocation
Indications
Advantages
Very rapid- 3 -4 days
Efficiency of
Hybridization and
deletion is high.
Sensitivity and specificity
is high.
Better resolution
Restricted to those abnormalities that
can be detected with currently available
probe.
Only one or a few abnormalities can be
assessed simultaneously.
Has higher sensitivity for trisomy but
less sensitive for detecting chromosome
loss or deletion.
Requires fluorescence Microscopy and
an image analysis system.
Limitations
FISH
• PCR-based quantitation technique.
• Multiplex reaction
• 45 Chromosomal segment can be identified in a single
reaction
• Probes are amplified
• And amplification depends upon specific hybridisation and
ligation
Multiplex ligation dependent probe
amplification (MLPA)
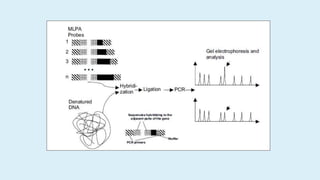
Basic steps in MLPA
1. Denaturation
2. Hybridization
3. Ligation
4. Amplification
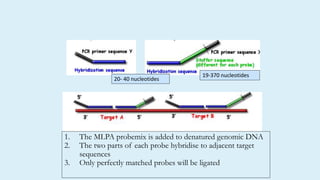
1. The MLPA probemix is added to denatured genomic DNA
2. The two parts of each probe hybridise to adjacent target
sequences
3. Only perfectly matched probes will be ligated
20- 40 nucleotides
19-370 nucleotides
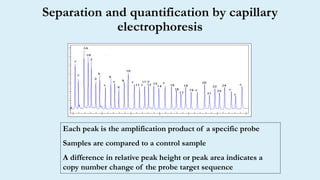
Separation and quantification by capillary
electrophoresis
Each peak is the amplification product of a specific probe
Samples are compared to a control sample
A difference in relative peak height or peak area indicates a
copy number change of the probe target sequence
Results
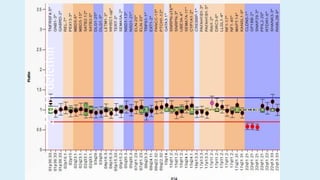
• Are always compared with a control sample
• Allele copy numbers
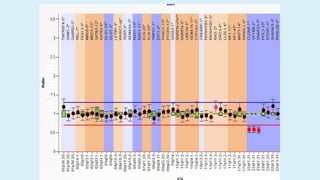
• A ratio of about 1 is obtained if both alleles are present, a ratio of about
0.5 when one allele is absent and a ratio of about 1.5 if one allele is
duplicated
22q11
deletion
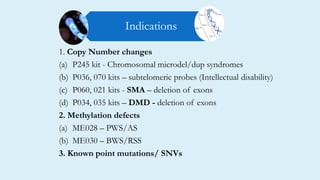
1. Copy Number changes
(a) P245 kit - Chromosomal microdel/dup syndromes
(b) P036, 070 kits – subtelomeric probes (Intellectual disability)
(c) P060, 021 kits - SMA – deletion of exons
(d) P034, 035 kits – DMD - deletion of exons
2. Methylation defects
(a) ME028 – PWS/AS
(b) ME030 – BWS/RSS
3. Known point mutations/ SNVs
Indications
Advantages
Cost effective
Multiple areas of genome
simultaneously
45 patient samples in one reaction
 Rapid results
Efficiency of Hybridization and
deletion is high. Identify
abberations that are too small to
be picked up by FISH
Versatile – can be customised
 Only known mutations can be detected
 Restricted to those abnormalities that
have currently available probes.
 Requires fluorescence Microscopy and an
image analysis system.
 Not detect mosaicism, tri/tetraploidies.
 Sometimes needs confirmation by
alternate method.
Limitations
MLPA
CLINICAL SCENARIOS
PATIENT 1
• Development delay
• Examination – mongoloid slant of eyes, flat
facies, small ears, b/l simian crease and
clinodactyly
• AVCD
• What genetic tests can be done- Trisomy 21?
• Conventional Karyotyping
• Fluorescence in situ hybridization (FISH)
PATIENT 2
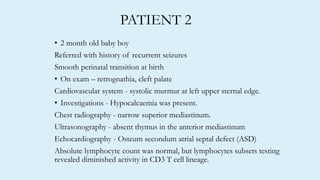
• 2 month old baby boy
Referred with history of recurrent seizures
Smooth perinatal transition at birth
• On exam – retrognathia, cleft palate
Cardiovascular system - systolic murmur at left upper sternal edge.
• Investigations - Hypocalcaemia was present.
Chest radiography - narrow superior mediastinum.
Ultrasonography - absent thymus in the anterior mediastinum
Echocardiography - Osteum secondum atrial septal defect (ASD)
Absolute lymphocyte count was normal, but lymphocytes subsets testing
revealed diminished activity in CD3 T cell lineage.
• Di George Syndrome
Will Karyotype detect a microdeletion syndrome??
Investigation of choice –
• FISH
• MLPA
22q11
deletion
PATIENT 3
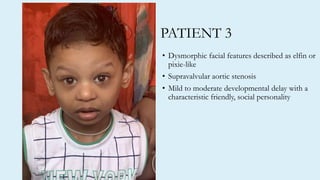
• Dysmorphic facial features described as elfin or
pixie-like
• Supravalvular aortic stenosis
• Mild to moderate developmental delay with a
characteristic friendly, social personality
What genetic tests can be done - deletion at
7q.11.23?
• Fluorescence in situ hybridization (FISH)
• MLPA with probes specific for the elastin gene, one of approximately 26
to 28 genes located at 7q11.23.
• Chromosomal microarray analysis (comparative genomic hybridization) –
can detect. However, above 2 tests are preferred.
PATIENT 4
• 28 year old woman with 4 Recurrent spontaneous first
trimester abortions
• POC – CMA was done – Trisomy 13
• Karyotype of couple was done to check if any of them is
balanced translocation carrier
• Karyotype of husband- 46XY t(4,13)
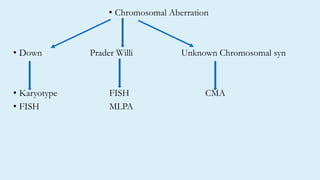
• Chromosomal Aberration
• Down Prader Willi Unknown Chromosomal syn
• Karyotype FISH CMA
• FISH MLPA
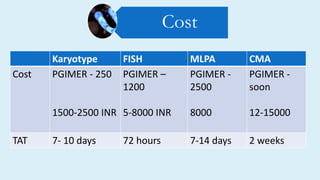
Cost
Karyotype FISH MLPA CMA
Cost PGIMER - 250
1500-2500 INR
PGIMER –
1200
5-8000 INR
PGIMER -
2500
8000
PGIMER -
soon
12-15000
TAT 7- 10 days 72 hours 7-14 days 2 weeks
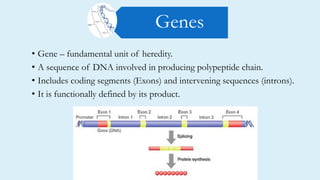
• Gene – fundamental unit of heredity.
• A sequence of DNA involved in producing polypeptide chain.
• Includes coding segments (Exons) and intervening sequences (introns).
• It is functionally defined by its product.
Genes
Is a Pathogenic Variation in DNA –
Point mutation - structural change
• Deletion
• Insertion
• Substitution - replacement of single base nucleotide with
another
• Frameshift – generally leads to non sense and chain termination
Functional change - can lead to missense or nonsense change.
Mutation
Disorders of the Gene
When to suspect Rare
Mendelian disorders? / How
to identify?
What are types of Mendelian
Diseases?
What are the tests available for
testing disorders of gene?
Indications
Technique
Advantages
Limitations
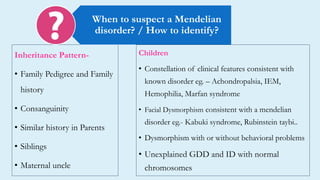
Inheritance Pattern-
• Family Pedigree and Family
history
• Consanguinity
• Similar history in Parents
• Siblings
• Maternal uncle
When to suspect a Mendelian
disorder? / How to identify?
Children
• Constellation of clinical features consistent with
known disorder eg. – Achondropalsia, IEM,
Hemophilia, Marfan syndrome
• Facial Dysmorphism consistent with a mendelian
disorder eg.- Kabuki syndrome, Rubinstein taybi..
• Dysmorphism with or without behavioral problems
• Unexplained GDD and ID with normal
chromosomes
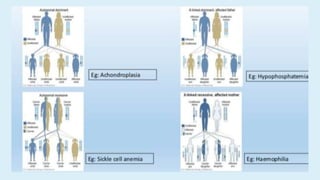
• Autosomal Dominant
• Autosomal Recessive
• X linked Dominant
• X linked Recessive
What are types of Mendelian
Diseases?
What are the tests available for
disorders of Gene?
Targeted
• PCR
• Sanger
Sequencing -
First
generation
Non Targeted
• Next
Generation
Sequencing
• Next generation Sequencing
NGS Panels
Clinical Exome sequencing
Whole Exome sequencing
Whole Genome sequencing
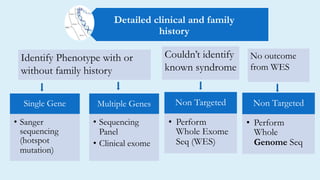
• PRE and POST test counselling is of utmost importance.
Single Gene
• Sanger
sequencing
(hotspot
mutation)
Multiple Genes
• Sequencing
Panel
• Clinical exome
Non Targeted
• Perform
Whole Exome
Seq (WES)
Detailed clinical and family
history
Identify Phenotype with or
without family history
Couldn’t identify
known syndrome
No outcome
from WES
Non Targeted
• Perform
Whole
Genome Seq
• DNA sequencing is the process of determining the sequence of
nucleotide bases (eg: ATCGAT) in a piece of DNA
• Frederick Sanger - two times Nobel Prize winner
• Human Genome Project – 1990-2003 – determining base pairs that
make up human DNA – 2.7 billion USD
Sanger Sequencing
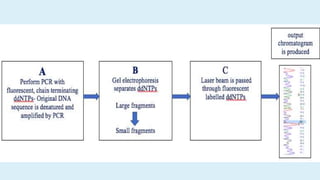
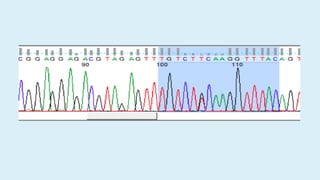
• Principle –
is a DNA sequencing method in which target DNA is denatured
annealed to oligonucleotide primers (fluorescently labelled)
extended by DNA polymerase using mixture of dNTPs and chain
terminating ddNTPs
• ddNTPs – lack 3’OH group to which next dNTP of growing chain is
added. Hence, no more nucleotides can be added.
Sanger Sequencing
• For confirmation of a variant found by NGS
• Once a variant is detected in an affected patient by NGS, Sanger
sequencing is performed For
• Segregation analysis in parents
• Family Screening
• For prenatal testing, in a future sibling of an affected child
• A small gene - cost effective to perform Sanger Sequencing rather
than NGS
• For common hotspot mutations in certain diseases like – Cystic
Fibrosis, Achondroplasia
Indications
Limitations
• Targeted
• Can only sequence short pieces
of DNA--about 300 to 1000
base pairs.
• High cost
• Laborious
• Great Accuracy
• Gold standard for SNV
• Cost depends on the region/ length
of DNA/ no. of exons.
Advantages
Sanger Sequencing
• Sequencing all of the protein-coding regions of genes in a
genome (known as the exome).
• Exome is only 1% of total genome
Whole Exome Sequencing
•To detect Single Nucleotide Variation (SNV)
For Mendelian disorders
Polygenic Disorders – such as Alzheimer's disease
Cancer Syndromes
Indications
Advantages
• Non focused
• All 30,000 genes
• Once data
generated, can be
stored, reanalyzed in
future.
• Large amount of data
• Results need clinical correlation
• Parents and sibling testing is required in most cases
• Many times Variants of unknown significance is found –
needs further testing to classify it into benign or
pathogenic
• Test is costly – price around 20,000 INR
• Time taken for results – 3- 6 weeks
• Ethical issues - newborns, adult onset disorders,
predictive testing – No strict guidelines in India
Limitations
Whole Exome Sequencing
• 99% of the human genome is not covered by exome
sequencing.
• Sequences all coding as well as non coding regions (Exons +
Introns)
• Presently, rarely practical in the clinical context
high costs
time associated with sequencing full genomes.
Whole Genome Sequencing
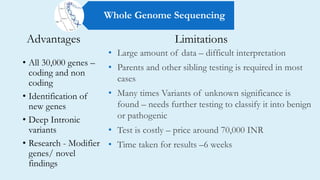
Advantages
• All 30,000 genes –
coding and non
coding
• Identification of
new genes
• Deep Intronic
variants
• Research - Modifier
genes/ novel
findings
• Large amount of data – difficult interpretation
• Parents and other sibling testing is required in most
cases
• Many times Variants of unknown significance is
found – needs further testing to classify it into benign
or pathogenic
• Test is costly – price around 70,000 INR
• Time taken for results –6 weeks
Limitations
Whole Genome Sequencing
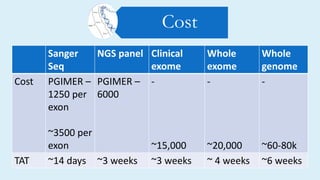
Cost
Sanger
Seq
NGS panel Clinical
exome
Whole
exome
Whole
genome
Cost PGIMER –
1250 per
exon
~3500 per
exon
PGIMER –
6000
-
~15,000
-
~20,000
-
~60-80k
TAT ~14 days ~3 weeks ~3 weeks ~ 4 weeks ~6 weeks
ABCD1 Adrenoleukodystrophy
AGL Glycogen storage disease IIIa, IIIb
ARSA Metachromatic leukodystrophy
ARSB Mucopolysaccharidosis type VI (Maroteaux-Lamy)
ASPA Canavan disease
CFTR
Congenital bilateral absence of vas deferens, Cystic fibrosis, Sweat
chloride elevation without CF, {Pancreatitis, hereditary}
G6PC Glycogen storage disease Ia
GAA Glycogen storage disease II
GALC Krabbe disease
GALNS Mucopolysaccharidosis IVA
GBA Gaucher disease
GCDH Glutaricaciduria, type I
GLB1
GM1-gangliosidosis, type I, II, III, Mucopolysaccharidosis type IVB
(Morquio)
GNPTAB Mucolipidosis II & III alpha/beta
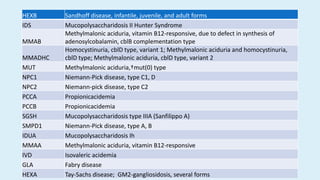
NGS Panel
HEXB Sandhoff disease, infantile, juvenile, and adult forms
IDS Mucopolysaccharidosis II Hunter Syndrome
MMAB
Methylmalonic aciduria, vitamin B12-responsive, due to defect in synthesis of
adenosylcobalamin, cblB complementation type
MMADHC
Homocystinuria, cblD type, variant 1; Methylmalonic aciduria and homocystinuria,
cblD type; Methylmalonic aciduria, cblD type, variant 2
MUT Methylmalonic aciduria,†mut(0) type
NPC1 Niemann-Pick disease, type C1, D
NPC2 Niemann-pick disease, type C2
PCCA Propionicacidemia
PCCB Propionicacidemia
SGSH Mucopolysaccharidosis type IIIA (Sanfilippo A)
SMPD1 Niemann-Pick disease, type A, B
IDUA Mucopolysaccharidosis Ih
MMAA Methylmalonic aciduria, vitamin B12-responsive
IVD Isovaleric acidemia
GLA Fabry disease
HEXA Tay-Sachs disease; GM2-gangliosidosis, several forms
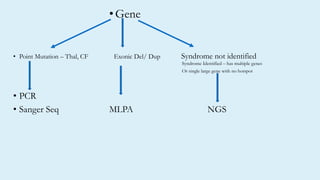
•Gene
• Point Mutation – Thal, CF Exonic Del/ Dup Syndrome not identified
• PCR
• Sanger Seq MLPA NGS
Syndrome Identified – has multiple genes
Or single large gene with no hotspot
THANK YOU