








Excretion of Drugs and Kinetics
of elimination
Dr. D. K. Brahma
Associate Professor
Department of Pharmacology
NEIGRIHMS, Shillong
Goal
• Different organs of drug excretion and
mechanism
• Renal excretion of drugs
• Concepts of drug clearance and plasma half
life
• Concept of the platue principle
Organs of Excretion
• Excretion is a transport procedure which the
prototype drug (or parent drug) or other metabolic
products are excreted through excretion organ or
secretion organ
• Hydrophilic compounds can be easily excreted.
• Routes of drug excretion
– Kidney
– Biliary excretion (Faeces)
– Exhaled air
– Sweat and saliva
– Milk
Faeces (Hepatic Excretion)
• Unabsorbed and derived from bile
• Drugs can be excreted in bile, especially when
they are conjugated with – glucuronic acid
 Organic acids - OATP and MRP2
 Organic Bases – OCT
 Lipophilic drugs – P-gp
 Larger molecules are eliminated (MW>300)
• Drug is absorbed  glucuronidated or sulfatated in the liver and secreted
through the bile  glucuronic acid/sulfate is cleaved off by bacteria in GI
tract  drug is reabsorbed (steroid hormones, rifampicin, amoxycillin,
contraceptives) - ENTEROHEPATIC CIRCULATION
• Anthraquinone, heavy metals – directly excreted in colon
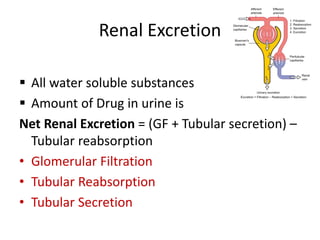
Renal Excretion
 All water soluble substances
 Amount of Drug in urine is
Net Renal Excretion = (GF + Tubular secretion) –
Tubular reabsorption
• Glomerular Filtration
• Tubular Reabsorption
• Tubular Secretion
Glomerular Filtration
• Net Renal excretion: (GF + tubular secretion) – tubular
reabsorption
• Glomerular capillaries have pores larger than usual
• All nonprotein bound drugs (lipid soluble or insoluble)
presented to the glomerulus are filtered
• Glomerular filtration of drugs depends on their plasma
protein binding and renal blood flow - Protein bound drugs
are not filtered !
• Normal GFR – 120 ml/min
• Renal failure and aged persons – declines progressively
Tubular Re-absorption
• Physiologically 99% of Glomerular Filtrates are reabsorbed
• Back diffusion of Drugs (99%) – lipid soluble drugs
• Depends on pH of urine, ionization etc.
• Lipid insoluble ionized drugs excreted as it is – aminoglycoside
(amikacin, gentamicin, tobramycin)
• Changes in urinary pH can change the excretion pattern of drugs
– Weak bases ionize more and are less reabsorbed in acidic urine.
– Weak acids ionized more and are less reabsorbed in alkaline urine
• Utilized clinically in salicylate and barbiturate poisoning – alkanized
urine
• Acidified urine – atropine and morphine etc.
• Effects of changes in urine pH is best observed with Drugs having
pKa of 5 – 8
Tubular Secretion
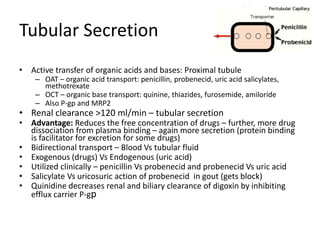
• Active transfer of organic acids and bases: Proximal tubule
– OAT – organic acid transport: penicillin, probenecid, uric acid salicylates,
methotrexate
– OCT – organic base transport: quinine, thiazides, furosemide, amiloride
– Also P-gp and MRP2
• Renal clearance >120 ml/min – tubular secretion
• Advantage: Reduces the free concentration of drugs – further, more drug
dissociation from plasma binding – again more secretion (protein binding
is facilitator for excretion for some drugs)
• Bidirectional transport – Blood Vs tubular fluid
• Exogenous (drugs) Vs Endogenous (uric acid)
• Utilized clinically – penicillin Vs probenecid and probenecid Vs uric acid
• Salicylate Vs uricosuric action of probenecid in gout (gets block)
• Quinidine decreases renal and biliary clearance of digoxin by inhibiting
efflux carrier P-gp
Renal Excretion – must remember!
• Acidic urine
• alkaline drugs eliminated
• acid drugs reabsorbed
• Alkaline urine
- acid drugs eliminated
- alkaline drugs absorbed
Kinetics of
Elimination
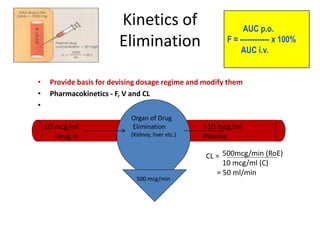
• Provide basis for devising dosage regime and modify them
• Pharmacokinetics - F, V and CL
•
AUC p.o.
F = ------------ x 100%
AUC i.v.
10 mcg/ml
Drug in
>10 mcg/ml
Plasma
500mcg/min (RoE)
10 mcg/ml (C)
= 50 ml/min
CL =
500 mcg/min
Organ of Drug
Elimination
(Kidney, liver etc.)
Clearance
• Clearance: The clearance (CL) of a drug is the
theoretical volume of plasma from which drug
is completely removed in unit time
CL = Rate of elimination (RoE)/C
Example = If a drug has 20 mcg/ml and RoE is 100
mcg/min
CL = 100/20 = 5 ml /min
Kinetics of Elimination
• First Order Kinetics (exponential): Rate of elimination is
directly proportional to drug concentration, CL
remaining constant
– Constant fraction of drug is eliminated per unit time
• Zero Order kinetics (linear): The rate of elimination
remains constant irrespective of drug concentration
– CL decreases with increase in concentration
– Alcohol, theophyline, tolbutmide etc.
Plasma half-life
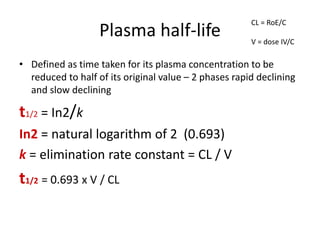
• Defined as time taken for its plasma concentration to be
reduced to half of its original value – 2 phases rapid declining
and slow declining
t1/2 = In2/k
In2 = natural logarithm of 2 (0.693)
k = elimination rate constant = CL / V
t1/2 = 0.693 x V / CL
CL = RoE/C
V = dose IV/C
Kinetics of Elimination
Zero Order 1st Order
conc.
Time
Plasma half-life
1 half-life …………. 50%
2 half-lives………… 25%
3 half-lives …….…..12.5%
4 half-lives ………… 6.25%
5 half-lives ………… 3.125%
• 1st order kinetics – t1/2 does not change (V and CL
remains unchanged
• 0 order kinetics – t1/2 increases (CL decreases as
dose is increased)
50 + 25 + 12.5 +
6.25 = 93.75
93.75 + 3.125 +
1.56 = 98%
after 5 HL
Repeated Dosing
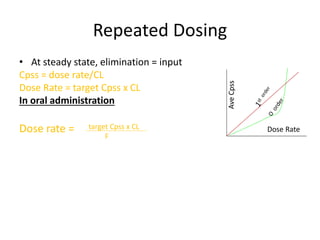
• At steady state, elimination = input
Cpss = dose rate/CL
Dose Rate = target Cpss x CL
In oral administration
Dose rate = target Cpss x CL
F
Dose Rate
AveCpss
Excretion - The Platue Principle
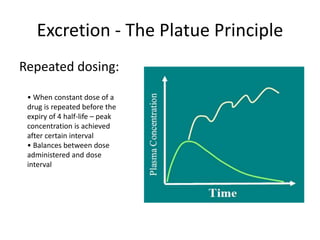
Repeated dosing:
• When constant dose of a
drug is repeated before the
expiry of 4 half-life – peak
concentration is achieved
after certain interval
• Balances between dose
administered and dose
interval
Target Level Strategy
• Drugs whose feect are not quantifiable, low safety margin drugs
(anticonvulsants, antidepressants, Lithium, Theophylline etc. –
aimed at achieving certain concentration within therapeutic range
• Drugs with short half-life (2-3 Hrs) – drugs are administered at
conventional intervals (6-12 Hrs) – fluctuations – target levels only
intermittently – however therapeutically acceptable for many drugs
• Long acting drugs: Prolonged half-life – accumulate and toxicity
– Have to wait for 4 half-life for steadty state
– Single dose or repeated dose in quick succession – to attain target
conc. Quickly
• Loading dose = target Cp X V/F
– Maintenance dose: dose to be repeated at specific intervals
– Dose Rate = target Cpss x CL
F
Summary – Must Know
• Drug Clearance
• Orders of kinetics
• Plasma half-life
• The Platue principle
Excretion of drugs and kinetics of elimination