Endovascular Management Strategies for Immature Arteriovenous Fistula Maturation
Comprehensive overview of diagnosis, hemodynamics, and endovascular interventions to salvage immature arteriovenous fistulas for hemodialysis access, including PTA, stent grafts, and clinical outcomes.
Global Burden
• AVFnon-maturation remains common.
• Prevalence: 20% to 60% of newly created
AVFs fail to mature adequately for use.
Port J Nephrol Hypert 2021
5.
Preoperative Planning
• VesselMapping: (DUS) is essential;
reduces failure rates from 35% to 8%
compared to physical exam alone.
• Minimum Diameters: Artery ≥2.0
mm; Vein ≥2.0 mm to 2.5 mm.
Hemodialysis Access - Society for Vascular Surgery
(KDOQI2019)
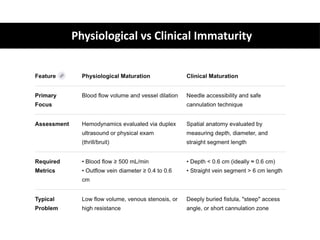
AVF Maturation
• Historical"Rule of 6s": 6 weeks post-
op; flow >600 mL/min, diameter >6
mm, depth <6 mm, and 6 cm length.
• 2019 KDOQI Functional Definition:
Ability to provide prescribed dialysis
with two needles for 75% of
treatments over 4 weeks.
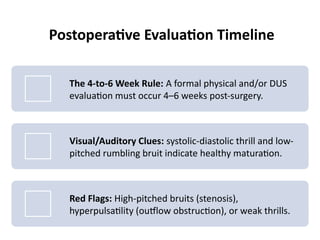
Postoperative Evaluation Timeline
The4-to-6 Week Rule: A formal physical and/or DUS
evaluation must occur 4–6 weeks post-surgery.
Visual/Auditory Clues: systolic-diastolic thrill and low-
pitched rumbling bruit indicate healthy maturation.
Red Flags: High-pitched bruits (stenosis),
hyperpulsatility (outflow obstruction), or weak thrills.
12.
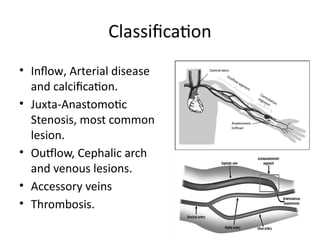
Classification
• Inflow, Arterialdisease
and calcification.
• Juxta-Anastomotic
Stenosis, most common
lesion.
• Outflow, Cephalic arch
and venous lesions.
• Accessory veins
• Thrombosis.
13.
Accessory Veins
(Competitive drainage)
•The "Steal" Problem: Large branches divert flow from the primary conduit,
dropping pressure and preventing dilatation.
• Clinical Goal: Eliminate competitive flow to divert 100% of volume into the
main outflow channel.
• Evidence: post-AVO, fistulas often mature within one month.
• Technical Option: AVO Methods
• Coil Embolization: Effective but carries a risk of migration to central
circulation or pulmonary arteries.
• Vascular Plugs (VPs): Self-expanding nitinol mesh; offers more precise
placement and lower migration risk.
• Surgical Ligation: Often preferred for acute takeoff angles where wire
selection is difficult.
Timing of Intervention
•Endovascular Salvage Window: If maturation
stalls by 6 weeks, intervene promptly (6–8
week window) to minimize CVC exposure.
• Acute Thrombosis: A critical medical
emergency; rescue is most successful within
48 hours.
• Avoid Preemptive PTA: Intervention on
asymptomatic stenosis in a
functioning/maturing AVF is NOT
recommended.
17.
Role of EndovascularIntervention
• Objective: Mechanical correction of anatomical lesions to
facilitate physiological remodeling.
• Salvage Rates: Endovascular techniques can rescue up to 80%
of immature AVFs from primary failure.
• Advantage: Minimally invasive, outpatient-based, and
preserves future "venous capital”.
18.
PTA
First-line therapy
• Options:Balloon-Assisted
Maturation (BAM)
• Primary Balloon Angioplasty (PBA)
Emerging technique of
intraoperative dilatation to
accelerate maturation from Day 1.
• Technical Success: Typically ranges
from 88.9% to 97%.
19.
PTA
• Sequential Sizing:4 mm high-
pressure balloons for juxta-
anastomotic lesions; 5–6 mm for
outflow.
• Large-Balloon Strategy: Using
balloons ≥7 mm leads to higher
maturation rates (97% vs. 88%)
and faster catheter-free HD.
The "Stentula" Technique
•Retrograde Placement: Stent placed
toward (but not crossing) the arterial
anastomosis.
• Strict Maturation Period: A 2-week "wait"
with antiplatelet therapy is mandatory to
allow epithelialization/fibrous
encapsulation.
• Result: The stented segment can be safely
and routinely punctured for HD access.
22.
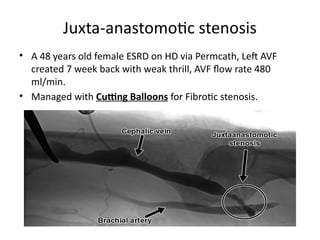
Juxta-anastomotic stenosis
• A48 years old female ESRD on HD via Permcath, Left AVF
created 7 week back with weak thrill, AVF flow rate 480
ml/min.
• Managed with Cutting Balloons for Fibrotic stenosis.
23.
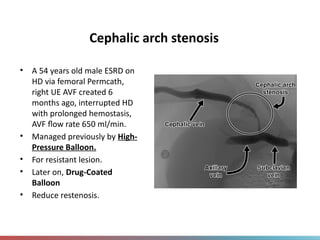
Cephalic arch stenosis
•A 54 years old male ESRD on
HD via femoral Permcath,
right UE AVF created 6
months ago, interrupted HD
with prolonged hemostasis,
AVF flow rate 650 ml/min.
• Managed previously by High-
Pressure Balloon.
• For resistant lesion.
• Later on, Drug-Coated
Balloon
• Reduce restenosis.
24.
Clinical Success
Outcomes
• TechnicalSuccess:
Reported at 95.7% to 97%
for endovascular salvage.
• Clinical Success (HD
readiness): Achieving
functional HD in 85.2% to
93.4% of salvaged cases.
25.
Post-Intervention Patency
• 1-YearPrimary Patency: Varies significantly (45.4% to 71.9%)
depending on initial lesion severity.
• 1-Year Secondary Patency: Consistently high, ranging from
82.8% to 94.8%.
• Maintenance: Functional patency often requires repeated
interventions (aim for <3 annually).
26.
Independent
Predictors of
Salvage
Success
• StenosisSeverity: Pre-intervention
narrowing >90% is a strong predictor of
reduced durability and early restenosis.
• Lesion Type: "Mixed" stenosis
(combined inflow and outflow) is
associated with poor outcomes (HR
6.33).
• Permcath History: A history of
ipsilateral Catheter is the sole risk
factor for complete maturation failure
after BAM.