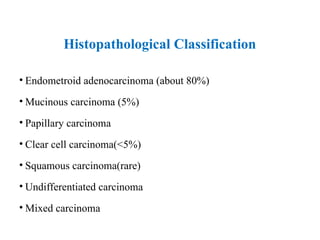
Introduction
•Endometrial cancer isthe sixth most common cancer, with 4,17 000 new
cases and 97,000 deaths in 2020.
•Third cancer malignancy of female genital tract in India next to cervical and
ovarian malignancy.
•The Incidence of endometrial cancer is rising alongside the growing obesity.
•Most women with endometrial cancer are diagnosed at an early stage and
have highly curable disease, reflected in excellent 5-year survival rates.
•Patients presenting with adverse clinicopathological characteristics have
biologically aggressive endometrial cancer phenotypes with poor prognosis.
•The diagnosis and management of endometrial cancer is challenging and
complex, requires the expertise team who are familiar with all aspects of its
evaluation and treatment.
Sung H et al,.2021
3.
Incidence
•Most frequently diagnosedcancer in females with the greatest incidence
in high-income countries.
•In developing countries including India, endometrial cancer is seen in 1.8
per 100,000 population.
The peak incidence of endometrial cancer is at 55-70 years,
20-25 % occur in Peri menopausal women
Only 5% develop in women below the age of 45 years (when they are
well differentiated and have good survival).
Crosbie E, Morrison J. The emerging epidemic of endometrial cancer: Time to take action. Cochrane
Database Syst Rev. 2014 Dec 22;12(ED000095
4.
Risk factors
• Mostof the risk factors are related to prolonged, unopposed estrogen
stimulation of endometrium.
• Nulliparity
• Late menopause
• Obesity
• Diabetes mellitus
• Unopposed estrogen therapy
• Tamoxifen therapy
• Atypical endometrial hyperplasia
• LYNCH II syndrome (Hereditary non polyposis colorectal cancer
syndrome)-Mutation in mismatch repair gene MLH1,MSH2,MSH6
Novak 16th edition
5.
Clinical features
Symptoms
•About 90%of women with endometrial carcinoma have abnormal
perimenopausal or postmenopausal vaginal bleeding or discharge as
their only presenting symptoms.
•May be asymptomatic (7-10 %) cases.
•Obesity and hypertension are associated constitutional factors.
Signs
• Pelvic examination- may reveal a normal looking healthy cervix and
blood or purulent discharge from external os.
• Bimanual examination-may reveal either atrophic, normal or enlarged
uterus.
6.
Etiology
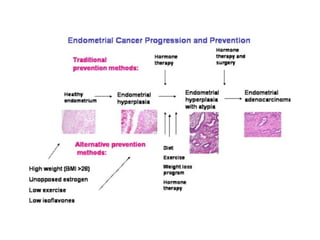
•Most of theendometrial cancer begins with uninterrupted endometrial
proliferation, hormonally stimulated by endogenous or exogenous estrogen
unopposed by progesterone or progestins, progressing through states of
simple to complex forms of endometrial hyperplasia (EH).
•Endometrial intraepithelial neoplasia (EIN), may transform to endometrioid
carcinoma by-
Stromal and/or myometrial invasion,
PTEN mutations, and KRAS2 mutations,
Microsatellite instability caused by mismatch repair (MMR) defects.
• The hormonal etiology of EIN and endometrial endometrioid carcinomas
usually express estrogen and progesterone receptors (ER and PR)
•Most endometrial endometrioid carcinomas are lower grade cancers
Mahdy H et al.,2022
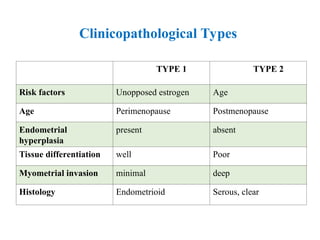
Clinicopathological Types
TYPE 1TYPE 2
Risk factors Unopposed estrogen Age
Age Perimenopause Postmenopause
Endometrial
hyperplasia
present absent
Tissue differentiation well Poor
Myometrial invasion minimal deep
Histology Endometrioid Serous, clear
9.
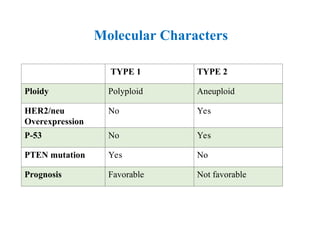
TYPE 1 TYPE2
Ploidy Polyploid Aneuploid
HER2/neu
Overexpression
No Yes
P-53 No Yes
PTEN mutation Yes No
Prognosis Favorable Not favorable
Molecular Characters
10.
FIGO Grading
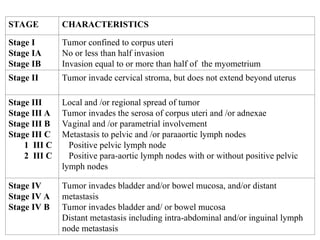
Staging ofEC is based on the FIGO 2018 (International Federation
of Gynecology and Obstetrics) staging system.
GRADE 1- <5 % non-squamous or non-morular growth pattern
GRADE 2- 6-50% non-squamous or non-morular growth pattern
GRADE 3- >50% non-squamous or non-morular growth pattern
11.
STAGE CHARACTERISTICS
Stage I
StageIA
Stage IB
Tumor confined to corpus uteri
No or less than half invasion
Invasion equal to or more than half of the myometrium
Stage II Tumor invade cervical stroma, but does not extend beyond uterus
Stage III
Stage III A
Stage III B
Stage III C
1 III C
2 III C
Local and /or regional spread of tumor
Tumor invades the serosa of corpus uteri and /or adnexae
Vaginal and /or parametrial involvement
Metastasis to pelvic and /or paraaortic lymph nodes
Positive pelvic lymph node
Positive para-aortic lymph nodes with or without positive pelvic
lymph nodes
Stage IV
Stage IV A
Stage IV B
Tumor invades bladder and/or bowel mucosa, and/or distant
metastasis
Tumor invades bladder and/ or bowel mucosa
Distant metastasis including intra-abdominal and/or inguinal lymph
node metastasis
12.
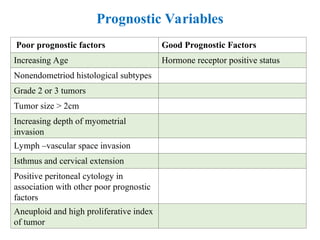
Prognostic Variables
Poor prognosticfactors Good Prognostic Factors
Increasing Age Hormone receptor positive status
Nonendometriod histological subtypes
Grade 2 or 3 tumors
Tumor size > 2cm
Increasing depth of myometrial
invasion
Lymph –vascular space invasion
Isthmus and cervical extension
Positive peritoneal cytology in
association with other poor prognostic
factors
Aneuploid and high proliferative index
of tumor
13.
Pathophysiology
• Endometrial carcinomasbegin as preinvasive intraepithelial
lesions, progress to full-blown invasive cancers then penetrating
ever more deeply into the myometrium to engage lymphatic
capillaries that carry the malignancy to regional lymph nodes.
• Tumorous involvement of the uterine cervix and stroma probably
is mostly through lymphatic channels
• Lymphatic capillaries also may carry endometrial carcinoma cells
to the adnexa.
Mahdy H et al.,2022
14.
• Locally advancingendometrial cancers may penetrate fully through the
myometrium and uterine serosa to involve surrounding peritoneum,
supporting tissues and other pelvic organs.
• Low-grade, type 1 endometrioid carcinomas tend to remain confined to
the uterus and are characterized by rather a favorable prognosis.
• High-grade, type 2 endometrioid and non-endometrioid carcinomas with
TP53 mutations often metastasize via the lymphatic system or transit
through the fallopian lumens to disseminate throughout the pelvis and
abdomen, manifesting at advanced stage and portending grave prognoses.
16.
Screening
• Screening isnot recommended in general population & not
very cost effective
• For high risk group (eg: Lynch syndrome) screening can be
done with TVS & aspiration biopsy ( start at 35yrs , annually
until hysterectomy)
17.
DIAGNOSIS
• Transvaginal sonography- Endometrial Thickness is assessed as per menopausal status.
A cutoff value of 4 mm is taken foe menopausal women and 16 mm for premenopausal
women. Any intracavitary growth irregular endometrium is also considered suspicious.
• Endometrial biopsy - Office endometrial aspiration biopsy is the first step in diagnosing
endometrial carcinoma with 90-98% accuracy. Hysteroscopy guided biopsy should be
done in patients with focal endometrial growth or thickening, irregular endometrium,
cervical stenosis, recurrent bleeding after negative endometrial biopsy or if specimen
obtained is inadequate on EA.
• Liquid based cytology (LBC) and endocervical curettage (ECC) may be performed to
rule out coexisting cervical pathology.
• MRI abdomen and pelvis is useful for detecting invasion into the myometrium and lymph
node metastasis.
• Chest Xray is added for lung metastasis.
18.
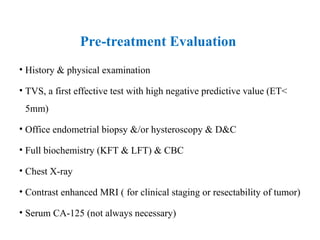
Pre-treatment Evaluation
• History& physical examination
• TVS, a first effective test with high negative predictive value (ET<
5mm)
• Office endometrial biopsy &/or hysteroscopy & D&C
• Full biochemistry (KFT & LFT) & CBC
• Chest X-ray
• Contrast enhanced MRI ( for clinical staging or resectability of tumor)
• Serum CA-125 (not always necessary)
Surgery isthe mainstay of treatment for endometrial cancer and is decided as
per the preoperative assessment of stage of disease based on clinical examination
and imaging.
Stage IA GI or II, endometroid histology - Extrafascial Total Abdominal
Hysterectomy with Bilateral Salpingo Oophorectomy (TAH with BSO).
Stage IB or IA GIII or non-endometroid histology or tumor >2 cm or stage II
- TAH with BSO with pelvic and para-aortic lymphadenectomy
Serous histology- TAH BSO with omentectomy and peritoneal biopsy
Stage III - Debulking surgery- TAH with BSO with omentectomy, removal of
abdominopelvic metastasis and enlarged nodes.
Stage IV: Neoadjuvant chemotherapy f/b cytoreductive Sx. Vaginal bleeding/pain
from local tumor/leg edema: pelvic radiotherapy.
21.
Choice of SurgicalApproach
•RCTs show superiority of minimally invasive approaches.
Considerations during MIS hysterectomy include use of uterine
manipulator to facilitate exposure and avoidance of power
morcellator to remove uterus should.
•MIS may be difficult in cases with excessive uterine size,
contraindication to trendelenburg position.
•Sentinel lymph node biopsy can safely replace complete
lymadenectomy where needed.
22.
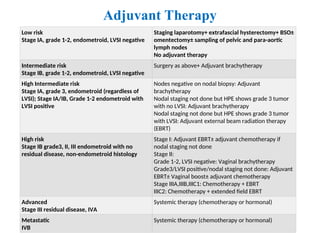
Adjuvant Therapy
Low risk
StageIA, grade 1-2, endometroid, LVSI negative
Staging laparotomy+ extrafascial hysterectomy+ BSO±
omentectomy± sampling of pelvic and para-aortic
lymph nodes
No adjuvant therapy
Intermediate risk
Stage IB, grade 1-2, endometroid, LVSI negative
Surgery as above+ Adjuvant brachytherapy
High Intermediate risk
Stage IA, grade 3, endometroid (regardless of
LVSI); Stage IA/IB, Grade 1-2 endometroid with
LVSI positive
Nodes negative on nodal biopsy: Adjuvant
brachytherapy
Nodal staging not done but HPE shows grade 3 tumor
with no LVSI: Adjuvant brachytherapy
Nodal staging not done but HPE shows grade 3 tumor
with LVSI: Adjuvant external beam radiation therapy
(EBRT)
High risk
Stage IB grade3, II, III endometroid with no
residual disease, non-endometroid histology
Stage I: Adjuvant EBRT± adjuvant chemotherapy if
nodal staging not done
Stage II:
Grade 1-2, LVSI negative: Vaginal brachytherapy
Grade3/LVSI positive/nodal staging not done: Adjuvant
EBRT± Vaginal boost± adjuvant chemotherapy
Stage IIIA,IIIB,IIIC1: Chemotherapy + EBRT
IIIC2: Chemotherapy + extended field EBRT
Advanced
Stage III residual disease, IVA
Systemic therapy (chemotherapy or hormonal)
Metastatic
IVB
Systemic therapy (chemotherapy or hormonal)
23.
Special Consideration
• Diagnosispost hysterectomy: If grade3 lesion, deep myometrial invasion, or LVSI –
remove adnexa or adjuvant EBRT
• Medically in operable patient: Most common reason is morbid obesity or severe
cardiopulmonary dysfunction.
• Primary radiotherapy is an option Well differentiated lesion, contraindication to
general anesthesia, unsuitable for radiotherapy can be treated with high dose
progestins or intrauterine hormone releasing device.
• Diagnosis in young women: Uncommon, can be confused with severe atypical
hyperplasia.
• Fertility preservation only recommended in grde1 tumor with no myometrial invasion.
• Progestins ( megestrol acetate 160-320mg/d or MPA 400-600 mg/d) may be given
with LNG-IUS should be continued as long as disease is static or in remission.
Hysterectomy is recommended once child bearing is complete
24.
Targeted Therapy
Includes drugstargeting molecular pathways vital to cancer survival.
The drugs available are-
Temsirolimus,
Deforolimus, & Everolimus (mTOR inhibitors),
Bevacizumab (Angiogenesis inhibitor) as single agent
Paclitaxel & Carboplatin,
Geftinib (tyrosine kinase inhbitor),
Palbciclib (CDK4/6 inhibitor) & Rastuzumab ( Her2/neu receptor)
25.
Follow-Up:
•ACOG recommends follow-upevery 3-4 months for 2-3yrs, then every 6 m0nth, annually after 5
yrs
•Routine chest X-ray & vaginal cytology not recommended
•Pelvic examination & symptoms directed examination is recommended
•High risk for other cancer so life style modification advocated
Recurrence:
•Main stay of treatment is surgery, radiation therapy or both
•Non localised tumor are treated with progestin therapy: MPA 50-100mg TDS or megesterol acetate
80mg BD or TDS
•Platinum based chemotherapy (cisplatin & doxorubicin or carboplatin & paclitaxel) is
recommended for patient with advanced or recurrent disease not amenable to cure by surgery and/or
radiotherapy.
26.
Summary
• 3rd
m/c malignancyof female genital tract in India
• Women can be counseled about the risk factors such as obesity and increased body mass index.
• Encouraged for lifestyle modification and weight loss which can lead to reduced endogenous
production of estrogen.
• Patients should be managed thoroughly by history examination and investigation for early
detection of precursor of Endometrial cancer
• Type 1 tumor is more common & have better prognosis
• Staging is mainly surgical
• No routine screening is recommended
• Surgery is the main stay of treatment & MIS are better approach then conventional laparotomy
• SLN mapping can safely replace conventional lymphadenectomy



 Most read
 Most read