1
Learning objective
At the end of this chapter the student will be able to:

 Describe the effects of insulin on different organ/systems
 Differentiate the types of insulin with their therapeutic uses and
adverse reactions
 Identify the mechanism of action, uses and side effects of oral
hypoglycemic agents
 Describe the therapeutic use of thyroid and anti thyroid drugs
 Recognize drugs used as oxytocic agents
 Describe Steroidal hormones and analogues with their
pharmacological actions
 Differentiate types of hormonal contraception with their uses and
adverse effects including preparations
2
ANTIDIABETIC DRUGS
INTRODUCTION
 Diabetes Mellitus (DM) is a disease that occurs as a result
of absolute or relative deficiency of insulin that results in
metabolic and vascular abnormalities
 is a group of metabolic diseases characterized by high blood
glucose levels – Hyperglycaemia
The etiologies /risk factors include:
 Obesity (because chronic calorie intake and prolonged
stimulation of  cell causes a decrease in insulin receptor,
and also adipose tissue & muscle are less sensitive to insulin)
3
 Hereditary
 Damage of pancreatic tissue
 Diabetogenic hormones(like growth hormone,
thyroid, epinephrine)-are antagonize the action of
insulin
 Diabetogenic drugs like thiazide diuretics, epinephrine,
phenothiazines
 Other factors like Pregnancy-eg.placenta & placental
hormones create resistance to insulin
4
Diagnosis
 Elevated FBG ≥126 mg/dl
 Glucose Tolerance test →2-hr plasma glucose 200mg/dl or
higher
 Hgb A1c ≥ 6.5%
Note: The diagnosis should be done on more than one occasion
5
DM can be classified as:
Type I: IDDM (or Juvenile type)
 This occurs predominantly in children and young
adults who have no insulin secretion
Type II: NIDDM (or maturity onset type)
 Usually occur after the age of 40 years
6
Antidiabetogenic drugs
I. INSULIN
 Sources of insulin include:
 enzyme modification of Pork or beef or a combination
of pork and beef insulin and
 Human insulin (Recombinant DNA technique)
7
Actions:
 Insulin lowers the blood glucose level by:
 increasing utilization of glucose by peripheral tissue and
 promoting synthesis and storage of glycogen
 The main actions of the hormone are exerted on metabolism
of carbohydrate (CHO), fat and protein in liver, muscle &
adipose tissue
8
Effects of insulin on:
Carbohydrate metabolism
 Liver:
 it increases glycogen synthesis from glucose and ↑se glucose
utilization
 it decreases gluconeogenesis and glycogenolysis
 Muscle:
 it increases glucose uptake, glucose utilization and glycogen
synthesis
 Adipose tissue:
 it increases glucose uptake and glycerol synthesis (glycerol
esterifies fatty acid to form triglycerides)
9
Fat metabolism
 Liver:
 it increases lipogenesis (fatty acid formation)
 Adipose tissue:
 it increases synthesis of triglycerides and synthesis of fatty
acid
Protein metabolism
 Liver:
 it decreases protein catabolism
 Muscle:
 it increases amino acid uptake and protein synthesis
10
Other metabolic effect:
 It increases uptake of K+, Ca++ and nucleosides into cells
and synthesis of nucleic acids
There are some factors that increase insulin demand:
 Like infection, surgery, pregnancy and
 Drugs (those that antagonize actions of insulin
glucocorticoids, thyroid hormone and/or adrenaline)
11
Types of insulin preparation:
Rapid-acting insulin (ultra short acting):
 insulin lispro, insulin aspart, insulin glulisine
 Clear solutions at neutral pH
 Very fast onset of action (5-15 min), short duration of action (3-5 h)
 Given 2-3 times/day
 Control postprandial hyperglycemia (s.c.)
 In emergency situations as in diabetic ketoacidosis (i.v)
Short acting (rapid onset): Eg. Regular Insulin
 Soluble crystalline zinc insulin
 Clear solutions at neutral pH
 Fast onset of action 30-45 min (s.c)
 Short duration of action (5-8 h)
 2-3 times/day
 To control postprandial hyperglycemia (s.c.)
 In emergency situations as in diabetic ketoacidosis (i.v).
 Can be used in pregnancy.
12
Types of insulin preparation…….
Intermediate acting Eg. Lente insuline, NPH(neutral
protamine hagedorn) insulin
 Onset of action: 1-2 h
 Duration of action: 13-20 h
 Turbid suspension at neutral pH
 Given S.C. only, not intravenously
 NOT used in emergencies (diabetic ketoacidosis)
Long acting E.g Protamine Zn insuline, insulin determir, insulin
glargine
 Given s.c., not intravenously
 Slow onset of action 2h.
 low continuous insulin level over 24 h
 Long duration of action (24 h)
 Once daily
 Insulin glargine- should not mixed with other insulin since its
solubility is affected due change in pH (soluble at pH of 4.0)
13
Therapeutic use
 Insulin is inactivated by GI enzymes, thus given by injection
 The subcutaneous route is ideal
 It is usually injected into the upper arms, thighs, buttocks, or
abdomen
 Insulin is needed by all patients with type 1 diabetes
 In type 2 diabetes (not controlled by diet and oral hypoglycemic
agents) for intercurrent events: surgery, infections, serious illness,
trauma
 Diabetic ketoacidosis (I.V. Regular human insulin)
 For control of diabetes in pregnancy - Regular Insulin
 They are also used in the treatment of hyperkalmia due to renal
failure
14
Adverse Reaction: can be categorized as
 Local: Lipodystrophy (atrophy or hypertrophy) at site of
injection, local hypersensitivity and secondary infections
 Common with older animal insulin preparations
 But this never seen human and analog insulin
preparations of neutral pH
 Lipodystrophy may be corrected by avoidance of the
same injection site
 Systemic: Hypoglycemic coma and Immunologic reaction
like hypersensitive
Hypoglycemic coma
 Corrected by oral/ iv glucos,or iv glucagon
 glucose 50% 20 – 100 ml IV, or
 glucagon 1mg IV, IM, SC
15
ORAL HYPOGLYCEMICS
 These are drugs administered orally to lower blood glucose
level in patients with type 2 diabetes
 They are grouped as:
 Insulin secretagogues eg. Sulphonylureas,
meglitinides
 Biguinides eg. Metformin
 Thiazolidinediones eg. Pioglitazone, rosiglitazone
 Are insulin sensitizing compounds
 ἀ-glucosidase inhibitors eg. Miglitol, acarbose
16
Sulphonyl ureas
 These compounds are chemically related to sulphonamides
 First generation:
 Tolbutamide, Chlorpropamide,tolazamide,acetohexamide
 Second generation:
 Glibenclamide(glyburide), Glipizide, glimepiride
Second generations are highly potent, safe on long term
use
17
Mechanism of action
 Hypoglycemic action is due to:
 the stimulation of insulin release from  cell
 by blocking the ATP-sensitive potassium channel →
depolarization → insulin release
Pharmacokinetics
 Similar spectrum of activity
 All are absorbed from the GIT
– Food and hyperglycemia retard absorption
 Highly plasma protein bound
 All the sulfonylureas are metabolized by the liver, and the
metabolites are excreted in the urine
 Thus sulfonylureas should be administered with caution to
patients with either renal or hepatic insufficiency
18
Sulphonyl ureas…..
Therapeutic Uses
 To control hyperglycemia in type 2 DM not managed
by diet and lifestyle changes
 More effective in patients > 40 years
 Contraindications to the use of these drugs include
type 1 DM, pregnancy, lactation and, significant
hepatic or renal insufficiency
19
Sulphonyl ureas…
Adverse Effects
• Hypoglycaemia: the longer the half life of the agent the more likely it
is to induce hypoglycemia
• Displacement from binding sites by other drugs can exacerbate
hypoglycemia
• Nausea & vomiting, cholestatic jaundice, agranulocytosis, aplastic &
haemolytic anaemia, hypersensitivity and severe skin reactions
• cause weight gain
Drug interaction:
 Hypoglycemia is enhanced by sulphonamides, phenylbutazone
 Alcohol produces “Disulfirum” like action (flushing of the face, severe
headache, vomiting etc.)
 Sulphonyl ureas increase anticoagulant effect of oral anticoagulant
20
Biguinides (Metformin)
 They potentiate the hypoglycemic action of insulin and
sulphonyl ureas
 but they don’t produce clinical hypoglycemia in diabetics
Mechanism:
 Decreases basal hepatic glucose production
 Increased action of insulin on muscle and fat
21
Pharmacokinetic
 Metformin has a half-life of about 3 hours and is excreted
unchanged in the urine
 is not associated with weight gain and even promotes
weight loss
• When added to a sulfonylurea, the effects of both agents are
additive
• Can also be combined with other oral agent
Use:
 Obese diabetics (uncontrolled by diet alone, they cause loss
of appetite or anorexia w/c leads to wt loss),
 Supplement to sulphonyl urea
22
Side effects:
Nausea, vomiting, anorexia, diarrhea, abdominal cramp,
metallic taste, lactic acidosis
Contraindication:
 Diabetes with renal insufficiency
 during pregnancy
 Alcoholics
 Cardiac failure
23
Thyroid and anti Thyroid Drugs
Thyroid hormones
 The thyroid gland secretes three main hormones: thyroxine (T4),
triiodothyronine (T3) and calcitonin
 T4& T3 are responsible for optimal growth, development, function, and
maintenance of all body tissues (nervous, skeletal, and reproductive
tissues)
 Calcitonin is involved in the control of plasma Ca2+
 Inadequate secretion of thyroid hormone (hypothyroidism)
 results in bradycardia, poor resistance to cold, and mental and physical
slowing (in children this can cause irreversible mental retardation and
cretinism)
 Excess secretion of thyroid hormone (hyperthyroidism)
 causes tachycardia and cardiac arrhythmias, body wasting, nervousness,
tremor, and excess heat production can occur

24
Thyroid drugs
 Synthetic levothyroxine (T4) is the preparation of choice for
 thyroid replacement(in hypothyroidism or cretinism) and
suppression therapy because of its stability
 Levo-thyroxine sodium (L-T4) Tab.,Inj
 Liothyronine (T3) is three to four times more potent than
levothyroxine
 It is used for short term suppression TSH – in nontoxic goiter
 it is not recommended for routine replacement therapy (risk of
cardiotoxicity)
Liothyronine Na (L-T3) Tab.,Inj
 Hypothyroidism (myxedema when severe) due to iodine deficiency
25
Antithyroid drugs
 Antithyroid drugs inhibit the function of the thyroid gland and
are used in hyperthyroidism (Graves' disease, toxic adenoma)
 These drugs include:
 Thiourea (thioamide) compounds, e.g., propylthiouracil,
methimazole, carbimazole
 Ionic inhibitors, e.g. , potassium percholate, potassium
thiocyanate
 Iodide, e.g. , Lugol’s iodine, potassium iodide; and,
 Radioactive iodine (131I)
26
27
Antithyroid drugs……
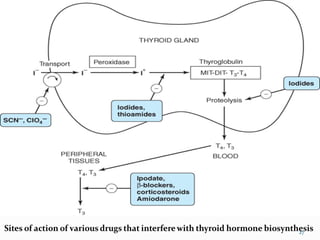
Thiourea Compounds (propylthiouracil, methimazole, carbimazole)
 Reduce formation of thyroid hormone by:
 Inhibit oxidation and organifiction of iodine
 Inhibit coupling of iodotyrosines to form T4 and T3
 Propylthiouracil also inhibits peripheral conversion of T4 to T3 (used
in thyroid storm)
 well absorbed from the GIT, but they have short t1/2 & slow in onset
 Carbimazole is rapidly converted to methimazole
 Both methimazole and PTU cross the placenta and also appear in the
milk, but less with PTU
Toxicities include:
 drug fever; skin rashes; cholestatic jaundice and, agranulocytosis
Pregnancy
 Use smallest possible amount of these drugs (PTU)-first trimester, then
methimazole for the remainder of the pregnancy
 overtreatment causes foetal goiter
 Breast feeding:- Propylthiouracil is the drug of choice
28
Antithyroid drugs……
Ionic Inhibitors
 Potassium perchlorate prevents the synthesis of
thyroid hormones through inhibition of uptake and
concentration of iodide by the gland
 It has the risk of aplastic anemia, therefore is no
longer used in the treatment of hyperthyroidism
29
Antithyroid drugs……
Iodides (Lugol’s iodine, potassium iodide)
 In pharmacologic doses (>6 mg/d), the major action of iodides is:
 to inhibit hormone release, possibly through inhibition of thyroglobulin
proteolysis
 Improvement in thyrotoxic symptoms occurs rapidly—within 2–7 days—
hence in thyroid storm
 In addition, iodides decrease the vascularity, size, and fragility of a
hyperplastic gland
 making the drugs valuable as preoperative preparation for surgery
ADRs
• Allergic reactions (angio-oedema, rashes, drug fever, lacrimation,
conjunctivitis), pain in the salivary glands
 Chronic use in pregnancy avoided →fetal goiter.
30
Antithyroid drugs……
Radioactive Iodine:
 It is used orally in hyperthyroidism as sodium 131I.
 It is trapped and concentrated as ordinary iodine, which emits beta
rays that act on parenchymal cells of the gland
 Used in diffuse toxic goiter (Thyrotoxicosis / Grave’s disease),
toxic nodular goiter, thyroid carcinoma
 It is contraindicated in pregnancy and lactation as it affects
thyroid gland in the fetus and the infant
 Its important toxicity is hypothyroidism
31
Antithyroid drugs……
Role of β- adrenergic blocker (Propranolol)
 This is an important drug which controls the peripheral
manifestations of hyperthyroidism (tachycardia,
tremor)
 In addition, it decreases the peripheral conversion of T4 to T3
Treatment of Thyroid Storm
 Life-threatening emergency
 Large amount of hormone into circulation occurs in
untreated or incompletely treated patient
 Management consists of:
 infusion of intravenous fluids, supportive management,
 administration of propylthiouracil, sodium iodide,
hydrocortisone, and propranolol
32
OXYTOCICS
 These are group of drugs that cause contraction of the uterus
 They include
 Oxytocin
 Prostaglandins
 Ergometrine
Oxytocin
• Oxytocin is a peptide hormone secreted by the posterior pituitary
Actions:
1. Oxytocin stimulates the uterus and cause physiologic type of
contraction
2. It also causes ejection of milk through contraction of the myo-
epithelial cells around the alveoli of the mammary gland
33
Pharmacokinetics:
 It is inactivated orally and absorbed rapidly after
intramuscular administration
 It can also be absorbed from the nasal and buccal
membranes
 Oxytocin is administered intravenously for initiation and
augmentation of labor
 It also can be administered intramuscularly for control of
postpartum bleeding
Use:
 Induction of labor in women with uterine inertia
 relief of breast engorgement during lactation (few
minutes before breast feeding) as nasal spray; and,
 postpartum hemorrhage
34
Side effect:
 Oxytocin may cause over stimulation and leads to rupture
of the uterus in the presence of cephalo-pelvic
disproportion
 Therefore it’s contraindicated in woman with a uterine scar
 High concentrations can cause excessive fluid retention, or
water intoxication, leading to hyponatremia, heart failure,
seizures, and death
35
Prostaglandins
 They induce labor at anytime during pregnancy but are most
effective at the third trimester
 In female reproductive system:
 prostaglandin E & F are found in ovaries, endometrium
and menstrual fluid which are responsible for initiating
and maintaining the normal birth process
 PGF2ά, and PGE stimulate both the tone and amplitude of
the uterine contraction
36
37
 dinoprostone (PGE2) has been used as an alternative to
oxytocin for the induction of labor
 misoprostol (PGE1)is an effective agent for both cervical
ripening and labor induction
Adverse reaction:
 nausa; vomiting; headache; diarrhea; and, fever etc.
PGs should be used cautiously in the presence of
hypo/hypertension, angina, and diabetes
 They are contraindicated in the presence of cardiac,
pulmonary (PGF2ά,) or hepatic disease
38
Ergometrine
• This is one of the ergot alkaloids which has the
ability to cause contraction of the uterine smooth
muscle
• It causes sustained uterine contraction
• It is completely absorbed after subcutaneous, and
intravenous administration
• It is metabolized in the liver and eliminated in the
urine
• Liver damage enhances the toxicity of ergot alkaloid
39
Use:
 After delivery of placenta if bleeding is severe (prevent
postpartum bleeding)
Adverse effect:
• Nausea and vomiting
• hypertension, headache, and possible seizures
Contraindications
• pregnancy, and a history of a cerebrovascular accident or
hypertension
ADRENOCORTICAL (steroidal)HORMONES
 The natural adrenocortical hormones are steroid molecules
(hormones) produced and released by the adrenal cortex
 These hormones are classified into:
 Sex Hormone – Estrogen, progesterone
- Androgen
 Glucocorticoid – Cortisone, hydrocortisone(Cortisol)
 Mineralocorticoid - Aldosterone
40
Sexual Hormones
 Female Sex Hormones
Estrogens
Progestrones
• Male Sex Hormones
Testosterone
5α-dihydrotestosterone
41
Female Sex Hormones
ESTROGENS:
can be classified into:
1. Natural – estradiol, esterone, estriol
2. Synthetic – Ethnylestradiol, mestranol, stilbestrol,
diethylstilbestrol, Methallenestril, etc
Ovary is the major site of estrogen synthesis in non
pregnant & premenopausal women
• Gonadotrophin-releasing hormone, released from the
hypothalamus, acts on the anterior pituitary to release FSH and LH
• FSH and LH stimulate follicle development in the ovary
FSH is the main hormone stimulating estrogen release 42
ESTROGENS…..
 In pregnant women, the feto-placental unit is the major source
of estrogens
 Peripheral sites of estrogen synthesis includes:
- Liver, kidney, brain, adipose tissue, testis
- Accounts for estrogen in postmenopausal women
 In postmenopausal women, ovarian steroid synthesis declines
and peripheral estrogen biosynthesis accounts for all estrogen
produced
 both in postmenopausal women and in males
43
Pharmacokinetics
 Naturally occurring estrogens: are readily absorbed through
the GIT, skin, and mucous membranes
 Taken orally, estradiol is rapidly metabolized (and partially
inactivated) by the liver
 Synthetic estrogen analogs: such as ethinyl estradiol and
mestranol, are well absorbed after oral administration or
through the skin or mucous membranes
 They have a prolonged action and a higher potency
compared to those of natural estrogens
44
MOA & Physiologic Effects of Estrogen
Binding to nuclear receptors and cause subsequent genomic
effects-either gene transcription (i.e. DNA-directed RNA and
protein synthesis) or gene repression
This results in the synthesis of specific proteins that mediate
a number of physiologic functions:
Physiologic Effects
 Stimulate the development of the vagina, uterus, and uterine
tubes as well as the secondary sex characteristics
 Ovary: estrogen affects the ovary through indirectly
influencing the secretion of gonadotrophin (FSH,LH)
 Uterus: it affects the ‘proliferative phase’ of the endometrium
and also increases the growth and sensitivity of myometrium for
oxytocin 45
Physiologic Effects …….
 When used with progesterone, it causes regular periodic bleeding
and shedding of the endometrial lining
 Cervix: it makes cervical mucus thin and alkaline
 Breast: estrogen causes the growth of gland and duct system
 Anterior pituitary: estrogen inhibit release of gonadotropins
(FSH, LH)
Others
 Retention of salt and water & increases Catt bone deposition
 Increase blood coagulation
They are responsible for estrous behavior in animals and may
influence behavior and libido in humans
stimulate development of pigmentation in the skin ( nipples and
areolae and in the genital region)
46
Therapeutic use:
• Contraceptive in combination with progestogens
• Functional uterine bleeding
• Dysmenorrhea (a pain during menstruation)
• Alleviation of menopausal disorder
• Osteoporosis
• Replacement therapy in ovarian failure
• Prevents atrophic vaginitis
Side effect:
 Thromboembolism, sodium and water retention,
withdrawal bleeding, nausea, endometrial carcinoma
Contraindication:
 History of thromboembolism, indiagnosed uterine
bleeding, endometrial carcinoma, liver disease
47
SELECTIVE ESTROGEN RECEPTOR MODULATORS (SERMS)
SERMs: Tamoxifen, Raloxifene, and Toremifene
 are compounds with tissue-selective actions
 These drugs are to produce:
 beneficial estrogenic actions in certain tissues (e.g., bone, brain, and
liver) during postmenopausal hormone therapy
 but antagonist activity in tissues such as breast and endometrium,
where estrogenic actions (e.g., carcinogenesis) might be deleterious
 Tamoxifen and toremifene are used for treatment of breast
cancer
 Both approved for t/t of metastatic breast cancer in
postmenopausal women
 Raloxifene is used primarily for prevention and treatment of
osteoporosis
48
Anti-Estrogens: Clomiphene
 By interfering with the negative feedback effect of estrogens on
the hypothalamus,
 clomiphene increases the secretion of gonadotropin-
releasing hormone and gonadotropins (FSH & LH),
→stimulation of ovulation
 The drug has been used successfully to treat infertility
associated with anovulatory cycles,
 but it is not effective in women with ovulatory dysfunction
due to pituitary or ovarian failure
Adverse
 headache, nausea, vasomotor flushes, visual disturbances, and
ovarian enlargement
49
The natural progestational hormone (progestogen) is
progesterone
 This is secreted by the corpus luteum in the second part
of the menstrual cycle, and by the placenta during
pregnancy.
 Small amounts are also secreted by testis and adrenal cortex
There are two main groups of progestogens
 The naturally occurring hormone and its derivatives
 e.g. hydroxyprogesterone, medroxyprogesterone
 Testosterone derivatives
 (e.g. Norethindrone, norgestrel and ethynodiol) can be given
orally
 Newer progestogens used in contraception include desogestrel
and gestodene
50
PROGESTRONES
Pharmacokinetics
 Progesterone is rapidly absorbed following administration by any
route
 Its half-life in the plasma is approximately 5 minutes
 It is almost completely metabolized in one passage through the
liver, and for that reason it is quite ineffective when given orally
 Synthetic progestins are less rapidly metabolized
 Medroxyprogesterone acetate IM has a duration of action of 3
months
 The other progestins last from 1 to 3 days
MOA
 Progestins enter the cell and bind to progesterone receptors
that are distributed between the nucleus and the cytoplasm →
activate gene transcription 51
Physiological and Pharmacological Actions
 Ovary: inhibition of ovulation
 has negative feedback effects on both hypothalamus and
anterior pituitary
 Uterus: decrease estrogen-driven endometrial proliferation and
leads to the development of a secretory endometrium
 and makes the myometrum less sensitive to oxytocin
 Cervix- cause the endocervical glands secrete a scant viscid
(thick) mucus
 Progesterone suppresses menstruation and uterine contractility
52
Physiological and Pharmacological Actions….
 Progesterone has depressant and hypnotic effects on the brain
 Metabolic actions:
 Thermogenic action, inhibits sodium reabsorption
Therapeutic use:
 Hormonal contraception
 Combined with estrogen for estrogen replacement therapy in
women with an intact uterus, to prevent endometrial hyperplasia
and carcinoma
 Premenustral tension
unwanted effects
 acne, fluid retention, weight change, depression, change in
libido, breast discomfort, irregular menstrual cycles and
breakthrough bleeding, thromboembolism
53
ANTIPROGESTOGENS
Mifepristone
 is a partial agonist at progesterone receptors
 It sensitizes the uterus to the action of prostaglandins
 It is given orally and has a plasma half-life of 21 hours
 Mifepristone is used, in combination with a prostaglandin
(e.g. gemeprost (PGE1)), as a medical alternative to
surgical termination of pregnancy
54
ORAL CONTRACEPTIVEs
 These are drugs taken orally to prevent conception
Types of hormonal contraceptives include:
1. Combination Oral Contraceptives (combinations of
estrogens and progestins)
a. monophasic forms (constant dosage of both components
during the cycle)
b. biphasic or triphasic forms (dosage of one or both
components is changed once or twice during the cycle)
2. Progestin-Only Contraceptives
3. Postcoital or Emergency Contraceptives
55
1. Combination Oral Contraceptives (COCs)
 COCs are available in many formulations.
Monophasic contains fixed amounts of the estrogen and progestin,
which is taken daily for 21 days, followed by a 7-day "pill-free"
period
The biphasic and triphasic preparations provide 2 or 3 different pills
containing varying amounts of active ingredients, to be taken at
different times during the 21-day cycle
 Withdrawal bleeding occurs 2 to 3 days after discontinuation of this
regimen (during the 7-day "off" period each month)
 The estrogen in most combined preparations is ethinylestradiol
 The progestin may be norethindrone, levonorgestrel, desogestrel
or gestodene
56
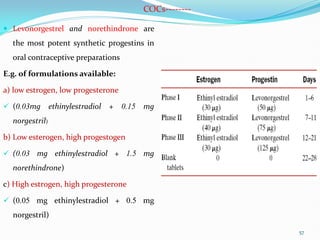
COCs--------
 Levonorgestrel and norethindrone are
the most potent synthetic progestins in
oral contraceptive preparations
E.g. of formulations available:
a) low estrogen, low progesterone
 (0.03mg ethinylestradiol + 0.15 mg
norgestril)
b) Low esterogen, high progestogen
 (0.03 mg ethinylestradiol + 1.5 mg
norethindrone)
c) High estrogen, high progesterone
 (0.05 mg ethinylestradiol + 0.5 mg
norgestril)
57
COCs--------
Their mode (mechanism)of action is as follows:
 Estrogen inhibits secretion of FSH via negative feedback on the
anterior pituitary and thus suppresses development of the
ovarian follicle
 Progestins inhibits secretion of LH and thus prevents
ovulation
 it also makes the cervical mucus less suitable for the passage of
sperm
 Estrogen and progestins act in concert to alter the
endometrium in such a way as to discourage implantation
58
COCs--------
Common adverse effects include:
 Increased incidence of thrombosis and embolism, attributed to
the estrogen component in particular
 Weight gain, owing to fluid retention or an anabolic effect or both
 mild nausea, flushing, dizziness, depression or irritability
 Skin changes (e.g. acne and/or an increase in pigmentation)
 Amenorrhea of variable duration on cessation of taking the pill
Contraindications:
 Oral contraceptives are C/I in the presence of cerebrovascular and
thromboembolic disease, estrogen-dependent neoplasms, liver disease,
and pregnancy
59
2.The progestogen-only contraceptives ("minipills")
• administered orally or by implantation under the skin
• suited for use in patients for whom estrogen administration is undesirable
Specific preparations include
 Low doses of progestins (e.g. 350 mg of norethindrone or 75 mg of
norgestrel) taken po daily without interruption
 Subdermal implants of levonorgestrel 216 mg (Norplant II) for slow
release and resultant long-term contraceptive action (e.g., up to 5 years)
 Crystalline suspensions of medroxyprogesterone acetate (Depo-
provera®) for IM injection of 150 mg of drug, which provides effective
contraception for 3 months
Side effects
 irregular bleeding episodes, headache, weight gain, and mood changes
60
3. Postcoital or Emergency Contraceptives ("morning after" pill)
 Pregnancy can be prevented following unprotected coitus by the
administration of high dose of estrogens alone or in combination with
progestins
 Plan B is an emergency contraceptive consisting of two tablets of the
progestin levonorgestrel (0.75 mg)
 Preven is two 2 pill doses of a high-dose oral contraceptive (0.25mg of
levonorgestrel and 0.05 mg of ethinyl estradiol per pill) separated by 12 hours
 The first dose of Plan B and Preven should be taken anytime within 72 hours
after intercourse, and this should be followed 12 hours later by a second dose.
 This t/t reduces the risk of px approximately 60% for Preven and 80% for
levonorgestrel alone (Plan B).
61
Postcoital or Emergency Contraceptives ("morning after" pill)…….
 Multiple mechanisms are likely to contribute to the efficacy of these
agents
• Some studies have shown that ovulation is inhibited or delayed,
but additional mechanisms thought to play a role include:
 alterations in endometrial receptivity for implantation
 interference with functions of the corpus luteum that maintain
pregnancy
 Production of cervical mucus that decreases sperm penetration
Adverse effects
 nausea or vomiting, headache, dizziness, breast tenderness, irregular
bleeding and abdominal and leg cramps
62
ADRENOCORTICAL HORMONES……
Glucocorticoids
 The important glucorticoid secreted in man is Cortisol
(hydrocortisone)
 It possesses some mineralocorticoid activity as well
 Cortisone is less potent and is converted to hydrocortisone
by the liver
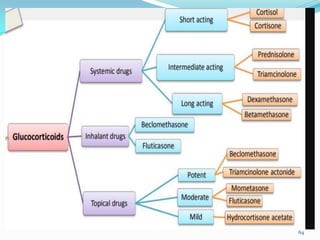
They are classified as
1. Short acting e.g cortisone ,hydrocortisone
2. Intermediate acting e.g. predinsolone, triamcinolone
3. Long acting e.g dexamethasone, betamethasone
63
64
ADRENOCORTICAL HORMONES……
 Dexamethasone and betamethasone have got a high
glucorticoid activity
 while cortisone and hydrocortisone have high
mineralocorticoid action
 Therapeutic activity in inflammatory disorder is
proportional to the glucocorticoid activity
Actions on CHO metabolism:
 antinsulinic effect
 Decreases peripheral utilization of glucose
 Increases gluconeogenesis
65
Protein metabolism:
 Inhibit protein synthesis,
 Increases catabolism
Fat metabolism:
 Interferes with fat storage causing deposits with
characteristic distribution (neck, visceral,
supraclavicular area, and face)
Electrolyte and H2O metabolism:
 Sodium and water retention------hypertension
 Hypokalemia
66
Other effects
 CNS: Euphoria and stimulation
 CVS: Restore vascular reactivity (hypertension)
 GIT: Peptic ulcer disease
Calcium metabolism:
 increased Ca++excretion, interfere with Ca++ absorption
67
Anti-Inflammatory and Immunosuppressive Effects
 Inhibits exudation, capillary dilatation, migration of phagocyte
& lymphocytes
 suppress effects on inflammatory cytokines and chemokines
and on other mediators of inflammation
Antiallergic:
 decrease capillary permeability by reducing the amount of
histamine released by basophils and mast cells.
68
Therapeutic use
1) Replacement therapy
 In Addisons disease
2) Anti-inflammatory
 In conditions like Collagen disease (rheumatoid carditis,
arthritis),
3) Hypersensitivity reactions
 Bronchial Asthma, status asthmaticus
 blood disease due to circulating antibodies (autoimmune
disease);
 eye disease (allergic inflammation of the eye);
 nephrotic syndrome; and, acute gout
4) Immunosuppression: In tissue / organ transplantation
69
5) Glucocorticoids such as
 Bethamethasone(12mg IM every 24 hrs for two doses)
 reduces the incidence of respiratory distress syndrome
in infants delivered prematurely
70
Precautions
 Check weight for fluid retention;
 Test urine for sugar;
 Follow blood pressure through measurement and check
bones by X-ray for osteoporosis;
 Doses should be tapered slowly (Don’t stop abruptly);
 Encourage diet rich in K+, protein and adequatecalcium,
low Nacl; and,
 Rule- out infection before initiation of treatment
71
Side effects:
Due to prolonged use:
 Weight gain and edema, hypokalmia; hyperglycemia;
osteoporosi, psychiatric disturbance; susceptibility to
infection (like TB);
 peptic ulceration; cushing syndrome(excessive production
of hydrocortisone); and, retarded growth
 Complication with rapid withdrawal results in
 adrenacortical insufficiency due to depression of adrenocortical
activity
72
Contraindication:
 They are contraindicated in patients with:
 peptic ulcer disease
 acute infection like active tuberculosis
 diabetes mellitus
 psychosis
 pregnancy
73
Mineralocorticoid
Aldosterone
 It is the main mineralocorticoid of the adrenal cortex.
 It increases absorption of Na+ at the distal tubule and
increases K+ excretion.
 They are not widely used in therapeutics
74