





























































Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 1
EMERGENCY DEPARTMENT
EXCELLENCE MANUAL
Global Standards for Emergency Care Excellence, Patient Safety, and Quality Healthcare
A Comprehensive Reference for
THE MULTIDISCIPLINARY EMERGENCY DEPARTMENT TEAM
Emergency Physicians • Triage & Emergency Nurses • Trauma Teams • ED Technicians, Pharmacists & Allied
Emergency Care Professionals
“The Door Never Closes, the Clock Never Stops — Every Second in the Emergency Department
Is a Decision That Shapes a Life.”
Dr J L Meena
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 2
DEDICATION
This book is dedicated to all those who are committed to advancing healthcare through speed, precision,
courage, and compassion for the stranger who walks through the door in their worst moment.
To the Patients
For whom every second counted in triage, every rapid diagnosis made under pressure, and every resuscitation
fought for without hesitation represents the difference between survival and loss — often decided before their
name is even fully known.
To My Family
For their unwavering love, patience, and encouragement, which have been the foundation of this journey.
To My Mentors & Teachers
For inspiring my passion, guiding my path, and instilling in me the value of speed without recklessness, and
calm without complacency.
To My Colleagues & Friends
For their support, collaboration, and shared dedication to a department that never closes and never turns
away.
To Every Member of the Emergency Department Team
Physicians, nurses, technicians, and every professional who works the unpredictable, relentless hours of
emergency care — who must be ready for anything, at any moment, for anyone who arrives — the frontline
where healthcare's promise to never turn a patient away is kept, second by second, all day and all night.
Your dedication, speed, and unwavering readiness are the silent pillars of a healthcare system that never
closes its doors. This book is for you, and because of you. Thank you to everyone who has been a part of
this journey
Dr J L Meena
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 3
FOREWORD
There is no other department in a hospital where a stranger can arrive, unannounced, at any hour, in any
condition, and be met not with a scheduling system but with an unconditional promise: we will assess you, we
will act, and we will not turn you away. The chest pain that could be a heart attack or could be anxiety, assessed
correctly within minutes. The trauma patient wheeled in from a road accident, whose survival depends on a
coordinated team acting in the first hour without a single wasted movement. The septic patient who looks
stable until, quite suddenly, they are not. The overdose, the stroke, the child with a fever that could be nothing
or could be everything — all of it arrives through the same door, at the same time, with no advance warning,
and the Emergency Department must be ready for every possibility, simultaneously, every single day.
The “Emergency Department Excellence Manual: Global Standards for Emergency Care Excellence, Patient
Safety, and Quality Healthcare” has been developed to provide a comprehensive professional framework for
the multidisciplinary Emergency Department team — emergency physicians, triage and emergency nurses,
trauma teams, and allied emergency care professionals — working together in the one department of the
hospital defined by its unconditional obligation to receive, assess, and treat every patient who arrives,
regardless of the hour, the diagnosis, or the resources available at that moment.
This manual brings together internationally recognized principles of triage and rapid assessment, resuscitation
and trauma care, time-sensitive treatment protocols (stroke, myocardial infarction, sepsis), mass casualty and
disaster response, ED overcrowding and boarding management, psychiatric and behavioural emergency care,
medico-legal documentation, infection control in the emergency setting, and continuous quality improvement
specific to emergency medicine. It is built around globally accepted accreditation standards — NABH, JCI, WHO
emergency care guidelines, and international emergency medicine society protocols — to provide a rigorous,
regulation-compliant framework for emergency department excellence.
The chapters of this manual guide the Emergency Department team through every dimension of the role —
from the moment of arrival and triage, through resuscitation, rapid diagnosis, and time-critical treatment, to
disposition, handover, and the professional conduct that defines excellence across every category of
emergency presentation: medical, surgical, trauma, obstetric, paediatric, and psychiatric.
The Emergency Department is not simply the hospital's front door — it is the place where the sickest, most
unpredictable, most time-critical patients in the entire healthcare system are received without appointment,
without warning, and without the luxury of complete information, and where the team's speed, judgment, and
coordination determine outcomes that will be decided, irreversibly, within the first minutes and hours. Their
work happens under a unique and unrelenting pressure: they must be ready for the worst possible case, for
every patient, every time, because they cannot know in advance which patient that will be.
It is hoped that this manual will serve as an indispensable resource for Emergency Physicians, Triage and
Emergency Nurses, Trauma Team Leaders, ED Technicians, hospital administrators, quality heads, and all those
committed to building a healthcare system where emergency care is delivered with the speed, precision,
accountability, and compassion that quality healthcare, at its most urgent, demands.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 4
“The Door Never Closes, the Clock Never Stops — Every Second in the Emergency Department Is a
Decision That Shapes a Life.”
With Best Wishes, Dr J L Meena
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 5
TABLE OF CONTENTS
FOREWORD............................................................................................................................................3
LIST OF ABBREVIATIONS........................................................................................................................7
MANUAL MOTTO...................................................................................................................................9
CHAPTER 1: Introduction.....................................................................................................................10
Purpose...........................................................................................................................................................10
Objectives .......................................................................................................................................................11
Vision & Mission .............................................................................................................................................13
CHAPTER 2: Role of the Emergency Department in Quality Healthcare............................................14
Triage & Rapid Assessment.............................................................................................................................14
Resuscitation & Trauma Care .........................................................................................................................14
Time-Sensitive Treatment Protocols (Stroke, MI, Sepsis)...............................................................................15
ED Overcrowding & Boarding Management...................................................................................................15
Mass Casualty & Disaster Response ...............................................................................................................16
Psychiatric & Behavioural Emergency Care ....................................................................................................16
Medico-Legal Documentation & Reporting....................................................................................................17
Disposition, Handover & Care Transitions......................................................................................................17
CHAPTER 3: Professional Standards for the Emergency Department Team......................................18
Professional Appearance & Behaviour ...........................................................................................................18
Communication Standards .............................................................................................................................19
Confidentiality & Information Security...........................................................................................................20
Ethical Standards ............................................................................................................................................20
Time Management, Teamwork & Continuous Learning.................................................................................21
CHAPTER 4: Patient- and Family-Centered Communication in the ED ..............................................22
The A-T-C-R-C Communication Model............................................................................................................22
Breaking Bad News & Communicating Under Pressure..................................................................................23
CHAPTER 5: Patient Safety and Emergency Care Standards ..............................................................25
The R-T-A-C-A Framework ..............................................................................................................................25
Daily Quality Standards Checklist ...................................................................................................................27
CHAPTER 6: Confidentiality, Privacy, and Information Security ........................................................29
Privacy in the Open ED Environment..............................................................................................................29
Cybersecurity of ED Information Systems ......................................................................................................30
CHAPTER 7: Standard Operating Procedures (SOPs)..........................................................................32
SOP 1: Triage and Acuity Classification...........................................................................................................32
SOP 2: Resuscitation (Code Blue/Cardiac Arrest) ...........................................................................................32
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 6
SOP 3: Major Trauma Team Activation...........................................................................................................33
SOP 4: Acute Stroke Protocol (Door-to-Needle).............................................................................................33
SOP 5: Acute Myocardial Infarction Protocol (Door-to-Balloon) ....................................................................34
SOP 6: Sepsis Recognition and Bundle in the ED ............................................................................................34
SOP 7: Mass Casualty Incident Activation.......................................................................................................35
SOP 8: Psychiatric Emergency and Violence De-Escalation ............................................................................35
SOP 9: ED-to-Ward/ICU Handover and Boarding Management.....................................................................36
SOP 10: Medico-Legal Case Documentation...................................................................................................36
CHAPTER 8: Communication with Special Groups..............................................................................38
CHAPTER 9: Handling Difficult Situations ...........................................................................................41
CHAPTER 10: Emergency Response — Critical Presentations in the ED.............................................45
CHAPTER 11: Digital Competency for the Emergency Department ...................................................48
CHAPTER 12: Daily Emergency Department Checklist........................................................................50
CHAPTER 13: Key Performance Indicators (KPIs)................................................................................52
CHAPTER 14: Top 20 Do's & Top 20 Don'ts.........................................................................................55
CHAPTER 15: Emergency Department Professional Pledge ...............................................................58
CONCLUSION........................................................................................................................................62
REFERENCES.........................................................................................................................................64
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 7
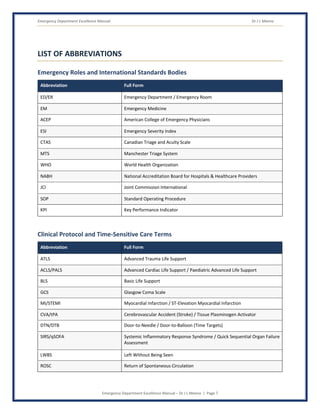
LIST OF ABBREVIATIONS
Emergency Roles and International Standards Bodies
Abbreviation Full Form
ED/ER Emergency Department / Emergency Room
EM Emergency Medicine
ACEP American College of Emergency Physicians
ESI Emergency Severity Index
CTAS Canadian Triage and Acuity Scale
MTS Manchester Triage System
WHO World Health Organization
NABH National Accreditation Board for Hospitals & Healthcare Providers
JCI Joint Commission International
SOP Standard Operating Procedure
KPI Key Performance Indicator
Clinical Protocol and Time-Sensitive Care Terms
Abbreviation Full Form
ATLS Advanced Trauma Life Support
ACLS/PALS Advanced Cardiac Life Support / Paediatric Advanced Life Support
BLS Basic Life Support
GCS Glasgow Coma Scale
MI/STEMI Myocardial Infarction / ST-Elevation Myocardial Infarction
CVA/tPA Cerebrovascular Accident (Stroke) / Tissue Plasminogen Activator
DTN/DTB Door-to-Needle / Door-to-Balloon (Time Targets)
SIRS/qSOFA Systemic Inflammatory Response Syndrome / Quick Sequential Organ Failure
Assessment
LWBS Left Without Being Seen
ROSC Return of Spontaneous Circulation
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 8
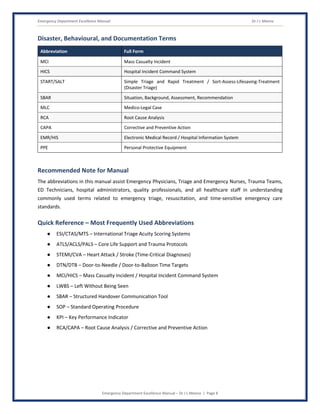
Disaster, Behavioural, and Documentation Terms
Abbreviation Full Form
MCI Mass Casualty Incident
HICS Hospital Incident Command System
START/SALT Simple Triage and Rapid Treatment / Sort-Assess-Lifesaving-Treatment
(Disaster Triage)
SBAR Situation, Background, Assessment, Recommendation
MLC Medico-Legal Case
RCA Root Cause Analysis
CAPA Corrective and Preventive Action
EMR/HIS Electronic Medical Record / Hospital Information System
PPE Personal Protective Equipment
Recommended Note for Manual
The abbreviations in this manual assist Emergency Physicians, Triage and Emergency Nurses, Trauma Teams,
ED Technicians, hospital administrators, quality professionals, and all healthcare staff in understanding
commonly used terms related to emergency triage, resuscitation, and time-sensitive emergency care
standards.
Quick Reference – Most Frequently Used Abbreviations
● ESI/CTAS/MTS – International Triage Acuity Scoring Systems
● ATLS/ACLS/PALS – Core Life Support and Trauma Protocols
● STEMI/CVA – Heart Attack / Stroke (Time-Critical Diagnoses)
● DTN/DTB – Door-to-Needle / Door-to-Balloon Time Targets
● MCI/HICS – Mass Casualty Incident / Hospital Incident Command System
● LWBS – Left Without Being Seen
● SBAR – Structured Handover Communication Tool
● SOP – Standard Operating Procedure
● KPI – Key Performance Indicator
● RCA/CAPA – Root Cause Analysis / Corrective and Preventive Action
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 9
MANUAL MOTTO
“The Door Never Closes,”
“The Clock Never Stops —”
“Every Second Is a Decision That Shapes a Life.”
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 10
CHAPTER 1: INTRODUCTION
1. Purpose
No other department in a hospital carries the Emergency Department's unconditional obligation: to receive
every patient who arrives, at any hour, in any condition, with no advance notice and often no complete
information, and to correctly separate within minutes those who can safely wait from those who will die
without immediate intervention. The chest pain that is a heart attack in one patient and indigestion in the next.
The trauma patient whose survival depends on a coordinated team acting within the first hour. The septic
patient who appears stable until, in the span of minutes, they are not. The stroke patient whose treatment
window closes forever after a matter of hours. Every one of these presentations arrives through the same door,
often simultaneously, and the Emergency Department must be ready for all of them, every day, without
exception.
The World Health Organization and the American College of Emergency Physicians recognize emergency care
as a foundational pillar of any functioning health system — the point at which time-critical intervention most
directly determines survival, and where systematic triage, rapid diagnosis, and protocolized time-sensitive
treatment are more powerfully evidence-linked to patient outcomes than in almost any other area of medicine.
Research consistently demonstrates that structured triage systems, protocolized stroke and myocardial
infarction pathways, and disciplined sepsis recognition bundles in the emergency setting produce dramatically
and measurably better patient survival than unstructured, ad hoc emergency response. In institutions where
the Emergency Department applies rigorous triage, time-sensitive protocol adherence, and coordinated
trauma and resuscitation response, patient survival and functional outcomes are demonstrably better. The
investment in Emergency Department excellence is, without qualification, one of the highest-yield investments
any healthcare system can make in the survival of patients whose care cannot wait.
Why the Emergency Department Is Critical to Healthcare Quality
● Provides the unconditional first point of access to emergency care for every patient, regardless of
ability to pay or time of arrival.
● Applies systematic triage that ensures the sickest patients are identified and treated first, not merely
in order of arrival.
● Delivers resuscitation and trauma care within the critical first minutes and hours where outcomes are
most decisively shaped.
● Implements time-sensitive treatment protocols (stroke, myocardial infarction, sepsis) where minutes
directly determine survival and disability.
● Manages mass casualty and disaster response, coordinating the hospital's front-line reception of
sudden, overwhelming demand.
● Recognizes and manages psychiatric and behavioural emergencies safely, for both patients and staff.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 11
● Maintains rigorous medico-legal documentation for cases with legal, forensic, or reportable public
health implications.
● Maintains regulatory compliance with national emergency care standards and international
accreditation guidelines.
● Contributes to accreditation compliance (NABH, JCI) for emergency and urgent care standards.
Key Responsibilities of the Emergency Department
● Conducting systematic triage and acuity classification for every patient immediately upon arrival.
● Providing immediate resuscitation and stabilization for critically ill and injured patients.
● Applying time-sensitive protocols for stroke, myocardial infarction, and sepsis without delay.
● Leading major trauma team activation and coordinated trauma resuscitation.
● Managing ED overcrowding and boarding to protect patient safety during periods of high demand.
● Activating and coordinating mass casualty incident response.
● Managing psychiatric emergencies and workplace violence risk safely.
● Coordinating safe, structured handover to inpatient, ICU, or other receiving services.
● Maintaining rigorous medico-legal case documentation and statutory reporting.
● Engaging in continuous professional development to maintain competence in evolving emergency
medicine evidence.
2. Objectives
1. Ensure Rapid, Accurate Triage for Every Patient
Every patient arriving at the Emergency Department must be assessed and prioritized accurately and
immediately. This is the ED's primary patient safety obligation.
How to Achieve:
● Apply a validated, standardized triage acuity scale (ESI, CTAS, MTS, or equivalent) consistently to every
patient.
● Conduct triage reassessment at defined intervals for patients awaiting further care.
● Identify and immediately escalate any patient whose condition changes while awaiting assessment.
2. Deliver Time-Sensitive Treatment Within Evidence-Based Windows
● Apply protocolized stroke, myocardial infarction, and sepsis pathways consistently, without exception.
● Monitor and continuously improve door-to-needle, door-to-balloon, and sepsis bundle compliance
times.
● Escalate immediately any barrier delaying time-critical treatment.
3. Provide Coordinated, Rapid Trauma and Resuscitation Response
● Maintain a trained, rehearsed trauma team activation protocol.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 12
● Apply systematic primary and secondary survey methodology (ATLS or equivalent) to every trauma
patient.
● Maintain continuous resuscitation readiness (equipment, medications, team availability).
4. Manage Overcrowding and Capacity Proactively
● Monitor ED boarding and overcrowding indicators continuously.
● Apply escalation protocols before overcrowding compromises patient safety.
● Coordinate proactively with hospital operations for bed availability and patient flow.
5. Maintain Disaster and Mass Casualty Readiness
● Maintain a current, tested mass casualty incident response plan.
● Apply standardized disaster triage methodology (START/SALT or equivalent).
● Participate regularly in disaster simulation and readiness training.
6. Maintain Regulatory and Accreditation Compliance
● Comply with national emergency care standards and international accreditation guidelines.
● Maintain NABH/JCI emergency and urgent care documentation standards.
● Participate in accreditation surveys with complete, auditable emergency care records.
3. Vision
Vision Statement
“To build and maintain an Emergency Department where every patient is triaged accurately and immediately,
every time-critical treatment begins within its evidence-based window, every trauma and resuscitation is met
with coordinated readiness, and no patient is ever harmed by a preventable delay, misclassification, or
coordination failure.”
4. Mission
Mission Statement
“To deliver safe, rapid, evidence-based, and compassionate emergency care that protects patients from harm
through systematic triage, time-sensitive protocol adherence, and coordinated trauma and resuscitation
response, while maintaining regulatory compliance and enabling the healthcare organization to provide quality
emergency care with confidence in its readiness for any patient, at any moment.”
Expected Outcomes of an Excellent Emergency Department Practice
● 100% of patients triaged using a validated acuity scale within the institutionally defined timeframe of
arrival.
● Door-to-needle time for stroke and door-to-balloon time for STEMI maintained within international
benchmark targets.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 13
● Sepsis bundle compliance within the defined time-sensitive treatment window for 100% of recognized
cases.
● ED boarding time maintained at or below institutional/national benchmark.
● Mass casualty and disaster response plans tested and verified functional per regular schedule.
● Complete, accurate, and NABH/JCI-compliant emergency care documentation.
● All significant emergency care incidents investigated with documented RCA and CAPA.
● Full compliance with national emergency care standards and international accreditation guidelines.
The Emergency Department is the one place in healthcare where the promise to never turn a patient away
is tested every single day, against every possible presentation, without warning. Their triage accuracy is
the first and most consequential safety decision in a patient's entire hospital journey, their time-sensitive
protocol discipline is what stands between treatable disease and permanent disability, and their readiness
for the unexpected is what a community depends upon when there is nowhere else to turn.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 14
CHAPTER 2: ROLE OF THE EMERGENCY DEPARTMENT IN QUALITY
HEALTHCARE
1. Triage and Rapid Assessment
Overview
Triage is the single most consequential safety decision in a patient's emergency care journey — the systematic
process by which the sickest patients are identified within minutes of arrival, before a complete diagnostic
workup is even possible.
Responsibilities
● Apply a validated, standardized triage acuity scale (ESI, CTAS, MTS, or institutional equivalent)
consistently to every patient upon arrival.
● Conduct systematic reassessment at defined intervals for patients awaiting further evaluation.
● Identify and immediately escalate any patient whose condition deteriorates while awaiting care.
● Apply rapid, focused assessment to distinguish immediately life-threatening presentations from stable
ones.
2. Resuscitation and Trauma Care
Overview
Resuscitation and trauma care represent the Emergency Department's most time-critical clinical function,
where coordinated team action within the first minutes and hours most decisively shapes survival and long-
term outcome.
Responsibilities
● Maintain continuous resuscitation readiness, including equipment, medication, and trained personnel
availability.
● Apply systematic primary and secondary survey methodology (ATLS or equivalent) to every trauma
patient.
● Lead coordinated, rehearsed trauma team activation and resuscitation response.
● Apply current advanced life support (ACLS/PALS) protocols for cardiac and respiratory arrest.
3. Time-Sensitive Treatment Protocols (Stroke, MI, Sepsis)
Overview
Stroke, myocardial infarction, and sepsis represent the clearest examples in all of medicine where minutes of
delay directly and measurably increase mortality and permanent disability.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 15
Responsibilities
● Apply protocolized acute stroke pathways, minimizing door-to-needle time for eligible thrombolysis
candidates.
● Apply protocolized STEMI pathways, minimizing door-to-balloon time for percutaneous intervention.
● Apply systematic sepsis screening and implement time-sensitive sepsis bundles immediately upon
recognition.
● Monitor and continuously improve time-to-treatment metrics for every time-sensitive protocol.
4. ED Overcrowding and Boarding Management
Overview
Emergency department overcrowding and inpatient boarding are directly and measurably associated with
increased mortality, medical error, and patient dissatisfaction — making capacity management a core patient
safety function, not merely an operational concern.
Responsibilities
● Monitor ED census, boarding time, and overcrowding indicators continuously.
● Apply defined escalation protocols before overcrowding compromises patient safety.
● Coordinate proactively with hospital operations and bed management for patient flow.
● Prioritize the safety of boarded patients through continued monitoring and care, not merely holding.
5. Mass Casualty and Disaster Response
Overview
The Emergency Department is the front-line reception point for mass casualty and disaster events, requiring
rapid, coordinated capacity expansion and standardized disaster triage methodology.
Responsibilities
● Maintain a current, tested mass casualty incident response plan integrated with the Hospital Incident
Command System.
● Apply standardized disaster triage methodology (START/SALT or institutional equivalent) during mass
casualty events.
● Participate regularly in disaster simulation and readiness training.
● Coordinate rapid capacity expansion and resource mobilization during surge events.
6. Psychiatric and Behavioural Emergency Care
Overview
Psychiatric and behavioural emergencies require specialized assessment and de-escalation skill, protecting
both patient safety and staff safety in an inherently unpredictable clinical situation.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 16
Responsibilities
● Apply structured risk assessment for suicidal ideation, self-harm, and violence risk.
● Apply verbal de-escalation techniques as the first-line response to agitation.
● Ensure appropriate environmental safety measures for patients at risk of self-harm or violence.
● Coordinate timely psychiatric consultation and appropriate disposition.
7. Medico-Legal Documentation and Reporting
Overview
Emergency department cases frequently carry legal, forensic, or statutory reporting implications, requiring
rigorous, defensible documentation practice.
Responsibilities
● Maintain complete, contemporaneous, and legally defensible documentation for every medico-legal
case.
● Apply correct evidence preservation and chain-of-custody procedures where applicable.
● Fulfil statutory reporting obligations (assault, abuse, notifiable disease, and equivalent) accurately and
promptly.
8. Disposition, Handover, and Care Transitions
Overview
The transition from Emergency Department care to inpatient admission, transfer, or discharge is a period of
continued vulnerability requiring structured, complete communication.
Responsibilities
● Apply structured handover communication (SBAR or equivalent) for every admission, transfer, or
significant disposition.
● Provide clear, complete discharge instructions and safety-netting advice for discharged patients.
● Coordinate follow-up arrangements for patients requiring ongoing outpatient management.
How the Emergency Department Contributes to Quality Healthcare
● By applying systematic triage, the ED ensures the sickest patients are identified and treated first,
regardless of arrival order.
● By delivering rapid resuscitation and trauma care, the ED shapes outcomes in the most decisive
minutes and hours of critical illness and injury.
● By applying time-sensitive protocols, the ED prevents the permanent disability and death that delay in
stroke, MI, and sepsis treatment directly causes.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 17
● By managing overcrowding proactively, the ED prevents the measurable harm associated with
boarding and capacity strain.
● By maintaining disaster readiness, the ED ensures the healthcare system can absorb sudden,
overwhelming demand without collapse.
● By managing psychiatric emergencies safely, the ED protects both vulnerable patients and the staff
caring for them.
The Emergency Department is where healthcare's promise of unconditional access is tested every day —
their triage accuracy is the first and most consequential safety decision a patient encounters, their time-
sensitive protocol discipline stands between treatable disease and permanent disability, and their
coordinated readiness is what an entire community depends upon in its most urgent moments.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 18
CHAPTER 3: PROFESSIONAL STANDARDS FOR THE EMERGENCY
DEPARTMENT TEAM
Emergency medicine practice requires an uncommon combination of rapid clinical judgment under
uncertainty, sustained composure through unpredictable and often chaotic conditions, genuine team
coordination across multiple simultaneous critical presentations, and unwavering commitment to the
unconditional obligation to treat every patient who arrives. The standards that govern Emergency Department
practice derive from emergency medicine science, patient safety principles, and the unique responsibility of
being ready for the worst possible case, for every patient, at every moment.
1. Professional Appearance
Standards
Attire and Identification
● Wear appropriate clinical attire and ID badge as per hospital policy, with role clearly identifiable to
patients and families.
● Follow the hospital's infection control dress code and PPE requirements, given the unpredictable
infectious and trauma exposure risk of the ED environment.
Professional Presence
● Maintain a calm, focused, and approachable demeanor, particularly during high-acuity or chaotic
periods.
● Model composed, decisive leadership during any resuscitation or mass casualty response.
2. Professional Behaviour
Expected Behaviours
Triage and Assessment Discipline
● Never allow a patient to wait for triage or reassessment beyond the institutionally defined safety
timeframe.
● Apply the same triage rigour to every patient, regardless of presentation, background, or perceived
urgency at first glance.
Time-Sensitive Protocol Discipline
● Never delay activation of a time-sensitive protocol (stroke, STEMI, sepsis) once criteria are met.
● Escalate immediately any barrier to timely treatment, rather than allowing delay to compound silently.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 19
Accountability
● Own every triage decision, every resuscitation action, and every disposition made for patients under
ED care.
● Report and disclose critical incidents and adverse events honestly and promptly.
Collaborative Respect
● Treat every member of the multidisciplinary ED team — physician, nurse, technician — as an essential,
equal safety partner.
● Coordinate genuinely with receiving departments (ICU, ward, OT) during handover and transfer.
Patient-Centered Focus
● Every triage and treatment decision is ultimately about the patient's survival and safety — not merely
departmental throughput.
3. Communication Standards
Communication with Patients and Families
● Communicate wait times, triage decisions, and treatment plans clearly and honestly, even during
periods of high demand.
● Deliver difficult news (serious diagnosis, death, disability) with structure and genuine compassion,
despite time pressure.
● Provide clear discharge instructions and safety-netting advice for every discharged patient.
Communication Within the ED Team
● Communicate clearly and rapidly during resuscitation and trauma response, using closed-loop
communication.
● Use structured handover tools (SBAR or equivalent) for every shift change and patient transfer.
● Escalate any deterioration or safety concern immediately and directly.
Written Communication Standards
● Emergency department documentation must be accurate, contemporaneous, and complete,
reflecting the rapid, high-volume nature of ED care.
● Medico-legal case documentation must be legally defensible and complete.
● Critical/urgent findings communication to receiving teams must be clearly documented.
4. Confidentiality and Information Security
Overview
The Emergency Department frequently manages patients with limited or no prior relationship to the
institution, requiring particular discipline in confidentiality despite the open, high-throughput nature of the
environment.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 20
Responsibilities
● Discuss patient information only in appropriate clinical settings and only with those who have a
legitimate need to know.
● Protect access credentials for EMR/HIS and ED tracking systems.
● Apply particular discretion for sensitive presentations (psychiatric, forensic, substance use, intimate
partner violence).
5. Ethical Standards
Core Ethical Principles for Emergency Department Practice
Non-Maleficence
● Never allow a triage or treatment delay to persist unaddressed once a genuine safety risk is identified.
● Never allow overcrowding or capacity pressure to compromise systematic assessment quality.
Beneficence and Non-Discrimination
● Treat every patient who arrives, regardless of ability to pay, immigration status, or any other non-
clinical factor.
● Apply the same clinical rigour and compassion to every patient, regardless of presentation or
background.
Honesty and Transparency
● Communicate diagnostic uncertainty honestly, particularly in the early, incomplete-information phase
of emergency assessment.
● Disclose complications and errors honestly and participate transparently in institutional review.
6. Time Management and Prioritization
Clinical Priority Framework
● Immediate/Resuscitation: Cardiac arrest, severe trauma, airway compromise — immediate response,
no delay.
● Emergent: Time-sensitive protocol activation (stroke, STEMI, sepsis) — immediate assessment and
treatment initiation.
● Urgent: Significant but non-immediately-life-threatening presentations — assessed within defined
triage timeframe.
● Non-Urgent: Stable presentations — managed per triage priority and department capacity.
7. Teamwork and Collaboration
Work Effectively With
● Trauma and surgical teams — for coordinated trauma resuscitation and surgical intervention.
● Cardiology and stroke/neurology teams — for time-sensitive STEMI and stroke protocol activation.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 21
● ICU and critical care teams — for coordinated critical patient transfer.
● Psychiatry and behavioural health teams — for psychiatric emergency assessment and disposition.
● Hospital operations and bed management — for boarding and capacity coordination.
● Quality department — for accreditation support, incident reporting, and CAPA.
8. Professional Competence and Continuous Learning
Areas of Competence
● Triage methodology and rapid clinical assessment across the full range of emergency presentations.
● Resuscitation, trauma care, and advanced life support protocols (ATLS, ACLS, PALS).
● Time-sensitive treatment pathways for stroke, myocardial infarction, and sepsis.
● Mass casualty and disaster response methodology.
● Psychiatric emergency assessment and de-escalation technique.
● FMEA, RCA, and CAPA methodologies for emergency care quality improvement.
Continuous Learning
● Maintain current certification in relevant life support protocols (BLS, ACLS, ATLS, PALS).
● Maintain current knowledge of evolving emergency medicine evidence and practice guidelines.
● Engage with national and international emergency medicine professional bodies (ACEP and
equivalent).
● Participate regularly in resuscitation, trauma, and disaster simulation training.
● Participate in NABH and JCI accreditation training for emergency care documentation standards.
Professional Standards Checklist
● Have I applied validated triage acuity assessment to every patient today?
● Have I activated every eligible time-sensitive protocol (stroke, STEMI, sepsis) without delay?
● Have I maintained resuscitation readiness throughout my shift?
● Have I communicated clearly with patients, families, and receiving teams today?
● Have I documented every medico-legal case completely and defensibly?
● Have I reported any incident or safety concern through the appropriate system?
Emergency Department professionalism is rapid clinical judgment held to an unwavering safety standard
— the team that never delays a time-sensitive protocol, never compromises triage rigour under pressure,
and never turns away a patient in need is the team every community depends upon in its most urgent
moments.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 22
CHAPTER 4: PATIENT- AND FAMILY-CENTERED COMMUNICATION IN
THE ED
Communication in the Emergency Department occurs under a unique constraint: there is often no pre-existing
relationship with the patient or family, no complete medical history, and no time to build trust gradually before
difficult conversations must happen. A family may learn, within the same hour, that their loved one arrived,
was critically ill, and did not survive — or conversely, that a frightening presentation turned out to be nothing
serious at all. Patient- and family-centered communication in the ED means recognizing that speed and
compassion are not in tension; genuine compassion, delivered efficiently, is itself part of excellent emergency
care.
Why Communication Quality Matters in the ED
● A patient or family who does not understand the triage process may experience unnecessary distress
or anger during a wait that is, in fact, clinically appropriate.
● Poorly communicated diagnostic uncertainty can leave patients confused about genuinely serious
findings or falsely reassured about ones that need urgent follow-up.
● A family receiving news of a sudden death or serious diagnosis deserves the same structured
compassion as any other setting, delivered despite ED time pressure.
● Unclear discharge instructions are a leading cause of ED bounce-back visits and preventable
complications after discharge.
The A-T-C-R-C Communication Model for the Emergency Department
A — Acknowledge
Definition
Acknowledge the patient's or family's fear and the disorientation of an unplanned, urgent hospital visit, even
within a brief encounter.
Examples
● “I know this is frightening and unexpected — I'm going to explain everything as clearly and quickly as
I can.”
T — Listen (Elicit the Full Story Rapidly)
Definition
Listen efficiently but genuinely for the key clinical history and the patient's own concerns, even under time
pressure.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 23
Techniques
● “Tell me exactly when this started and what's worried you most about it.”
● Listen for red-flag symptoms the patient may not recognize as significant.
C — Clarify (Explain Findings and Plan Simply)
Definition
Explain triage decisions, diagnostic findings, and the treatment plan in clear, jargon-free language, appropriate
to the urgency of the situation.
Examples
● “Based on what we've found, here's what we think is happening and here's our plan for the next few
hours.”
R — Respond (Provide Honest, Actionable Information)
Definition
Respond to questions and concerns honestly, including honest acknowledgment of diagnostic uncertainty
where it exists.
Examples
● “We don't have a definite answer yet, but here's what we're ruling out and what would tell us it's
something serious.”
C — Confirm (Verify Understanding, Especially at Discharge)
Definition
Confirm the patient and family genuinely understand the plan, particularly discharge instructions and warning
signs requiring return.
Examples
● “Can you tell me in your own words what to watch for that would mean you need to come back right
away?”
Breaking Bad News and Communicating Under Pressure
Structured Approach for the ED Setting
● Arrange as private a setting as the ED environment allows for delivering serious news.
● Deliver difficult information directly and honestly, using clear warning statements before serious news,
even under time constraint.
● Allow space for the family's emotional response before continuing with further information or next
steps.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 24
● Involve chaplaincy, social work, or other support resources promptly for families facing sudden loss or
serious diagnosis.
Communicating During Resuscitation and Trauma Response
Team Communication Principles
● Use closed-loop communication during resuscitation, confirming that instructions were heard and
completed.
● Assign and communicate clear roles at the start of any trauma or resuscitation activation.
● Consider family presence during resuscitation per institutional policy, with a dedicated support person
assigned to the family if present.
Communicating Triage Decisions and Wait Times
Principles
● Explain triage priority decisions honestly when a patient or family questions the wait, without
becoming defensive.
● Provide realistic wait time estimates and proactive updates if circumstances change.
● Reassess and communicate promptly if a waiting patient's condition appears to change.
Common ED Communication Mistakes to Avoid
● Failing to explain triage prioritization, leaving patients feeling arbitrarily deprioritized.
● Rushing through discharge instructions without confirming genuine patient understanding.
● Delivering serious news in a public or non-private ED space without appropriate consideration.
● Using excessive medical jargon under time pressure, sacrificing genuine patient understanding for
speed.
● Failing to communicate diagnostic uncertainty honestly, creating false reassurance or unnecessary
alarm.
Communication in the Emergency Department must be both immediate and genuine — the team that
explains triage honestly, delivers difficult news with structure and compassion despite time pressure, and
confirms genuine understanding at discharge protects patients as surely as any resuscitation performed
within the department's walls.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 25
CHAPTER 5: PATIENT SAFETY AND EMERGENCY CARE STANDARDS
Patient safety in the Emergency Department is uniquely defined by speed under uncertainty — a department
that triages accurately, treats time-sensitive conditions within evidence-based windows, and coordinates
trauma response seamlessly produces measurably better survival than one that does not, often by a matter of
minutes that cannot be recovered later. The R-T-A-C-A framework applies with particular intensity to the time-
critical, high-uncertainty nature of emergency practice.
1. RESPECT
Definition
Treating every patient who arrives — regardless of presentation, background, ability to pay, or apparent
urgency — with the same rigorous clinical assessment and genuine dignity.
How the ED Demonstrates Respect
● Respect for the Unconditional Obligation: Assess and treat every patient who arrives, without
discrimination based on non-clinical factors.
● Respect for Patient Dignity: Maintain privacy and dignity even within the open, high-throughput ED
environment.
● Respect for Every Team Member's Contribution: Value the triage nurse's first assessment as highly as
the physician's subsequent evaluation.
● Equal Service Standards: Apply the same triage rigour and clinical care to every patient, regardless of
insurance status or social circumstance.
2. TIMELINESS
Definition
Triaging, assessing, and treating patients within timeframes that reflect genuine clinical urgency — the single
most defining patient safety dimension of emergency care.
Why Timeliness Is a Patient Safety Issue
In no other area of medicine is timeliness as directly and measurably linked to survival and disability as in
emergency care. A delayed triage can miss a deteriorating patient. A delayed stroke or STEMI protocol
activation directly costs brain or heart muscle that cannot be recovered. Time in the Emergency Department is
not merely a service quality metric — it is frequently the entire difference between recovery and permanent
harm.
ED Timeliness Standards
● Triage: every patient assessed within the institutionally defined maximum time of arrival.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 26
● Resuscitation: cardiac arrest and immediately life-threatening presentations receive immediate
response, no delay.
● Time-sensitive protocols: stroke and STEMI treatment initiated within internationally recognized
benchmark windows; sepsis bundles completed within the defined time-sensitive window.
● Reassessment: waiting patients reassessed at defined intervals appropriate to their triage acuity.
3. ACCURACY
Definition
Applying triage classification, clinical assessment, and time-sensitive protocol criteria correctly and
consistently, despite incomplete information and time pressure.
Why Accuracy Is Non-Negotiable in the ED
An inaccurate triage classification can place a critically ill patient in a queue meant for stable presentations. An
inaccurate application of stroke or STEMI protocol criteria can delay treatment for a patient who genuinely
needed it, or expose a patient to unnecessary risk who did not. Accuracy in the ED, achieved under uncertainty
and time pressure, is what separates systematic emergency medicine from dangerous improvisation.
Areas Requiring ED Accuracy
● Triage Classification: Every patient must be assessed using a validated, consistently applied acuity
scale.
● Time-Sensitive Protocol Criteria: Every stroke, STEMI, and sepsis activation must be based on accurate,
systematic clinical criteria.
● Documentation: Every ED record must accurately and completely reflect the rapid, evolving clinical
picture.
● Medico-Legal Documentation: Every medico-legal case record must be accurate and legally defensible.
4. COMPASSION
Definition
Recognizing that every patient in the ED is experiencing an unplanned, often frightening crisis, and that genuine
compassion, delivered efficiently, is itself a core component of excellent emergency care.
How the ED Demonstrates Compassion
● Provide Genuine Reassurance Despite Time Pressure: Brief, sincere communication matters even
during the busiest shifts.
● Deliver Difficult News with Structure and Care: Sudden death and serious diagnosis disclosure deserve
the same compassionate structure as in any other setting.
● Support Vulnerable and Frightened Patients: Psychiatric, elderly, paediatric, and trauma patients often
require additional reassurance and patience.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 27
● Extend Compassion to Frustrated Waiting Patients: Acknowledge the genuine difficulty of waiting,
even when the wait reflects appropriate triage prioritization.
5. ACCOUNTABILITY
Definition
Taking full professional responsibility for every triage decision, every time-sensitive protocol activation, and
every disposition made for patients under ED care.
ED Accountability Standards
● Every triage assessment and clinical decision is documented with the responsible team member's
identification.
● Never allow a known triage or treatment delay to go unaddressed or unescalated.
● Report every critical incident and adverse event honestly through the quality and incident reporting
systems.
● Participate in RCA for significant incidents with complete clinical honesty, without defensiveness.
● Participate in quality audits and accreditation surveys with accurate, complete emergency care
records.
The R-T-A-C-A Framework in the Emergency Department
Standard Core Focus in the Emergency Department
Respect Unconditional treatment obligation; equal care regardless of background or payer
Timeliness Immediate resuscitation response; time-sensitive protocol windows; defined triage
reassessment
Accuracy Validated triage scoring, systematic protocol criteria, complete documentation
Compassion Genuine reassurance despite time pressure; structured, compassionate difficult news
delivery
Accountability Every decision owned and documented; every incident honestly reviewed
Daily Quality Standards Checklist for the Emergency Department
● Apply validated triage acuity assessment to every patient upon arrival.
● Activate every eligible time-sensitive protocol (stroke, STEMI, sepsis) without delay.
● Maintain continuous resuscitation and trauma readiness.
● Monitor and escalate ED boarding and overcrowding per defined protocol.
● Communicate honestly and compassionately with every patient and family.
● Document every medico-legal case completely and defensibly.
● Report any incident or safety concern through the quality reporting system.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 28
In the Emergency Department, patient safety is measured in minutes that cannot be recovered — the
family experiences it as a stroke caught in time to reverse, a heart attack treated before permanent muscle
damage, or simply an honest, compassionate answer delivered quickly during the most frightening hour of
their lives. That is patient safety delivered at the speed emergency medicine demands.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 29
CHAPTER 6: CONFIDENTIALITY, PRIVACY, AND INFORMATION
SECURITY
The Emergency Department presents a distinctive confidentiality challenge: care occurs in an inherently open,
high-throughput environment, often for patients with no prior relationship to the institution, frequently
including sensitive presentations — psychiatric crisis, intimate partner violence, substance use, sexual assault
— disclosed to strangers within minutes of arrival. Balancing rapid, open-environment care with rigorous
confidentiality requires deliberate, disciplined practice.
1. Privacy in the Open ED Environment
Responsibilities
● Use curtains, screens, or private rooms wherever available, particularly for sensitive history-taking and
examination.
● Conduct sensitive conversations (psychiatric assessment, forensic history, serious diagnosis disclosure)
in as private a space as the ED environment allows.
● Never discuss one patient's condition within earshot of another patient's bay or waiting family.
● Minimize unnecessary exposure of patient information on visible monitors or whiteboards.
2. Confidentiality of Sensitive ED Presentations
Overview
Psychiatric crises, intimate partner violence, sexual assault, and substance use disclosures carry particular
sensitivity, often disclosed for the first time to ED staff.
Responsibilities
● Handle disclosures of violence, abuse, or psychiatric crisis with heightened confidentiality and
discretion.
● Communicate only the clinically necessary information to the wider care team, not disclosure details
themselves.
● Apply appropriate mandatory reporting obligations (abuse, certain injuries) while maintaining
maximum discretion consistent with legal requirement.
3. Clinical Data and EMR/HIS Confidentiality
Responsibilities
● Access only the patient records necessary for current ED care responsibilities.
● Never discuss a patient's clinical information with anyone outside the legitimate care team.
● Follow hospital IT and cybersecurity policy for all EMR/HIS and ED tracking system access.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 30
● Never leave ED workstations unlocked or logged in when unattended.
4. Medico-Legal and Forensic Confidentiality
Overview
Medico-legal cases require particular confidentiality discipline given their legal implications and potential law
enforcement involvement.
Responsibilities
● Maintain strict confidentiality of medico-legal case details, sharing only through appropriate legal and
clinical channels.
● Apply correct evidence preservation and chain-of-custody procedures without compromising patient
confidentiality beyond legal necessity.
● Coordinate with hospital legal counsel for any case with significant medico-legal implications.
5. Cybersecurity of ED Information Systems
Why Cybersecurity Is a Patient Safety Issue
ED tracking and information systems provide the real-time situational awareness upon which safe, rapid triage
and treatment depend. A compromised system risks both data breach and, if patient tracking or triage data is
corrupted, direct patient safety harm through misdirected or delayed care.
Responsibilities
● Use only authorized, unique login credentials for all ED information system access.
● Never share login credentials with colleagues, regardless of workload pressure.
● Never connect personal devices to hospital clinical networks without IT authorization.
● Report any suspected unauthorized access or cybersecurity anomaly to IT security immediately.
6. Confidentiality for High-Profile and Vulnerable Patients
Responsibilities
● Maintain the same confidentiality standard for VIP, high-profile, or notorious patients as for every
other patient.
● Never disclose patient identity, presentation, or condition to media or unauthorized persons.
● Apply heightened discretion for patients whose presentation involves potential criminal activity or
public safety implications.
Confidentiality Checklist for the Emergency Department
● Maintain privacy measures during examination and sensitive history-taking even in an open ED
environment.
● Handle disclosures of violence, abuse, or psychiatric crisis with heightened discretion.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 31
● Use only authorized credentials for EMR/HIS and ED tracking systems.
● Maintain strict confidentiality of medico-legal case documentation.
● Never connect personal devices to hospital clinical networks without IT authorization.
● Fulfil mandatory reporting obligations while maintaining maximum appropriate discretion.
In the Emergency Department, confidentiality must be actively maintained within an inherently open, high-
throughput environment, for patients who often disclose their most sensitive information to complete
strangers within minutes of walking through the door.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 32
CHAPTER 7: STANDARD OPERATING PROCEDURES (SOPs) FOR THE
EMERGENCY DEPARTMENT
Objectives of Emergency Department SOPs
● Ensure consistent, safe, and rapid emergency care practice for every patient.
● Minimize patient harm through systematic, documented triage, resuscitation, and time-sensitive
protocols.
● Support NABH/JCI accreditation compliance for emergency and urgent care standards.
● Provide a defensible clinical and legal framework for incident investigation and quality improvement.
SOP 1: Triage and Acuity Classification
Purpose
To ensure every patient is assessed and prioritized accurately and immediately upon arrival.
Procedure
● Step 1: Immediate Visual Assessment — conduct immediate visual assessment for any immediately
life-threatening presentation upon arrival.
● Step 2: Apply Validated Triage Scale — apply a validated acuity scale (ESI, CTAS, MTS, or institutional
equivalent) systematically.
● Step 3: Document Vital Signs and Chief Complaint — record vital signs and chief complaint accurately.
● Step 4: Assign Priority — assign triage priority based on acuity scale outcome.
● Step 5: Reassess at Defined Intervals — reassess waiting patients per acuity-based reassessment
schedule.
● Step 6: Document — document the complete triage assessment and any reassessment.
Quality Standards
● 100% of patients triaged using a validated acuity scale within the institutionally defined timeframe of
arrival.
● Reassessment intervals met per acuity-based schedule for 100% of waiting patients.
SOP 2: Resuscitation (Code Blue/Cardiac Arrest)
Purpose
To ensure immediate, coordinated resuscitation response to cardiac or respiratory arrest.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 33
Procedure
● Step 1: Recognize and Activate — recognize the arrest and activate the resuscitation team
immediately.
● Step 2: Initiate High-Quality CPR — initiate CPR immediately per current ACLS/PALS guidelines.
● Step 3: Assign Roles — assign clear roles using closed-loop communication.
● Step 4: Identify Reversible Causes — systematically identify and treat reversible causes of arrest.
● Step 5: Continue Per Guidelines — continue resuscitation per current guidelines until ROSC or
termination criteria are met.
● Step 6: Document and Debrief — document the resuscitation timeline and conduct a team debrief.
Quality Standards
● 100% of resuscitation events include documented team debrief.
● Response time from recognition to CPR initiation tracked and trended.
SOP 3: Major Trauma Team Activation
Purpose
To ensure rapid, coordinated trauma team response for major trauma presentations.
Procedure
● Step 1: Apply Activation Criteria — apply standardized trauma activation criteria based on mechanism
and physiological status.
● Step 2: Activate the Trauma Team — activate the full trauma team immediately upon meeting criteria.
● Step 3: Conduct Primary Survey — conduct systematic primary survey (ATLS methodology)
immediately upon arrival.
● Step 4: Conduct Secondary Survey — conduct complete secondary survey once the primary survey is
addressed.
● Step 5: Coordinate Definitive Care — coordinate imaging, surgical consultation, and definitive care
pathway.
● Step 6: Document — document the complete trauma assessment and management.
Quality Standards
● 100% of major trauma activations include documented primary and secondary survey.
● Trauma team activation-to-arrival time tracked and trended.
SOP 4: Acute Stroke Protocol (Door-to-Needle)
Purpose
To minimize door-to-needle time for eligible acute ischemic stroke patients.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 34
Procedure
● Step 1: Recognize Stroke Symptoms — recognize stroke symptoms and activate the stroke protocol
immediately.
● Step 2: Obtain Urgent Imaging — obtain urgent CT/MRI imaging without delay.
● Step 3: Assess Eligibility — assess thrombolysis/thrombectomy eligibility per current evidence-based
criteria.
● Step 4: Administer Treatment — administer thrombolytic therapy or coordinate thrombectomy within
the evidence-based time window.
● Step 5: Document — document the complete timeline from arrival to treatment.
Quality Standards
● Door-to-needle time maintained within international benchmark target (e.g., ≤ 60 minutes) for 100%
of eligible patients.
SOP 5: Acute Myocardial Infarction Protocol (Door-to-Balloon)
Purpose
To minimize door-to-balloon time for eligible STEMI patients.
Procedure
● Step 1: Obtain Immediate ECG — obtain and interpret ECG within the institutionally defined timeframe
of arrival.
● Step 2: Activate the STEMI Protocol — activate the cardiac catheterization team immediately upon
STEMI recognition.
● Step 3: Administer Initial Therapy — administer evidence-based initial pharmacological therapy per
protocol.
● Step 4: Coordinate Rapid Transfer — coordinate rapid transfer to the catheterization laboratory.
● Step 5: Document — document the complete timeline from arrival to intervention.
Quality Standards
● Door-to-balloon time maintained within international benchmark target (e.g., ≤ 90 minutes) for 100%
of eligible patients.
SOP 6: Sepsis Recognition and Bundle in the ED
Purpose
To recognize sepsis rapidly and implement time-sensitive management within the critical treatment window.
Procedure
● Step 1: Screen Systematically — apply systematic sepsis screening (SIRS/qSOFA or institutional
equivalent) to every at-risk patient.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 35
● Step 2: Obtain Cultures and Lactate — obtain blood cultures and serum lactate immediately upon
recognition.
● Step 3: Administer Antibiotics — administer broad-spectrum antibiotics within the institutionally
defined time-sensitive window.
● Step 4: Resuscitate — initiate fluid resuscitation and vasopressor support as indicated.
● Step 5: Reassess — reassess haemodynamic status and treatment response systematically.
● Step 6: Document — document the complete sepsis bundle timeline.
Quality Standards
● Sepsis bundle elements completed within the institutionally defined time-sensitive window for 100%
of recognized cases.
SOP 7: Mass Casualty Incident Activation
Purpose
To ensure rapid, coordinated ED response to mass casualty and disaster events.
Procedure
● Step 1: Recognize and Activate — recognize the MCI trigger and activate the mass casualty response
plan.
● Step 2: Apply Disaster Triage — apply standardized disaster triage methodology (START/SALT or
equivalent).
● Step 3: Expand Capacity — activate surge capacity and overflow area protocols.
● Step 4: Coordinate with Incident Command — coordinate with the Hospital Incident Command
System.
● Step 5: Document and Debrief — document the event and conduct post-event debrief.
Quality Standards
● MCI response plan tested per regular schedule with documented drill outcomes.
SOP 8: Psychiatric Emergency and Violence De-Escalation
Purpose
To ensure safe, structured management of psychiatric emergencies and behavioural crisis.
Procedure
● Step 1: Assess Risk — conduct structured risk assessment for self-harm, suicide, and violence potential.
● Step 2: Apply De-Escalation — apply verbal de-escalation techniques as first-line response.
● Step 3: Ensure Environmental Safety — apply appropriate environmental safety measures for at-risk
patients.
● Step 4: Coordinate Psychiatric Consultation — coordinate timely psychiatric assessment.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 36
● Step 5: Determine Safe Disposition — determine appropriate disposition based on risk assessment and
consultation.
● Step 6: Document — document the complete risk assessment and management.
Quality Standards
● 100% of psychiatric emergency presentations include documented structured risk assessment.
SOP 9: ED-to-Ward/ICU Handover and Boarding Management
Purpose
To ensure safe, structured handover and proactive management of ED boarding.
Procedure
● Step 1: Confirm Admission Decision — confirm the admission decision and receiving department/bed.
● Step 2: Provide Structured Handover — provide complete handover using a standardized tool (SBAR
or equivalent).
● Step 3: Continue Monitoring During Boarding — maintain appropriate monitoring and care for
boarded patients awaiting bed placement.
● Step 4: Escalate Prolonged Boarding — escalate per defined protocol when boarding exceeds safety
thresholds.
● Step 5: Document — document the handover and boarding duration.
Quality Standards
● 100% of admissions include documented structured handover.
● ED boarding time tracked and maintained at or below institutional benchmark.
SOP 10: Medico-Legal Case Documentation
Purpose
To ensure complete, legally defensible documentation for medico-legal cases.
Procedure
● Step 1: Identify MLC Status — identify and flag medico-legal case status immediately upon recognition.
● Step 2: Document Thoroughly — document history, examination findings, and injuries completely and
objectively.
● Step 3: Preserve Evidence — apply correct evidence preservation and chain-of-custody procedures
where applicable.
● Step 4: Fulfil Reporting Obligations — complete mandatory statutory reporting accurately and
promptly.
● Step 5: Coordinate with Authorities — coordinate with law enforcement or forensic services as
required.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 37
● Step 6: Document — maintain complete, defensible medico-legal documentation.
Quality Standards
● 100% of medico-legal cases include complete, defensible documentation.
● 100% of mandatory statutory reporting obligations fulfilled within required timeframe.
Emergency Department SOP Daily Compliance Checklist
● All patients triaged using validated acuity scale within defined timeframe.
● Every eligible time-sensitive protocol (stroke, STEMI, sepsis) activated without delay.
● Resuscitation and trauma readiness maintained throughout the shift.
● ED boarding monitored with escalation applied per protocol.
● All admissions include documented structured handover.
● Any incident or safety concern reported through the appropriate system.
SOPs in emergency medicine are the operating instructions for a system built to respond correctly under
uncertainty and time pressure. When followed consistently, they are the systematic foundation of triage
accuracy, time-sensitive treatment, and coordinated trauma response for every patient who arrives
without warning.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 38
CHAPTER 8: COMMUNICATION WITH SPECIAL GROUPS
The Emergency Department receives every category of patient the healthcare system serves — from a
frightened elderly patient with a fall, to a critically injured trauma patient, to a paediatric fever, to a person in
acute psychiatric crisis, to a family suddenly facing sudden loss. Excellent emergency care requires adapted
communication for each of these very different circumstances, often within the same shift, sometimes within
the same hour.
1. Trauma Patients and Families
Overview
Major trauma presentations require rapid, coordinated communication within the team and honest, timely
updates for waiting families.
Communication Guidelines
● Communicate rapidly and clearly within the trauma team using closed-loop communication.
● Provide honest, timely updates to waiting families, acknowledging genuine uncertainty where it exists.
● Prepare families for what they may see or hear if visiting during ongoing resuscitation, per institutional
policy.
2. Paediatric Patients and Families
Overview
Children and their families require developmentally appropriate communication and particular reassurance
given the heightened anxiety paediatric emergencies provoke.
Communication Guidelines
● Communicate with parents/caregivers as primary decision-making partners while engaging the child
appropriately for their age.
● Use age-appropriate language and reassurance directly with the child where possible.
● Explain procedures and expected sensations honestly before they occur.
3. Elderly and Frail Patients
Overview
Elderly patients often present with atypical symptoms and multiple comorbidities, requiring both careful
clinical assessment and patient communication.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 39
Communication Guidelines
● Allow additional time for history-taking and explanation, checking genuine understanding without
being patronizing.
● Involve family/caregivers appropriately, particularly for patients with cognitive impairment.
● Screen for and sensitively address possible elder abuse or neglect where clinical suspicion arises.
4. Psychiatric and Behavioural Crisis Patients
Overview
Patients in psychiatric crisis require calm, non-confrontational communication and structured risk assessment.
Communication Guidelines
● Approach with a calm, non-judgmental, and genuinely curious demeanor.
● Apply verbal de-escalation principles consistently, avoiding confrontational or dismissive language.
● Communicate risk assessment findings and disposition plans clearly to the patient where clinically
appropriate.
5. Victims of Violence, Abuse, and Sexual Assault
Overview
Patients disclosing violence or assault require trauma-informed, sensitive communication that avoids re-
traumatization.
Communication Guidelines
● Use trauma-informed communication principles: patience, choice, and control returned to the patient
wherever possible.
● Avoid repeated, unnecessary retelling of traumatic history across multiple staff members.
● Coordinate sensitively with forensic, social work, and law enforcement resources as needed.
6. Patients with Substance Use Disorders
Overview
Patients presenting with intoxication or substance use require non-judgmental, harm-reduction-informed
communication.
Communication Guidelines
● Communicate without judgment, focusing on clinical safety and genuine care.
● Provide honest information about risks and available support resources.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 40
7. Multidisciplinary Consulting Teams
Overview
Timely, clear communication with consulting specialties directly affects the speed and quality of definitive care.
Communication Guidelines
● Communicate the specific clinical question and relevant findings clearly and concisely when requesting
consultation.
● Communicate urgency accurately, neither underselling a genuine emergency nor requesting
unnecessary emergent consultation.
8. Hospital Administration and Quality Department
Communication Guidelines
● Present triage compliance, time-sensitive protocol performance, and boarding data in management-
accessible formats.
● Advocate for necessary resources (staffing, capacity, equipment) with clear patient safety justification.
● Respond to quality and accreditation inquiries with complete and accurate documentation.
Universal Emergency Department Communication Principles
● Communicate clearly and efficiently, recognizing that speed and compassion are not in tension.
● Respond to every deterioration and every family's genuine concern with appropriate urgency.
● Always confirm genuine understanding, particularly for discharge instructions and safety-netting
advice.
● Document every significant clinical communication completely.
The Emergency Department that communicates with equal skill toward trauma teams in crisis and toward
every frightened patient or family walking through its doors serves every stakeholder at maximum impact
— rapid clinical excellence delivered alongside the genuine compassion that emergency care, at its most
human, demands.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 41
CHAPTER 9: HANDLING DIFFICULT SITUATIONS
Common Difficult Situations for the Emergency Department
● The department reaches dangerous overcrowding with no ward beds available for admission.
● A patient deteriorates while waiting in the triage queue.
● A time-sensitive protocol (stroke, STEMI, sepsis) is delayed due to a systemic bottleneck.
● A violent or agitated patient threatens staff or other patients.
● A family disputes a triage prioritization decision, becoming hostile.
● A mass casualty event exceeds the department's immediate capacity.
● A patient leaves without being seen (LWBS) despite a genuine clinical need.
● Diagnostic uncertainty persists in a patient the team suspects has a serious, time-sensitive condition.
● A colleague's clinical judgment or fitness for duty raises concern during a high-pressure shift.
● A medico-legal case requires urgent evidence preservation amid competing clinical priorities.
Core Principles for Handling Difficult Situations
1. Patient Safety Is Paramount
In every difficult situation, the patient safety implication drives every decision — a deteriorating patient must
never wait for administrative resolution, and time-sensitive protocols must never be delayed for non-clinical
reasons.
2. Escalate Immediately and Persistently
A genuine safety concern is not resolved until it reaches someone who can act on it — escalate through
alternative channels if the first attempt does not produce a response.
3. Apply Standardized Protocols Under Pressure
Crisis and high-volume conditions are precisely when standardized protocols matter most — resist the
temptation to improvise when a proven protocol exists.
4. Document Everything
Every difficult clinical situation must be contemporaneously documented — what was found, what was
communicated, what decisions were made, and by whom.
Handling Dangerous ED Overcrowding
Steps
● Activate the defined overcrowding escalation protocol immediately upon reaching unsafe thresholds.
● Coordinate with hospital operations for accelerated discharge and bed turnover.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 42
● Maintain continued monitoring and care for boarded patients, never treating boarding as a suspension
of clinical responsibility.
● Escalate to hospital administration if standard measures are insufficient.
Handling Deterioration in the Waiting Queue
Steps
● Apply immediate reassessment and escalate triage priority the moment deterioration is identified.
● Move the patient to an appropriate treatment area without delay.
● Document the deterioration and response thoroughly, initiating incident review if delay contributed
to the deterioration.
Handling a Delayed Time-Sensitive Protocol
Steps
● Identify the specific bottleneck (imaging delay, consultation delay, resource unavailability)
immediately.
● Escalate directly to resolve the bottleneck without accepting continued delay.
● Document the delay, cause, and resolution thoroughly, and initiate RCA for the systemic cause.
Handling a Violent or Agitated Patient
Steps
● Apply verbal de-escalation techniques as the immediate first-line response.
● Ensure staff and patient safety through appropriate environmental measures and security support.
● Apply chemical or physical restraint only per institutional protocol, as a last resort, with appropriate
monitoring and documentation.
● Debrief the team following any significant violent incident.
Handling a Hostile Family Disputing Triage Decisions
Steps
● Listen genuinely to the family's concern without immediate defensiveness.
● Explain the triage rationale clearly and honestly.
● Reassess the patient if the family's concern raises a genuine possibility of clinical change.
● De-escalate calmly, involving security only if genuine safety risk emerges.
Handling a Mass Casualty Event Exceeding Capacity
Steps
● Activate the Hospital Incident Command System and mass casualty response plan immediately.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 43
● Apply standardized disaster triage methodology consistently.
● Coordinate external mutual aid and transfer arrangements as needed.
● Conduct thorough post-event review to strengthen future capacity planning.
Handling a Patient Who Left Without Being Seen
Steps
● Attempt to contact the patient promptly if their triage acuity suggested genuine risk.
● Document the circumstances of the LWBS event thoroughly.
● Use LWBS pattern data to identify and address systemic wait-time or communication issues.
Handling Persistent Diagnostic Uncertainty in a Suspected Time-Sensitive Condition
Steps
● Apply a systematic, protocol-driven diagnostic approach rather than premature reassurance.
● Seek subspecialty consultation where uncertainty persists despite thorough evaluation.
● Apply a safety-net approach: treat empirically or admit for observation where the risk of missing a
time-sensitive diagnosis is genuine.
● Communicate the uncertainty honestly to the patient, with clear safety-netting instructions if
discharged.
Handling Concern About a Colleague's Fitness for Duty
Steps
● Address any immediate patient safety concern directly and without delay.
● Escalate to department leadership immediately if the concern involves impairment or an immediate
safety risk.
● Document the concern and actions taken through appropriate professional channels.
Handling Urgent Evidence Preservation Amid Competing Priorities
Steps
● Prioritize immediate patient care needs first, applying evidence preservation procedures wherever this
does not compromise clinical care.
● Delegate evidence preservation tasks to available team members where clinical demands prevent the
primary clinician from doing so directly.
● Document the circumstances and any necessary deviation from standard evidence preservation
procedure.
The CALM Model for the Emergency Department
● C – Control the immediate patient safety risk.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 44
● A – Acknowledge the clinical and situational reality accurately.
● L – Lead with evidence — triage criteria, time-sensitive protocols, and clinical guidelines.
● M – Manage through documented escalation channels when needed.
Difficult situations in the Emergency Department are always, ultimately, tests of whether standardized
protocol and systematic escalation hold firm under the pressure of chaos, volume, and uncertainty. The
team that never lets a deteriorating patient wait, never abandons a time-sensitive protocol under pressure,
and escalates persistently until genuine safety is restored is fulfilling the highest professional obligation of
emergency care.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 45
CHAPTER 10: EMERGENCY RESPONSE — CRITICAL PRESENTATIONS IN
THE ED
Overview
Emergency response is, in a fundamental sense, the entire discipline of emergency medicine — every patient
who arrives is, by the nature of the department, a potential critical presentation until proven otherwise. This
chapter addresses the specific, highest-acuity presentations that demand the Emergency Department's most
immediate, standardized, and rehearsed response.
Emergency Scenarios Requiring Immediate ED Response
● Cardiac arrest.
● Airway compromise or respiratory failure.
● Major trauma with haemodynamic instability.
● Acute ischemic stroke within the treatment window.
● ST-elevation myocardial infarction (STEMI).
● Septic shock.
● Anaphylaxis.
● Status epilepticus.
● Acute severe mental health crisis with imminent risk.
● Mass casualty or disaster event.
1. Cardiac Arrest
Immediate Response
● Initiate high-quality CPR immediately per current ACLS/PALS guidelines.
● Activate the resuscitation team and ensure the crash cart and defibrillator are immediately available.
● Assign clear roles using closed-loop communication.
● Systematically identify and treat reversible causes.
2. Airway Compromise or Respiratory Failure
Steps
● Assess airway, breathing, and oxygenation immediately.
● Escalate respiratory support (supplemental oxygen, non-invasive ventilation, intubation) per severity.
● Call for immediate anesthesia/airway support for a difficult or rapidly deteriorating airway.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 46
3. Major Trauma with Haemodynamic Instability
Steps
● Activate the major trauma team immediately per standardized criteria.
● Apply immediate haemorrhage control and activate the massive transfusion protocol as indicated.
● Coordinate rapid imaging and surgical consultation for definitive source control.
4. Acute Ischemic Stroke Within Treatment Window
Steps
● Activate the stroke protocol immediately upon symptom recognition.
● Obtain urgent imaging and assess thrombolysis/thrombectomy eligibility without delay.
● Administer treatment or coordinate transfer for intervention within the evidence-based time window.
5. ST-Elevation Myocardial Infarction (STEMI)
Steps
● Obtain and interpret ECG immediately upon arrival for chest pain or equivalent presentation.
● Activate the cardiac catheterization team immediately upon STEMI recognition.
● Administer evidence-based initial therapy and coordinate rapid transfer to intervention.
6. Septic Shock
Steps
● Recognize septic shock criteria and initiate the sepsis bundle immediately.
● Administer aggressive fluid resuscitation and vasopressor support per protocol.
● Administer broad-spectrum antibiotics within the institutionally defined time-sensitive window.
7. Anaphylaxis
Steps
● Administer epinephrine immediately upon recognition, without delay for confirmation.
● Support airway, breathing, and circulation aggressively with fluid resuscitation as needed.
● Monitor for biphasic reaction and observe for an appropriate period following treatment.
8. Status Epilepticus
Steps
● Apply the standardized status epilepticus treatment algorithm immediately.
● Secure the airway and administer first-line benzodiazepine therapy without delay.
● Escalate to second-line and, if needed, anesthesia-supported management per protocol.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 47
9. Acute Severe Mental Health Crisis with Imminent Risk
Steps
● Conduct immediate risk assessment and ensure environmental safety.
● Apply verbal de-escalation as first-line intervention.
● Coordinate urgent psychiatric consultation and safe disposition planning.
10. Mass Casualty or Disaster Event
Steps
● Activate the mass casualty incident response plan and Hospital Incident Command System
immediately.
● Apply standardized disaster triage methodology consistently.
● Coordinate rapid capacity expansion and resource mobilization.
Emergency Response: Key Performance Targets
Emergency Scenario Maximum Response Time Key Action
Cardiac Arrest Immediate High-quality CPR; treat reversible
causes
Acute Ischemic Stroke Within evidence-based window Urgent imaging;
thrombolysis/thrombectomy
eligibility
STEMI Within evidence-based window Activate cath lab; door-to-balloon
target
Septic Shock Immediate Fluid resuscitation; antibiotics
within time window
Anaphylaxis Immediate Administer epinephrine without
delay
Emergency Preparedness Checklist for the Emergency Department
● Resuscitation equipment, medications, and airway equipment verified and accessible at all times.
● Stroke and STEMI protocol activation pathways tested and functional.
● Mass casualty incident response plan tested per regular schedule.
● Regular participation in resuscitation, trauma, and disaster simulation training.
Emergency preparedness in the ED is not a policy statement — it is the immediate, standardized, rehearsed
response that determines survival in the minutes before definitive treatment can begin. The team that has
practiced these critical presentations until the response is automatic protects patients in the moments
when there is no time to think, only to act correctly.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 48
CHAPTER 11: DIGITAL COMPETENCY FOR THE EMERGENCY
DEPARTMENT
Objectives
● Enable the Emergency Department team to use triage, tracking, and clinical information systems
accurately, securely, and efficiently.
● Leverage technology to improve triage accuracy, time-sensitive protocol tracking, and coordinated
communication.
● Manage the cybersecurity of ED information systems as a core patient safety function.
Core Digital Competencies for the Emergency Department
1. ED Tracking and Patient Flow Systems
Essential Skills
● Manage real-time patient tracking, triage status, and bed/bay assignment within the ED tracking
system.
● Generate flow performance reports (triage time, treatment time, boarding time) supporting
operational decision-making.
2. Electronic Medical Record (EMR) / Hospital Information System (HIS)
Essential Skills
● Document triage, assessment, and treatment accurately and in real time.
● Access relevant patient history, prior records, and diagnostic results efficiently.
3. Time-Sensitive Protocol Alert Systems
Essential Skills
● Use automated alert systems for stroke, STEMI, and sepsis protocol activation effectively.
● Verify and act on system-generated alerts promptly, applying independent clinical judgment.
4. Disaster and Mass Casualty Communication Systems
Essential Skills
● Use institutional emergency notification and incident command communication systems effectively.
● Maintain familiarity with both digital and manual/backup emergency communication methods.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 49
5. AI-Assisted Triage and Risk Stratification
Awareness
● AI and predictive analytics tools are increasingly applied to triage risk stratification and early
deterioration prediction.
● Understand and appropriately leverage these tools while maintaining independent clinical judgment
— AI tools are decision-support, not a substitute for systematic assessment.
6. Telemedicine for Remote Specialist Consultation
Essential Skills
● Use telemedicine platforms for remote stroke, trauma, or specialist consultation where applicable.
● Maintain clear communication protocols supporting remote consultation quality.
7. Cybersecurity and Information Security
Personal Digital Security Responsibilities
● Use unique, strong credentials for all ED tracking and clinical system logins.
● Lock or log out of workstations whenever stepping away, even briefly.
● Never connect personal devices to hospital clinical networks.
● Report all cybersecurity anomalies to IT security immediately.
Digital Competency Checklist
● Navigate ED tracking and EMR/HIS systems for all core documentation and monitoring functions
without assistance.
● Use time-sensitive protocol alert systems effectively and verify alerts with independent clinical
judgment.
● Apply basic cybersecurity practices to all clinical system access.
● Know the downtime procedure for ED tracking/EMR system failure.
Digital competency for the Emergency Department is the ability to integrate rapid, systematic clinical
judgment with the tracking systems, protocol alerts, and predictive analytics tools that modern emergency
medicine increasingly depends upon — using technology to extend, never replace, the disciplined clinical
assessment that defines safe emergency care.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 50
CHAPTER 12: DAILY EMERGENCY DEPARTMENT CHECKLIST
Objectives
● Provide a structured daily framework for safe, consistent, and rapid emergency care practice.
● Ensure every triage, protocol, and readiness obligation is addressed every shift.
● Support accurate clinical documentation and departmental performance data quality.
PART A: START-OF-SHIFT CHECKLIST
Personal and Professional Readiness
● Appropriate clinical attire, PPE, and ID badge displayed.
● EMR/HIS and ED tracking systems functional and accessible.
Handover and Readiness Review
● Reviewed structured handover from previous shift, including any pending or unstable patients.
● Verified resuscitation equipment, medications, and airway equipment are stocked and functional.
● Reviewed current department census, acuity mix, and capacity status.
PART B: TRIAGE CHECKLIST
● Validated triage acuity scale applied to every arriving patient.
● Waiting patients reassessed per acuity-based interval schedule.
● Any deterioration in the waiting queue identified and escalated immediately.
PART C: TIME-SENSITIVE PROTOCOL CHECKLIST
● Stroke protocol activated immediately for every eligible presentation.
● STEMI protocol activated immediately for every eligible presentation.
● Sepsis screening applied systematically to every at-risk patient.
PART D: RESUSCITATION AND TRAUMA CHECKLIST
● Resuscitation and trauma team readiness maintained throughout the shift.
● Any trauma activation includes documented primary and secondary survey.
PART E: CAPACITY AND BOARDING CHECKLIST
● ED census and boarding time monitored continuously.
● Overcrowding escalation protocol applied per defined thresholds.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 51
PART F: PSYCHIATRIC AND SAFETY CHECKLIST
● Structured risk assessment completed for every psychiatric/behavioural presentation.
● Environmental safety measures applied for at-risk patients.
PART G: DOCUMENTATION AND MLC CHECKLIST
● All clinical documentation completed accurately and contemporaneously.
● Medico-legal cases documented completely and defensibly.
PART H: HANDOVER AND DISPOSITION CHECKLIST
● Structured handover provided for every admission, transfer, or significant disposition.
● Discharge instructions and safety-netting advice provided and understanding confirmed.
PART I: SAFETY AND INCIDENT CHECKLIST
● Any incident, near-miss, or LWBS event reported through the appropriate system.
● CAPA actions from previous incidents reviewed for completion.
PART J: END-OF-SHIFT CHECKLIST
● All documentation finalized in institutional systems.
● Structured handover prepared for the incoming shift.
● Clinical systems securely logged out.
Daily Self-Assessment for the Emergency Department
● Did we apply validated triage assessment to every patient today?
● Did we activate every eligible time-sensitive protocol without delay?
● Did we maintain resuscitation and trauma readiness throughout the shift?
● Did we monitor and respond to ED boarding and overcrowding appropriately?
● Did we communicate honestly and compassionately with every patient and family?
● Have we reported any incident through the appropriate system?
A consistent, structured daily routine — from start-of-shift equipment verification to end-of-shift handover
— transforms individual clinical skill into a systemic emergency care safety programme that operates
reliably across every shift, every protocol, and every patient who arrives without warning.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 52
CHAPTER 13: KEY PERFORMANCE INDICATORS (KPIs) FOR THE
EMERGENCY DEPARTMENT
Objectives
● Measure triage accuracy, time-sensitive protocol performance, and emergency care safety objectively.
● Enable data-driven continuous improvement in emergency department practice.
● Support NABH/JCI accreditation standards for emergency and urgent care.
● Demonstrate the value and patient safety impact of the Emergency Department to institutional
leadership.
Categories of Emergency Department KPIs
1. Triage and Access KPIs
KPI Definition Target
Triage Compliance Rate % of patients triaged using validated acuity scale within
defined timeframe
100%
Triage Reassessment Compliance % of waiting patients reassessed per acuity-based
schedule
≥ 95%
Left Without Being Seen (LWBS)
Rate
% of patients who leave before being seen At or below
national/institutional
benchmark
2. Time-Sensitive Protocol KPIs
KPI Definition Target
Door-to-Needle Time (Stroke) Median time from arrival to thrombolysis for
eligible patients
≤ 60 minutes (or
institutional/international
benchmark)
Door-to-Balloon Time (STEMI) Median time from arrival to PCI for eligible patients ≤ 90 minutes (or
institutional/international
benchmark)
Sepsis Bundle Compliance % of recognized sepsis cases with bundle
completed within time window
≥ 90%
3. Resuscitation and Trauma KPIs
KPI Definition Target
Cardiac Arrest Survival to ROSC % of in-ED cardiac arrests achieving return of
spontaneous circulation
Track and trend
against benchmark
Trauma Team Activation Compliance % of major trauma presentations meeting criteria with
team activation
100%
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 53
KPI Definition Target
Trauma Team Response Time Time from activation to team arrival Within institutional
target
4. Capacity and Flow KPIs
KPI Definition Target
ED Boarding Time Average time from admission decision to ward bed
placement
At or below
institutional/national
benchmark
ED Length of Stay Median total time from arrival to disposition Track and trend
against benchmark
Overcrowding Escalation Frequency Number of overcrowding escalation activations per
period
Track and minimize
5. Safety and Governance KPIs
KPI Definition Target
Incident Reporting Rate % of significant incidents/near-misses reported
through the quality system
100%
RCA Completion Rate % of significant incidents with completed RCA within
institutional timeline
100%
CAPA Completion Rate % of CAPA actions completed by agreed target date ≥ 90%
6. Disaster Readiness KPIs
KPI Definition Target
MCI Drill Compliance % of scheduled mass casualty drills completed 100%
Staff Certification Compliance % of staff with current ATLS/ACLS/PALS certification as
applicable
100%
Using KPIs for Continuous Improvement
● Review all Emergency Department KPIs regularly at departmental quality and governance meetings.
● Analyse time-sensitive protocol performance trends to identify targeted process improvements.
● Use boarding and overcrowding data to drive hospital-wide patient flow coordination.
● Present KPI data to hospital management to demonstrate the patient safety impact of emergency care.
● Use disaster drill outcomes to strengthen mass casualty readiness continuously.
Emergency Department KPIs translate rapid clinical excellence into institutional accountability —
demonstrating that the investment in triage accuracy, time-sensitive protocol adherence, and coordinated
resuscitation response is a measurable, trackable, life-saving patient safety programme at the front line of
the entire healthcare system.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 54
CHAPTER 14: TOP 20 DO'S & TOP 20 DON'TS FOR THE EMERGENCY
DEPARTMENT
Introduction
The Emergency Department carries healthcare's unconditional obligation to receive, assess, and treat every
patient who arrives, at any hour, in any condition. Their daily professional decisions — about triage rigour,
protocol discipline, and coordinated readiness — determine whether that promise is genuinely kept, one
patient at a time, all day and all night. These Do's and Don'ts provide the practical daily architecture of
Emergency Department excellence.
TOP 20 DO'S FOR THE EMERGENCY DEPARTMENT
● 1. Apply Validated Triage to Every Patient, Every Time — No exceptions, regardless of apparent
urgency at first glance.
● 2. Reassess Waiting Patients on Schedule — A queue is not a place to stop watching.
● 3. Activate Time-Sensitive Protocols Immediately — Stroke, STEMI, and sepsis criteria met means
immediate action.
● 4. Maintain Continuous Resuscitation Readiness — Equipment checked, team ready, every shift.
● 5. Apply Systematic Trauma Assessment — Primary and secondary survey, every major trauma, every
time.
● 6. Escalate Every Genuine Safety Concern Immediately — Persistence until it reaches someone who
can act.
● 7. Communicate Honestly About Wait Times and Uncertainty — Trust depends on genuine
information.
● 8. Monitor and Escalate Overcrowding Proactively — Before it becomes a genuine safety crisis.
● 9. Apply De-Escalation as First-Line Response to Agitation — Verbal skill before physical intervention.
● 10. Provide Structured Handover for Every Admission — SBAR or equivalent, every time.
● 11. Confirm Genuine Understanding at Discharge — Teach-back, not just handing over a sheet of
paper.
● 12. Document Medico-Legal Cases Completely and Defensibly — Objectivity and completeness protect
everyone.
● 13. Treat Every Patient Regardless of Background or Payer — This is the department's unconditional
obligation.
● 14. Maintain Current Life Support Certification — ATLS, ACLS, PALS — always current, never lapsed.
● 15. Debrief After Every Significant Resuscitation or Critical Event — Consolidate learning while it is
fresh.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 55
● 16. Test Mass Casualty Plans Regularly — A plan tested only in theory is not genuinely ready.
● 17. Apply Trauma-Informed Communication for Violence and Abuse Disclosures — Patience, choice,
and control matter.
● 18. Report Every Incident Honestly — Including your own errors and near-misses.
● 19. Coordinate Genuinely with Consulting and Receiving Teams — Clear, specific, timely
communication.
● 20. Continue Learning — Emergency medicine evidence evolves rapidly. The team that does not learn
continuously treats today's patients with yesterday's protocols.
TOP 20 DON'TS FOR THE EMERGENCY DEPARTMENT
● 1. Don't Skip or Rush Triage Assessment — Every patient deserves systematic, validated evaluation.
● 2. Don't Let a Waiting Patient Go Unreassessed — Deterioration can happen silently.
● 3. Don't Delay a Time-Sensitive Protocol for Any Non-Clinical Reason — Minutes cost brain, heart
muscle, and lives.
● 4. Don't Allow Resuscitation Equipment to Go Unchecked — Verify readiness every shift, without
exception.
● 5. Don't Skip Systematic Trauma Survey Under Time Pressure — Missed injuries cause preventable
harm.
● 6. Don't Accept a Single Failed Escalation Attempt as Final — Persist through alternative channels.
● 7. Don't Provide False Reassurance About Wait Times — Honesty protects trust even when the news
is difficult.
● 8. Don't Ignore Rising Overcrowding Indicators — Escalate before the crisis, not after.
● 9. Don't Escalate to Physical Restraint Without Attempting De-Escalation First — Verbal skill is the first-
line standard.
● 10. Don't Hand Over Informally for Complex or Unstable Patients — Structure protects against critical
omissions.
● 11. Don't Rush Discharge Instructions Without Confirming Understanding — This is a leading cause of
preventable bounce-back.
● 12. Don't Document Medico-Legal Cases Incompletely or Speculatively — Objectivity and
completeness are non-negotiable.
● 13. Don't Apply Lesser Care Based on Payer Status or Background — The obligation is unconditional.
● 14. Don't Let Certification Lapse — Life support skills must remain current and practiced.
● 15. Don't Skip Team Debriefing After a Critical Event — Unprocessed events repeat their gaps.
● 16. Don't Skip Scheduled Disaster Drills — An untested plan is an unreliable plan.
● 17. Don't Force Repeated Retelling of Traumatic History Across Staff — This re-traumatizes vulnerable
patients.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 56
● 18. Don't Hide or Minimize an Incident — Suppressed incidents cannot drive the improvement that
prevents recurrence.
● 19. Don't Delay or Obscure Communication with Consulting Teams — Clarity and timeliness protect
the patient.
● 20. Don't Practice Outside Current Emergency Medicine Evidence — Personal habit or outdated
protocol must never override current best practice.
Emergency Department Golden Rules
● Triage everyone, every time — validated, systematic, without exception.
● Reassess the waiting — a queue is not a place to stop watching.
● Activate protocols immediately — minutes are the difference between recovery and permanent harm.
● Stay resuscitation-ready — every shift, every piece of equipment, verified.
● Escalate persistently — until genuine safety is restored, not just attempted.
● Communicate honestly — about waits, about uncertainty, about difficult news.
● De-escalate before restraining — verbal skill is the first-line standard.
● Hand over with structure — SBAR or equivalent, every time.
● Report every incident — including your own, honestly and promptly.
● Never stop learning — today's emergency medicine evidence is not yesterday's.
Daily Commitment Statement
“Today, I will triage every patient accurately, activate every time-sensitive protocol without delay, maintain
resuscitation readiness throughout my shift, communicate honestly with every patient and family, escalate
every genuine safety concern persistently, and uphold every safety standard without exception — because
every patient who walks through this door, at any hour, in any condition, deserves nothing less than my
complete readiness.”
The Top 20 Do's and Top 20 Don'ts are the daily professional architecture of Emergency Department
excellence — each shaped by the understanding that emergency care is patient safety management
practiced at maximum speed under maximum uncertainty, and that there are no minor lapses when
minutes determine survival.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 57
CHAPTER 15: EMERGENCY DEPARTMENT PROFESSIONAL PLEDGE
Introduction
An Emergency Department Professional Pledge is a formal, collective commitment to uphold the highest
standards of triage accuracy, time-sensitive protocol discipline, coordinated resuscitation, and continuous
learning. It serves as a daily affirmation that every triage decision, every protocol activated, and every patient
received without condition is an act of professional purpose in service of a community that depends on this
department to never close its doors and never turn anyone away.
Purpose of the Pledge
● Reinforce the Emergency Department's collective identity as the unconditional first point of access to
emergency care.
● Promote a culture of triage rigour, protocol discipline, and honest incident reporting.
● Strengthen the commitment to coordinated resuscitation, trauma response, and disaster readiness.
● Support continuous professional development and emergency medicine excellence.
● Build institutional and community recognition of the Emergency Department as the front line where
healthcare's promise of access is kept every single day.
Official Emergency Department Professional Pledge
“We solemnly pledge that as the Emergency Department team, we will fulfil our collective and individual
responsibilities with the highest standards of clinical rigour, professional integrity, and unwavering
commitment to every patient who arrives at our door, at any hour, in any condition, without exception.
We will apply validated, systematic triage to every patient immediately upon arrival, and we will reassess every
waiting patient per defined schedule, knowing that deterioration can occur silently and that our vigilance is the
safeguard against it.
We will activate every time-sensitive protocol — stroke, STEMI, sepsis — immediately upon recognition,
without delay for any non-clinical reason, knowing that minutes we cannot recover directly determine whether
our patients survive with their brain, their heart, and their future intact.
We will maintain continuous readiness for resuscitation and trauma, every shift, every piece of equipment
verified, every team member prepared for the patient we cannot predict in advance but must always be ready
to receive.
We will communicate honestly with every patient and family, even under the pressure of time and uncertainty,
and we will escalate every genuine safety concern persistently until it reaches someone who can act on it.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 58
We will treat every patient who arrives with the same rigour and compassion, regardless of their ability to pay,
their background, or the hour of their arrival, honouring the unconditional obligation that defines this
department.
We will report every incident and near-miss honestly, debrief after every critical event, and continuously test
our readiness for the disasters and mass casualties we hope never to face but must always be prepared for.
We will continuously expand our knowledge and skill — knowing that emergency medicine evidence evolves
rapidly, and that the team that does not learn continuously treats today's patients with yesterday's protocols.
With rapid clinical judgment, unwavering readiness, and genuine compassion for every stranger who walks
through our door, we pledge to be the Emergency Department that never closes, never turns anyone away,
and never stops fighting for every second that can be given back to a patient's life.”
Daily Commitment Statement
“Today, we commit to triaging every patient accurately, activating every time-sensitive protocol without delay,
maintaining resuscitation readiness, communicating honestly, escalating every safety concern persistently, and
upholding every standard without exception — because every patient who arrives at our door deserves our
complete readiness.”
Core Values Reflected in the Pledge
1. Unconditional Access
Every patient received and assessed, regardless of background or circumstance.
2. Triage Rigour
Systematic, validated assessment applied consistently, every patient, every time.
3. Time-Sensitive Discipline
Immediate protocol activation where minutes determine survival and disability.
4. Coordinated Readiness
Continuous preparation for resuscitation, trauma, and disaster, rehearsed rather than assumed.
5. Honest Communication
Genuine, compassionate communication despite time pressure and uncertainty.
6. Accountability
Every decision owned and documented; every incident honestly reported.
7. Persistent Escalation
Safety concerns pursued until genuinely resolved, not merely raised once.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 59
8. Continuous Learning
Emergency medicine evidence evolves. Professional competence requires perpetual learning.
When the Pledge Should Be Recited
● At the beginning of every new Emergency Department team member's appointment.
● At the start of a new departmental leadership role or shift responsibility.
● At departmental quality and morbidity/mortality review meetings.
● At NABH/JCI accreditation preparation events.
● As a periodic collective affirmation, particularly following a significant critical event or mass casualty
drill.
Benefits of the Pledge
For Patients
● Confidence that they will be assessed accurately and promptly, regardless of when or how they arrive.
● Assurance that any time-critical condition will be recognized and treated within its evidence-based
window.
● Trust that the department is genuinely ready for any emergency, including their own.
For the Healthcare System
● A reliable front line that absorbs unpredictable demand without compromising safety.
● Coordinated readiness that protects the entire hospital during surge and disaster events.
● A source of accurate, timely referral into the appropriate level of ongoing care.
For Healthcare Organizations
● Measurable improvement in time-sensitive protocol performance and patient survival outcomes.
● Stronger NABH/JCI accreditation performance in emergency and urgent care standards.
● Reduced adverse events and their profound clinical, legal, and reputational consequences.
Emergency Department Oath of Readiness
“We pledge to be the door that never closes and the team that is always ready — ensuring that every patient
who arrives, at any hour, in any condition, is met with accurate triage, immediate time-critical treatment, and
the genuine compassion that emergency care, at its most urgent, demands.”
Emergency Department Signature Commitment
This pledge is recited collectively by the multidisciplinary Emergency Department team and may be individually
signed by:
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 60
Name: ___________________________
Role: Emergency Physician / Triage Nurse / Emergency Nurse / ED Technician / Allied Emergency Care
Professional
Department: Emergency Department
Registration/Employee ID: _______________
Signature: ________________________
Date: ____________________________
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 61
CONCLUSION
No other department in a hospital carries quite the same unconditional promise as the Emergency Department:
whoever you are, whenever you arrive, whatever has happened to you, we will see you, assess you, and act.
That promise is kept not through good intentions but through disciplined systems — validated triage applied
to every patient without exception, time-sensitive protocols activated the instant criteria are met, resuscitation
readiness verified every single shift, and a team trained to coordinate seamlessly through chaos that cannot
be scheduled in advance.
Throughout this manual, we have explored the full scope of Emergency Department professional practice —
from triage and rapid assessment, through resuscitation, trauma care, and time-sensitive treatment protocols,
to overcrowding management, mass casualty response, psychiatric emergency care, and the professional
conduct that defines excellence across every category of emergency presentation. These responsibilities
collectively define a discipline that is simultaneously the most unpredictable and the most systematically
protocol-driven area of medicine — because unpredictability at the point of arrival is answered, deliberately,
with rigorous standardization in response.
The Importance of the Emergency Department in Healthcare Quality
● The unconditional access point — receiving every patient regardless of background, payer status, or
hour of arrival.
● The triage authority — identifying the sickest patients within minutes, before complete information is
even available.
● The time-critical treatment provider — delivering stroke, cardiac, and sepsis care within windows
where minutes determine permanent outcome.
● The trauma and resuscitation team — coordinating life-saving response in the most decisive minutes
of critical illness and injury.
● The disaster front line — absorbing sudden, overwhelming demand that the rest of the healthcare
system depends upon it to manage.
● The safety net for the vulnerable — psychiatric crisis, abuse, homelessness, and every presentation
with nowhere else to turn.
● The honest investigator — learning systematically from every incident to protect the next patient who
arrives unannounced.
Key Lessons from This Manual
Triage Is the First and Most Consequential Safety Decision
Before any diagnosis is made, before any treatment begins, the triage decision determines who is seen first —
and getting this decision right, consistently, for every patient, is the foundation upon which all subsequent
emergency care safety depends.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 62
Time-Sensitive Protocols Exist Because Minutes Are Irreversible
Unlike many clinical decisions that can be revisited and corrected, the minutes lost to a delayed stroke or
cardiac protocol activation cannot be recovered — standardization exists precisely because human judgment
under time pressure benefits from a protocol that does not have to be invented in the moment.
Readiness Must Be Verified, Not Assumed
A resuscitation team that has not checked its equipment, a mass casualty plan that has never been drilled —
these are readiness in name only. Genuine readiness is proven through continuous verification and rehearsal.
The Unconditional Obligation Is What Makes This Department Unique
No other part of the healthcare system carries quite the same absolute commitment to receive every patient,
regardless of circumstance — and honouring that obligation, consistently, is what separates emergency
medicine from every other specialty.
Escalation Persistence Protects Patients When the First Attempt Fails
A safety concern raised once and not acted upon is not resolved — the discipline of escalating through
alternative channels until genuine action occurs is what protects patients when the first response falls short.
The Impact of Excellent Emergency Department Practice
● Every patient triaged accurately and treated according to genuine clinical urgency.
● Stroke, cardiac, and sepsis patients treated within evidence-based windows that preserve function and
life.
● Trauma and resuscitation coordinated seamlessly in the most decisive minutes of critical illness and
injury.
● Mass casualty and disaster events absorbed safely through tested, rehearsed capacity plans.
● Every patient, regardless of background, met with the same rigorous care and genuine compassion.
● NABH/JCI accreditation reflecting genuine emergency and urgent care excellence.
Final Commitment
“As the Emergency Department, we commit to triaging every patient accurately, activating every time-sensitive
protocol without delay, maintaining continuous resuscitation and trauma readiness, communicating honestly
and compassionately, escalating every safety concern persistently, and upholding every regulatory and ethical
standard without exception — because every patient who arrives at our door, at any hour, in any condition,
depends on our readiness to receive them.”
Final Motto
“The Door Never Closes, the Clock Never Stops — Every Second in the Emergency Department Is a Decision
That Shapes a Life.”
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 63
Together, We Are the Front Line That Never Closes — Ensuring Every Patient Is Triaged Accurately, Every
Second Counts Toward Survival, and No One Is Ever Turned Away.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 64
REFERENCES
Global Accreditation and Regulatory Standards
● Joint Commission International (JCI) – JCI Accreditation Standards for Hospitals: Access to Care and
Continuity of Care (ACC) and Care of Patients (COP) Chapters, including Emergency Care Requirements.
● National Accreditation Board for Hospitals & Healthcare Providers (NABH, India) – Standards for
Hospital Access, Assessment and Continuity of Care, and Emergency Department Specific
Requirements (5th Edition).
● International Society for Quality in Health Care (ISQua) – Guidelines and Principles for Health and Social
Care Standards, applied to Emergency Medicine Services.
● World Health Organization (WHO) – Emergency Care Systems Framework and Guidelines for Essential
Trauma Care.
Triage and Rapid Assessment Standards
● Emergency Nurses Association / American College of Emergency Physicians – Emergency Severity
Index (ESI) Implementation Handbook.
● Canadian Association of Emergency Physicians – Canadian Triage and Acuity Scale (CTAS) Guidelines.
● Manchester Triage Group – Manchester Triage System (MTS) Guidelines.
Resuscitation, Trauma, and Life Support Standards
● American Heart Association (AHA) – Guidelines for Cardiopulmonary Resuscitation and Emergency
Cardiovascular Care (ACLS/BLS).
● American Academy of Pediatrics / American Heart Association – Pediatric Advanced Life Support
(PALS) Guidelines.
● American College of Surgeons Committee on Trauma – Advanced Trauma Life Support (ATLS) Student
Course Manual.
● International Liaison Committee on Resuscitation (ILCOR) – Consensus on Science and Treatment
Recommendations.
Time-Sensitive Treatment Protocol Standards
● American Heart Association / American Stroke Association – Guidelines for the Early Management of
Patients with Acute Ischemic Stroke.
● American College of Cardiology / American Heart Association – Guidelines for the Management of
Patients with ST-Elevation Myocardial Infarction.
● Surviving Sepsis Campaign – International Guidelines for Management of Sepsis and Septic Shock.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 65
Mass Casualty and Disaster Response Standards
● Hospital Incident Command System (HICS) – Guidebook and Implementation Standards.
● World Health Organization – Mass Casualty Management Systems and Hospital Emergency Response
Checklist.
● START/SALT Triage Methodology – Consensus Guidelines for Mass Casualty Triage.
Psychiatric Emergency and Workplace Violence Standards
● American College of Emergency Physicians – Policy Statement on Care of the Psychiatric Patient in the
Emergency Department.
● Occupational Safety and Health Administration (OSHA) – Guidelines for Preventing Workplace
Violence in Healthcare Settings.
Overcrowding, Boarding, and Patient Flow Standards
● American College of Emergency Physicians (ACEP) – Policy Statements on Emergency Department
Crowding and Boarding.
● Institute of Medicine (US) – Hospital-Based Emergency Care: At the Breaking Point.
● Institute for Healthcare Improvement (IHI) – Patient Flow and Emergency Department Throughput
Improvement Resources.
Indian Regulatory and Statutory Framework
● National Medical Commission (NMC) – Code of Medical Ethics Regulations Applicable to Emergency
Care.
● Clinical Establishments (Registration and Regulation) Act, India – Applicable Emergency Care
Regulatory Requirements.
● Medico-Legal Case (MLC) Reporting Requirements under Indian Penal Code and Criminal Procedure
Code, as applicable to Emergency Departments.
● Protection of Children from Sexual Offences (POCSO) Act and Applicable Mandatory Reporting
Statutes, India.
Quality Improvement and Patient Safety Frameworks
● Institute for Healthcare Improvement (IHI) – Framework for Patient Safety and Quality Improvement
in Emergency Medicine.
● The Joint Commission (US) – National Patient Safety Goals Applicable to Emergency Services.
● World Health Organization – Global Patient Safety Action Plan 2021–2030.
Cybersecurity and Digital Health Records
● NIST Cybersecurity Framework – Applied to Healthcare Emergency Department Information Systems.
● HL7 International – Health Level Seven Data Interchange Standards.
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 66
This manual has been developed using internationally recognized principles and best practices from JCI Access
to Care and Care of Patients Standards, NABH Emergency Department Standards, WHO Emergency Care
Systems Framework, AHA/ILCOR Resuscitation Guidelines, ATLS/ACLS/PALS Life Support Protocols, Surviving
Sepsis Campaign Guidelines, Hospital Incident Command System (HICS) Disaster Response Standards, ACEP
Policy Statements, applicable Indian statutory and medico-legal reporting requirements, and international
emergency medicine patient safety frameworks. Institutions should verify current versions of all cited
guidelines and regulatory requirements, as clinical protocols and accreditation standards are subject to
periodic revision.
ॐ जय माता द( ॐ
Emergency Department Excellence Manual Dr J L Meena
Emergency Department Excellence Manual – Dr J L Meena | Page 67
END OF MANUAL
Thank You
This manual has been prepared with the vision to empower the multidisciplinary Emergency Department team
with global standards, best practices, and professional guidance to ensure safe, rapid, and compassionate
emergency care.
Our Commitment Continues
The journey of learning never ends. As emergency medicine evidence evolves and healthcare advances, our
commitment to patient safety, rapid readiness, quality, and compassion must remain unwavering.
Together, We Build Trust
Every accurate triage, every protocol activated in time, every trauma coordinated seamlessly, and every patient
received without condition contributes to one greater purpose — a community that can trust the door will
always be open, and the team behind it will always be ready.
“The Door Never Closes, the Clock Never Stops — Every Second in the Emergency Department
Is a Decision That Shapes a Life.”
REMEMBER: Safety is our priority • Speed is our discipline • Readiness is our strength • Compassion is our
purpose • Learning is our journey
Thank you for being a part of this vital mission. Your dedication makes a difference every day.
Dr J L Meena