Overview of medical interventions like forced diuresis and extracorporeal methods to accelerate toxin removal, reduce toxicity duration, and improve outcomes in poisoning cases.
Elimination Enhancement inClinical Toxicology :
Elimination enhancement (also called enhanced elimination) is
the use of specific medical interventions to increase the removal
of a poison or toxin from the body after it has been absorbed
into the bloodstream. It is used in selected cases of poisoning to
reduce the duration and severity of toxicity, especially when
supportive care alone is insufficient.
Elimination enhancement is the deliberate use of pharmacological
or extracorporeal techniques to accelerate the elimination of toxic
substances from the body, thereby reducing toxin concentration,
limiting organ damage, and improving patient outcomes.
3.
Objectives of EliminationEnhancement
The main aims are to:
Remove the poison from the bloodstream as quickly
as possible.
Shorten the duration of toxic effects.
Prevent complications such as organ failure.
Reduce mortality in severe poisoning.
Decrease the need for prolonged intensive care.
5.
"The various methodsof eliminating absorbed poisons from
the body"
Introduction
Once a poison has been absorbed, the body's natural
elimination through the kidneys, liver, lungs, and
gastrointestinal tract may be too slow. If the poison continues
circulating in the blood, it can cause severe toxicity and organ
damage.
Therefore, elimination enhancement techniques are used to:
•Reduce the concentration of poison in the blood.
•Shorten the duration of poisoning.
•Prevent permanent organ damage.
•Improve survival in severe intoxication.
6.
1. Forced Diuresis
Forceddiuresis is the deliberate increase in urine production by
administering large amounts of intravenous fluids, sometimes
combined with diuretics, to increase the renal excretion of certain
poisons.
Principle
The kidneys remove many drugs from the blood.
If urine production increases:
➡ More blood passes through the kidneys.
➡ More poison is filtered.
➡ Greater amount of poison is eliminated in urine.
7.
Mechanism
Normally
Blood → Kidney→ Small amount of toxin removed → Urine
During forced diuresis
Blood → Kidney → Increased urine flow → More toxin removed → Large urine
output
How is it done?
The patient receives
Intravenous normal saline
Sometimes mannitol
Sometimes furosemide (rarely used now)
Urine output is carefully monitored.
Target urine output
3–6 mL/kg/hour
8.
2. Extracorporeal Techniques
"Extracorporeal"means outside the body.
These methods remove blood from the patient, eliminate
the poison using a machine or filter, and return the purified
blood to the body.
Blood → Machine → Poison removed → Clean blood
returned
These methods are used only in life-threatening poisoning.
9.
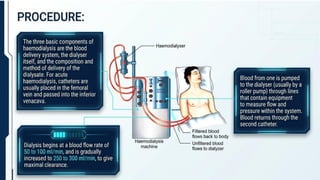
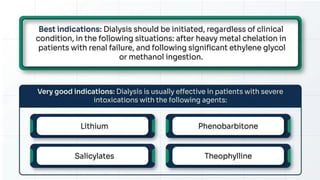
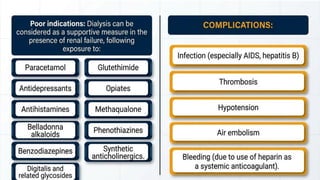
A. Haemodialysis
Blood passesthrough a dialysis machine containing a semipermeable
membrane.
The poison diffuses from blood into dialysis fluid.
Mechanism
Blood → Dialysis membrane → Poison diffuses into dialysate → Clean blood
returns
Best for
Poisons that are
Water soluble
Low molecular weight
Low protein binding
Low volume of distribution
Ex: Lithium, Valproic Acid, Methanol, Salicylates
10.
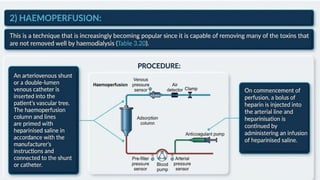
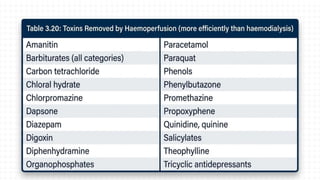
B. Hemoperfusion
Blood passesthrough a cartridge filled with activated charcoal or resin.
Instead of diffusion, toxins adsorb onto the charcoal surface.
Mechanism
Blood → Charcoal cartridge → Poison sticks to charcoal → Clean blood
returns
Best for
Protein-bound drugs such as
Carbamazepine
Phenobarbital
Theophylline
11.
Advantages
Removes toxins thatdialysis cannot remove effectively.
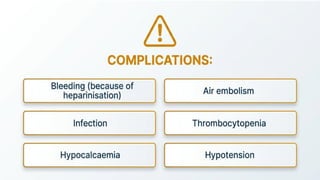
Complications
Thrombocytopenia
Hypocalcemia
Hypoglycemia
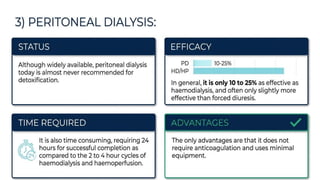
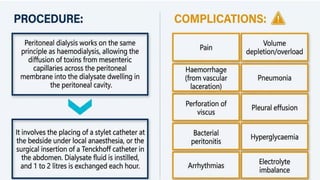
C. Peritoneal Dialysis
The peritoneum (lining of the abdominal cavity) acts as the dialysis membrane.
Dialysis fluid is introduced into the abdomen.
Toxins diffuse from blood vessels into the fluid, which is then drained.
Mechanism
Blood vessels → Peritoneal membrane → Dialysis fluid → Removed
12.
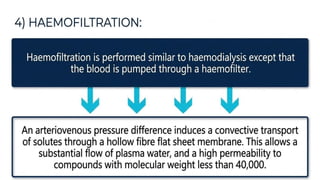
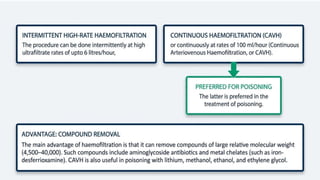
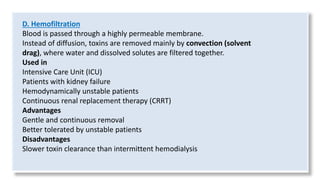
D. Hemofiltration
Blood ispassed through a highly permeable membrane.
Instead of diffusion, toxins are removed mainly by convection (solvent
drag), where water and dissolved solutes are filtered together.
Used in
Intensive Care Unit (ICU)
Patients with kidney failure
Hemodynamically unstable patients
Continuous renal replacement therapy (CRRT)
Advantages
Gentle and continuous removal
Better tolerated by unstable patients
Disadvantages
Slower toxin clearance than intermittent hemodialysis
13.
E. Plasmapheresis
The plasma(liquid part of blood) is separated and removed, then
replaced with donor plasma or albumin.
Mechanism
Blood → Plasma separated → Plasma removed → New plasma added
→ Blood returned
Uses
Useful when toxins are
Highly protein bound
Located mainly in plasma
Examples include
Amanita mushroom toxins (selected cases)
Certain autoimmune disorders (more common indication)
Advantages
Removes toxins attached to plasma proteins.
14.
F. Plasma Perfusion
Insteadof whole blood, only the plasma is passed through an adsorbent column
to remove toxins.
Mechanism
Blood → Plasma separated → Plasma through adsorbent → Clean plasma
returned
Uses
Rarely used; reserved for selected poisonings involving large plasma-bound
toxins.
G. Cardiopulmonary Bypass (CPB)
A heart–lung machine temporarily takes over the function of the heart and
lungs.
19.
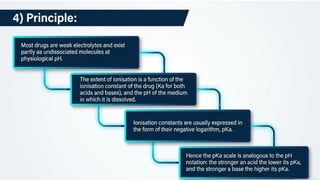
The principle ofionization and ion trapping, which is the basis for
enhancing renal elimination of drugs in poisoning (clinical toxicology).
Understanding this concept helps explain why urinary alkalinization is used
for acidic drug poisoning and urinary acidification (rarely used today) was
once considered for basic drug poisoning.
Principle: Ionization of Drugs
Drugs exist in two forms:
Non-ionized (Unionized) form
Ionized form
The proportion of these two forms depends on:
pKa of the drug
pH of the surrounding environment (urine, plasma, stomach, etc.)
The relationship is described by the Henderson–Hasselbalch equation.
20.
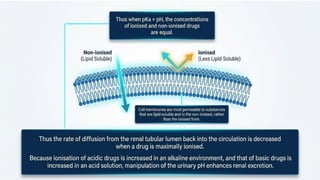
50% HA (non-ionized)
50%A⁻ (ionized)
Both forms are present equally.
Non-ionized molecules:
have no electrical charge
dissolve well in lipids
diffuse easily through membranes
Therefore they can move:
from urine back into blood
from blood into tissues
across intestinal membranes
across the blood-brain barrier
Example
A weak acid in its non-ionized form
HA
can easily diffuse through the renal tubular membrane.
Therefore it is reabsorbed back into blood.
21.
Ionized molecules
carry apositive or negative charge
dissolve well in water
do not dissolve well in lipids
Therefore they cannot easily cross cell membranes.
Only the non-ionized form of a drug can easily cross biological
membranes because it is lipid soluble.
The ionized form remains in the aqueous fluid and crosses
membranes poorly.
This principle is called passive diffusion.




 Most read

 Most read




 Most read