PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
1 | P a g e
drprabhatdevkota@gmail.com
Postgraduate Ophthalmology Exam Notes
© First Edition, 2026
Author
Dr. Prabhat Kiran Devkota, MBBS(TU), MD(NAMS)
MBBS – Chitwan Medical College Teaching Hospital, Institute of
Medicine, Tribhuvan University (TU), Nepal
MD (Ophthalmology) – Lumbini Eye Institute & Research Center,
National Academy of Medical Sciences (NAMS), Nepal
Email: drprabhatdevkota@gmail.com
All rights reserved.
No part of this publication may be reproduced, stored in a retrieval system,
transmitted, or distributed in any form or by any means, whether electronic,
mechanical, photocopying, recording, or otherwise, without prior written permission
of the author, except for brief quotations used for academic, educational, or review
purposes.
Disclaimer
This book is intended solely as an educational and revision resource for postgraduate
ophthalmology trainees and practitioners. While every effort has been made to ensure
the accuracy and reliability of the information presented, the author does not
guarantee that all content is free from errors or omissions. Readers are encouraged to
consult standard textbooks, peer-reviewed literature, institutional guidelines, and
current evidence-based recommendations before making clinical decisions.
The author shall not be held responsible for any consequences arising from the use of
information contained in this book.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
2 | P a g e
drprabhatdevkota@gmail.com
Preface
This book is a compilation of notes gathered during my preparation for the Final MD
Examination in Ophthalmology. The material has been collected from standard
textbooks, lecture notes, journals, online resources, and personal study notes.
Topics have been organized in a chapter-wise format to facilitate quick revision and
easy reference. Although there are many excellent ophthalmology resources available,
I felt it worthwhile to compile and share these notes with future ophthalmology
trainees and colleagues.
This work represents a continuous learning process rather than a definitive textbook.
Suggestions, corrections, contributions, and constructive feedback are greatly
appreciated and will help improve future editions.
I sincerely hope this book serves as a useful companion in your postgraduate
ophthalmology journey.
Good Luck and Best Wishes!
For comments, suggestions, or contributions, please contact:
Dr. Prabhat Devkota, MD
drprabhatdevkota@gmail.com
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
3 | P a g e
drprabhatdevkota@gmail.com
CONTENTS
SN Topic
1 Ophthalmic Drug Delivery
2 Cycloplegics
3 Mydriatics
4 Corticosteroids
5 General Principles of Preparation
8 Antibacterial Agents
9 Antifungal Agents
10 Antiviral Agents
11 Antiglaucoma Medications
12 Anti-VEGF Drugs
13 Immunosuppressive Therapy (IMT)
14 Sodium Chloride (Hypertonic Saline)
15 Antiallergic Drugs
16 Local Anesthetics
17 Botulinum Toxin (Botox)

18 Mitomycin-C (MMC)
19 5-Fluorouracil (5-FU)
20 Ophthalmic Viscosurgical Devices (OVDs)
21 Non-Steroidal Anti-Inflammatory Drugs (NSAIDs)
22 Tear Supplements
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
4 | P a g e
drprabhatdevkota@gmail.com
OPHTHALMIC DRUG DELIVERY
Topical Administration
Most common, noninvasive, self-administered.
Limitations:
Rapid systemic absorption via conjunctival/episcleral vessels & nasolacrimal drainage.
Limited posterior segment penetration.
Forms
• Solutions: easy, minimal vision interference, short contact time.
• Suspensions: require shaking, variable resuspension, may clog droppers (esp. prednisolone
acetate 1%).
• Ointments: prolonged contact, act as reservoir, blurred vision, preferred for bedtime dosing
or corneal ulcers.
• Gels / In situ gels: sustained contact, reduced frequency (e.g., timolol gel).
• Sprays: noninvasive, useful in children, closed eyelid administration.
• Unit-dose dispensers: preservative-free, short-term use.
• Special Devices
• Soft contact lenses: prolonged delivery; water content affects absorption.
• Collagen shields: dissolve over 12–72 hrs; release drug gradually.
• Filter paper strips: fluorescein, lissamine green, rose bengal; precise dosing.
• Cotton pledgets: prolonged local exposure for mydriatics.
• Continuous irrigation / Morgan lens: for large volumes (chemical burns).
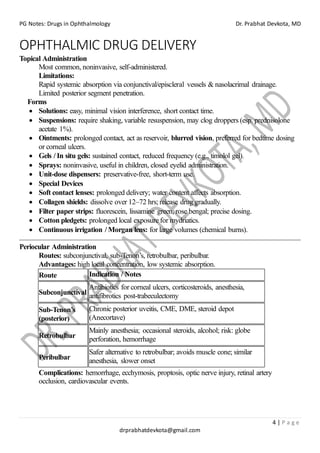
Periocular Administration
Routes: subconjunctival, sub-Tenon’s, retrobulbar, peribulbar.
Advantages: high local concentration, low systemic absorption.
Route Indication / Notes
Subconjunctival
Antibiotics for corneal ulcers, corticosteroids, anesthesia,
antifibrotics post-trabeculectomy
Sub-Tenon’s
(posterior)
Chronic posterior uveitis, CME, DME, steroid depot
(Anecortave)
Retrobulbar
Mainly anesthesia; occasional steroids, alcohol; risk: globe
perforation, hemorrhage
Peribulbar
Safer alternative to retrobulbar; avoids muscle cone; similar
anesthesia, slower onset
Complications: hemorrhage, ecchymosis, proptosis, optic nerve injury, retinal artery
occlusion, cardiovascular events.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
5 | P a g e
drprabhatdevkota@gmail.com
Intracameral Administration
Direct anterior chamber delivery.
• Indications: viscoelastic, lidocaine anesthesia, tissue plasminogen activator, sustained-release
steroid pellets (Surodex).
• Reduces systemic exposure, high local effect.
Intravitreal Administration
• Direct vitreous delivery; bypasses blood–ocular barrier.
• Indications:
• Antibiotics / antifungals → bacterial/fungal endophthalmitis.
• Antivirals → CMV retinitis (Vitrasert implant, ganciclovir).
• Corticosteroids → diabetic macular edema, noninfectious posterior uveitis (Retisert,
triamcinolone).
• Anti-VEGF →AMD (ranibizumab, pegaptanib, aflibercept).
• Advantages: high posterior drug levels, minimal systemic toxicity.
• Complications: retinal detachment, vitreous hemorrhage, endophthalmitis.
Key Exam Pearls
• Topical drugs rarely reach posterior segment.
• Nasolacrimal occlusion increases intraocular absorption and reduces systemic effects.
• Ointments → prolonged contact; blur vision → use at night.
• Sprays can achieve effective drug delivery on closed eyelids.
• Subconjunctival antibiotics → corneal ulcers; posterior sub-Tenon’s steroids → macular
edema.
• Vitrasert → sustained ganciclovir for CMV retinitis.
• Morgan lens → continuous irrigation for chemical burns.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
6 | P a g e
drprabhatdevkota@gmail.com
CYCLOPLEGICS
ATROPINE
Class: Naturally occurring alkaloid, nonselective muscarinic antagonist
Source: Atropa belladonna (belladonna plant)
Topical ophthalmic: 1% solution and 1% ointment
Mechanism ofAction (MOA)
Nonselective M3 muscarinic receptor antagonist → blocks parasympathetic input
Effects in the eye:
Mydriasis: relaxes sphincter pupillae
Cycloplegia: paralyzes ciliary muscle → prevents accommodation
Duration:
Mydriasis: up to 10 days
Cycloplegia: 7–12 days
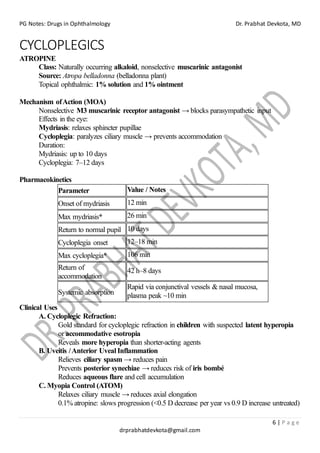
Pharmacokinetics
Parameter Value / Notes
Onset of mydriasis 12 min
Max mydriasis* 26 min
Return to normal pupil 10 days
Cycloplegia onset 12–18 min
Max cycloplegia* 106 min
Return of
accommodation
42 h–8 days
Systemic absorption
Rapid via conjunctival vessels & nasal mucosa,
plasma peak ~10 min
Clinical Uses
A. Cycloplegic Refraction:
Gold standard for cycloplegic refraction in children with suspected latent hyperopia
or accommodative esotropia
Reveals more hyperopia than shorter-acting agents
B. Uveitis /Anterior Uveal Inflammation
Relieves ciliary spasm → reduces pain
Prevents posterior synechiae → reduces risk of iris bombé
Reduces aqueous flare and cell accumulation
C. Myopia Control (ATOM)
Relaxes ciliary muscle → reduces axial elongation
0.1% atropine: slows progression (<0.5 D decrease per year vs 0.9 D increase untreated)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
7 | P a g e

drprabhatdevkota@gmail.com
D.Amblyopia (Pharmacologic Penalization)
Cycloplegic blur in better eye → forces use of amblyopic eye
Used for moderate/mild amblyopia (VA>20/100)
E. Other Uses: Malignant Glaucoma, NVG, Corneal Ulcer/keratitis
Systemic Uses:
• Symptomatic bradycardia – increases heart rate by blocking vagal stimulation.
• Organophosphate / carbamate poisoning – antagonizes muscarinic effects (salivation,
bronchorrhea, bradycardia).
• Pre-anesthetic / during anesthesia – reduces secretions (saliva, bronchial) and prevents
vagal-induced bradycardia.
Adverse Effects
A. Ocular
• Local irritation, allergic dermatitis (eyelids), papillary conjunctivitis, keratitis
• Angle-closure glaucoma risk → rare in normal eyes; IOPelevation unpredictable in
open-angle glaucoma
• Mydriasis → photophobia, glare
B. Systemic
• Rapid systemic absorption → dose-dependent toxicity
• Peripheral effects (low dose): dry mouth, depressed salivation, facial flushing,
inhibited sweating
• Central effects (high dose): restlessness, hallucinations, somnolence, convulsions
• Children <3 years, Down syndrome, or neurologically impaired → higher sensitivity
Systemic Reactions to Atropine in Children:
Diffuse cutaneous flush, Depressed salivation/thirst, Fever, Urinary retention, Tachycardia,
Somnolence, Excitement/restlessness and hallucinations, Speech disturbances, Ataxia,
Convulsion
Contraindications
• Hypersensitivity to belladonna alkaloids
• Open-angle or angle-closure glaucoma
• Known IOPelevation tendency
• Caution: infants, small children, elderly, Down syndrome
Treatment of Overdose
• Mainly supportive: hydration, temperature control
• Severe/life-threatening: Physostigmine (anticholinesterase)
• Adults: 1–2 mg IVslowly, may repeat every 30 min if needed
• Children: 0.02 mg/kg IM/slow IV, max 0.5 mg/min, repeat up to 2 mg
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
8 | P a g e
drprabhatdevkota@gmail.com
High-Yield Exam Pearls
• Most potent cycloplegic and mydriatic agent
• Mydriasis lasts up to 10 days, cycloplegia 7–12 days
• Topical atropine: rapid systemic absorption → caution in children & elderly
• Used in latent hyperopia, accommodative esotropia, uveitis, myopia control, and
pharmacologic amblyopia therapy
• Overdose → CNS effects and death in young children possible
• Physostigmine is the antidote for severe toxicity
ATOM (Atropine for the Treatment of Myopia) Study
Mechanism of Action (MOA)
• Atropine → increases retinal dopamine activity (proposed mechanism)
• ↓ Axial elongation of the eyeball
• ↓ Myopia progression
ATOM I (2006)
Study Design
• 1% atropine vs placebo
• Duration: 2 years
Key Findings
• ↓ Myopia progression (~77% reduction)
• ↓ Axial length elongation
• Highly effective but associated with significant adverse effects
Adverse Effects
• Photophobia
• Near vision blur (loss of accommodation)
• Allergic conjunctivitis/dermatitis (occasionally)
Limitation
• Marked rebound phenomenon after stopping treatment
ATOM II (2012)
Study Design
• Compared 0.5%, 0.1%, and 0.01% atropine
• Duration: 2 years treatment + washout
Key Findings
• 0.01% atropine had:
o Least adverse effects
o Least rebound after discontinuation
o Better long-term efficacy despite slightly less initial effect
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
9 | P a g e
drprabhatdevkota@gmail.com
HOMATROPINE
Pharmacology
• Class: Nonselective muscarinic antagonist (anticholinergic)
• Source: Partly synthetic; derived from Solanaceae family (like atropine)
• Potency: ~1/10th as potent as atropine
• pKa: 9.88 → ~0.32% un-ionized at physiological pH → limited corneal penetration
• Stability: Quite stable in solution
• Commercial Formulations: Hydrobromide salt, 2% and 5% ophthalmic solution
Ocular Pharmacokinetics
• Mydriasis: Maximum effect ~40 minutes after 1% solution
• Duration: Pupil recovery 1–3 days
• Cycloplegia: Less than atropine, more prolonged than cyclopentolate; weak in dark
irides
Clinical Uses
• Anterior uveitis – reduces ciliary spasm, prevents posterior synechiae
• Not preferred for:
• Cycloplegic refraction (weak cycloplegia)
• Fundus examination (prolonged mydriasis in dark irides)
Side Effects
• Similar to atropine:
• Ocular: irritation, allergic reactions, mydriasis, blurred near vision
• Systemic (rare with topical use): CNS toxicity, especially in elderly
• Toxicity managed like atropine overdose
Contraindications
• Hypersensitivity to belladonna alkaloids
• History of glaucoma (angle-closure or open-angle)
• Caution in infants, elderly, and nursing mothers (small amounts excreted in breast milk;
considered compatible with breastfeeding)
Exam Pearls
• Shorter-acting and less potent than atropine → useful when moderate cycloplegia and
mydriasis is needed
• Preferred over atropine when less systemic toxicity is desired
• Weak cycloplegic effect → not suitable for fundus exams or refraction in children
• Main use: anterior uveitis management
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
10 | P a g e
drprabhatdevkota@gmail.com
TROPICAMIDE
Class / Pharmacology
• Synthetic derivative of tropic acid.
• Nonselective muscarinic antagonist; may have moderate M4 receptor selectivity.
• pKa: 5.37 → ~2.3% ionized at physiologic pH → high corneal penetration (better
than atropine, homatropine, cyclopentolate).
• Commercial forms: 0.25%, 0.5%, 1% solutions.
• Fast onset and short duration compared with other anticholinergics.
MOA: Tropicamide is a short-acting competitive M3 muscarinic antagonist that blocks
parasympathetic input to the iris sphincter (→ mydriasis) and ciliary muscle (→ cycloplegia),
causing unopposed sympathetic dilation and loss of accommodation.
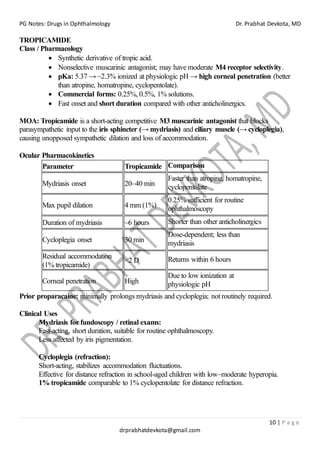
Ocular Pharmacokinetics
Parameter Tropicamide Comparison
Mydriasis onset 20–40 min
Faster than atropine, homatropine,
cyclopentolate
Max pupil dilation 4 mm (1%)
0.25% sufficient for routine
ophthalmoscopy
Duration of mydriasis ~6 hours Shorter than other anticholinergics
Cycloplegia onset 30 min
Dose-dependent; less than
mydriasis
Residual accommodation
(1% tropicamide)
<2 D Returns within 6 hours
Corneal penetration High
Due to low ionization at
physiologic pH
Prior proparacaine: minimally prolongs mydriasis and cycloplegia; not routinely required.
Clinical Uses
Mydriasis for fundoscopy / retinal exams:
Fast-acting, short duration, suitable for routine ophthalmoscopy.
Less affected by iris pigmentation.
Cycloplegia (refraction):
Short-acting, stabilizes accommodation fluctuations.
Effective for distance refraction in school-aged children with low–moderate hyperopia.
1% tropicamide comparable to 1% cyclopentolate for distance refraction.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
11 | P a g e
drprabhatdevkota@gmail.com
Combination therapies:
0.25% tropicamide + 1% hydroxyamphetamine (Paremyd) → optimal dilation with minimal
cycloplegia.
Alternative: 0.5% tropicamide + 2.5% phenylephrine.
Research / diagnostic use:
Evaluated in early detection ofAlzheimer’s and Parkinson’s via pupillary response
(experimental).
Side Effects
Ocular:
Transient stinging on instillation.
May increase IOPin open-angle glaucoma; usually small, but can exceed 10 mm Hg in some.
Systemic:
Rapid absorption but low affinity for systemic muscarinic receptors → systemic reactions
rare.
Is generally safe in patients with cardiovascular disease or neonates.
Rare acute hypersensitivity / syncope reported (mostly children).
Contraindications
• Hypersensitivity to belladonna alkaloids (cross-reactivity possible).
• Narrow anterior chamber angles → risk of angle-closure glaucoma, though low
(~0.03–0.3% in screened adults).
• Caution in glaucoma patients (recheck IOPpost-dilation).
Exam Pearls
• Tropicamide has greater mydriatic than cycloplegic effect, fast onset, short duration →
drug of choice for routine fundus exams.
• Cycloplegia: dose-dependent; short-acting, less suitable for latent hyperopia testing in
children.
• Paremyd (0.25% tropicamide + 1% hydroxyamphetamine) → clinically useful mydriasis
with minimal effect on accommodation.
• Safe in cardiovascular disease; rare systemic toxicity.
• Useful in school-aged children for distance refraction; faster recovery than cyclopentolate
or homatropine.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
12 | P a g e
drprabhatdevkota@gmail.com
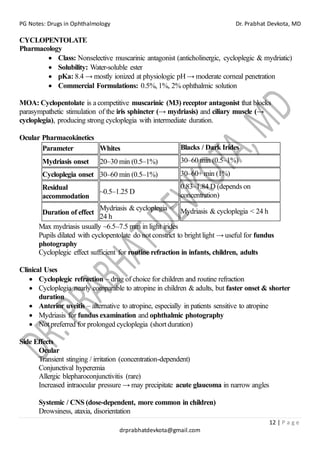
CYCLOPENTOLATE
Pharmacology
• Class: Nonselective muscarinic antagonist (anticholinergic, cycloplegic & mydriatic)
• Solubility: Water-soluble ester
• pKa: 8.4 → mostly ionized at physiologic pH → moderate corneal penetration
• Commercial Formulations: 0.5%, 1%, 2% ophthalmic solution
MOA: Cyclopentolate is a competitive muscarinic (M3) receptor antagonist that blocks
parasympathetic stimulation of the iris sphincter (→ mydriasis) and ciliary muscle (→
cycloplegia), producing strong cycloplegia with intermediate duration.
Ocular Pharmacokinetics
Parameter Whites Blacks / Dark Irides
Mydriasis onset 20–30 min (0.5–1%) 30–60 min (0.5–1%)
Cycloplegia onset 30–60 min (0.5–1%) 30–60+ min (1%)
Residual
accommodation
~0.5–1.25 D
0.83–1.84 D (depends on
concentration)
Duration of effect
Mydriasis & cycloplegia <
24 h
Mydriasis & cycloplegia < 24 h
Max mydriasis usually ~6.5–7.5 mm in light irides
Pupils dilated with cyclopentolate do not constrict to bright light → useful for fundus
photography
Cycloplegic effect sufficient for routine refraction in infants, children, adults
Clinical Uses
• Cycloplegic refraction – drug of choice for children and routine refraction
• Cycloplegia nearly comparable to atropine in children & adults, but faster onset & shorter
duration
• Anterior uveitis – alternative to atropine, especially in patients sensitive to atropine
• Mydriasis for fundus examination and ophthalmic photography
• Not preferred for prolonged cycloplegia (short duration)
Side Effects
Ocular
Transient stinging / irritation (concentration-dependent)
Conjunctival hyperemia
Allergic blepharoconjunctivitis (rare)
Increased intraocular pressure → may precipitate acute glaucoma in narrow angles
Systemic / CNS (dose-dependent, more common in children)
Drowsiness, ataxia, disorientation
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
13 | P a g e
drprabhatdevkota@gmail.com
Incoherent speech, restlessness, visual/tactile hallucinations
Psychotic reactions (children, 2% solution)
Rare: grand mal seizures (especially in neurologically impaired children or with concomitant
drugs)
Peripheral atropine-like effects (flushing, dry mucous) are rare
Contraindications
• Infants, young children → avoid >0.5% solution
• Children with spastic paralysis or brain damage
• Known hypersensitivity to cyclopentolate
• Narrow-angle or open-angle glaucoma
• Caution: systemic absorption reduced by nasolacrimal occlusion
Exam Pearls
• Cyclopentolate is first-line for routine cycloplegic refraction in children
• Faster onset and shorter duration than atropine → useful for outpatient refractions
• Dark irides require higher concentration or repeated doses for adequate cycloplegia
• CNS toxicity is dose-dependent; children are more susceptible
• Toxicity treatment is same as atropine
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
14 | P a g e
drprabhatdevkota@gmail.com
MYDRIATICS
PHENYLEPHRINE
Class: Synthetic sympathomimetic amine (α1-adrenergic agonist)
MOA:
Stimulates α1 receptors → contracts iris dilator → mydriasis
Constricts conjunctival arterioles → blanching of conjunctiva
Stimulates Müller’s muscle → widens palpebral fissure
Minimal β-receptor effect
Minor effect via norepinephrine release from adrenergic nerve terminals
IOP Effect: May decrease IOP in normal & open-angle glaucoma eyes
Pregnancy Category: C
Stability: Oxidizes on exposure to air, light, or heat → antioxidants like sodium bisulfite added
Preparations
Concentration Common Use
2.5% Routine mydriasis, infants, elderly
10%
Breaking posterior synechiae, peripheral vessel vasoconstriction
during LASIK, diagnostic in Horner’s syndrome
Shelf-life: Sensitive to light, heat, air; store per manufacturer instructions
Pharmacokinetics & Mydriasis
• Onset: 45–60 min
• Duration: 6–7 hours
• Effect on accommodation: Minimal (~1–2 D loss vs cycloplegics)
• Response influenced by:
• Iris color (poorer dilation in dark irides)
• Corneal integrity (enhanced after trauma or anesthetic)
• Combination with tropicamide → faster, more convenient mydriasis
Clinical Uses
• Diagnostic Mydriasis – routine fundus exam or photography
• Breaking posterior synechiae – typically 10% with topical anesthetic
• Peripheral corneal vessel constriction – e.g., during LASIK
• Prevention of miotic cysts – with echothiophate therapy in glaucoma or accommodative
esotropia
• Ptosis management / Horner’s syndrome test – 1% solution for denervation hypersensitivity
Side Effects
Ocular
• Transient stinging, pain, lacrimation
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
15 | P a g e
drprabhatdevkota@gmail.com
• Keratitis
• Pigmented aqueous floaters (age & iris color-dependent, disappear in 12–24 h)
• Rebound miosis or conjunctival congestion
• Conjunctival hypoxia
• Allergic dermatoconjunctivitis (“scalded” appearance)
Systemic (more common with 10% or multiple doses)
• Hypertension → acute rise in systolic & diastolic BP
• Tachycardia or reflex bradycardia
• Occipital headache
• Ventricular arrhythmias, subarachnoid hemorrhage
• Skin blanching
• High-risk groups: elderly, neonates, cardiac disease, insulin-dependent diabetes,
idiopathic orthostatic hypotension
Drug interactions:
Avoid with MAO inhibitors, tricyclic antidepressants, reserpine, guanethidine,
methyldopa
Caution with atropinized patients → enhanced pressor effect
Contraindications / Precautions
• 10% phenylephrine: use with caution in:
• Cardiac disease, hypertension, aneurysms, advanced arteriosclerosis
• Infants, elderly → only 2.5% recommended
• Single drop per hour per eye; avoid prolonged or repeated use
• Avoid in combination with MAO inhibitors, TCA, reserpine, guanethidine,
methyldopa
• Avoid in patients previously atropinized
Exam Pearls
• Phenylephrine does not produce significant cycloplegia → mainly mydriatic
• 2.5% is routine safe concentration, 10% reserved for specific therapeutic/diagnostic use
• Iris color & corneal integrity influence drug efficacy
• Useful in Horner’s syndrome diagnosis – 1% phenylephrine shows dilation only in
postganglionic lesions
• Systemic absorption risks increase with: age extremes, compromised health, high
concentration, multiple drops
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
16 | P a g e
drprabhatdevkota@gmail.com
MIOTICS
Pilocarpine
Available Concentrations: 0.5%, 1%, 2%, 4%, 6%
Drug Class
• Direct-acting muscarinic cholinergic agonist (parasympathomimetic)
Receptor Action
• Stimulates M1, M2, M3, M4, and M5 muscarinic receptors
Mechanism ofAction
• Iris sphincter contraction → Miosis
• Ciliary muscle contraction → Spasm of accommodation
• Contraction of longitudinal ciliary muscle → Pulls scleral spur → Opens trabecular meshwork
→ ↑ Conventional aqueous outflow → ↓ Intraocular pressure (IOP)
Pharmacokinetics
Parameter Value
Onset ~15 minutes
Peak effect 30–60 minutes
Duration ~4 hours
Indications
• Primary open-angle glaucoma (POAG)
• Acute angle-closure glaucoma (AACG) (after initial IOP reduction)
• Secondary glaucoma
• Before laser peripheral iridotomy (LPI)
• Reversal of pharmacologic mydriasis (occasionally)
Adverse Effects
Ocular
• Miosis
• Accommodative spasm
• Brow ache/headache
• Conjunctival hyperemia
• Lid myokymia
• Reduced night vision
• Retinal detachment (rare; especially in high myopes)
Systemic (SLUDGE Syndrome)
• S – Salivation
• L – Lacrimation
• U – Urination
• D – Diarrhea
• G – Gastrointestinal cramps
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
17 | P a g e
drprabhatdevkota@gmail.com
• E – Emesis (nausea/vomiting)
Additional:
• Bradycardia
• Hypotension
• Bronchospasm
• Sweating
Contraindications
• Significant cataract (especially PSC/NS)
• Young patients (<40 years)
• Neovascular glaucoma (NVG)
• Uveitic glaucoma
• High myopia (↑ risk of retinal detachment)
• Bronchial asthma/COPD
• Hypersensitivity
• Caution with succinylcholine anesthesia (prolonged neuromuscular blockade)
Pilocarpine Preparation
➢ 0.125% Pilocarpine
Preparation
• 1 mL of 1% pilocarpine
•
o 7 mL normal saline/artificial tears
• = 8 mL of 0.125% pilocarpine
Use
• Diagnosis ofAdie's tonic pupil (denervation supersensitivity)
➢ 0.1% Pilocarpine
Preparation
• 1 mL of 1% pilocarpine
•
o 9 mL normal saline
• = 10 mL of 0.1% pilocarpine
Use
• Evaluation of anisocoria, particularly when assessing cholinergic
supersensitivity.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
18 | P a g e
drprabhatdevkota@gmail.com
CORTICOSTEROIDS
Mechanism ofAction (MOA)
Genomic Action
Bind cytoplasmic glucocorticoid receptors
Steroid–receptor complex → nucleus → modulates gene transcription
↑ Anti-inflammatory proteins (lipocortin/annexin-1)
↓ Pro-inflammatory genes
CoreAnti-inflammatory Effects
Inhibit phospholipase A2 → ↓ arachidonic acid → ↓ prostaglandins & leukotrienes
↓ Cytokines (IL-1, IL-2, TNF-α)
↓ Capillary permeability & edema
↓ Leukocyte adhesion & migration
Stabilize lysosomal membranes
↓ Fibroblast proliferation & collagen synthesis
Exam Pearl: Steroids act upstream of NSAIDs in the arachidonic acid pathway.
Indications in Ophthalmology
1. Eyelids
Allergic blepharitis
Contact dermatitis
Herpes zoster dermatoblepharitis
Chemical burns
Neonatal hemangioma
2.Conjunctiva
Allergic conjunctivitis
Vernal keratoconjunctivitis
Herpes zoster conjunctivitis
Chemical burns
Mucocutaneous conjunctival lesions
3.Cornea
Immune keratoplasty rejection
Disciform keratitis
Marginal infiltrates
Interstitial keratitis
Acne rosacea keratitis
Chemical burns
Avoid in active epithelial HSV keratitis
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
19 | P a g e
drprabhatdevkota@gmail.com
4.Uvea
Anterior uveitis
Posterior uveitis
Sympathetic ophthalmia
5.Sclera
Scleritis
Episcleritis
6.Retina
Retinal vasculitis
7.Optic Nerve
Optic neuritis
Temporal arteritis (systemic steroids emergency)
8.Orbit
Orbital pseudotumor
Graves’ophthalmopathy
9.Extraocular Muscles
Ocular myasthenia gravis
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
20 | P a g e
drprabhatdevkota@gmail.com
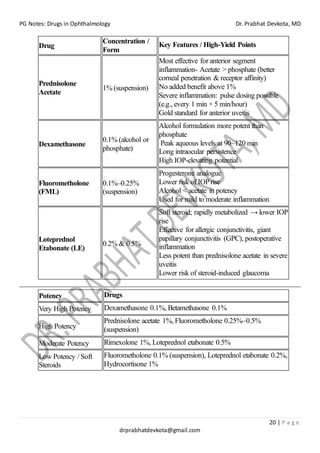
Drug
Concentration /
Form
Key Features / High-Yield Points
Prednisolone
Acetate
1% (suspension)
Most effective for anterior segment
inflammation- Acetate > phosphate (better
corneal penetration & receptor affinity)
No added benefit above 1%
Severe inflammation: pulse dosing possible
(e.g., every 1 min × 5 min/hour)
Gold standard for anterior uveitis
Dexamethasone
0.1% (alcohol or
phosphate)
Alcohol formulation more potent than
phosphate
Peak aqueous levels at 90–120 min
Long intraocular persistence
High IOP-elevating potential
Fluorometholone
(FML)
0.1%–0.25%
(suspension)
Progesterone analogue
Lower risk of IOPrise
Alcohol < acetate in potency
Used for mild to moderate inflammation
Loteprednol
Etabonate (LE)
0.2% & 0.5%
Soft steroid; rapidly metabolized → lower IOP
rise
Effective for allergic conjunctivitis, giant
papillary conjunctivitis (GPC), postoperative
inflammation
Less potent than prednisolone acetate in severe
uveitis
Lower risk of steroid-induced glaucoma
Potency Drugs
Very High Potency Dexamethasone 0.1%, Betamethasone 0.1%
High Potency
Prednisolone acetate 1%, Fluorometholone 0.25%–0.5%
(suspension)
Moderate Potency Rimexolone 1%, Loteprednol etabonate 0.5%
Low Potency / Soft
Steroids
Fluorometholone 0.1% (suspension), Loteprednol etabonate 0.2%,
Hydrocortisone 1%
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
21 | P a g e
drprabhatdevkota@gmail.com
Ocular Side Effects
Posterior Subcapsular Cataract (PSC)
Dose & duration dependent
Risk increases:
15 mg/day systemic prednisone
Long-term topical use
Children more susceptible
Often irreversible
Mechanism (theory):
Steroid binds lens crystallins → sulfhydryl exposure → protein aggregation
Steroid-Induced Glaucoma
Onset: 2–8 weeks
Reversible after stopping
Higher risk:
POAG patients
First-degree relatives
High myopes (>5D)
Children
Potency for IOPrise:
Dexamethasone > Prednisolone > FML ≈ Rimexolone > Loteprednol
Mechanism:
↓ Trabecular outflow
↑ Glycosaminoglycans
Cytoskeletal changes in trabecular meshwork
↓ Phagocytosis
Infection Risk
Steroids:
Suppress immunity
Mask symptoms
Never use alone in active infection.
High-risk infections:
Fungal keratitis
HSV epithelial keratitis
Bacterial infections (if no scarring risk, avoid)
Delayed Corneal Healing
↓ Fibroblast activity
↓ Collagen synthesis
Risk of corneal melt
Scleral thinning
Steroid-induced Uveitis (Rare)
More common in blacks
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
22 | P a g e
drprabhatdevkota@gmail.com
AC cells + flare
Stop steroid → improvement
Mydriasis & Ptosis
Reversible
Possibly vehicle-related effect
Calcific Band Keratopathy
Seen with phosphate formulations
Systemic Side Effects (Especially with systemic/periocular use)
Head to Toe
CNS
o Mood changes (euphoria, irritability)
o Depression
o Steroid psychosis
o Insomnia
o Pseudotumor cerebri (children)
o Seizures (rare)
Eye
o Posterior subcapsular cataract (PSC)
o Steroid-induced glaucoma
o Delayed wound healing
o Increased risk of infections (HSV, fungal)
Cardiovascular
o Hypertension
o Fluid retention
o Edema
o Exacerbation of heart failure
o Dyslipidemia
o Accelerated atherosclerosis (long-term)
Respiratory
o Increased susceptibility to infections
o Reactivation ofTB
Gastrointestinal
o Gastritis
o Peptic ulcer disease
o GI bleeding
o Pancreatitis (rare)
o Hepatic steatosis (long-term)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
23 | P a g e
drprabhatdevkota@gmail.com
Hematologic / Immune
o Immunosuppression
o Masking of infection
o Leukocytosis (neutrophilia)
o Poor vaccine response
Musculoskeletal
o Osteoporosis (most important)
o Pathological fractures
o Avascular necrosis (femoral head)
o Proximal myopathy
o Growth retardation (children)
Endocrine / Metabolic
o Cushingoid features (moon face, buffalo hump)
o Hyperglycemia / Steroid-induced Diabetes
o Adrenal suppression
o Growth suppression
o Weight gain
o Negative nitrogen balance
Skin
o Skin thinning
o Striae
o Acne
o Easy bruising
o Delayed wound healing
o Hirsutism
Electrolyte / Renal
o Sodium retention
o Hypokalemia
o Fluid retention
Reproductive
o Menstrual irregularities
o Decreased fertility (long-term)
Very High-Yield Exam Pearls
• Most common serious complication: Osteoporosis
• Classic cataract: Posterior subcapsular cataract
• Classic glaucoma: Steroid-induced open-angle glaucoma
• Abrupt withdrawal →Acute adrenal crisis
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
24 | P a g e
drprabhatdevkota@gmail.com
• Long-term use → Cushing’s syndrome
Contraindications
Absolute
Active epithelial HSVkeratitis
Untreated fungal infection
Active TB
Relative
Glaucoma
Diabetes
Hypertension
CHF
Peptic ulcer
Osteoporosis
Psychosis
Drug interactions:
MAO inhibitors
Phenytoin, barbiturates → increase steroid metabolism
Reduce anticoagulant effect
Monitoring Protocol
Patients on topical steroids:
Check IOP every 2–4 weeks
Slit lamp for:
Dendrites
Fungal keratitis
PSC
Long-term → lens & optic nerve evaluation
Systemic therapy:
BP
Blood glucose
Bone density
Cataract screening
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
25 | P a g e
drprabhatdevkota@gmail.com
GENERAL PRINCIPLES OF PREPARATION
Reconstitution
Converting a dry powder (vial) into a liquid solution by adding sterile water or sterile saline.
Example:
Amphotericin B 50 mg vial + 10 mL sterile water → 5 mg/mL solution
Purpose: To make the drug usable for topical or systemic use
Key Points:
No change in drug concentration beyond the simple solution
Done for injectables or powders
Fortification
The use of reformulations of parenteral antibiotics as eye drops with non-marketed
composition or concentrations.
Increasing the concentration of a drug above its standard commercial preparation for severe
infections (especially corneal infections).
Example:
Tobramycin commercial drops 0.3% (3 mg/mL) → fortified to 1.4% (14 mg/mL) using
injectable Tobramycin 40 mg/mL
Purpose: To achieve higher therapeutic levels in the cornea
Key Points:
Usually done with injectables, not commercial drops (if concentration needs to increase)
Must be prepared aseptically
Stored refrigerated at 2–8°C, short shelf-life (≈7 days)
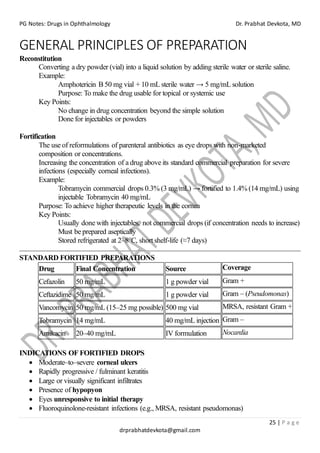
STANDARD FORTIFIED PREPARATIONS
Drug Final Concentration Source Coverage
Cefazolin 50 mg/mL 1 g powder vial Gram +
Ceftazidime 50 mg/mL 1 g powder vial Gram – (Pseudomonas)
Vancomycin 50 mg/mL (15–25 mg possible) 500 mg vial MRSA, resistant Gram +
Tobramycin 14 mg/mL 40 mg/mL injection Gram –
Amikacin 20–40 mg/mL IV formulation Nocardia
INDICATIONS OF FORTIFIED DROPS
• Moderate–to–severe corneal ulcers
• Rapidly progressive / fulminant keratitis
• Large or visually significant infiltrates
• Presence of hypopyon
• Eyes unresponsive to initial therapy
• Fluoroquinolone-resistant infections (e.g., MRSA, resistant pseudomonas)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
26 | P a g e
drprabhatdevkota@gmail.com
• Post-trabeculectomy blebitis
• Endophthalmitis
• Pediatric ocular infections (higher bacterial frequency)
• When higher drug concentration is required
Preparation & Handling
• Organism-directed selection is essential.
• Prepare under strict aseptic conditions (preferably laminar airflow).
• Compounded by a doctor/pharmacist using a sterile disposable syringe.
• Label preparation & expiry dates clearly.
• Educate patient regarding dose and storage.
• Shake before instillation.
Storage & Stability (MCQ Favourite)
• Store at 2–8°C (≈4°C).
• Preservative-free → short shelf life.
• Discard after 7 days.
• Minimize contamination with proper handling.
Advantages
• Achieve high stromal drug levels.
• Provide bactericidal concentrations.
• Particularly effective in deep or severe ulcers.
Limitations
• Ocular surface / epithelial toxicity possible.
• Require frequent dosing.
• Dependence on refrigeration.
• Limited shelf life.
• Epithelial toxicity.
• Aminoglycosides & vancomycin → delayed epithelial healing.
• Causes retarded corneal re-epithelialization
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
27 | P a g e
drprabhatdevkota@gmail.com
Common Topical Preparations
Cefazolin 50 mg/mL (5%) --------same for Ceftazidime 50 mg/mL (5%)
Preparation
• 500 mg Cefazolin powder + 10 mL sterile distilled water (DW)
= 50 mg/mL (5%)
OR
• 250 mg Cefazolin powder + 5 mL sterile distilled water (DW)
= 50 mg/mL (5%)
Store at 4°C, protect from light, use within 7 days
Vancomycin 15,25,50 mg/mL (1.5%,2.5%,,5%)
Method: To a 500 mg vial of vancomycin
Add 33 ml of 0.9% sodium chloride (no preservatives) to produce a solution of 15 mg/ml.
Add 20 ml of 0.9% sodium chloride (no preservatives) to produce a solution of 25 mg/ml.
Add 10 ml of 0.9% sodium chloride (no preservatives) to produce a solution of 50 mg/ml.
Storage: Refrigerate and shake well before instillation.
Tobramycin 14 mg/mL (1.4%) ----------- same for Gentamicin 14 mg/mL (1.4%)
Preparation
• Gentamicin/Tobramycin eye drops 0.3% (3 mg/mL) = 5 mL
o Drug content = 3 × 5 = 15 mg
• Add Gentamicin/Tobramycin injection (40 mg/mL) = 2 mL
o Drug content = 40 × 2 = 80 mg
Calculation
• Total drug = 15 + 80 = 95 mg
• Total volume = 5 + 2 = 7 mL
• Final concentration = 95 ÷ 7 = 13.5 mg/mL
• ≈ 1.35% (commonly referred to as 1.4% or 14 mg/mL)
Amikacin 40 mg/mL (4%)
Amikacin vial 100 mg powder
To obtain 40 mg/mL: Add 2.5 mL sterile water for injection
Especially effective for: Nocardia keratitis
Amphotericin B 0.15%
Reconstitute 50 mg vial of amphotericin B powder with 10 mL sterile water→ 5 mg/mL
Take 3 mL of 5 mg/mL solution
Add 7 mL sterile water / NS
Final volume = 10 mL
Final concentration = 1.5 mg/mL (0.15%)
Store at 4°C, protect from light, use within 7 days
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
28 | P a g e
drprabhatdevkota@gmail.com
Voriconazole (1%)
Take Voriconazole powder 200 mg
Reconstitute with 19 mLsterile water for injection
Final volume → 20 mL
Final concentration → 10 mg/mL (≈1%)
Storage: Refrigerate at 4°C and shake well before instillation
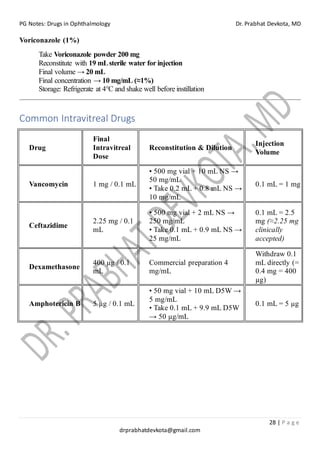
Common Intravitreal Drugs
Drug
Final
Intravitreal
Dose
Reconstitution & Dilution
Injection
Volume
Vancomycin 1 mg / 0.1 mL
• 500 mg vial + 10 mL NS →
50 mg/mL
• Take 0.2 mL + 0.8 mL NS →
10 mg/mL
0.1 mL = 1 mg
Ceftazidime
2.25 mg / 0.1
mL
• 500 mg vial + 2 mL NS →
250 mg/mL
• Take 0.1 mL + 0.9 mL NS →
25 mg/mL
0.1 mL = 2.5
mg (≈2.25 mg
clinically
accepted)
Dexamethasone
400 µg / 0.1
mL
Commercial preparation 4
mg/mL
Withdraw 0.1
mL directly (=
0.4 mg = 400
µg)
Amphotericin B 5 µg / 0.1 mL
• 50 mg vial + 10 mL D5W →
5 mg/mL
• Take 0.1 mL + 9.9 mL D5W
→ 50 µg/mL
0.1 mL = 5 µg
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
29 | P a g e
drprabhatdevkota@gmail.com
ANTIBACTERIAL AGENTS
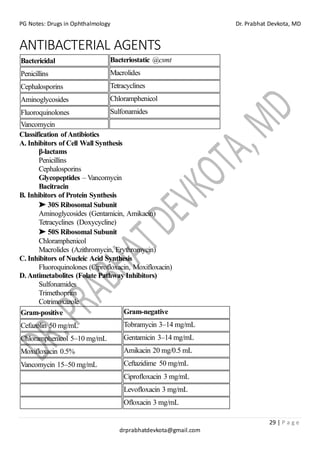
Bactericidal Bacteriostatic @csmt
Penicillins Macrolides
Cephalosporins Tetracyclines
Aminoglycosides Chloramphenicol
Fluoroquinolones Sulfonamides
Vancomycin
Classification ofAntibiotics
A. Inhibitors of Cell Wall Synthesis
β-lactams
Penicillins
Cephalosporins
Glycopeptides – Vancomycin
Bacitracin
B. Inhibitors of Protein Synthesis
➤ 30S Ribosomal Subunit
Aminoglycosides (Gentamicin, Amikacin)
Tetracyclines (Doxycycline)
➤ 50S Ribosomal Subunit
Chloramphenicol
Macrolides (Azithromycin, Erythromycin)
C. Inhibitors of Nucleic Acid Synthesis
Fluoroquinolones (Ciprofloxacin, Moxifloxacin)
D.Antimetabolites (Folate Pathway Inhibitors)
Sulfonamides
Trimethoprim
Cotrimoxazole
Gram-positive Gram-negative
Cefazolin 50 mg/mL Tobramycin 3–14 mg/mL
Chloramphenicol 5–10 mg/mL Gentamicin 3–14 mg/mL
Moxifloxacin 0.5% Amikacin 20 mg/0.5 mL
Vancomycin 15–50 mg/mL Ceftazidime 50 mg/mL
Ciprofloxacin 3 mg/mL
Levofloxacin 3 mg/mL
Ofloxacin 3 mg/mL
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
30 | P a g e
drprabhatdevkota@gmail.com
A. Beta-Lactams: Inhibit bacterial cell wall peptidoglycan synthesis → bactericidal
Cephalosporins
1st Gen: Cephalexin, Cephradine, Cefadroxil, Cefazolin
2nd Gen: Cefaclor, Cefprozil, Cefuroxime, Cefoxitin, Cefotetan
3rd Gen: Cefixime, Cefdinir, Cefotaxime, Ceftriaxone, Ceftazidime
4th Gen: Cefepime
5th Gen: Ceftaroline, Ceftobiprole
Mechanism ofAction (MOA)
Bactericidal
β-lactam antibiotics
Inhibit bacterial cell wall synthesis
Bind penicillin-binding proteins (PBPs) → prevent peptidoglycan cross-linking → weak
cell wall → bacterial lysis
Spectrum ofActivity: Active mainly against GPC and GNB
• Cefazolin (1G) Fortified 5% topical
Gram-Positive: MSSA (Methicillin-sensitive Staph aureus), Streptococcus spp. (S. pyogenes,
S. pneumoniae – penicillin-sensitive)
Gram-Negative: Limited/modest
• Ceftazidime (3G) Intravitreal 2.25 mg/0.1 mL
Gram-Negative: Pseudomonas aeruginosa, Moderate coverage of Enterobacteriaceae
Gram-Positive: Limited/reduced activity
Indications
• Bacterial Corneal Ulcers
• Gonococcal Ophthalmia Neonatorum
• Preseptal Or Orbital Cellulitis
• Bacterial Endophthalmitis
Adverse Effects
Ocular ADRs: Rare; mild irritation
Systemic ADRs:
Hypersensitivity: rash, urticaria, fever, bronchospasm, anaphylaxis
GI upset: nausea, vomiting, diarrhea
C. difficile colitis
Joint/skin reactions
Renal impairment
Vitamin K deficiency → bleeding
Contraindications
Known cephalosporin allergy or penicillin allergy
Hemophilia
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
31 | P a g e
drprabhatdevkota@gmail.com
B. Glycopeptides
Vancomycin 50 mg/mL eye drops (fortified) / Intravitreal solution
Mechanism ofAction (MOA)
Bactericidal
Inhibits bacterial cell wall synthesis
Binds to D-Ala-D-Ala terminus of peptidoglycan precursors→ Prevents cross-linking of
peptidoglycan → weak cell wall → bacterial lysis
Spectrum ofActivity
Gram-Positive: Staphylococcus aureus (MRSA), Staphylococcus epidermidis, Streptococcus
pneumoniae, Enterococcus spp.
(Highly active against Gram-positive bacteria, including MRSA and penicillin-resistant S.
pneumoniae)
Anaerobes: Clostridium difficile
Not active against Gram-negative bacteria
Indications
• Bacterial Endophthalmitis
• Ocular infections caused by MRSA or penicillin-resistant streptococci
• Moderate to severe Preseptal Cellulitis (systemic use)
• Serious infections when other antibiotics fail
Adverse Effects
Ocular ADRs (topical/intravitreal)
Irritation, burning, stinging (especially if not buffered)
Rare corneal epithelial toxicity at high concentrations
Systemic ADRs (IV/oral)
Nephrotoxicity
Ototoxicity → hearing loss, tinnitus, vertigo
“Red man syndrome” (rapid infusion) → flushing, hypotension
Rare hematologic effects: neutropenia, thrombocytopenia
Contraindications
• Known hypersensitivity or allergy
• Caution in patients with renal impairment, hearing disorders, or concurrent
ototoxic/nephrotoxic drugs
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
32 | P a g e
drprabhatdevkota@gmail.com
Bacitracin: Polypeptide antibiotic, Topical ointment (usually 500 units/g)
Mechanism ofAction (MOA)
Inhibits bacterial cell wall synthesis by blocking dephosphorylation of bactoprenol
Bactericidal against Gram-positive bacteria
Spectrum ofActivity
Gram-Positive: Staphylococcus aureus (including some MRSA), Streptococcus spp,
Corynebacteria
Gram-Negative: Minimal / negligible activity
Ocular Indications
• Superficial bacterial conjunctivitis (mild cases)
• Blepharitis (Staph-related)
• Prophylaxis after minor ocular trauma or suture sites
• Often used in combination with neomycin or polymyxin B
Adverse Effects
• Ocular irritation, itching, burning
• Rare hypersensitivity reactions
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
33 | P a g e
drprabhatdevkota@gmail.com
C.Aminoglycosides
Gentamicin 0.3% eye drops / 0.3% ointment
Tobramycin 0.3% eye drops / 0.3% ointment
Neomycin 0.5%–1% ophthalmic ointment
Amikacin (used intravitreally / fortified for corneal ulcers)
Mechanism ofAction (MOA)
• Bactericidal → inhibits protein synthesis
• Binds to 30S ribosomal subunit
• Causes misreading of mRNA → defective proteins → bacterial death
• Synergistic effect with β-lactams or vancomycin against gram-positive and gram-negative
bacteria
Spectrum ofActivity
Gram-Positive: Staphylococcus aureus, Streptococci & Enterococci
Gram-Negative: Pseudomonas aeruginosa, E. coli, Klebsiella, Proteus, Enterobacter, Serratia
Indications
• Bacterial conjunctivitis
• Blepharitis
• Keratoconjunctivitis / Corneal ulcers (fortified drops)
• Empiric therapy for Pseudomonas corneal ulcers (gentamicin or tobramycin + cefazolin)
• Endophthalmitis (amikacin intravitreal for gram-negative coverage)
Adverse Effects
Ocular ADRs
• Punctate epithelial erosions / corneal toxicity
• Delayed epithelial healing
• Conjunctival hyperemia, chemosis
• Rare allergic reactions (cross-reactivity with neomycin ~50%)
Systemic ADRs
• Nephrotoxicity
• Ototoxicity
• Pseudotumor cerebri
• Retinal damage after intravitreal gentamicin (macular infarction)
Contraindications
• Hypersensitivity
• Use caution in renal impairment (systemic use)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
34 | P a g e
drprabhatdevkota@gmail.com
D. Tetracyclines
Tetracycline 1% ophthalmic ointment, Doxycycline 100 mg oral
Mechanism of Action (MOA)
• Bacteriostatic
• Binds to 30S ribosomal subunit → Blocks attachment of aminoacyl-tRNA to A site →
Inhibits addition of amino acids → ↓ protein synthesis
• Inhibits bacterial lipase production → ↓ free fatty acids in meibomian glands
• Inhibits matrix metalloproteinases (MMPs) → ↓ corneal collagenase activity
• Anti-inflammatory effect (↓ IL-1, TNF-α mediated damage)
• Anti-collagenolytic → prevents corneal melting
Spectrum of Activity
Gram-Positive: Staphylococcus, Streptococcus
Gram-Negative: H. influenzae, Vibrio cholerae, Brucella, Yersinia pestis
Atypical: Chlamydia (Drug of choice), Rickettsia (DOC) Mycoplasma pneumoniae), Borrelia
(Lyme disease)
Indications
Ocular Infectious
• Trachoma
• Chlamydial Inclusion conjunctivitis
• gonococcal ophthalmia neonatorum (Prophylaxis)
Ocular Non-Infectious
• Meibomianitis / MGD
• Acne rosacea
• Recurrent chalazion
• Phlyctenular keratoconjunctivitis
• Corneal melting / sterile corneal ulcer
• Persistent epithelial defects/ chemical injury
Adverse Effects
Ocular ADRs: Mild irritation / burning, Hypersensitivity reactions
Systemic ADRs
GI Effect: • Nausea, vomiting, • Diarrhea, • Esophagitis (especially doxycycline)
Photosensitivity
Teeth & Bone Effects: Tooth discoloration (yellow-brown), Enamel hypoplasia, Bone growth
suppression
Intracranial Hypertension & Papilledema
Contraindications
• Hypersensitivity
• Pregnancy (2nd & 3rd T)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
35 | P a g e
drprabhatdevkota@gmail.com
• Lactating
• Children < 8 years (tooth discoloration)
• Severe hepatic dysfunction
• Caution in renal impairment
Polymyxin B 0.1% (Polymyxins, Cationic polypeptide antibiotic)
Mechanism ofAction (MOA):
Bactericidal → disrupts bacterial cell membrane integrity
Cationic detergent → binds phospholipids in Gram-negative bacterial membranes →
Increases membrane permeability → osmotic imbalance → cell death
Spectrum ofActivity:
Gram-negative: P. aeruginosa, E. coli, Klebsiella, Proteus
Indications:
• External ocular infections (conjunctivitis, blepharitis)
• Prevent infection in corneal or conjunctival compromise
• Used in combination with other antibiotics or steroids for lid/conjunctival infections
• Topical prophylaxis with steroid therapy
Adverse Effects:
Ocular ADRs: Mild irritation, conjunctival hyperemia, allergic reactions of eyelid/conjunctiva
Subconjunctival injection: Pain, chemosis, tissue necrosis
Systemic ADRs: Rare with topical use; systemic use is neurotoxic and nephrotoxic
Contraindications:
Hypersensitivity or intolerance to Polymyxin B
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
36 | P a g e
drprabhatdevkota@gmail.com
E. Macrolides
Erythromycin 0.5%–1% ophthalmic ointment
Azithromycin 1% eye drops
Mechanism ofAction (MOA)
Bacteriostatic → inhibits bacterial protein synthesis
• Binds to 50S ribosomal subunit
• Prevents elongation of the peptide chain → blocks protein synthesis
Reduces Staphylococcus aureus colonization on eyelid margins
•Anti-inflammatory effect is secondary to reduction of bacterial load and exotoxin
production
Spectrum ofActivity
Gram-Positive: Streptococcus pyogenes, Streptococcus pneumoniae, Staphylococcus aureus
(except some MRSA)
Gram-Negative : H. influenzae, Moraxella catarrhalis, Chlamydia trachomatis / C.
pneumoniae, Mycoplasma pneumoniae, Borrelia burgdorferi
Indications
• Staphylococcal eyelid infections → erythromycin ointment
• Prophylaxis of ophthalmia neonatorum → erythromycin ointment
• Chlamydial conjunctivitis / Trachoma → oral erythromycin or azithromycin (single 1-g
dose in adults, 20 mg/kg in children)
Adverse Effects
Ocular ADRs
• Mild irritation with topical erythromycin or azithromycin drops
Systemic ADRs
• Gastrointestinal: nausea, vomiting, diarrhea, abdominal pain (most common)
• Headache, dizziness, dyspepsia
• Mild allergic reactions: urticaria, rashes, fever, eosinophilia
Contraindications
• Known hypersensitivity
• Clarithromycin: avoid in pregnancy unless no alternative therapy
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
37 | P a g e
drprabhatdevkota@gmail.com
F. Chloramphenicol 0.5% eye drops, 1% ointment
Mechanism ofAction (MOA)
Bacteriostatic
Binds to 50S ribosomal subunit
Inhibits peptidyl transferase enzyme
Blocks aminoacyl-tRNA binding
Prevents peptide bond formation → inhibits bacterial protein synthesis
Spectrum ofActivity
Gram-Positive: Streptococcus, Staphylococcus
Gram-Negative: H. influenzae, Neisseria, Enterobacteriaceae
Atypical Organisms: Rickettsia, Chlamydia, Mycoplasma, Spirochetes
Indications:
Bacterial conjunctivitis
Blepharitis
External ocular infections
Alternative when other antibiotics fail
Adverse Effects
Ocular ADRs:
Mild burning / stinging
Ocular irritation
Allergic conjunctivitis
Eyelid edema (rare)
Systemic ADR:
Bone marrow suppression: Anemia, leukopenia, thrombocytopenia
Idiosyncratic aplastic anemia
Hypersensitivity reactions
Contact dermatitis
Contraindications
h/o Hypersensitivity
Previous bone marrow suppression / blood dyscrasias
h/o aplastic anemia
Pre-existing hematologic disorders
Neonates (risk of systemic absorption → Gray baby syndrome)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
38 | P a g e
drprabhatdevkota@gmail.com
G. Fluoroquinolones
Generations:
1st: Nalidixic acid
2nd: Ciprofloxacin, Ofloxacin
3rd: Levofloxacin
4th: Moxifloxacin, Gatifloxacin (C8-methoxy, dual target → lower resistance)
Mechanism ofAction (MOA)
Rapidly inhibit bacterial DNAsynthesis → bactericidal
Target enzymes:
DNAgyrase (Topoisomerase II) → mainly in Gram-negative bacteria
Topoisomerase IV → mainly in Gram-positive bacteria
These enzymes maintain supercoiling and separation of DNAduring replication
Human cells lack these enzymes → selective toxicity
Spectrum ofActivity
Gram-Negative: Enterobacteriaceae, Haemophilus influenzae, Neisseria, Pseudomonas
(especially ciprofloxacin)
Gram-Positive: Staphylococcus aureus, Coagulase-negative Staph, Streptococcus (better with
3rd & 4th gen)
Why 4th Generation is Superior?
C8-methoxy group
Dual enzyme inhibition
Requires 2 mutations for resistance
Enhanced Gram-positive activity
Maintains Gram-negative potency
Side Effects
Burning/stinging
Bitter taste
Conjunctival hyperemia
Foreign body sensation
Ciprofloxacin-Specific:
White corneal precipitates
Bandage contact lens deposits
Mild epithelial cytotoxicity (minimal clinically)
Pediatric use: Avoid <2 years
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
39 | P a g e
drprabhatdevkota@gmail.com
ANTIFUNGAL AGENTS
Indications
Filamentous fungi (Aspergillus, Fusarium): Natamycin 5% (drug of choice), Amphotericin B 0.15–
0.3%, Voriconazole 1%
Yeast (Candida): Amphotericin B (drug of choice), Nystatin 3.5% ointment
Systemic therapy: Deep stromal infection, scleral involvement, endophthalmitis, large ulcer >6 mm,
immunocompromised patients
Topical steroids: Contraindicated during active fungal keratitis
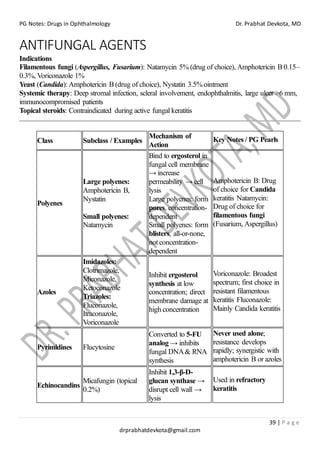
Class Subclass / Examples
Mechanism of
Action
Key Notes / PG Pearls
Polyenes
Large polyenes:
Amphotericin B,
Nystatin
Small polyenes:
Natamycin
Bind to ergosterol in
fungal cell membrane
→ increase
permeability → cell
lysis
Large polyenes: form
pores, concentration-
dependent
Small polyenes: form
blisters, all-or-none,
not concentration-
dependent
Amphotericin B: Drug
of choice for Candida
keratitis Natamycin:
Drug of choice for
filamentous fungi
(Fusarium, Aspergillus)
Azoles
Imidazoles:
Clotrimazole,
Miconazole,
Ketoconazole
Triazoles:
Fluconazole,
Itraconazole,
Voriconazole
Inhibit ergosterol
synthesis at low
concentration; direct
membrane damage at
high concentration
Voriconazole: Broadest
spectrum; first choice in
resistant filamentous
keratitis Fluconazole:
Mainly Candida keratitis
Pyrimidines Flucytosine
Converted to 5-FU
analog → inhibits
fungal DNA& RNA
synthesis
Never used alone;
resistance develops
rapidly; synergistic with
amphotericin B or azoles
Echinocandins
Micafungin (topical
0.2%)
Inhibit 1,3-β-D-
glucan synthase →
disrupt cell wall →
lysis
Used in refractory
keratitis
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
40 | P a g e
drprabhatdevkota@gmail.com
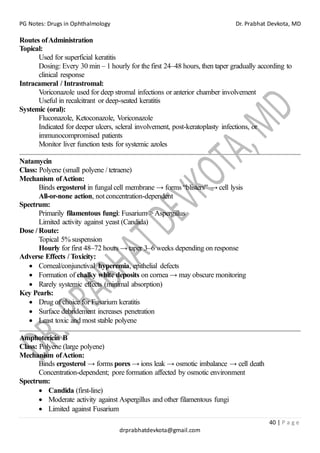
Routes ofAdministration
Topical:
Used for superficial keratitis
Dosing: Every 30 min – 1 hourly for the first 24–48 hours, then taper gradually according to
clinical response
Intracameral / Intrastromal:
Voriconazole used for deep stromal infections or anterior chamber involvement
Useful in recalcitrant or deep-seated keratitis
Systemic (oral):
Fluconazole, Ketoconazole, Voriconazole
Indicated for deeper ulcers, scleral involvement, post-keratoplasty infections, or
immunocompromised patients
Monitor liver function tests for systemic azoles
Natamycin
Class: Polyene (small polyene / tetraene)
Mechanism ofAction:
Binds ergosterol in fungal cell membrane → forms “blisters” → cell lysis
All-or-none action, not concentration-dependent
Spectrum:
Primarily filamentous fungi: Fusarium >Aspergillus
Limited activity against yeast (Candida)
Dose / Route:
Topical 5% suspension
Hourly for first 48–72 hours → taper 3–6 weeks depending on response
Adverse Effects / Toxicity:
• Corneal/conjunctival hyperemia, epithelial defects
• Formation of chalky white deposits on cornea → may obscure monitoring
• Rarely systemic effects (minimal absorption)
Key Pearls:
• Drug of choice for Fusarium keratitis
• Surface debridement increases penetration
• Least toxic and most stable polyene
Amphotericin B
Class: Polyene (large polyene)
Mechanism ofAction:
Binds ergosterol → forms pores → ions leak → osmotic imbalance → cell death
Concentration-dependent; pore formation affected by osmotic environment
Spectrum:
• Candida (first-line)
• Moderate activity against Aspergillus and other filamentous fungi
• Limited against Fusarium
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
41 | P a g e
drprabhatdevkota@gmail.com
Dose / Route:
Topical 0.15% (freshly prepared in dextrose, stored in dark bottles)
Intracameral: 500 µg/0.1 mL
Intravitreal: 5 µg/0.1 mL
Adverse Effects / Toxicity:
Local: punctate epithelial erosions, green conjunctiva, conjunctival nodules
Extremely toxic subconjunctivally at higher doses
Systemic toxicity if given IV: nephrotoxicity, electrolyte imbalance
Key Pearls:
Drug of choice for Candida keratitis
Penetration improves with debridement
Fresh preparation required; turns milky if degraded → discard
Itraconazole
Class: Triazole
Mechanism ofAction:
Inhibits 14α-demethylase → blocks ergosterol synthesis → membrane dysfunction
Fungistatic at normal doses; some fungicidal activity at higher concentrations
Spectrum:
• Candida species (yeast)
• Limited activity against filamentous fungi (less effective for Fusarium)
Dose / Route:
Oral 200 mg twice daily (BD)
Topical 1% (limited ocular penetration)
Adverse Effects / Toxicity:
• GI upset, nausea, diarrhea
• Hypokalemia, hypertriglyceridemia
• Hepatotoxicity (monitor LFTs if long-term)
Key Pearls:
• Adjunctive agent for fungal keratitis, particularly deeper or refractory Candida infections
• Poor corneal penetration limits monotherapy in stromal keratitis
Voriconazole
Class: Triazole (second-generation, synthetic)
Mechanism ofAction:
Inhibits 14α-demethylase → prevents ergosterol synthesis → cell membrane dysfunction
High potency; lower minimal inhibitory concentration (MIC) than other azoles
Spectrum:
• Broad-spectrum: Candida, Aspergillus, Fusarium (variable; Fusarium less predictable)
• Effective in recalcitrant fungal keratitis and deep stromal infections
Dose / Route:
Topical 1% (prepared in pharmacy, not commercially available)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
42 | P a g e
drprabhatdevkota@gmail.com
Oral 200 mg BD
Intrastromal / intracameral / intravitreal injections for deep or anterior chamber involvement
Adverse Effects / Toxicity:
Systemic: minimal but may cause visual disturbances, mild hepatotoxicity
Topical/intrastromal: local irritation
Key Pearls:
Drug of choice forAspergillus keratitis resistant to natamycin
Can be used intrastromally in deep stromal infections or intravitreally in endophthalmitis
Cost and availability may limit routine use
Fluconazole
Class: Triazole
Mechanism ofAction:
Inhibits 14α-demethylase → blocks ergosterol synthesis → membrane dysfunction
Spectrum:
• Candida species (yeast)
• Limited activity against filamentous fungi (Aspergillus)
Dose / Route:
Topical 0.2% solution
Oral 200 mg/day (deep ulcers, systemic therapy)
Adverse Effects / Toxicity:
Hepatotoxicity, rash, nausea, headache
Rare: Stevens-Johnson syndrome, thrombocytopenia
Key Pearls:
• Good ocular penetration → suitable for deeper ulcers or systemic therapy
• Mainly used for Candida keratitis
Exam Pearls
• Natamycin 5% = drug of choice for Fusarium keratitis
• Amphotericin B = drug of choice for Candida keratitis
• Voriconazole = newer azole, effective forAspergillus, Fusarium; use topically, intrastromal, or
orally
• Flucytosine = never use alone; synergistic with amphotericin B/azoles
• Systemic antifungal indications: large/deep ulcer, scleral involvement, endophthalmitis, post-
keratoplasty, immunocompromised
• Topical steroids = strictly contraindicated in active fungal corneal ulcer
• Debridement = increases penetration of Natamycin &Amphotericin B
• Polyenes vsAzoles: Polyenes = fungicidal; Azoles = fungistatic at low doses, fungicidal at
high doses
• Preparation caution: Amphotericin B must be freshly prepared, stored in dark bottles at 2–8°C
• Polyenes: Bind ergosterol → pores/blisters → cell lysis
• Azoles: Inhibit 14α-demethylase → block ergosterol synthesis → membrane dysfunction
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
43 | P a g e
drprabhatdevkota@gmail.com
• Flucytosine: Antimetabolite → DNA/RNA synthesis inhibition
• Echinocandins: Inhibit glucan synthesis → cell wall lysis
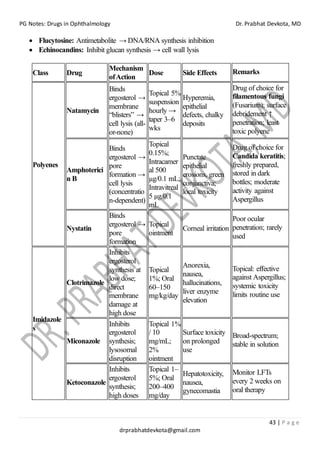
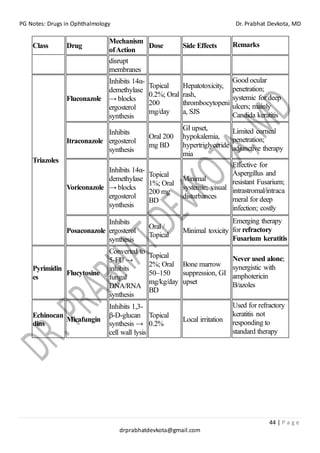
Class Drug
Mechanism
ofAction
Dose Side Effects Remarks
Polyenes
Natamycin
Binds
ergosterol →
membrane
“blisters” →
cell lysis (all-
or-none)
Topical 5%
suspension
hourly →
taper 3–6
wks
Hyperemia,
epithelial
defects, chalky
deposits
Drug of choice for
filamentous fungi
(Fusarium); surface
debridement ↑
penetration; least
toxic polyene
Amphoterici
n B
Binds
ergosterol →
pore
formation →
cell lysis
(concentratio
n-dependent)
Topical
0.15%;
Intracamer
al 500
µg/0.1 mL;
Intravitreal
5 µg/0.1
mL
Punctate
epithelial
erosions, green
conjunctiva;
local toxicity
Drug of choice for
Candida keratitis;
freshly prepared,
stored in dark
bottles; moderate
activity against
Aspergillus
Nystatin
Binds
ergosterol →
pore
formation
Topical
ointment
Corneal irritation
Poor ocular
penetration; rarely
used
Imidazole
s
Clotrimazole
Inhibits
ergosterol
synthesis at
low dose;
direct
membrane
damage at
high dose
Topical
1%; Oral
60–150
mg/kg/day
Anorexia,
nausea,
hallucinations,
liver enzyme
elevation
Topical: effective
against Aspergillus;
systemic toxicity
limits routine use
Miconazole
Inhibits
ergosterol
synthesis;
lysosomal
disruption
Topical 1%
/ 10
mg/mL;
2%
ointment
Surface toxicity
on prolonged
use
Broad-spectrum;
stable in solution
Ketoconazole
Inhibits
ergosterol
synthesis;
high doses
Topical 1–
5%; Oral
200–400
mg/day
Hepatotoxicity,
nausea,
gynecomastia
Monitor LFTs
every 2 weeks on
oral therapy
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
44 | P a g e
drprabhatdevkota@gmail.com
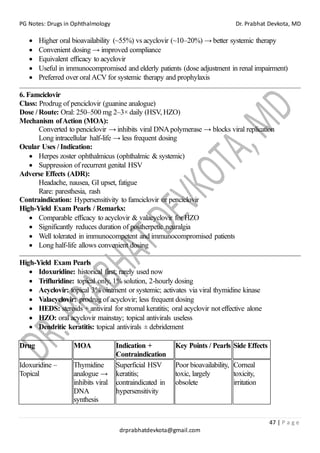
Class Drug
Mechanism
ofAction
Dose Side Effects Remarks
disrupt
membranes
Triazoles
Fluconazole
Inhibits 14α-
demethylase
→ blocks
ergosterol
synthesis
Topical
0.2%; Oral
200
mg/day
Hepatotoxicity,
rash,
thrombocytopeni
a, SJS
Good ocular
penetration;
systemic for deep
ulcers; mainly
Candida keratitis
Itraconazole
Inhibits
ergosterol
synthesis
Oral 200
mg BD
GI upset,
hypokalemia,
hypertriglyceride
mia
Limited corneal
penetration;
adjunctive therapy
Voriconazole
Inhibits 14α-
demethylase
→ blocks
ergosterol
synthesis
Topical
1%; Oral
200 mg
BD
Minimal
systemic; visual
disturbances
Effective for
Aspergillus and
resistant Fusarium;
intrastromal/intraca
meral for deep
infection; costly
Posaconazole
Inhibits
ergosterol
synthesis
Oral /
Topical
Minimal toxicity
Emerging therapy
for refractory
Fusarium keratitis
Pyrimidin
es
Flucytosine
Converted to
5-FU →
inhibits
fungal
DNA/RNA
synthesis
Topical
2%; Oral
50–150
mg/kg/day
BD
Bone marrow
suppression, GI
upset
Never used alone;
synergistic with
amphotericin
B/azoles
Echinocan
dins
Micafungin
Inhibits 1,3-
β-D-glucan
synthesis →
cell wall lysis
Topical
0.2%
Local irritation
Used for refractory
keratitis not
responding to
standard therapy
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
45 | P a g e
drprabhatdevkota@gmail.com
ANTIVIRAL AGENTS
1. Idoxuridine (IDU)
Class: Thymidine nucleoside analog
Route: Topical (0.1% solution, 0.5% ointment)
Mechanism: Inhibits viral DNAsynthesis
Notes:
First topically effective antiviral
Rarely used today due to:
Frequent application requirement
Toxicity
Availability of newer agents
2.Vidarabine (Ara-A)
Class: Adenine nucleoside analog
Route: Topical (3% ointment), IV (systemic)
Mechanism: Inhibits viral DNApolymerase → blocks viral DNAsynthesis
Notes:
Water-insoluble
Effective for herpetic keratitis
Rarely used systemically now
3.Trifluridine
Class: Fluorinated thymidine analog
Route: Topical 1% solution
Mechanism: Inhibits viral thymidylate synthase → blocks viral DNAsynthesis
Notes:
Not used systemically (rapid degradation in blood)
Can be used 2-hourly while awake in active keratitis
Useful in dendritic keratitis
4.Acyclovir (ACV)
Class: Synthetic guanine nucleoside analog (purine analogue)
Routes & Dosage:
Topical: 3% ointment, 5×/day for 7–14 days (dendritic keratitis)
Oral: 200–800 mg 5×/day for 7–10 days (HSVkeratitis, HZO)
Prophylaxis: 400 mg 2×/day (prevent recurrent HSV)
IV: 5–10 mg/kg q8h (severe systemic HSV/VZV)
Mechanism ofAction:
• Guanine analogue is phosphorylated by viral thymidine kinase → forms monophosphate
• Monophosphate is further converted by host kinases to triphosphate
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
46 | P a g e
drprabhatdevkota@gmail.com
• Triphosphate inhibits viral DNApolymerase and incorporates into viral DNA, causing
premature DNAchain termination
• Selectively active in virus-infected cells → minimal effect on host DNA
Spectrum ofActivity:
• HSV-1, HSV-2 (primary targets)
• VZV (varicella-zoster virus)
• EBV (limited)
• CMV (only at high IVdoses)
Ocular Uses:
• Dendritic keratitis: Topical ACV 3% ointment 5×/day × 7–14 days
• Stromal keratitis / systemic involvement: Oral ACV 400 mg 5×/day
• Prevention of recurrence: Oral ACV 400 mg 2×/day post-surgery or recurrent HSV
Adverse Effects (ADR):
Topical: Minimal local irritation, stinging, punctate keratitis
Oral/IV: Nausea, vomiting, diarrhea, headache, fatigue, dizziness, rash
Rare: Nephrotoxicity (IV), neurotoxicity (high IV doses), hematologic abnormalities
Contraindication: Hypersensitivity
High-Yield Exam Pearls:
• Activated only in virus-infected cells → selective toxicity
• Topical ACV preferred for superficial dendritic keratitis
• Oral ACV used for stromal keratitis, HZO, prophylaxis
• Early initiation (<72h) crucial for HZO to prevent keratitis, uveitis, ARN
• Resistance rare (<1% immunocompetent, 3–4% immunocompromised)
5.Valacyclovir (VACV)
Class: Prodrug of acyclovir (L-valyl ester) → improved oral bioavailability
Dose / Route:
Acute HSV keratitis / HZO: 1000 mg TID × 7 days
Prophylaxis / recurrent HSV: 500–1000 mg once daily
Mechanism ofAction (MOA):
Hydrolyzed to acyclovir in liver & GI tract
Inhibits viral DNApolymerase → blocks viral replication
Same spectrum as acyclovir: HSV-1, HSV-2, VZV
Ocular Uses / Indication:
• HSV keratitis (especially stromal or systemic therapy)
• Herpes zoster ophthalmicus (HZO)
• Suppression / prophylaxis of recurrent HSV keratitis
Adverse Effects (ADR):
Headache, nausea, vomiting, diarrhea, fatigue
Rare: thrombotic microangiopathy, renal impairment (especially in dehydration)
Contraindication: Hypersensitivity to acyclovir or valacyclovir
High-Yield Exam Pearls / Remarks:
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
47 | P a g e
drprabhatdevkota@gmail.com
• Higher oral bioavailability (~55%) vs acyclovir (~10–20%) → better systemic therapy
• Convenient dosing → improved compliance
• Equivalent efficacy to acyclovir
• Useful in immunocompromised and elderly patients (dose adjustment in renal impairment)
• Preferred over oral ACV for systemic therapy and prophylaxis
6. Famciclovir
Class: Prodrug of penciclovir (guanine analogue)
Dose / Route: Oral: 250–500 mg 2–3× daily (HSV, HZO)
Mechanism ofAction (MOA):
Converted to penciclovir → inhibits viral DNApolymerase → blocks viral replication
Long intracellular half-life → less frequent dosing
Ocular Uses / Indication:
• Herpes zoster ophthalmicus (ophthalmic & systemic)
• Suppression of recurrent genital HSV
Adverse Effects (ADR):
Headache, nausea, GI upset, fatigue
Rare: paresthesia, rash
Contraindication: Hypersensitivity to famciclovir or penciclovir
High-Yield Exam Pearls / Remarks:
• Comparable efficacy to acyclovir & valacyclovir for HZO
• Significantly reduces duration of postherpetic neuralgia
• Well tolerated in immunocompetent and immunocompromised patients
• Long half-life allows convenient dosing
High-Yield Exam Pearls
• Idoxuridine: historical first; rarely used now
• Trifluridine: topical only, 1% solution, 2-hourly dosing
• Acyclovir: topical 3% ointment or systemic; activates via viral thymidine kinase
• Valacyclovir: prodrug of acyclovir; less frequent dosing
• HEDS: steroids + antiviral for stromal keratitis; oral acyclovir not effective alone
• HZO: oral acyclovir mainstay; topical antivirals useless
• Dendritic keratitis: topical antivirals ± debridement
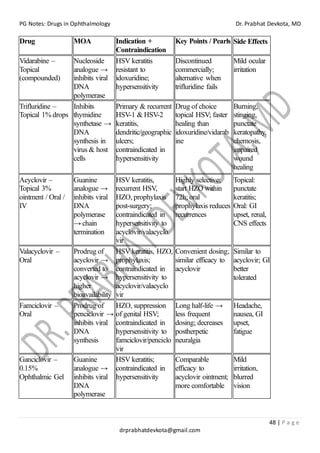
Drug MOA Indication +
Contraindication
Key Points / Pearls Side Effects
Idoxuridine –
Topical
Thymidine
analogue →
inhibits viral
DNA
synthesis
Superficial HSV
keratitis;
contraindicated in
hypersensitivity
Poor bioavailability,
toxic, largely
obsolete
Corneal
toxicity,
irritation
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
48 | P a g e
drprabhatdevkota@gmail.com
Drug MOA Indication +
Contraindication
Key Points / Pearls Side Effects
Vidarabine –
Topical
(compounded)
Nucleoside
analogue →
inhibits viral
DNA
polymerase
HSV keratitis
resistant to
idoxuridine;
hypersensitivity
Discontinued
commercially;
alternative when
trifluridine fails
Mild ocular
irritation
Trifluridine –
Topical 1% drops
Inhibits
thymidine
synthetase →
DNA
synthesis in
virus & host
cells
Primary & recurrent
HSV-1 & HSV-2
keratitis,
dendritic/geographic
ulcers;
contraindicated in
hypersensitivity
Drug of choice
topical HSV; faster
healing than
idoxuridine/vidarab
ine
Burning,
stinging,
punctate
keratopathy,
chemosis,
impaired
wound
healing
Acyclovir –
Topical 3%
ointment / Oral /
IV
Guanine
analogue →
inhibits viral
DNA
polymerase
→ chain
termination
HSV keratitis,
recurrent HSV,
HZO, prophylaxis
post-surgery;
contraindicated in
hypersensitivity to
acyclovir/valacyclo
vir
Highly selective;
start HZO within
72h; oral
prophylaxis reduces
recurrences
Topical:
punctate
keratitis;
Oral: GI
upset, renal,
CNS effects
Valacyclovir –
Oral
Prodrug of
acyclovir →
converted to
acyclovir →
higher
bioavailability
HSV keratitis, HZO,
prophylaxis;
contraindicated in
hypersensitivity to
acyclovir/valacyclo
vir
Convenient dosing;
similar efficacy to
acyclovir
Similar to
acyclovir; GI
better
tolerated
Famciclovir –
Oral
Prodrug of
penciclovir →
inhibits viral
DNA
synthesis
HZO, suppression
of genital HSV;
contraindicated in
hypersensitivity to
famciclovir/penciclo
vir
Long half-life →
less frequent
dosing; decreases
postherpetic
neuralgia
Headache,
nausea, GI
upset,
fatigue
Ganciclovir –
0.15%
Ophthalmic Gel
Guanine
analogue →
inhibits viral
DNA
polymerase
HSV keratitis;
contraindicated in
hypersensitivity
Comparable
efficacy to
acyclovir ointment;
more comfortable
Mild
irritation,
blurred
vision
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
49 | P a g e
drprabhatdevkota@gmail.com
ANTIGLAUCOMA MEDICATIONS
INTRODUCTION
Intraocular pressure (IOP) depends on:
1. Rate of aqueous humor production
2. Trabecular (conventional) outflow
3. Uveoscleral (unconventional) outflow
4. Episcleral venous pressure
Lowering IOP is the only proven method to prevent glaucoma progression.
MECHANISM-BASED CLASSIFICATION
1. Drugs Increasing Aqueous Outflow
• Uveoscleral: Prostaglandin analogues, EP2 agonists --- 25-35%
• Trabecular: Cholinergics, ROCK inhibitors, Nitric oxide donors
2. Drugs Decreasing Aqueous Production
• β-blockers --- 20-30%
• Carbonic anhydrase inhibitors --- 15-20%
• α₂-adrenergic agonists --- 15-20%
3. Drugs Reducing Vitreous Volume
• Hyperosmotic agents
Q.Disadvantages of Using Two Separate Drugs
• Poor compliance
• Difficult dosing schedule
• Washout effect
• Increased preservative toxicity
• Higher cost
Q.Advantages of Fixed Combinations
• Simple dosing
• Better compliance
• Avoids washout effect
• Greater IOP reduction
• Less preservative exposure
• Reduced systemic toxicity
• More economical
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
50 | P a g e
drprabhatdevkota@gmail.com
I. PROSTAGLANDIN ANALOGUES (PGAs)
Class
• PGF2α derivatives / Prostamides / Eicosanoids
Drugs
• Latanoprost 0.005% – once daily (qHS)
• Travoprost 0.004% – qHS – good effect over diurnal variation & BAK free
formulation
• Bimatoprost 0.01% / 0.03% – qHS
• Tafluprost 0.0015% – qHS
• Unoprostone 0.15% – BID
• Latanoprostene bunod 0.024% – qHS
Mechanism of Action (PG Depth)
• FP receptor agonists in: Ciliary muscle & Sclera
• ↑ Matrix metalloproteinases (MMP-1, MMP-9)
• ↓ Collagen types I & III
• Extracellular matrix remodeling
• ↑ Intermuscular spaces → ↑ uveoscleral outflow
Latanoprostene bunod 0.024%
• Releases nitric oxide (NO)
• NO → guanylate cyclase → ↑ cGMP
• Relaxes trabecular meshwork + Schlemm canal
• Dual outflow enhancement
IOP Reduction
• 25–35% (maximum among topical drugs)
• Bed Time – max efficacy & decreased ADR d/t vasodilation
• Flat diurnal curve
• Peak: 10–14 hours
• Full effect: 4–6 weeks
Indications
• Primary open-angle glaucoma (POAG)
• Ocular hypertension
• Normal-tension glaucoma (NTG)
• Secondary open-angle glaucoma
• Selected chronic angle-closure cases
Contraindications (Relative)
• Active uveitis (↑ inflammation)
• Hypersensitivity
• Herpetic keratitis (reactivation)
• Aphakia / posterior capsular rent → CME
• Recent intraocular surgery
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
51 | P a g e
drprabhatdevkota@gmail.com
• Pregnancy (relative)—1st
T: abortion & 3rd
T: Induction of labor
• Contact Lens wear
Adverse Effects
Ocular
• Conjunctival hyperemia
• Iris pigmentation
• Eyelash hypertrichosis
• Fornix shortening
• Periorbital fat atrophy (PAP)
• Rare CME, anterior uveitis (Iritis)
• Reactivation of viral keratitis (HSV)
Systemic
• No systemic ADR
• Headache & myalgia (rare)
PG Exam Pearls
• First-line drug for POAG
• Best nocturnal IOP control
• Once-daily bedtime dosing
• Switch within PG class if non-responder
• Remove contact lenses before instillation
• DOC in uveitic glaucoma: Timolol, Brimonidine, Dorzolamide
• Benefits of PG: Single dosing, 30- 35% IOP reduction, Flat IOP curve, Nil systemic
ADR
• Ways to decrease systemic absorption: Punctal Occlusion, Closing eyes for 3
minutes
• Advantages of Dorzolamide–Timolol (DT)
o Greater IOP reduction than either drug alone
o Additive/synergistic effect
o Better efficacy
o No electrolyte imbalance (unlike systemic CAIs)
Indications for Surgery in Glaucoma
• Failure to achieve target IOP.
• Progressive glaucomatous damage despite maximal medical therapy (3 drugs for ≥3
months).
• Drug intolerance.
• Poor compliance with medical therapy.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
52 | P a g e
drprabhatdevkota@gmail.com
II. BETA-ADRENERGIC BLOCKERS
Class
• Non-selective and β₁-selective blockers
Drugs
Cardioselective β₁-Blocker
• Betaxolol 0.25–0.5% – BD (β₁-selective)
Non-Selective β-Blockers
• Timolol 0.25–0.5% – BD
• Levobunolol 0.25–0.5% – OD/BD
• Carteolol 1% – BD
Ideal Time: Morning – blunt early morning increased IOP d/t circidian rhythm
Mechanism of Action
• Block β-receptors in non-pigmented ciliary epithelium
• ↓ Adenyl cyclase → ↓ cAMP
• ↓ Na⁺/K⁺ ATPase activity
• ↓ aqueous humor production
IOP Reduction: 20–30%, Reduced nocturnal efficacy
Indications
• POAG, Secondary glaucomas, Add-on to PGAs
Contraindications
• Bronchial asthma, COPD
• Sinus bradycardia
• Heart block
• Congestive heart failure
• Diabetes mellitus
• Peripheral vascular disease
• Myasthenia gravis
Adverse Effects
Ocular
• Dry eye, Superficial punctate keratitis, Corneal anesthesia
Systemic
• Bradycardia
• Hypotension
• Bronchospasm
• Depression, fatigue
• Masked hypoglycemia
PG Exam Pearls
• Avoid bedtime dosing (systemic hypotension)
• Betaxolol safer in pulmonary disease (less potent)
• Long-term drift & short-term escape phenomenon
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
53 | P a g e
drprabhatdevkota@gmail.com
III. ALPHA-2 ADRENERGIC AGONISTS
Drugs
• Brimonidine 0.1–0.2% – TDS— Alphagan-Z (0.1%),Alphagan-P (0.15%),Alphagan
(0.2%)
• Apraclonidine 0.5–1% – TDS (short-term) – decrease aqueous production
Mechanism of Action
• Presynaptic α₂ stimulation:
o ↓ norepinephrine release
o ↓ aqueous production
• Postsynaptic α₂:
o ↑ uveoscleral outflow
• Possible neuroprotective effect
IOP Reduction: 20–25%
Indications
• POAG (adjunct)
• Post-laser IOP spike prevention (apraclonidine)
Contraindications
• Infants & children <2 years--- crosses BBB—Somnolence, Bradycardia, Hypotension,
Apnea, CNS depression
• MAO inhibitors
• Tricyclic antidepressants
• Severe cardiovascular disease
Adverse Effects
• Allergic follicular conjunctivitis
• PEEs, decreased Tear production, decreased corneal sensation
• Dry mouth
• Fatigue
• Hypotension
• Apnea & CNS depression in infants
• Somnolence
PG Exam Pearls
• Apraclonidine → tachyphylaxis
• Brimonidine-Purite better tolerated
• Preferred short-term adjunct
IV. CARBONIC ANHYDRASE INHIBITORS (CAIs)
A. TOPICAL CAIs
• Dorzolamide 2% – TDS
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
54 | P a g e
drprabhatdevkota@gmail.com
• Brinzolamide 1% – TDS
Mechanism
• Inhibit CA-II in ciliary processes
• ↓ bicarbonate → ↓ Na⁺ transport
• ↓ aqueous production
IOP Reduction
• 15–20%
B. SYSTEMIC CAIs
• Acetazolamide 250 mg QID / 500 mg SR BD --- avoided in Sickle cell—low pH
causes more sickling
• Methazolamide 50 mg BD–TDS
IOP Reduction
• 30–40%
Indications
• Acute angle-closure glaucoma
• Pre-operative IOP control
• Refractory glaucoma
Contraindications
• Sulfonamide allergy
• Renal failure
• Chronic Liver Disease
• Renal Transplant
• Addison’s disease
• Pregnancy
Adverse Effects
• Ocular: Corneal edema, transient myopia, burning/stinging.
• Metabolic: Hyperchloremic metabolic acidosis, hypokalemia, paresthesia.
• GU: Renal calculi, nocturia, impotence.
• GI: Nausea, vomiting, abdominal pain, GI upset.
• Hemato(rare): Aplastic anemia, agranulocytosis, neutropenia, thrombocytopenia.
• CNS: Fatigue, Tingling sensation, drowsiness, headache, paresthesia.
• Derma (sulfonamide reactions): Rash, pruritus, Stevens–Johnson syndrome (SJS),
toxic epidermal necrolysis (TEN), exfoliative dermatitis.
PG Exam Pearls
• Most potent aqueous suppressors
• Topical CAIs not additive to systemic CAIs
• Avoid long-term systemic use
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
55 | P a g e
drprabhatdevkota@gmail.com
V. CHOLINERGIC AGONISTS (MIOTICS)
Drugs
• Pilocarpine 0.5–4% – QID (gel qHS)
• Carbachol 1.5% – TDS
• Echothiophate iodide – BD
Mechanism of Action
• POAG: M₃ receptor stimulation → Ciliary muscle contraction (longitudinal fibers) →
Scleral spur traction → Trabecular meshwork opens (↑ porosity) → ↑ Aqueous
outflow via Schlemm's canal → ↓ IOP.
• PACG: M₃ receptor stimulation → Miosis → Peripheral iris pulled away from
trabecular meshwork → Relieves pupillary block → Opens anterior chamber angle →
↑ Aqueous outflow → ↓ IOP.
IOP Reduction: 20–25%
Indications
• Acute angle-closure glaucoma
• Plateau iris syndrome
• Post-laser prophylaxis
Contraindications
• Uveitis
• High myopia
• Phacolytic glaucoma
• Cataract
• Neovascular glaucoma
• Retinal detachment risk
Adverse Effects
Ocular
• Miosis → poor night vision
• Brow ache
• Induced myopia – d/t CB contraction
• Lacrimation—d/t punctal stenosis
• Retinal detachment (rare)
Systemic
• Bradycardia
• Bronchospasm
• GI cramps
PG Exam Pearls
• Oldest antiglaucoma drug
• Mainly for acute angle closure
• Pilocarpine 0.1% diagnostic for Adie pupil
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
56 | P a g e
drprabhatdevkota@gmail.com
VI. RHO-KINASE (ROCK) INHIBITORS
Drugs – Dose
• Netarsudil 0.02% – OD
• Ripasudil 0.4% – BD
• Netarsudil + Latanoprost – OD
Mechanism of Action
• Inhibit ROCK-1 & ROCK-2
• ↓ Actin stress fibers
• Relax trabecular meshwork
• ↑ Schlemm canal permeability
• ↓ Episcleral venous pressure
IOP Reduction
• 20–30%
Adverse Effects
• Conjunctival hyperemia (most common)
• Subconjunctival hemorrhage
• Corneal verticillate
(Drug causing Verticillate: Amiodarone, HCQ, Chloroquine, Tamoxifen, Indomethacin,
RhoKinase Inhibitor)
PG Exam Pearls
• Only drugs acting directly on trabecular cytoskeleton
• Useful in resistant glaucoma
Newer Ocular Hypotensive Agents
• Natural cannabinoids.
• ECM hydrolysis activators (MMPs – Matrix Metalloproteinases) → ↑ Trabecular
outflow.
• Cytoskeleton modulators → Relax trabecular meshwork.
• Ethacrynic acid → Increases trabecular outflow.
• Protein kinase inhibitors → Increase aqueous outflow.
• cGMP-enhancing compounds → Improve aqueous outflow.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
57 | P a g e
drprabhatdevkota@gmail.com
VII. HYPEROSMOTIC AGENTS
Drugs – Dose
• IV Mannitol 20% IV – 1–2 g/kg over 30–60 min --- less irritating for blood vessel &
can be used in DM & CRFpatients.
(Instruction: no to get up immediately after injection—causes hypotension)
• Oral Isosorbide 45%
• Oral Glycerol 50%– 1–1.5 g/kg
Mechanism
• ↑ Plasma osmolarity
• Fluid shift from vitreous → plasma
• ↓ Vitreous volume
• Rapid IOP reduction
ADR
• Ocular: Rebound rise in IOP, intraocular hemorrhage.
• CNS: Hyperosmolarity causing confusion, disorientation, thirst, chills, and fever.
• GI: Nausea, vomiting, diarrhea, and abdominal cramps.
• Renal/Fluid & Electrolytes: Diuresis leading to dehydration, hypovolemia, and
electrolyte imbalance.
• CVS: Angina, pulmonary edema, and congestive heart failure (CHF/CCF).
• Others: Hyperglycemia and hypersensitivity reactions.
Indications
• Acute angle-closure glaucoma
• Pre-operative IOP lowering
• Malignant Glaucoma
Contraindications
• Cardiac failure
• Renal failure
• Anuria
• Pulmonary edema
• Dehydration
• Diabetes (glycerol)
PG Exam Pearls
• Emergency drugs
• Short-acting
• Risk of rebound IOP rise
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
58 | P a g e
drprabhatdevkota@gmail.com
Neuroprotective Drugs in Glaucoma
Prevents retinal ganglion cell (RGC) death independent of IOP reduction.
❖ NMDA Receptor Antagonist
• Memantine: Blocks glutamate-mediated excitotoxicity → ↓ Ca²⁺ influx →
Prevents RGC apoptosis.
❖ Nitric Oxide (NO) Synthase Inhibitor
• Aminoguanidine: Inhibits NO-mediated neurotoxicity.
❖ Calcium Channel Blockers
• Nimodipine, Verapamil: ↑ Optic nerve blood flow; useful in normal-tension
glaucoma (NTG); enhance RGC survival.
❖ Other Neuroprotective Agents
• Brimonidine (α₂-agonist): Neuroprotective effect beyond IOP lowering.
• Neurotrophic factors: BDNF, CNTF, NGF → Promote RGC survival.
• Antioxidants: Resveratrol, α-lipoic acid → Reduce oxidative stress.
• Apoptosis inhibitors: Prevent programmed RGC death.
• Caspase inhibitors: Block apoptosis pathway.
• Coenzyme Q10: Mitochondrial neuroprotection.
Newer Drug Delivery Systems in Glaucoma
• Durysta® (Bimatoprost intracameral implant): Biodegradable implant; sustained
release 3–4 months; FDA-approved (2020) for POAG/OHT.
• iDose® Travoprost: Intracameral implant with >6 months sustained release; ~32–
33% IOP reduction.
• Bimatoprost ring: Preservative-free forniceal ring containing 13 mg bimatoprost.
• Travoprost punctal plug: Inserted into the inferior canaliculus for sustained drug
delivery.
• Drug-eluting contact lens: Silicone hydrogel lens loaded with nanoparticles for
continuous ocular drug release.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
59 | P a g e
drprabhatdevkota@gmail.com
Class / Drugs MOA
Indication /
IOP
Reduction
Contraindications
Key Side
Effects / Notes
PGAs –
Latanoprost,
Travoprost,
Bimatoprost,
Tafluprost,
Unoprostone,
Latanoprostene
bunod
↑ Uveoscleral
outflow, ECM
remodeling;
Latanoprostene
bunod: + NO
trabecular
outflow
First-line for
POAG, NTG,
secondary
OAG; IOP↓
25–35%
Relative: recent
surgery, uveitis,
herpetic keratitis
Hyperemia,
iris/periocular
pigmentation,
eyelash growth;
bedtime dosing
β-Blockers –
Timolol,
Levobunolol,
Carteolol,
Metipranolol,
Betaxolol
↓ Aqueous
production via
β1/β2 blockade
First- or
second-line,
additive
therapy; IOP↓
20–30%
Asthma, COPD,
bradycardia, HF,
diabetes, PVD
Ocular: burning,
hyperemia;
systemic:
bradycardia,
bronchospasm,
CNS effects;
avoid bedtime
dosing
α2-Agonists –
Brimonidine,
Apraclonidine
↓ Aqueous, ↑
uveoscleral
outflow;
neuroprotective
Adjunct
therapy, post-
laser
prophylaxis;
IOP↓ 20–25%
<2y, MAOIs,
tricyclics
Allergy,
stinging, fatigue,
dry mouth;
apraclonidine
short-term only
CAIs –
Dorzolamide,
Brinzolamide,
Acetazolamide,
Methazolamide
Inhibit carbonic
anhydrase → ↓
bicarbonate → ↓
aqueous
production
Second-line,
acute
glaucoma,
intolerance;
Topical ~20%,
Oral ~30%
Sulfa allergy,
renal/hepatic
disease, Addison’s
Topical:
stinging, bitter
taste; oral:
malaise,
acidosis, kidney
stones, rare SJS
Cholinergics /
Miotics –
Pilocarpine,
Carbachol,
Echothiophate
Constrict ciliary
muscle → ↑
trabecular
outflow; pulls
iris from TM
Acute angle-
closure, post-
laser
prophylaxis;
IOP↓ 20–25%
Age>40, cataract,
uveitis, neovascular
glaucoma
Miosis, brow
ache, headache,
myopia; mainly
acute use
ROCK
inhibitors –
Netarsudil,
Ripasudil
Relax TM → ↑
conventional
outflow;
neuroprotective
Adjunct
therapy, ocular
hypertension,
POAG; IOP↓
moderate
None absolute
Hyperemia,
corneal
verticillata, mild
irritation
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
60 | P a g e
drprabhatdevkota@gmail.com
Class / Drugs MOA
Indication /
IOP
Reduction
Contraindications
Key Side
Effects / Notes
Omidenepag
(EP2 agonist) –
Omidenepag
Isopropyl
↑ Trabecular +
uveoscleral
outflow via
ECM
remodeling
Alternative /
adjunct for
latanoprost
non-
responders,
POAG, NTG;
IOP↓ 2–5
mmHg
None absolute
Hyperemia, rare
macular edema;
no pigmentation
changes
Hyperosmotics
– Mannitol,
Glycerol,
Isosorbide
↑ Plasma
osmolality →
water drawn
from vitreous
Acute IOP
reduction,
preoperative
control, acute
angle-closure;
rapid IOP↓
Anuria,
dehydration,
pulmonary edema,
cardiac
compromise
Nausea,
headache,
electrolyte
disturbance;
glycerol ↑
glucose
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
61 | P a g e
drprabhatdevkota@gmail.com
ANTI-VEGF DRUGS
Anti-VEGF
Intravitreal Injection
• Preferred site: Inferotemporal quadrant (Parsplana wide & adv of bells phenomena)
• Avoid: 3 & 9 o'clock meridians (long posterior ciliary nerves & arteries)
• Pars plana entry:
o Phakic: 4 mm
o Pseudophakic: 3.5 mm
o Aphakic: 3 mm (from limbus)
Strategies:
1. Monthly Dosing
• Best visual outcomes
• High treatment burden
2. Pro Re Nata (PRN)
• 3 initial loading doses
• Monthly monitoring/ follow-up
• Inject when needed (wet)
3. Treat & Extend (TREX)
• 3 initial loading doses f/b monthly injection till stability
• Gradually extend interval by 1-2 weeks based on CST & BCVA
(max: 12 wk, min: 4 wk)
• Inject when come
10% Central Subfield Thickness (CST) & 5 letter rule
Worsening:
• ↑ CST > 10%
• ↓ BCVA >5 ETDRS letter (ie. 1 Snellen line)
Improving:
• ↓ CST > 10%
• ↑ BCVA >5 ETDRS letter (ie. 1 Snellen line)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
62 | P a g e
drprabhatdevkota@gmail.com
Indications:
• Wet AMD/CNV, DME, PDR, RVO with CME, ROP, Myopic CNV
• Corneal neovascularization, Pterygium
• NVI, NVG
Advantages:
• Targeted inhibition of pathological angiogenesis
• Reduces macular edema, neovascularization, leakage
• Prolonged effect with newer agents (Brolucizumab, Faricimab)
Complications:
• Ocular: Endophthalmitis, ↑IOP, uveitis, retinal detachment, VH, Cataract, SCH
(injection related)
• Systemic (rare): Stroke, MI, thromboembolic events
Contraindications:
• Pregnancy,
• Active ocular infection/inflammation,
• Hypersensitivity,
• Recent CVA/MI (relative caution)
Mechanism of Action
• Pegaptanib: Selectively binds VEGF-165 → blocks VEGFR-1/2 → inhibits
angiogenesis and vascular leakage.
• Bevacizumab: Binds all VEGF-A isoforms → prevents VEGFR activation →
inhibits endothelial proliferation, neovascularization, and leakage.
• Ranibizumab: High-affinity VEGF-A binding → blocks VEGFR-mediated
angiogenesis and vascular permeability; small Fab fragment → better retinal
penetration and low systemic exposure.
Newer Anti-VEGF:
• Aflibercept: Soluble VEGF trap (VEGFR-1/2 fused to IgG Fc) → binds VEGF-A,
VEGF-B, PlGF → inhibits VEGFR signaling and vascular leakage.
• Brolucizumab: Small Single Chain Fragent(scFv) binds VEGF-A → high molar
dose in small volume → long-lasting intravitreal VEGF inhibition.
• Faricimab: Bispecific antibody →
1. VEGF-A inhibition → reduces angiogenesis & leakage,
2. Ang-2 inhibition → stabilizes vessels, reduces vascular inflammation →
prolonged durability.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
63 | P a g e
drprabhatdevkota@gmail.com
Drug Class / Target MOA
MW
(kDa)
t½
(Vitreous)
IVT Dose FDA
Pegaptanib
(Macugen)
Pegylated RNA
aptamer / VEGF-
165
Selectively binds
VEGF-165 → ↓
angiogenesis &
leakage
50 ~10 d
0.3 mg q6
wk
2004
Bevacizumab
(Avastin)
Full length
monoclonal Ab /
VEGF-A
Binds all VEGF-A
→ inhibits
angiogenesis &
leakage
149 ~ 21 d
1.25 mg
q4–6 wk
Off-
label
Ranibizumab
(Lucentis)
Fab fragment /
VEGF-A
High-affinity
VEGF-A inhibition
48 ~ 9 d
0.5 mg q4
wk
2006
Aflibercept
(Eylea)
Fusion protein /
VEGF-A, VEGF-
B, PlGF
Decoy receptor
binds VEGF-A/B
& PlGF
115 ~7–9 d
2 mg q8
wk (after
loading)
2011
Brolucizumab
(Beovu)
Single Chain
Fragent(scFv) /
VEGF-A
Small scFv → high
molar dose,
prolonged VEGF
suppression
26 ~3–4 d
6 mg q8–
12 wk
2019
Faricimab
(Vabysmo)
Bispecific mAb /
VEGF-A + Ang-
2
Dual inhibition →
anti-VEGF +
vessel stabilization
150 ~7.5 d
6 mg q8–
16 wk
2022
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
64 | P a g e
drprabhatdevkota@gmail.com
PEGAPTANIB (Macugen)
Class: Pegylated RNA aptamer (not antibody)
MOA
Selectively binds VEGF-165 isoform
Blocks VEGFR-1 and VEGFR-2 activation
↓ Angiogenesis and vascular leakage
Indications
Neovascular AMD (historical use)
Dose
0.3 mg intravitreal every 6 weeks
ADR
Injection-related complications
Less effective than newer agents
BEVACIZUMAB (Avastin)
Class: Full-length humanized monoclonal antibody (149 kDa)
MOA:
Binds all VEGF-A isoforms
Prevents VEGFR activation
Inhibits endothelial proliferation & leakage
Indications
• Wet AMD (off-label)
• DME
• BRVO / CRVO macular edema
• ROP
• NVG / iris neovascularization
• Oncology (systemic)- RCC, Ca Cervix/Ovary, Breast mets, SCC (lungs)
Dose
1.25 mg / 0.05 mL intravitreal
Monthly or OCT-guided (PRN/T&E)
Most cost-effective; off-label use
ADR
Ocular:
Endophthalmitis
IOPspike
Vitreous hemorrhage
Systemic (rare):
↑ BP
Thromboembolic events
GI bleeding/perforation
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
65 | P a g e
drprabhatdevkota@gmail.com
RANIBIZUMAB (Lucentis)
Class: Monoclonal antibody fragment (Fab) – 48 kDa
MOA
High-affinity binding to all VEGF-Aisoforms
Small size → better retinal penetration
Minimal systemic exposure
Indications
• Wet AMD (FDAapproved 2006)
• DME
• RVO macular edema
• Myopic CNV
Dose
0.5 mg / 0.05 mL intravitreal
Monthly OR PRN OR Treat-and-Extend
ADR
Similar to other intravitreal agents
Lower systemic risk compared to bevacizumab
NEWER ANTI-VEGFs: AFLIBERCEPT (Eylea), BROLUCIZUMAB, FARICIMAB
AFLIBERCEPT (Eylea)
Class: Receptor-antibody fusion protein (VEGF Trap) – 115 kDa
MOA
Decoy receptor (VEGFR-1 + VEGFR-2 fused to IgG Fc)
Binds:
VEGF-A
VEGF-B
Placental Growth Factor (PlGF)
Strong binding affinity
Indications
• Wet AMD
• DME
• RVO macular edema
• Myopic CNV
Dose
2 mg / 0.05 mL
3 monthly loading doses
Then every 8 weeks
ADR
Similar injection risks
Rare intraocular inflammation
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
66 | P a g e
drprabhatdevkota@gmail.com
BROLUCIZUMAB (Beovu)
Class: Single-chain antibody fragment (scFv) – 26 kDa
MOA
Binds VEGF-A
Very small size → high molar dose
Prolonged VEGF suppression
Indications
Wet AMD
Dose
6 mg intravitreal
q8–12 weeks after loading
ADR
Intraocular inflammation
Retinal vasculitis
Occlusive retinal vasculitis (rare but serious)
FARICIMAB (Vabysmo)
Class: Bispecific monoclonal antibody (150 kDa)
MOA
Dual mechanism:
• VEGF-Ainhibition → ↓ angiogenesis & leakage
• Angiopoietin-2 inhibition → vessel stabilization, ↓ inflammation
Indications
Wet AMD
DME
Dose
6 mg intravitreal
Can extend to 12–16 weeks
ADR
Similar to other anti-VEGF
Inflammation possible
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
67 | P a g e
drprabhatdevkota@gmail.com
IMMUNOSUPPRESSIVE THERAPY (IMT)
A. Therapeutic Indications
• Failure of high-dose steroids (2–4 weeks)
• Inflammation not quiet after 4 weeks
• Relapse on tapering
• Steroid intolerance / contraindication
B. Ocular Severity Indicators
Adults:
• VA< 20/100
• Severe vitreous haze
• Recurrent CME
JIA:
• Posterior involvement
• Glaucoma, cataract
• Hypotony, rubeosis
C. Diseases Requiring Early IMT (VERY HIGH YIELD)
• Behçet disease
• VKH
• Sympathetic ophthalmia
• JIA-associated uveitis
• Serpiginous choroiditis
• Birdshot chorioretinopathy
• Necrotizing scleritis (GPA)
• Ocular cicatricial pemphigoid
• PUK with systemic vasculitis
PRE-TREATMENT EVALUATION (MANDATORY)
✔ CBC
✔ LFT
✔ RFT
✔ Urinalysis
✔ Lipid profile
✔ BP
Screen for:
• TB (mandatory before TNF inhibitors)
• Hepatitis B & C
• HIV
• Demyelinating disease (avoid TNFi)
• Malignancy
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
68 | P a g e
drprabhatdevkota@gmail.com
• Autoimmune systemic disease
Pregnancy counseling:
• MTX & MMF contraindicated
• Azathioprine relatively safe
CLASSIFICATION OFIMMUNOSUPPRESSIVE AGENTS
1. ANTImetabolites (First-Line)
Methotrexate (MTX)
Mycophenolate mofetil (MMF)
Azathioprine (AZA)
2. T-Cell Inhibitors (Calcineurin Inhibitors)
Cyclosporine
Tacrolimus
Sirolimus (mTOR inhibitor)
3. Alkylating Agents (Last Resort)
Cyclophosphamide
Chlorambucil
4. Biologics
TNF-α inhibitors (Adalimumab, Infliximab)
IL-6 inhibitor (Tocilizumab)
CD20 inhibitor (Rituximab)
IL1 Receptor Antagonist: Anakinra,
JAK Kinase inhibitors: Tofacitinib
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
69 | P a g e
drprabhatdevkota@gmail.com
ANTIMETABOLITES (FIRST-LINE AGENTS)
1. METHOTREXATE (MTX)
Mechanism ofAction (MOA)
Inhibits Dihydrofolate reductase (DHFR)
↓ Tetrahydrofolate → ↓ DNAsynthesis
Immunosuppressive effect mainly via:
• ↑ Extracellular adenosine
• Suppression ofT-cell activation
• ↓ Pro-inflammatory cytokines
Indications
• JIA-associated uveitis ( Pediatric gold standard)
• Anterior & intermediate uveitis
• VKH
• Sympathetic ophthalmia
• Serpiginous choroiditis
• Ocular cicatricial pemphigoid
• Scleritis
Contraindications
Absolute:
• Pregnancy (Teratogenic)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
70 | P a g e
drprabhatdevkota@gmail.com
• Chronic liver disease
• Active hepatitis
• Severe renal failure
• Alcohol abuse
Relative:
• Interstitial lung disease
• Cytopenia
Prevention of Complication:
• Use of Folic Acid
• Alcohol abstinence
• Contraception for wpmen
• Avoid other hepatotoxic drugs
Dose
Start: 7.5–15 mg/week
Increase by 2.5–5 mg every 4 weeks
Max: 25 mg/week
15 mg/week → Prefer SC route
✔ Folic acid 1–5 mg/day mandatory
Adverse Effects (ADR)
Common:
• Nausea (most common)
• GI upset
• Fatigue
Serious:
• Hepatotoxicity
• Bone marrow suppression
• Interstitial pneumonitis
• Teratogenicity
Remarks
• Onset: 3–6 months
• Monitor CBC, LFT, RFT every 2–3 months
• No increased malignancy risk in children (SITE data)
• Alcohol abstinence mandatory
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
71 | P a g e
drprabhatdevkota@gmail.com
2. MYCOPHENOLATE MOFETIL (MMF)
MOA
Prodrug → Mycophenolic acid (MPA)
Inhibits Inosine Monophosphate Dehydrogenase (IMPDH)
Blocks de novo guanosine synthesis
Selectively suppresses T & B lymphocytes
Indications
• Posterior uveitis
• Panuveitis
• Birdshot chorioretinopathy
• Behçet disease
• Methotrexate nonresponsive
• OCP
• Scleritis
Contraindications
• Pregnancy
• Severe active infection
• Severe leukopenia
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
72 | P a g e
drprabhatdevkota@gmail.com
Dose
• 500 mg BD (twice daily) initially
• Increase to 1 g twice daily
• Max: 3 g/day
ADR
Common:
• Diarrhea (most common)
• Nausea
• GI ulceration
Serious:
• Leukopenia
• Infections
• Rare lymphoma
Remarks
• Onset: 3–4 months
• Relatively safer in liver disease
• Good option for posterior disease
• Monitor CBC & LFT every 4–6 weeks
3. AZATHIOPRINE (AZA)
MOA
Converted to 6-mercaptopurine
Inhibits purine synthesis
Affects rapidly dividing lymphocytes
Metabolized by TPMT enzyme
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
73 | P a g e
drprabhatdevkota@gmail.com
Indications
Pregnancy (preferred IMT)
Sarcoidosis
Pars planitis
VKH
Behçet disease
Scleritis
JIAiridocyclitis
Contraindications
• TPMT deficiency
• Severe cytopenia
• Active malignancy
• Relative:
• Liver dysfunction
Dose
1–2.5 mg/kg/day
Start low (25–50 mg/day) → escalate
ADR
• GI disturbances
• Leukopenia
• Thrombocytopenia/ Marrow Suppression
• Hepatitis/ Hepatotoxicity
• Pancreatitis
• Secondary Infection
• Increased malignancy risk (highest among antimetabolites)
Remarks
• TPMT (Thiopurine Methyltransferase) testing mandatory before starting
(Low/No TPMT: not recommended; Intermediate TPMT: reduced dose, Normal/High
TPMT: Higher dose)
• Onset: ~4 months
• Monitor CBC weekly initially
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
74 | P a g e
drprabhatdevkota@gmail.com
CALCINEURIN INHIBITORS (T-Cell Inhibitors)
4. CYCLOSPORINE
Mechanism ofAction (MOA)
• Binds cyclophilin → inhibits calcineurin → ↓ NFAT activation → ↓ IL-2 (± IL-6) transcription
→ ↓ T-cell activation & cytokine release
Ophthalmic Uses
Topical (FDAapproved 2002)
• Chronic dry eye (KCS) – Sjögren & non-Sjögren (0.05% emulsion)
• Corneal Graft Rejection
• Meibomian gland dysfunction
• Ocular surface inflammation
• Severe/refractory VKC (off-label)
Systemic
• Behçet posterior uveitis
• VKH
• Birdshot chorioretinopathy
• Sympathetic ophthalmia
• Sarcoid uveitis
• Other autoimmune uveitis
Clinical Effects (Topical)
• ↓ Ocular surface inflammation
• ↑ Goblet cell density
• ↑ Baseline tear production (not reflex tearing)
• Improves epithelial integrity
• ↓ Corneal staining & SPK
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
75 | P a g e
drprabhatdevkota@gmail.com
• Improves Schirmer test
• Steroid-sparing agent
Dose
Topical
• 0.05% emulsion (preservative-free)
• BD
• Onset: 3–6 months
Systemic
• 2.5–5 mg/kg/day
• Maximum: 10 mg/kg/day
Adverse Effects
Topical
• Burning/stinging (most common)
• Minimal systemic absorption
Systemic
• Nephrotoxicity (dose-limiting)
• Neurotoxicity
• Hypertension
• Gingival hyperplasia
• Hypertrichosis
• Hirsutism
• Hyperlipidemia
Contraindications
• Uncontrolled hypertension
• Renal insufficiency
• Malignancy
Monitoring
• Serum creatinine
• Blood pressure
High-Yield Pearls
• FDA-approved topical immunomodulator for dry eye
• Steroid-sparing
• Improves baseline tear secretion only
• Safe for long-term use
• Often combined with other IMTs for uveitis
5.TACROLIMUS
Mechanism ofAction (MOA)
• Binds FKBP-12 → inhibits calcineurin → ↓ NFAT activation → ↓ IL-2, IL-3, IL-4, TNF-α,
IFN-γ → ↓ T-cell activation
Exam Pearl: Tacrolimus is ~100× more potent than cyclosporine.
Ophthalmic Uses
Topical (Off-label)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
76 | P a g e
drprabhatdevkota@gmail.com
• Severe VKC
• AKC
• Steroid-dependent allergic conjunctivitis
• Giant papillary conjunctivitis
• Ocular GVHD
• Ocular cicatricial pemphigoid (adjunct)
• Peripheral ulcerative keratitis (adjunct)
Systemic
• Same indications as cyclosporine
• Cyclosporine intolerance
Dose
Topical
• 0.03% ointment
• 0.1% ointment (severe disease)
• BD; taper after control
Systemic
• 0.05–0.2 mg/kg/day
Advantages
• Steroid-sparing
• No cataract
• No steroid-induced glaucoma (no rise in IOP)
• Suitable for long-term therapy
• Faster onset than cyclosporine
Adverse Effects
Topical
• Burning/stinging
• Transient hyperemia
• Herpetic keratitis reactivation
• Secondary infection (rare)
Systemic
• Nephrotoxicity
• Neurotoxicity (tremor)
• Hyperglycemia/diabetes
Contraindications
• Active ocular infection
• Hypersensitivity
• Caution in herpetic keratitis
High-Yield Pearls
• 100× more potent than cyclosporine
• Faster onset
• Preferred for severe/refractory VKC &AKC
• Fewer cosmetic adverse effects than cyclosporine
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
77 | P a g e
drprabhatdevkota@gmail.com
ALKYLATING AGENTS (last resort)
6. CYCLOPHOSPHAMIDE
MOA
Alkylates DNA
Cross-linking → cell death
Suppresses B & T cells
Indications
• Necrotizing scleritis
• PUK (GPA, PAN, RA)
• OCP
• Bilateral Mooren ulcer
• Severe Behçet
Contraindications
• Pregnancy
• Severe marrow suppression
• Active infection
Dose
1 mg/kg/day PO
OR
IV pulse 1 g/m² every 2 weeks
ADR
• Alopecia
• Hemorrhagic cystitis
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
78 | P a g e
drprabhatdevkota@gmail.com
• Infertility/ Sterility
• Reddish urine
• Secondary malignancy (bladder CA)
• Bone marrow suppression
Remarks
• Ensure hydration
• Monitor urine for hematuria
• CBC & Urine Analysis:
o WBC: ≥ 3,500–4,000 cells/mm³
o Absolute Neutrophil Count (ANC): > 1,500 cells/mm³
o Platelet Count: > 75,000 cells/mm³
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
79 | P a g e
drprabhatdevkota@gmail.com
BIOLOGICS
Genetically engineered proteins or monoclonal antibodies (mAbs) targeting a specific
cytokine, inflammatory cell, or cell-surface receptor. Provide targeted immunomodulation
by blocking a key step in the inflammatory cascade. Unlike conventional
immunosuppressants, they do not cause global immunosuppression.
• Biologics (Biopharmaceuticals): Therapeutic proteins or monoclonal antibodies
produced from living organisms using biotechnology.
• Biosimilars: Highly similar versions of approved biologics with comparable
efficacy, safety, and quality (not identical generics).
7.ADALIMUMAB (only FDAApproved for Uveitis)
MOA
Fully human monoclonal antibody
Binds TNF-α (soluble & membrane-bound)
Prevents inflammatory cascade
Indications
• 1st line: Behçet, JIAuveitis
• 2nd line: HLAB27, Posterior uveitis, Intermediate uveitis & Sarcoidosis
• Noninfectious intermediate uveitis
• Panuveitis
Contraindications
• Active infection
• Latent TB untreated
• Multiple sclerosis
• Recent malignancy
Dose
40 mg SC every 2 weeks
Weekly in refractory cases
ADR
• TB reactivation
• Lymphoma risk
• Demyelinating disease
• Injection site reaction
Remarks
• Screen TB & Hepatitis B
• Onset ~12 weeks
• VISUAL & SYCAMORE trials support use
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
80 | P a g e
drprabhatdevkota@gmail.com
8. INFLIXIMAB
Infliximab is a chimeric anti–TNF-α monoclonal antibody used in refractory non-infectious
uveitis.
MOA
Binds to tumor necrosis factor-alpha (TNF-α) → blocks inflammatory cascade.
↓ Interleukin-6
↓ Chemokines (e.g., macrophage chemoattractant protein-1)
↓ Adhesion molecules (ICAM-1)
Result → potent suppression of ocular inflammation
Dose
3–5 mg/kg IV at 0,2,6 weeks
Maintenance every 4–8 weeks
Primary Indication
• Refractory non-infectious uveitis
• Behçet’s uveitis
• Chronic pediatric uveitis
• Severe inflammatory ocular disorders requiring biologics
• PUK
ADR
• Increased susceptibility forTB, Fungal infection
• Infusion reaction
• Anti-drug antibody formation
• TB reactivation
• Pulmonary embolism
• Congestive heart failure
• Lupus-like syndrome
• Vitreous hemorrhage
Remarks
• Rapid onset (6–12 weeks)
• Preferred in severe Behçet
• Monitor CBC & LFT
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
81 | P a g e
drprabhatdevkota@gmail.com
9.TOCILIZUMAB
MOA: IL-6 receptor antagonist
Indications
• Uveitic macular edema
• Retinal vasculitis
• GCA
ADR
• Hyperlipidemia
• Infection
• Elevated LFT
Remarks: Best biologic for refractory UME
10. RITUXIMAB
MOA
Anti-CD20 monoclonal antibody
B-cell depletion
Indications
• ANCAvasculitis
• Scleritis
• Refractory autoimmune uveitis
ADR
• Infusion reactions
• HBV reactivation
• Opportunistic infections
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
82 | P a g e
drprabhatdevkota@gmail.com
ULTRA-HIGH-YIELD COMPARISON
Drug
Class +
MOA
Indications +
Contraindications
Dose +
Onset
MajorADR
Key
Remark
s
Methotrexat
e (MTX)
Antimetabolit
e (1st line);
Inhibits
DHFR → ↓
THF → ↓
DNA
synthesis; ↑
Adenosine →
↓ T-cell
activation
Indications: JIAuveitis
(gold standard),
Anterior/Intermediate
uveitis, VKH, SO,
Serpiginous, OCP,
Scleritis. Contra:
Pregnancy, chronic liver
disease, severe renal
failure, alcohol abuse, ILD
7.5–25
mg/wee
k
(PO/SC)
; Folic
acid
mandato
ry;
Onset:
3–6 mo
Hepatotoxicit
y, BM
suppression,
Interstitial
pneumonitis,
Teratogenicity
; Nausea
(MC)
Monitor
CBC/LF
T; No ↑
malignan
cy risk in
children
(SITE);
Alcohol
abstinenc
e
Mycopheno
late mofetil
(MMF)
Antimetabolit
e; Inhibits
IMPDH → ↓
guanosine
synthesis →
Selective T &
B cell
suppression
Indications: Posterior
uveitis, Panuveitis,
Birdshot, Behçet, OCP,
Scleritis, MTX non-
response. Contra:
Pregnancy, severe
infection, leukopenia
1–3
g/day
(BD);
Onset:
3–4 mo
Diarrhea
(MC),
Leukopenia,
Infection,
Rare
lymphoma
Safer in
liver
disease;
Good for
posterior
disease
Azathioprin
e (AZA)
Antimetabolit
e; Converted
to 6-MP →
Inhibits
purine
synthesis;
TPMT
dependent
Indications: Preferred in
pregnancy, Sarcoidosis,
Pars planitis, VKH,
Behçet, JIA. Contra:
TPMT deficiency,
cytopenia, active
malignancy
1–2.5
mg/kg/d
ay;
Onset:
~4 mo
Leukopenia,
Hepatitis,
Pancreatitis, ↑
Malignancy
(highest
among
antimetabolite
s)
TPMT
testing
mandator
y;
Weekly
CBC
initially
Cyclosporin
e
Calcineurin
inhibitor;
Binds
cyclophilin
→ Inhibits
calcineurin
→ ↓ IL-2 →
↓ T-cell
activation
Indications: Behçet
posterior uveitis, VKH,
Birdshot, SO, Sarcoid.
Contra: Uncontrolled
HTN, renal insufficiency,
malignancy
2.5–5
mg/kg/d
ay;
Onset:
4–8 wks
Nephrotoxicit
y (dose
limiting),
HTN,
Gingival
hyperplasia,
Hypertrichosis
Monitor
BP &
Creatinin
e;
Combina
tion
therapy
common
Tacrolimus
Calcineurin
inhibitor;
Binds FKBP
Indications: CsA
intolerance, similar T-cell
mediated uveitis. Contra:
0.05–0.2
mg/kg/d
ay;
Nephrotoxicit
y,
Neurotoxicity
Fewer
cosmetic
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
83 | P a g e
drprabhatdevkota@gmail.com
Drug
Class +
MOA
Indications +
Contraindications
Dose +
Onset
MajorADR
Key
Remark
s
→ Inhibits
calcineurin
(more potent
than CsA)
Renal failure, uncontrolled
DM
Onset:
4–8 wks
(tremor),
Hyperglycemi
a/DM
ADR
than CsA
Cyclophosp
hamide
Alkylating
agent (last
resort); DNA
alkylation →
Cross-linking
→ B & T cell
death
Indications: Necrotizing
scleritis, PUK
(GPA/RA/PAN), OCP,
Bilateral Mooren, Severe
Behçet. Contra:
Pregnancy, marrow
suppression, infection
1
mg/kg/d
ay PO
OR IV1
g/m²
q2w;
Onset:
4–8 wks
Hemorrhagic
cystitis,
Infertility,
Bladder CA,
BM
suppression
Hydratio
n
mandator
y;
Monitor
urine;
Target
WBC
3500–
4000
Adalimuma
b
Biologic
(Anti-TNF-α,
fully human
mAb);
Blocks TNF-
α
inflammatory
cascade
Indications: Noninfectious
intermediate/posterior/pan
uveitis, JIA, Behçet.
Contra: Active infection,
untreated TB, MS, recent
malignancy
40 mg
SC q2w;
Onset:
~12 wks
TB
reactivation,
Demyelinatio
n, Lymphoma
risk, Injection
reaction
Screen
TB &
HBV;
VISUAL
&
SYCAM
ORE
trials
Infliximab
Biologic
(Anti-TNF-α,
chimeric
mAb)
Indications: Severe
Behçet (rapid control),
refractory posterior
uveitis. Contra: Active
infection, TB
3–5
mg/kg
IV
(0,2,6
wks →
q4–8w);
Onset:
6–12
wks
Infusion
reaction, Anti-
drug
antibodies, TB
reactivation
Faster
than
ADA;
Preferred
in
fulminant
Behçet
Tocilizuma
b
Biologic
(Anti-IL-6
receptor)
Indications: Refractory
uveitic macular edema
(best), Retinal vasculitis,
GCA. Contra: Active
infection
Monthly
IV/SC;
Onset:
8–12
wks
Hyperlipidemi
a, ↑ LFT,
Infection
Best
biologic
for
refractory
UME
Rituximab
Biologic
(Anti-CD20);
Indications: ANCA
vasculitis, refractory
IV
infusion
Infusion
reaction, HBV
Preferred
in
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
84 | P a g e
drprabhatdevkota@gmail.com
Drug
Class +
MOA
Indications +
Contraindications
Dose +
Onset
MajorADR
Key
Remark
s
B-cell
depletion
scleritis, severe
autoimmune uveitis.
Contra: Active infection,
HBV
(2 doses
2 wks
apart);
Onset:
2–3 mo
reactivation,
Opportunistic
infection
ANCA-
associate
d disease
FINAL EXAM PEARLS
• First-Line & Drug Selection
• MTX → Most common first-line IMT
• MMF → Strong for posterior/panuveitis
• AZA→ Pregnancy-safe IMT
• Adalimumab → Only FDA-approved biologic for noninfectious uveitis
• JIAchild → MTX →Adalimumab (if refractory)
• Pregnancy requiring IMT →Azathioprine
• Posterior disease → MMF
• Fulminant Behçet → Infliximab
• Necrotizing scleritis / PUK → Cyclophosphamide
• Life-threatening systemic vasculitis → Cyclophosphamide
• Refractory Uveitic Macular Edema (UME) → Tocilizumab
• ANCA-associated vasculitis → Rituximab
• Always screen TB before TNF inhibitors
• Avoid TNF inhibitors in Multiple Sclerosis
• Nephrotoxicity → Cyclosporine, Tacrolimus
• Hemorrhagic cystitis → Cyclophosphamide
• Maintain remission for ≥ 24 months before tapering IMT
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
85 | P a g e
drprabhatdevkota@gmail.com
SODIUM CHLORIDE (HYPERTONIC SALINE)
Mechanism / Pharmacology
Sodium chloride is a normal component of tears; 0.9% solution = isotonic with tears.
Hypertonic solutions (2%–5%) create an osmotic gradient that draws fluid from the cornea →
reduces corneal edema.
5% ointment: maximum effect occurs 3–4 hours after application.
Requires an intact epithelium for optimal efficacy; damaged epithelium reduces osmotic
effect due to increased penetration of salt.
Formulations: 2% solution, 5% solution, 5% ointment.
Indications / Clinical Uses
Reduction of corneal edema in various conditions:
• Bullous keratopathy
• Fuchs’ endothelial dystrophy
• Post-surgical corneal edema
• Acute corneal hydrops in keratoconus (limited efficacy if epithelium is compromised)
Dosage / Administration:
Drops: 1–2 drops every 3–4 hours; more frequent in early morning for worst vision.
Ointment: Nighttime use; less frequent dosing.
Special considerations:
Hot, dry days may reduce need due to increased tear evaporation.
5% concentration generally more effective than 2%.
Side Effects / Adverse Reactions
Topical discomfort: stinging, burning, irritation (common, especially 5%)
Epistaxis: reported with 2% solution
Visual considerations: improves vision, usually outweighs mild discomfort
Storage: do not use if solution changes color or becomes cloudy
High-Yield Exam Pearls
Hypertonic saline works only with intact epithelium; damaged epithelium reduces osmotic
effect.
5% ointment → longest-lasting effect; best for nighttime use.
For morning corneal edema, several early-morning instillations improve vision.
Side effects are generally tolerable and predictable; patient counseling important.
Useful in Fuchs’, bullous keratopathy, post-surgical edema.
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
86 | P a g e
drprabhatdevkota@gmail.com
STAINS IN OPHTHALMOLOGY
Feature
Fluorescein
Sodium
Rose Bengal
Lissamine
Green
Indocyanine
Green (ICG)
Methylen
e Blue
Light /
Excitation
Cobalt blue 493
nm → emits 520
nm (green)
Visible light →
pink/magenta
Visible light
→ green
Near-infrared
805 nm →
emits 835 nm
Absorptio
n 660 nm
→ blue
Vital / Non-vital
Vital (stains
intercellular
spaces &
damaged
epithelium)
Non-vital / stains
devitalized &
unprotected cells
Non-vital /
stains
degenerate
& mucus
cells
Vital for
vascular
imaging
Vital for
nerves &
devitalized
tissue
Main Clinical
Uses
-
Corneal/conjuncti
val defects-
TBUT- Lacrimal
drainage test-
Goldmann
tonometry-
Fluorescein
angiography- Iris
angiography-
Aqueous &
vitreous
fluorophotometry
- Dry eye diagnosis-
Corneal/conjunctiva
l lesions- Edge of
herpetic dendritic
ulcers
- Dry eye
evaluation-
Conjunctiva
l & corneal
epithelial
cell damage
- Retinal &
choroidal
angiography-
Choroidal
neovascularizati
on detection
- Corneal
nerve
staining-
Lacrimal
sac
visualizati
on (DCR)-
Lens
capsule
staining in
cataract
surgery
Advantages /
High Yield
Bright green
fluorescence at
physiologic pH,
hydrophilic, low
toxicity, widely
available
Highlights
devitalized/unprotec
ted cells, useful in
Sjögren’s
Less
irritating
than rose
bengal,
longer-
lasting
staining
Near-IR
penetrates
pigment &
hemorrhage,
binds plasma
proteins → less
leakage
Stains
devitalized
cells,
mucus,
nerves;
useful in
surgery
Disadvantages /
Side Effects
Topical: mild
irritation, stains
contact lensesIV:
nausea, vomiting,
rare allergy,
skin/urine
discoloration
Irritating,
phototoxic, may kill
cells/virus, stains
skin/clothing
Minimal
irritation,
rare allergy
Rare allergic
reactions, avoid
in
iodine/shellfish
allergy,
pregnancy not
established
Irritating,
temporary
tissue
staining
Special
Precautions /
Allergy, prior
severe reaction;
Avoid before viral
culture of herpetic
Avoid
contaminati
Iodine allergy,
shellfish allergy,
Allergy to
dye; use
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
87 | P a g e
drprabhatdevkota@gmail.com
Feature
Fluorescein
Sodium
Rose Bengal
Lissamine
Green
Indocyanine
Green (ICG)
Methylen
e Blue
Contraindicatio
ns
careful use in
pregnancy
lesions; stains
skin/clothes
on with
contact
lenses
high risk
anaphylaxis
topical
anesthetic
to reduce
irritation
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
88 | P a g e
drprabhatdevkota@gmail.com
ANTIALLERGIC DRUGS
1.Topical H1Antihistamines
Drugs
First-generation: Pheniramine, Antazoline (usually combined with naphazoline)
Second-generation: Emedastine, Azelastine, Ketotifen, Olopatadine
Pharmacology
First-generation:
Block H1 receptors → relieve itching, redness, tearing
Often combined with decongestants (naphazoline)
Second-generation:
Selective H1 receptor antagonists
Inhibit histamine release from mast cells
No effect on α-adrenergic, dopamine, muscarinic, serotonin receptors
Onset: 10–20 min
Duration: 4–24 h depending on drug
Clinical Uses
• Seasonal allergic conjunctivitis (SAC)
• Perennial allergic conjunctivitis (PAC)
• Mild VKC (symptomatic relief)
• Relief of ocular itching, redness, chemosis, tearing
Side Effects
• Burning, stinging, discomfort on instillation
• Pheniramine: less stinging than antazoline
• Antazoline–naphazoline: mydriasis (light irides), verticillate keratopathy with long-term use
• Rare: drug-induced allergy
Contraindications
• Allergy to components
• Narrow-angle glaucoma (risk of mydriasis)
• Caution with systemic antihistamines (sedation)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
89 | P a g e
drprabhatdevkota@gmail.com
2. Mast Cell Stabilizers
Drugs
Cromolyn sodium (2%), Lodoxamide, Nedocromil, Pemirolast, Sodium cromoglycate
Pharmacology
• Inhibit mast cell degranulation → prevent histamine and mediator release
• Additional effects (drug-dependent):
• Lodoxamide: inhibits eosinophil migration, leukotriene production; superior to cromolyn in
VKC
• Nedocromil: inhibits multiple inflammatory cells; faster onset (15–30 min)
• Pemirolast: inhibits eosinophil chemotaxis
• Azelastine (dual effect): effective in VKC
• Mechanism may include inhibition of calcium influx and broader effects on inflammatory
cell chemotaxis
• Require continuous administration; clinical response may take up to 2 weeks in mild
VKC
Clinical Uses
• SAC, PAC, VKC (especially atopic), GPC
• First-line therapy in VKC
• Maintenance therapy or adjunct to rapid-acting drugs
Dosage
4–6 times/day; maintenance 2 times/day
Nedocromil: 2 times/day
Side Effects
• Burning, stinging, conjunctival injection, itchy/watery eyes
• Headache (more with nedocromil, pemirolast)
• Minimal systemic absorption
Contraindications: Allergy to drug components
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
90 | P a g e
drprabhatdevkota@gmail.com
3. Mast Cell–Antihistamine Combinations (Dual-Action Drugs)
Drugs
Olopatadine, Ketotifen, Azelastine, Epinastine
Pharmacology
H1 receptor antagonism + mast cell stabilization
Inhibit mast cell degranulation, basophil release, eosinophil chemotaxis
Drug-specific notes:
Olopatadine: high H1 affinity, mild H2/H3; inhibits cytokine production
Ketotifen: binds H1/H2/H3; decreases eosinophil activation
Azelastine: selective H1; inhibits eosinophil activation
Epinastine: weak H2/H3, α1/α2 adrenergic effect; inhibits eosinophil chemotaxis
Onset: within minutes
Clinical Uses
• Ocular itching, allergic conjunctivitis, VKC
• Rapid symptomatic relief + long-term prevention
• Olopatadine 0.2%: 24-hour duration, once daily
• Other dual-action drugs: twice daily dosing
Side Effects
• Burning, stinging, foreign body sensation, dry eye, pruritus
• Systemic: headache, flu-like symptoms, rhinitis
• Most common: headache + burning/stinging
Contraindications: Allergy to drug components
High-Yield Exam Pearls
• Mast cell stabilizers = prophylactic, slow onset; prevent degranulation, broader anti-
inflammatory effects.
• Dual-action drugs (Olopatadine, Ketotifen, Azelastine, Epinastine) = rapid relief + long-
term benefit.
• First-generation antihistamines = symptomatic relief; may cause mydriasis.
• VKC management hierarchy:
• Mild → topical antihistamines or mast cell stabilizers
• Moderate → dual-action drugs
• Severe/resistant → topical cyclosporine ± short-term corticosteroids
• Onset: dual-action <10 min; mast cell stabilizers days to 2 weeks.
• Dosage frequency: mast cell stabilizers 4–6x/day; dual-action drugs usually 2x/day
(Olopatadine 0.2% = once/day).
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
91 | P a g e
drprabhatdevkota@gmail.com
LOCAL ANESTHETICS
I. Ester-linked:
(Metabolized by plasma cholinesterase → Higher allergy risk (PABA derivatives) → Shorter acting)
• Cocaine
• Proparacaine
• Procaine
• Chloroprocaine
• Tetracaine
• Benoxinate
II.Amide-linked:
(Metabolized in liver (hepatic microsomal enzymes)→ Longer acting→ Rare allergy)
• Lidocaine
• Mepivacaine
• Bupivacaine
• Etidocaine
Lignocaine (Lidocaine)
Amide-linked local anesthetic
Intermediate potency
Intermediate duration of action
Mechanism ofAction
Blocks voltage-gated sodium channels
Prevents Na⁺ influx during depolarization
Stabilizes neuronal membrane
Reversibly blocks nerve impulse conduction
Acts preferentially on: Small Myelinated fibers (pain first)
Order of block: Pain → Temperature → Touch → Pressure → Motor
Pharmacokinetics
• Rapid onset (2–5 min)
• Highly lipid soluble
• Crosses BBB & placenta
• Hepatic metabolism (CYP450)
• Metabolites excreted in urine
• 60–90 min (without adrenaline)
• 90–120 min (with adrenaline)
Preparations in Ophthalmology
• 2% Lignocaine – most common
• 1% (minor procedures)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
92 | P a g e
drprabhatdevkota@gmail.com
• With adrenaline (1:100,000 or 1:200,000)
• Preservative-free (intraocular use)
Dosage
Without Adrenaline: Max dose: 3–5 mg/kg
With Adrenaline: Max dose: 7 mg/kg
Uses in Ophthalmology
A. Injectable Anesthesia
• Peribulbar block
• Retrobulbar block
• Sub-Tenon’s anesthesia
• Facial nerve block
B. Topical Use
• 4% solution (less common)
• Intracameral use (0.5–1%)
C. Intracameral
• Used in cataract surgery
• Provides analgesia without akinesia
Adverse Effects
Local Toxicity
• Chemosis
• Subconjunctival hemorrhage
• Myotoxicity (extraocular muscle damage)
• Corneal toxicity (with repeated topical use)
Systemic Toxicity
CNS
• Circumoral numbness
• Tinnitus
• Metallic taste
• Dizziness
• Seizures
• CNS depression
• Respiratory arrest
Cardiovascular
• Hypotension
• Arrhythmias
• Bradycardia
• Cardiac arrest
Contraindications
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
93 | P a g e
drprabhatdevkota@gmail.com
• Severe hepatic disease
• Hypersensitivity (rare)
• Severe heart block
• Caution in elderly & cardiac patients
Proparacaine
Drug class: Local anesthetic (amide-type)
Commercial concentration: 0.5% solution
Formulations: With or without 0.25% sodium fluorescein
Pharmacology
Blocks sodium channels → inhibits nerve impulse conduction → local anesthesia
Onset, intensity, and duration similar to tetracaine 0.5% and benoxinate 0.4%
Penetration: Less corneal/conjunctival penetration than tetracaine
Effect on corneal thickness: Temporary instability (~5 min) after administration → important
for pachymetry or refractive surgery measurements
Clinical Uses
• General-purpose topical anesthesia for:
• Slit-lamp procedures
• Minor ocular surface surgery
• Tonometry, gonioscopy, foreign body removal
• Widely accepted by patients due to minimal discomfort on instillation
Advantages
• Less pain on instillation than tetracaine (~86% of patients preferred)
• Minimal irritation
• Can be combined with fluorescein for corneal staining
Storage
Unopened: Room temperature
Opened: Keep tightly capped; refrigerate to prevent discoloration
Discard if solution is discolored
Side Effects
Common: Minimal; generally well tolerated
Rare:
Local allergic hypersensitivity (conjunctival hyperemia, eyelid edema, lacrimation)
Allergic contact dermatitis (fingertips in healthcare workers)
Cross-sensitivity with tetracaine possible
Exacerbation of preexisting Stevens-Johnson syndrome (rare)
Transient corneal thickness instability (~5 min)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
94 | P a g e
drprabhatdevkota@gmail.com
BOTULINUM TOXIN (BOTOX)
FDAapproval: 1978 (for facial dystonias)
Most accepted treatment for Benign Essential Blepharospasm (BEB)
90% patients show significant symptomatic improvement
Used widely in ophthalmology, oculoplasty, strabismus, cosmetic and therapeutic indications
Mechanism ofAction
Source
Produced by Clostridium botulinum
7 serotypes: A–G
Clinical use: Type A(most common) and Type B
Action
• Blocks acetylcholine (ACh) release at presynaptic neuromuscular junction
• Inhibits ACh exocytosis → prevents muscle contraction
• Causes temporary chemodenervation
• Results in localized muscle paralysis
Key Points
Effect is reversible
Neurotransmission restored in weeks to months
Does NOT destroy nerve → causes functional block
Potency & Preparation
Unit Definition
Potency expressed in International Units (IU)
1 IU = LD50 in 50% female Swiss-Webster mice (intraperitoneal injection)
Formulation
Available as lyophilized freeze-dried powder
Vials: 50, 100, 200 units
Contains:
Human albumin
Preservative-free sodium chloride
Requires reconstitution with normal saline
Final concentration: 2–10 U per 0.1 mL
Types of Botulinum Toxin
TypeA
Most commonly used
Brands: Botox®
Type B
Myobloc®
Structurally similar but different molecular constitution
Available as liquid (no reconstitution required)
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
95 | P a g e
drprabhatdevkota@gmail.com
Used in TypeAresistance
Dose is 50–100× higher than TypeA
Typical dose: 1200–2500 U per eye
Indications in Ophthalmology
• Benign Essential Blepharospasm (BEB)
• Hemifacial spasm
• Meige syndrome
• Apraxia of eyelid opening
• Strabismus (selected cases)
• Upper eyelid retraction (thyroid eye disease)
• Spastic entropion
• Cosmetic indications (crow’s feet)
Injection Technique
Pre-procedure
Antiseptic skin preparation
Detailed examination & injection planning
Informed consent
Pre-injection documentation (photos/video)
Optional topical anesthetic (1% lidocaine cream)
Post-Procedure Care
Avoid strenuous activity for 24 hrs
Avoid pressure/massage for 24 hrs
Avoid lying face down
Avoid alcohol same day
No facial massage for 24–48 hrs
Cold compress for bruising
Resume anticoagulants next day
Pharmacodynamics
Parameter Value
Onset 2–3 days
Peak effect 7–10 days
Duration 3–4 months
Review After 10 days
Reinjection required every 3–4 months
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
96 | P a g e
drprabhatdevkota@gmail.com
Contraindications
Absolute
• Allergy to Botox/Dysport/Xeomin/Myobloc
• Pregnancy
• Lactation
• Neuromuscular junction disorders:
• Myasthenia gravis
• ALS
• Infection at injection site
Relative
• Chronic anticoagulant therapy
• Drugs decreasing neuromuscular transmission:
• Aminoglycosides
• Penicillamine
• Quinine
• Calcium channel blockers
Complications
• Bruising
• Local pain
• Ocular
• Blepharoptosis (10–15%) → due to levator diffusion
• Ectropion
• Lagophthalmos
• Corneal exposure
• Dry eye
• Diplopia
• Systemic weakness
Important Exam Pearls
• Gold standard treatment for BEB
• Works by blocking ACh release at NMJ
• Effect is temporary chemodenervation
• Onset: 2–3 days, peak at 7–10 days
• Duration: 3–4 months
• Ptosis is most common significant complication (10–15%)
• Type B used in TypeAresistance
• Avoid central pretarsal injection to prevent ptosis
• Avoid in myasthenia gravis
• 1 IU defined by mouse LD50
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
97 | P a g e
drprabhatdevkota@gmail.com
MITOMYCIN-C (MMC)
Mitomycin-C is an antineoplastic antibiotic isolated from Streptomyces caespitosus.
Differentiated from Mitomycin A& B (same organism).
First ophthalmic use: 1969 (Japan) – recurrent pterygium.
Widely used as an antifibrotic adjunct in ocular surgeries.
Chemical & Molecular Profile
Chemical formula: C₁₅H₁₈N₄O₅
Alkylating antimetabolite
Quinone-containing compound
Becomes active after intracellular reduction
Preparation:
2 mg MMC vial (powder) & Sterile distilled water for injection required
To make 0.02% (0.2 mg/mL) → dissolve 2 mg in 10 mL sterile water.
To make 0.04%(0.4 mg/mL) → dissolve 2 mg in 5 mL sterile water.
Mitomycin-C (MMC) Preparation for Glaucoma Surgery
• MMC vial: 10 mg
• Add: 10 mL sterile water
• Stock concentration: 1 mg/mL
➢ Phaco + Trabeculectomy:
Sponge Application (0.4 mg/mL)
• 1 mL of 1 mg/mL MMC
o 1.5 mL sterile water
• → Final concentration: 0.4 mg/mL
➢ Trabeculectomy Alone:
Sponge Application (0.2 mg/mL)
• 1 mL of 1 mg/mL MMC
o 4 mL sterile water
• → Final concentration: 0.2 mg/mL
Mechanism ofAction
Antimetabolite
Alkylating agent
Anti-proliferative
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
98 | P a g e
drprabhatdevkota@gmail.com
Mechanism ofAction
Prodrug → activated by intracellular reduction
Loss of methoxy group → forms bi-/tri-functional alkylating agent
Causes DNAcross-linking
N-position of adenine
O6 & N-position of guanine
Inhibits DNAreplication and transcription
Suppresses fibroblast proliferation
Produces antifibrotic and antimitotic effect
Cell Cycle Effect
Maximal effect in:
Late G1 phase
Early S phase
Overall: Cell cycle non-specific alkylating agent
Exam Pearl:
Acts by DNAcross-linking → inhibition of mitosis → reduced fibrosis & tumor growth.
Pharmacokinetics & Bioavailability
• Delivered in fully solubilized form
• Highly bioavailable when epithelium is denuded
• Hydrophobic → penetrates denuded cornea/conjunctiva
• Minimal penetration through intact epithelium
• No detectable systemic blood levels after topical use
Preparation & Storage
Reconstituted in sterile water at neutral pH
Inactivated in acidic solutions
Stored under refrigeration
Stable for 2 weeks after reconstitution
Clinical Uses in Ophthalmology
Major Uses
Ocular surface tumors
Pterygium surgery
Dacryocystorhinostomy (DCR)
Strabismus surgery
Refractive surgery (PRK)
Allergic conjunctivitis
MMC in Ocular Surface Tumors
Indications
Conjunctival SCC
OSSN
PG Notes: Drugs in Ophthalmology Dr. Prabhat Devkota, MD
99 | P a g e
drprabhatdevkota@gmail.com
Recurrent or multifocal lesions
Advantages
Treats satellite lesions
Treats entire ocular surface
No need for margin control
Dose
0.04% (0.4 mg/ml)
QID for 3 weeks
Key Point
Rapidly cycling tumor cells affected
Stem cells relatively spared
MMC in Pterygium Surgery
Role
Prevents recurrence by inhibiting fibroblast proliferation
Intraoperative Use
0.02–0.04% (0.2–0.4 mg/ml)
Applied over bare sclera
Duration: 1–5 minutes
Postoperative Use (Older Regimen)
0.04% QID × 2 weeks
Evidence-Based Insight
Recurrence reduced to ~2%
Placebo recurrence ~88%
Warning (Exam Favorite)
Postoperative prolonged use → severe complications
Iritis
Secondary glaucoma
Corneal edema
Cataract
Scleral calcification
Corneal perforation
⚠ Currently preferred: Short intraoperative application
MMC in Dacryocystorhinostomy (DCR)
Rationale
Failure due to fibrous closure of:
Osteotomy site
Common canaliculus
Use
Applied over osteotomy site & flaps
0.02–0.04%
Duration: 5–30 minutes