Treatment of Hyperlipidemias
Pharmacology Team
Ansam Sawalha, Adham Abu Taha, Suhaib Hattab,
Naim Kittana and Waleed Sweileh
An-Najah National University
Faculty of Medicine and Health Sciences
Department of Biomedical Sciences
1
Risk factors for coronary heart disease (CHD):
1. High LDL cholesterol and TG
2. low HDL cholesterol.
3. Cigarette smoking
4. Hypertension
5. Obesity
6. Diabetes
2
• Elevated cholesterol can be due to:
1. Lifestyle: lack of exercise and consumption of a diet
containing excess saturated fatty acids
2. A single inherited gene defect in lipoprotein metabolism
3. A combination of genetic and lifestyle factors.
3
TREATMENT GOALS
• The primary goal: Reduction of the LDL level
• Recommendations for the reduction of LDL cholesterol to
specific target levels are influenced by
– Coexistence of CHD
– number of other cardiac risk factors
• The higher the overall risk of heart disease, the more
aggressive the recommended LDL-lowering therapy.
4
ATHEROSCLEROSIS
A. Significance: Major cause of death in the U.S. (heart attacks
and strokes)
B. Risk Factors: Hypertension, age, obesity, diabetes, high fat
diet, smoking, stress, low HDL, lack of exercise, family history
and high plasma lipoproteins (VLDL, IDL and LDL).
5
ATHEROSCLEROSIS
C. Pathogenesis:
- Elevated plasma lipoproteins such as VLDL, IDL and LDL are a
major risk factor in atherosclerosis
- Endothelium of blood vessel is injured and blood components
(LDL and platelets) infiltrate injured area.
- Growth factors cause proliferation of cells and plaque starts to
form at site of injury.
6
ATHEROSCLEROSIS
C. Pathogenesis: (Continue)
- Cells internalize LDL (oxidized) and form foam cells (saturated
with fat).
- Cells die and plaque is formed.
- Narrowed vessel gets clogged by blood clot and stroke or heart
attack is the consequence.
7
D. Rationale of treatment: Studies have clearly demonstrated
that appropriate diet and drugs reduces atherosclerosis-
induced mortality 20 to 40%.
ATHEROSCLEROSIS
8
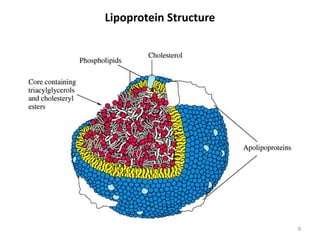
Lipoprotein Structure
9
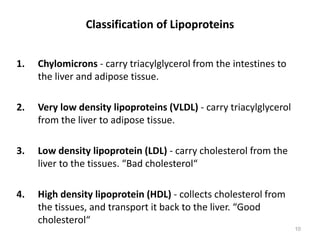
Classification of Lipoproteins
1. Chylomicrons - carry triacylglycerol from the intestines to
the liver and adipose tissue.
2. Very low density lipoproteins (VLDL) - carry triacylglycerol
from the liver to adipose tissue.
3. Low density lipoprotein (LDL) - carry cholesterol from the
liver to the tissues. “Bad cholesterol“
4. High density lipoprotein (HDL) - collects cholesterol from
the tissues, and transport it back to the liver. “Good
cholesterol“
10
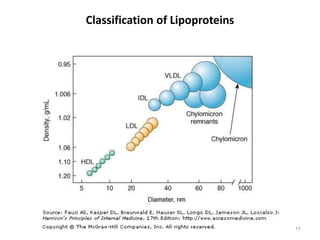
Classification of Lipoproteins
11
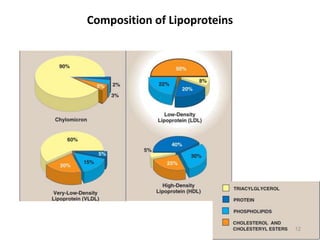
Composition of Lipoproteins
12
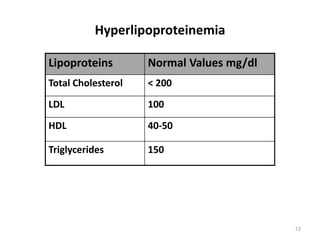
Hyperlipoproteinemia
Lipoproteins Normal Values mg/dl
Total Cholesterol < 200
LDL 100
HDL 40-50
Triglycerides 150
13
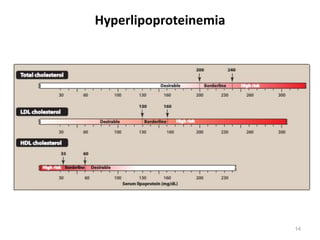
Hyperlipoproteinemia
14
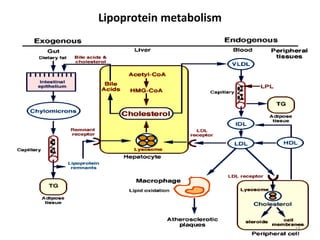
Lipoprotein metabolism
15
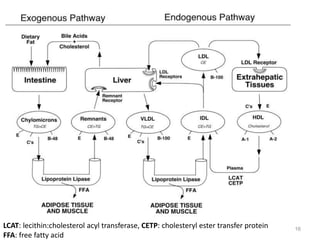
LCAT: lecithin:cholesterol acyl transferase, CETP: cholesteryl ester transfer protein
FFA: free fatty acid
16
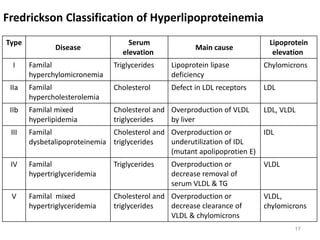
Fredrickson Classification of Hyperlipoproteinemia
Lipoprotein
elevation
Main cause
Serum
elevation
Disease
Type
Chylomicrons
Lipoprotein lipase
deficiency
Triglycerides
Familal
hyperchylomicronemia
I
LDL
Defect in LDL receptors
Cholesterol
Familal
hypercholesterolemia
IIa
LDL, VLDL
Overproduction of VLDL
by liver
Cholesterol and
triglycerides
Familal mixed
hyperlipidemia
IIb
IDL
Overproduction or
underutilization of IDL
(mutant apolipoprotien E)
Cholesterol and
triglycerides
Familal
dysbetalipoproteinemia
III
VLDL
Overproduction or
decrease removal of
serum VLDL & TG
Triglycerides
Familal
hypertriglyceridemia
IV
VLDL,
chylomicrons
Overproduction or
decrease clearance of
VLDL & chylomicrons
Cholesterol and
triglycerides
Familal mixed
hypertriglyceridemia
V
17
Treatment options for hypercholesterolemia
• Moderate hyperlipidemia:
– Lifestyle changes, such as diet, exercise, and weight
reduction, can lead to modest decreases in LDL levels and


increases in HDL levels.
– Patients who are unwilling to modify their lifestyle drug
therapy may be required.
18
Drug therapy:
Patients with
– LDL levels >160 mg/dL
– one other major risk factor, such as hypertension,
diabetes, smoking, or a family history of early CHD
Aggressive treatment:
– Patients with two or more additional risk factors should be
treated aggressively
– Aim:
• reducing LDL level to less than 100 mg/dL and, in some
patients, to as low as 70 mg/dL.
19
Treatment options for hypertriacylglycerolemia
• Primary modes of treating hypertriacylglycerolemia:
– Diet
– Exercise
• Efficacious drugs in lowering TG:
1. Niacin
2. Fibric acid derivatives
20
21
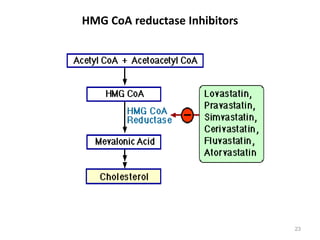
HMG CoA reductase Inhibitors (Statins) :
• Most efficacious and well tolerated.
• They act by competitive inhibition of HMG CoA reductase
– the rate limiting step in cholesterol synthesis.
22
HMG CoA reductase Inhibitors
23
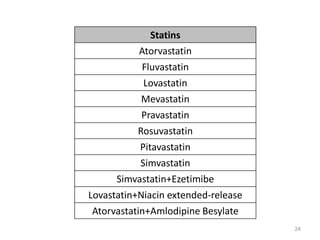
Statins
Atorvastatin
Fluvastatin
Lovastatin
Mevastatin
Pravastatin
Rosuvastatin
Pitavastatin
Simvastatin
Simvastatin+Ezetimibe
Lovastatin+Niacin extended-release
Atorvastatin+Amlodipine Besylate
24
HMG CoA reductase Inhibitors (Statins):
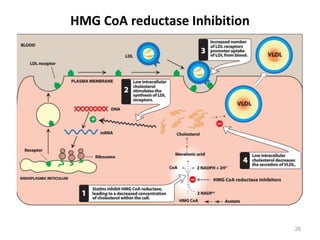
1. Reduced cholesterol synthesis results in a compensatory
increase in the hepatic uptake of plasma cholesterol
mediated by an increase in the number of LDL receptors.
2. Hepatic synthesis of VLDL is reduced
3. There is an increase in HDL levels
25
HMG CoA reductase Inhibition
26
• Lovastatin and Simvastatin:
– Prodrugs, have to be hydrolyzed to be activated.
– Cross the BBB and can cause sleep disturbances
• Fluvastatin – Less myopathy
• Atorvastatin and rosuvastatin are long acting
• Rosuvastatin, Pitavastatin, & Atorvastatin are the most
potent in decreasing LDL cholesterol.
• Atorvastatin (Lipitor®) – antioxidant effect
HMG CoA reductase Inhibitors
27
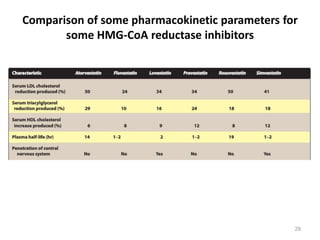
Pharmacokinetics:
• Absorption after oral administration:
– Pravastatin and fluvastatin: complete
– Lovastatin and simvastatin: 30 -50%
• Pravastatin and fluvastatin are active as such
• All are metabolized in the liver and excreted through bile and
feces, but there is also some urinary elimination
28
Comparison of some pharmacokinetic parameters for
some HMG-CoA reductase inhibitors
29
Therapeutic uses of HMG-CoA reductase inhibitors :
• Lowering plasma cholesterol levels in all types of hyperlipidemias
• Patients who are homozygous for familial hypercholesterolemia
lack LDL receptors and, therefore, benefit much less from
treatment with these drugs.
30
Adverse effects of HMG CoA reductase Inhibitors:
• Headache
• Sleep disturbances
• Hepatotoxicity
• Myopathy (muscle tenderness) and rhabdomyolysis
31
Drug interactions:
– May increase Warfarin levels
Contraindications:
• During pregnancy and in nursing mothers.
• In children or teenagers.
32
Bile acid–binding resins
 Cholestyramine
 Colestipol
 Colesevelam
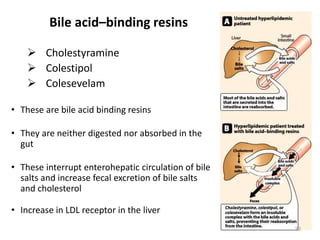
• These are bile acid binding resins
• They are neither digested nor absorbed in the
gut
• These interrupt enterohepatic circulation of bile
salts and increase fecal excretion of bile salts
and cholesterol
• Increase in LDL receptor in the liver
33
Effect of bile-acid binding resins
34
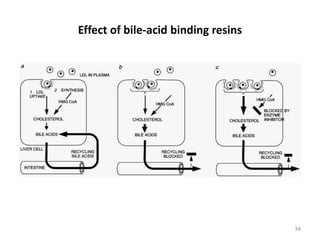
• Compensatory increase in the activity of HMG CoA reductase
results in increased cholesterol synthesis and thus increased
VLDL secretion – blunting the long term effectiveness of
monotherapy
• Mild increase in triglycerides can be seen.
Effect of bile-acid binding resins
35
Therapeutic uses of bile-acid binding resins:
• These are the drugs of choice (often in combination with diet
or niacin) in treating Type IIA and Type IIB hyperlipidemias
 [Note: In those rare individuals who are homozygous for
Type IIA, that is, for whom functional LDL receptors are
totally lacking, these drugs have little effect on plasma LDL
levels]
• Cholestyramine can also relieve pruritus caused by
accumulation of bile acids in patients with biliary obstruction
• It is also used to treat diarrhea
36
Adverse effects
• GI disturbances, such as constipation, nausea, and
flatulence.
• Colesevelam has fewer GI side effects than other bile
acid sequestrants.
• At high doses, cholestyramine and colestipol (but not
colesevelam) impair the absorption of the fat-soluble
vitamins (A, D, E, and K).
37
Drug interactions:
• Cholestyramine and colestipol interfere with the intestinal
absorption of many drugs (for example, tetracycline,
phenobarbital, digoxin, warfarin, pravastatin, fuvastatin,
aspirin, and thiazide diuretics).
• Therefore, drugs should be taken at least 1–2 hours before, or
4–6 hours after, the bile acid–binding resins.
38
• It decrease cholesterol absorption by localizing at the
brush border of the small intestine.
• Leads to an increase in LDL-cholesterol uptake into cells, thus
decreasing levels in the plasma.
• Can be used in combination with Simvastatin
Cholesterol uptake inhibitor: Ezetimibe
39
Pharmacokinetics of Ezetimibe
• Ezetimibe is metabolized in the small intestine and liver via
glucuronide conjugation, with subsequent biliary and renal
excretion.
• half-life of approximately 22 hours.
• Patients with moderate to severe hepatic insufficiency should
not be treated with ezetimibe.
40
Niacin (nicotinic acid)
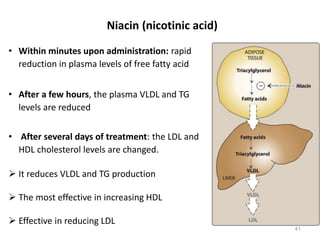
• Within minutes upon administration: rapid
reduction in plasma levels of free fatty acid
• After a few hours, the plasma VLDL and TG
levels are reduced
• After several days of treatment: the LDL and
HDL cholesterol levels are changed.
 It reduces VLDL and TG production
 The most effective in increasing HDL
 Effective in reducing LDL
41
Therapeutic uses of niacin:
• Niacin lowers both cholesterol and triacylglycerol.
• It is useful in the treatment of familial hyperlipidemias.
• Used in treating severe hypercholesterolemias
• It is the most potent anti-hyperlipidemic agent for raising
plasma HDL levels, which is the most common indication for
its clinical use.
42
Adverse effects of Niacin
• Cutaneous dilator – flushing, itching
• Liver dysfunction
• Hyperglycemia
• Potentiates gout (decrease uric acid secretion), diabetes and
peptic ulcers
43
Fibric acid derivatives
• Drugs:
 Fenofibrate (a prodrug for the active metabolite fenofibric
acid)
 Clofibrate
 Gemfibrozil
• They lower serum triacylglycerol and increase HDL levels
44
Mechanism of action of Fibric acid derivatives
• They interact with the peroxisome proliferator activated
receptor alpha (PPARα) which regulates gene expression of
enzymes involved in fatty acid oxidation.
• They increase expression of lipoprotein lipase, which
enhances clearance of triglyceride rich lipoproteins.
• Fibrates also increase the level of HDL cholesterol by
increasing the expression of apo AI and apo AII.
45
Therapeutic uses:
• Patients with hypertriacylglycerolemia (Type IV [elevated VLDL]
or Type V [elevated VLDL plus chylomicron] disease) who do not
respond to diet or other drugs may also benefit from treatment
with these agents.
• Treatment of Type III hyperlipidemia (dysbetalipo proteinemia),
in which intermediate-density lipoprotein particles accumulate.
46
Adverse effects:
• Gall stones with Clofibrate
• Myopathy (Myositis):
- Inflammation of skeletal muscles) causing muscle weakness
and tenderness
- Rhabdomyolysis can occur
- Risk is greatly increased in combination with statins
(contraindicated)
• Nausea
• Skin Rash
47
Drug interactions:
• Fibrates compete with the coumarin anticoagulants for
binding sites on plasma proteins (monitor INR frequently)
• They may transiently elevate the levels of sulfonylureas.
48
PCSK9 inhibitor
Alirocumab
Evolocumab
Alirocumab
Monoclonal Antibody - Proprotein Convertase Subtilisin/Kexin Type 9
(PCSK9) Inhibitor
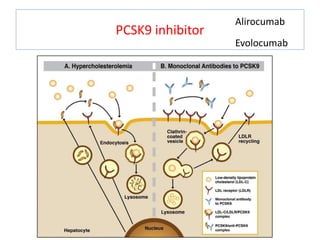
• PCSK9 is an enzyme that binds to an epidermal growth factor-
like domain of the LDL receptor, and targets it for lysosomal
degradation.
• degradation of LDL receptors reduces the amount of LDL that
can be cleared from the circulation
– If PCSK9 is inhibited (and does not bind to the LDL
receptor), the receptor can return to the surface of the
liver cell and remove more cholesterol.
• Inhibiting PCSK9 prevents destruction of the LDL receptor &
facilitates recycling of hepatic LDL receptors, which enhances
removal of LDL from the blood
• when added to patients taking statins, alirocumab produced
an additional 36-59% mean reduction in LDL compared to
those given a placebo
• Indications:
– Adjunct therapy (e.g. if statins are not enough) to lower
LDL in patients with
• heterozygous hypercholesterolemia (HeFH)
• atherosclerotic CV disease (e.g. myocardial infarction or
stroke)
– Used in combination with diet, exercise, and maximally
tolerated doses of statins
• Pharmacokinetics:
– subcutaneous injection
– after sc injection, maximal suppression of PCSK9 occurs in
4-8 hours
– half life 17-20 days
• at low concentrations the antibody (drug) is eliminated
by binding to its target
• at higher concentrations the drug is eliminated by
proteolytic degredation
• Side Effects:
– ~2% estimated incidence (but its still a new drug)
– itching, swelling, pain or bruising at the injection site
– nasopharyngitis, flu
– allergic reactions requiring hospitalization
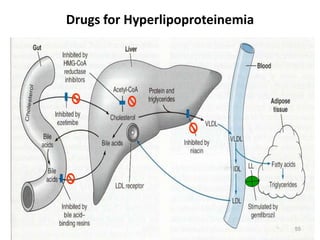
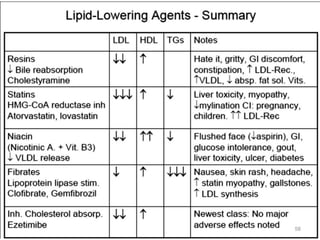
Drugs for Hyperlipoproteinemia
55
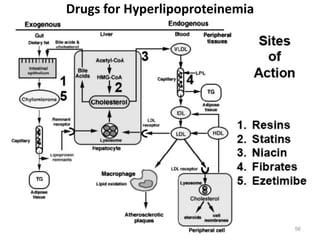
Drugs for Hyperlipoproteinemia
56
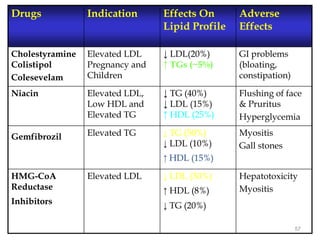
Drugs Indication Effects On
Lipid Profile
Adverse
Effects
Cholestyramine
Colistipol
Colesevelam
Elevated LDL
Pregnancy and
Children
↓ LDL(20%)
↑ TGs (~5%)
GI problems
(bloating,
constipation)
Niacin Elevated LDL,
Low HDL and
Elevated TG
↓ TG (40%)
↓ LDL (15%)
↑ HDL (25%)
Flushing of face
& Pruritus
Hyperglycemia
Gemfibrozil Elevated TG ↓ TG (50%)
↓ LDL (10%)
↑ HDL (15%)
Myositis
Gall stones
HMG-CoA
Reductase
Inhibitors
Elevated LDL ↓ LDL (30%)
↑ HDL (8%)
↓ TG (20%)
Hepatotoxicity
Myositis
57
58