Drugs for Diabetes
Mellitus
Dr. Arthi
II nd yr Post graduate
Department of Pharmacology
Rajah Muthiah Medical college
INSULIN
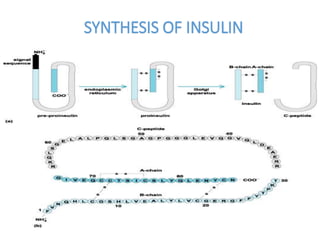
• Human insulin consists of 51 aa
in two chainsconnected by 2
disulfide bridges (a single gene
product cleaved into 2 chains
during post-translational
modification).
• T1/2 ~5-10 minutes, degraded by
glutathione-insulin
transhydrogenase (insulinase) which
cleavesthe disulfidelinks.
• Bovine insulin differs by 3aas,
pork insulin differs by 1aa.
• Insulin is stored in acomplexwith
Zn2+ions.
SYNTHESIS OF INSULIN
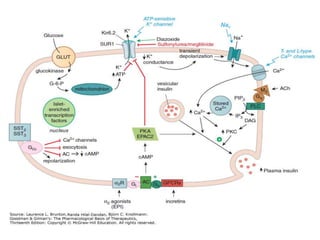
INSULIN RELEASE
• Secretion ismost commonly elicited by elevated glucose levels;
increasedglucoselevelsin β-cellsresults inincreased ATPlevels, this
results in ablock of K+channels causing membrane depolarization
which opensCa2+channels.
• Theinflux of Ca2+results in apulsatile secretion ofinsulin;
continued Ca2+influx results in activation of transcription factors
for insulin.
• Oral glucoseelicits more insulin secretion than IVglucose; oral
administration elicits gut hormones whichaugment the insulin
response.
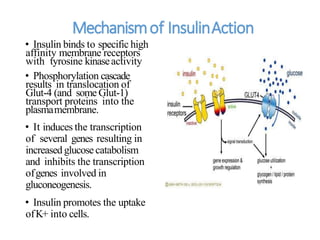
Mechanismof InsulinAction
• Insulin binds to specific high
affinity membrane receptors
with tyrosine kinaseactivity
• Phosphorylation cascade
results in translocation of
Glut-4 (and some Glut-1)
transport proteins into the
plasmamembrane.
• It induces the transcription
of several genes resulting in
increased glucosecatabolism
and inhibits the transcription
ofgenes involved in
gluconeogenesis.
• Insulin promotes the uptake
ofK+ into cells.
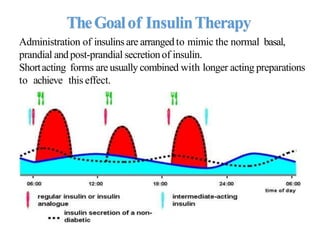
TheGoalof InsulinTherapy
Administration of insulins are arranged to mimic the normal basal,
prandial and post-prandial secretionof insulin.
Shortacting forms are usually combined with longer acting preparations
to achieve this effect.
Conventional insulins:
Short acting- regular insulin
Intermediate- NPH insulin
Insulin Analogs
Ultra short acting-Lispro, Aspart, Glulisine
Long acting- Glargine, Detemir
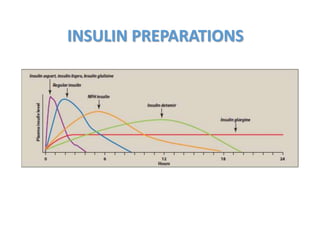
INSULIN PREPARATIONS
• Lispro, aspart and glulisine forms are classified as rapid-
acting insulins because of their rapid onset and short duration
of action
• Rapid acting insulins usually administered 15 minutes prior to a
meal or immediately following a meal
• These are mostly combined with basal insulin to maintain
baseline level of insulin.
• Onset of action is 15-30min and lasts for 3-4hrs.
RAPID ACTING INSULIN PREPARATIONS
Regular insulin:
starts within 60 min and lasts for 6-8 hrs ,
soluble human crystalline insulin with added Zn
ions
It controls the post prandial hypoglycemia
Intermediate –actingInsulinPreparations
Isophane NPHinsulin:
Neutral protamine insulin is a suspension of crystalline
zinc insulin combined with protamine (a polypeptide).
The conjugation with protamine delays its onset of
action and prolongs it effectiveness.
It is usually given in combination with regular insulin.
Long-actinginsulinpreparations
1.Insulin glargine: Precipitation at theinjection site
extends the duration of action of thispreparation. pH has to
kept acidic.
2.Detemir insulin: hasaFAsidechain complexed with insulin
resulting in slowdissolution.
3.Insulin degludec: has a FA side chain which allows
fomation of multi-hexamers forming a subcutaneous depot
resulting in slow dissolution.
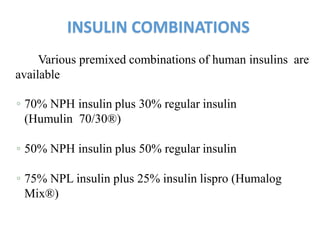
Various premixed combinations of human insulins are
available
◦ 70% NPH insulin plus 30% regular insulin
(Humulin 70/30®)
◦ 50% NPH insulin plus 50% regular insulin
◦ 75% NPL insulin plus 25% insulin lispro (Humalog
Mix®)
INSULIN COMBINATIONS
AdverseEffectsof Insulin
1. Hypoglycemia may occur due to insulin overdose,
insufficient caloric intake (missed meal, improper meal
content, delayed meal, etc.). Ethanol consumption
promotes hypoglycemic response.
Symptoms: ↑ HR, diaphoresis, anxiety,
2. Hypokalemia -insulin draws K+into the cell with glucose
(hyperglycemia with normalK+).
3. Lipodystrophy at injectionsite
4. Weight gain
5. Inslin reistance
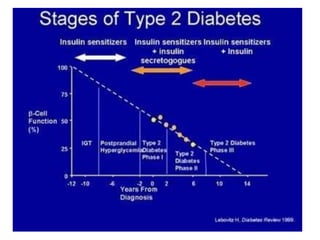
 Insulin secretagogues
◦ Sulfonylureas
 Meglitinides-Repaglinide, Nateglinide
 Insulin sensitizers
◦ Biguanides-Metformin
◦ Thiazolidinediones-Pioglitazone ,
Rosiglitazone
 α-Glucosidase inhibitor-Acarbose,
Miglitol, Voglibose
 Dipeptidyl peptidase-IV
inhibitors-Gliptins
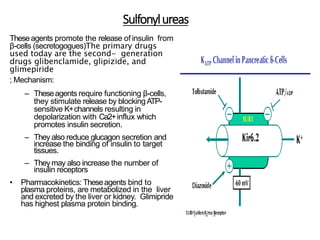
Sulfonylureas
Theseagents promote the release of insulin from
β-cells (secretogogues)The primary drugs
used today are the second- generation
drugs glibenclamide, glipizide, and
glimepiride
; Mechanism:
– Theseagents require functioning β-cells,
they stimulate release by blockingATP-
sensitive K+channels resulting in
depolarization with Ca2+influx which
promotes insulin secretion.
– Theyalso reduce glucagon secretion and
increase the binding of insulin to target
tissues.
– Theymay also increase the number of
insulin receptors
• Pharmacokinetics: Theseagents bind to
plasma proteins, are metabolized in the liver
and excreted by the liver or kidney. Glimipride
has highest plasma protein binding.
Sulfonylureas
Adverse Effects:
• Theseagents tend to causeweight gain,
hyperinsulinemia and hypopglycemia.
• Hepatic or renal insufficiency causes
accumulation of these agents promoting the
risk of hypoglycemia.
• There are anumber of drug-drug interactions.
Elderly patients appear particularly susceptible
to the toxicities of theseagents.
Meglitinideanalogs
Theseagents repaglinide and nateglinide act as secretogogues.
• Mechanism: Bind to ATPsensitive K+channels like
sulfonylureas acting in asimilar fashion to promote insulin
secretion however their onset and duration of action are
much shorter.
• When used in combination with other oral agents they
produce better control than any monotherapy.
• Adverse Effects: Lesshypoglycemia than sulfonylureas
• Drugs that inhibit CYP3A4(ketoconozole, fluconazole,
erythromycin, etc.) prolong their duration of effect.
• Drugs that promote CYP3A4(barbiturates,
carbamazepine and rifampin) decrease their
effectiveness.
Insulin Sensitizers
Biguanides and Thiazolidinediones.
Biguanides:
• Metformin is classified asan insulin sensitizer, it increases glucose
uptake and utilization bytarget tissues. It requires the presenceof
insulin to be effective but does not promoteinsulin secretion. The
risk of hypoglycemia is greatlyreduced.
• Mechanism:
• Inhibits hepatic gluconeogenesis.
• It increases the uptake of glucose by skeletal muscles
• It also reduces hyperlipidemia (↓LDL and VLDL cholesterol and
↑ HDL).
• Metformin also decreases appetite. It is the onlyoral
hypoglycemic shown to reduce cardiovascular mortality. Itcan be
used in combination withother oral agents and insulin.
• Adverse effects: Nausea, mettallic taste, anorexia, vitamin B12
deficieny
Thiazolidinediones
(Glitazones)
• MOA: These agents bind to PPAR-gamma receptor
which is expressed in adipose tissue, skeletal muscle
and liver which controls glucose and lipid metabolism.
• It increases the GLUT-4 glucose transporters in skeletal
muscle and adipose tissue.
• Pioglitazone is given at a dose of 11-45mg dose daily
• Rosiglitazone at a dose of 4-8mg daily
• Adverse effects: edema and fluid retention, deposition
of subcutaneous fat.
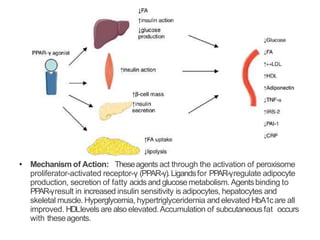
• Mechanism of Action: Theseagents act through the activation of peroxisome
proliferator-activated receptor-γ (PPAR-γ).Ligandsfor PPAR-γregulate adipocyte
production, secretion of fatty acidsand glucosemetabolism. Agentsbinding to
PPAR-γresult in increased insulin sensitivity is adipocytes, hepatocytes and
skeletal muscle. Hyperglycemia, hypertriglyceridemia and elevated HbA1care all
improved. HDLlevels are also elevated.Accumulation of subcutaneous fat occurs
with theseagents.
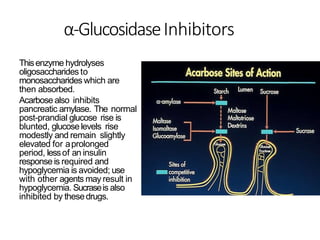
α-GlucosidaseInhibitors
Thisenzyme hydrolyses
oligosaccharides to
monosaccharides which are
then absorbed.
Acarbose also inhibits
pancreatic amylase. The normal
post-prandial glucose rise is
blunted, glucoselevels rise
modestly and remain slightly
elevated for aprolonged
period, lessof an insulin
response is required and
hypoglycemia is avoided; use
with other agents may result in
hypoglycemia. Sucraseis also
inhibited by thesedrugs.
α-GlucosidaseInhibitors
Acarbose and miglitol are two agents of thisclassused
for type 2diabetes.
Mechanism of action:Theseagents are oligosaccharide
derivatives taken at the beginning of ameal delay carbohydrate
digestion by competitively inhibiting α-glucosidase, amembrane
bound enzyme of the intestinal brushborder.
Pharmacokinetics: Acarbose is poorly absorbed remaining in
the intestinal lumen. Migitol is absorbed and excreted by the
kidney. Both agents exert their effect in the intestinal lumen.
Adverse Effects: flatulence, diarrhea, cramping. Metformin
bioavailability is severely decreased when usedconcomitantly.
Theseagents should not be used in diabetics withintestinal
pathology.
IncretinTherapy
•
•
•
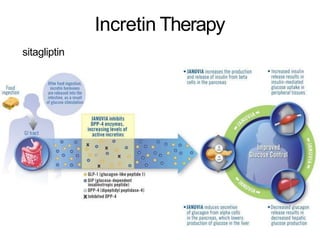
Incretinsare naturally occurringhormonesthat the gutreleases throughoutthe
day the level of activeincretinsincreases significantlywhen foodis ingested.
Endogenousincretinsare
GLP-1(glucagon-likepeptide 1) and
GIP (glucose-dependentinsulinotropicpeptide)
GIPandGLP-1are the 2 major incretin hormonesin humans
Incretin Therapy
sitagliptin
MECHANISMOFACTION:
Theseincretins are released from the gut in response to ingestion
of food and collectively contribute to glucosecontrol by:
• Stimulating glucose-dependent insulin release from
pancreaticbeta cells (GLP-1and GIP):
• Decreasing glucagon production from pancreatic alpha cells
(GLP-1) when glucose levels are elevated.
Thecombination of increased insulin production and decreased
glucagon secretion reduces hepatic glucose production when
plasma glucoseis elevated.
The physiologic activity of incretins is limited by the
enzyme dipeptidyl peptidase-4 (DPP-4), which
rapidly degrades active incretins after their release.
TheIncretin Effect Is Diminished in Type2 Diabetes
Levels of GLP-1 are decreased.
The insulinotropic response to GIP is diminished but
not absent.
Defective GLP-1 release and diminished response to
GIP may be important factors in glycemic
dysregulation in type 2 diabetes.


 Orally active DPP-4 inhibitors used for the treatment of
patients with type 2 diabetes
◦ Sitagliptin - 100mg OD
◦ Vildagliptin -50mg
◦ saxagliptin, linagliptin, alogliptin
Dipeptidyl peptidase 4 Inhibitors:
• Orally active DPP-4 inhibitors used for the
treatment of patients with type 2 diabetes
◦ Sitagliptin - 100mg OD
◦ Vildagliptin -50mg
◦ saxagliptin, linagliptin, alogliptin
Mechanism of action
Inhibit the enzyme DPP-4, which is responsible for the
inactivation of incretin hormones such as GLP-1
Prolonging the activity of incretin hormones results in
increased insulin release in response to meals and
reduction in glucagon secretion
It delays the gastric emptying and supresses appetite.
 DPP-4 inhibitors may be used as monotherapy
or in combination with a sulfonylurea,
metformin, glitazones, or insulin
Adverse effects
 Nasopharyngitis
 Headache
 Pancreatitis has occurred with sitagliptin

Adverse effects
 Nasopharyngitis
 Headache
 Pancreatitis has occurred with sitagliptin
 Dapagliflozin
 Canagliflozin
Mechanism of action:
 SGLT2 is responsible for reabsorbing filtered
glucose in the tubular lumen of the kidney
 By inhibiting SGLT2, these agents decrease
reabsorption of glucose, increase urinary glucose
excretion, and lower blood glucose
 Decreases reabsorption of sodium and causes
osmotic diuresis reducing systolic blood pressure
 Given once daily in the morning
 Canagliflozin should be taken before the first meal
of the day
 Metabolized by glucuronidation to inactive
metabolites
 Should be avoided in patients with renal dysfunction
Adverse effects:
 Female genital mycotic infections urinary tract
infections, and urinary frequency
 Hypotension

Bromocriptine and colesevelam produce modest
reductions in HbA1c
 The mechanism of action of glucose lowering is
unknown
 Indicated for type 2 diabetes
 Modest efficacy, adverse effects limit their use in
clinical practice
 Used as an adjunct to mealtime insulin therapy in
patients with type 1 and type 2 diabetes
 Acts as amylinomimetic, delaying gastric emptying,
decreasing postprandial glucagon secretion, and
improving satiety
 Administered SC and should be injected immediately
prior to meals
 When pramlintide is initiated, the dose of rapid- or
short-acting insulin should be decreased by 50% prior
to meals to avoid a risk of severe hypoglycemia
 Pramlintide may not be mixed in the same syringe with
any insulin preparation
 Adverse effects
◦ Nausea
◦ Anorexia
◦ Vomiting
 Pramlintide should not be given to patients with
diabetic gastroparesis, cresol hypersensitivity, or
hypoglycemic unawareness
Dual PPAR alpha and gamma agents
• Saroglitazar 2-4 mg/day
• Aleglitazar 150-600microgm/d.
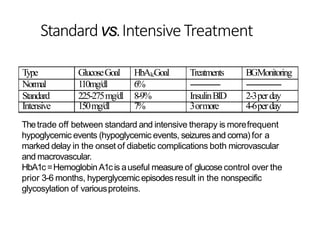
Standardvs.IntensiveTreatment
Type GlucoseGoal HbA1cGoal Treatments BGMonitoring
Normal 110mg/dl 6% ------------ --------------
Standard 225-275mg/dl 8-9% InsulinBID 2-3perday
Intensive 150mg/dl 7% 3ormore 4-6perday
Thetrade off between standard and intensive therapy is morefrequent
hypoglycemic events (hypoglycemic events, seizuresand coma) for a
marked delay in the onset of diabetic complications both microvascular
and macrovascular.
HbA1c=Hemoglobin A1cis auseful measure of glucose control over the
prior 3-6 months, hyperglycemic episodesresult in the nonspecific
glycosylation of variousproteins.

THANK
YOU