Outline
1. Introduction andDevelopmental abnormalities
2. Infections - Bacterial ,Viral, Fungal, Protozoal
3. Circulatory disorders
4. Head injury
5. Spinal Cord Disorders and Spinal injury
6. Peripheral Nervous system
7. Neuromuscular Disorders and Demyelinating Diseases
8. Motor Neurone Disease
9. Metabolic and Degenerative Disorders - Ageing and
Dementia
10.Tumours
3.
Introduction review ofanatomy and physiology
The nervous system is the most complex body
system whose working determines our
personality, intelligence and skills.
It is specialized properties of irritability,
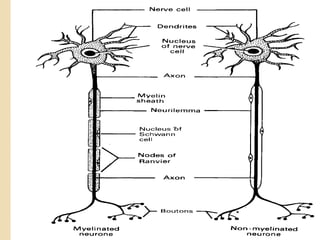
conduction and integration.
Irritability is the ability to receive and respond to
stimuli from internal and external environments.
Information originates in sensory nerve endings
in simple or complex receptors that work as
inputs to the brain.
4.
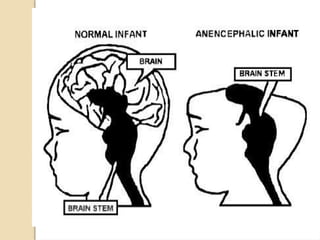
Nerves travellingfrom the brain and
spinal cord to the muscles and glands
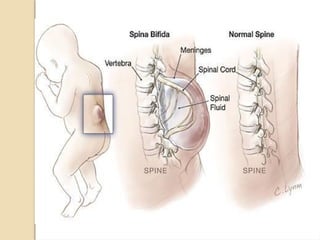
initiate coordinating and regulating
responses in these structures
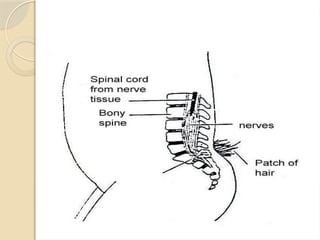
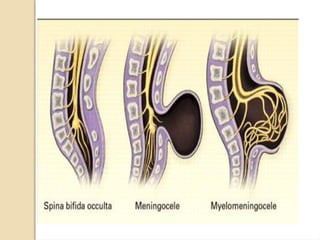
Communication makes possible control;
control makes possible integration;
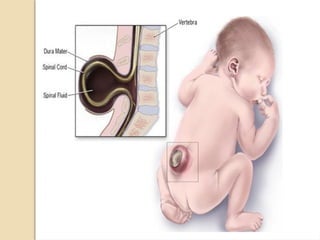
integration makes possible homeostasis,
which makes possible survival.
5.
General Function ofNervous
System
Communication Control
→ →
Integration Homeostasis Survival
→ →
6.
ORGANIZATION OFTHE
NERVOUS SYSTEM
The central nervous system (CNS),
which consists of the brain and
spinal cord, is the structural and
functional centre of the entire
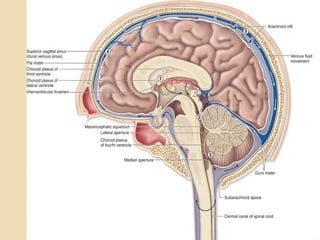
nervous system.
The CNS integrates incoming
information, evaluates the
information and initiates an
outgoing response.
7.
The neuroneis the basic functional unit of
the central nervous system.
There are 100 billion neurones and 10 – 50
times the number of glial cells in the CNS.
There are different types of neurones with
different purposes. The neurones are
arranged in a multitude of differently
organized neural networks determining the
functions of the nervous system
8.
Sensory Division –Sensory
Receptors
Many actions of the nervous system are
initiated by sensory experience emanating
from sensory receptors such as visual
(eyes), auditory (ears) and tactile ones on
the surface of skin.
Information from the sensory receptors can
cause an immediate reaction from the brain
or activate memory of the experience to
determine the body reaction to threats in
the environment.
9.
Motor Division –Effectors
The nervous system controls bodily
functions by controlling contraction
of skeletal muscles and smooth
muscles and in internal organs and
secretion by both exocrine and
endocrine glands
11.
The Meninges
Meningescover the brain tissues and
have CSF circulating freely in the
subarachnoid space over the whole
CNS surface and in the ventricular
system.
The CSF acts as a protective water
bath.
12.
PNS
The peripheralnervous system (PNS) consists of
nerves that lie in the periphery.
Peripheral nerves originating from the brain are
called cranial nerves and those originating from the
spinal cord are called spinal nerves.
Both cranial and spinal nerves consist of fibres that
form incoming and outgoing information pathways.
The PNS has two main subdivisions called the
sensory (afferent) nervous system that consists of
incoming sensory or afferent pathways and the
motor (efferent) nervous system that has all
outgoing or efferent pathways
13.
The motornervous system is further
subdivided into somatic nervous system,
which carry information to the somatic
effectors (skeletal muscles) and the autonomic
nervous system (ANS) that carry information
to the autonomic or visceral effectors
(smooth muscles, cardiac muscle and glands).
The autonomic nervous is autonomous of the
voluntary control hence it governs itself
without our conscious knowledge
14.
The ANSis divided into sympathetic nervous system
and parasympathetic nervous system.
The sympathetic nervous system has pathways that
leave the spinal cords at the middle portion are
involved in preparing the body to deal with
immediate threats to the internal environment by
providing the “fight-or-flight” response.
The parasympathetic pathways exit at the brain or
lower portions of the spinal cord and they
coordinate the body’s normal resting activities. It is
the “rest-and-repair” division of the nervous system.
15.
CELLS OFTHE NERVOUS
SYSTEM
Made up of two types of cells namely
the neurones and neuroglia (glial
cells).
Neurones are excitable cells that
conduct impulses making the
nervous system functions possible as
they make up the wiring of the
body’s information circuit.
16.
Neuroglia orglial cells are cells that offer
support functions and thy do not conduct
impulses.
Nerve cells operate by generating electric
signals that pass from one part of the cell
to another part of the same cell by
releasing chemical messengers called
neurotransmitters facilitating
communication between cells.
18.
Neurones arespecialized cells that respond to
chemical and physical stimuli, conduct
electrochemical impulses and release chemical
regulators that are specific in function.
These characteristics enable the neurones
perform functions such as perception of stimuli,
learning, memory and control of muscle in glands.
The neurone has three principal parts namely the
cell body (soma, perikaryo), dendrites (processes)
and axon (nerve fibre).
19.
Glial cellsare the cells that support the
neurones physically and metabolically and form
the bulk of the cells in the CNS accounting for
80 – 90%.
They are 50 – 60 times more than the
neurones. Neurones branch more extensively
than the glial cells and occupy 50% of the
volume of the brain and spinal cord.
The neuroglia include: - astroglia (astrocytes),
oligodendroglia (oligodendrocytes), microglia,
Schwann cells, ependyma and satellite cells.
20.
Causes of NeuroneDamage
1.Anoxia and hypoxia(ischaemia)
2. Hypoglycaemia
3. Infections
4.Trauma
5. Intramuscular metabolic disturbances e.g.
vitamin B12 deficiencies
EFFECTS OF NEURONAL
DAMAGE
The two main types of neuronal damage depending on the
rapidity of the changes include rapid necrosis (associated
with acute failure of function) and slow atrophic changes
(associated with gradual loss of function).
The process of aging is associated with cumulative atrophy
and disappearance of neurones. In some persons the
process is accentuated resulting in presenile dementia.
Neuronal damage results in primary degeneration
(necrosis and atrophy) and secondary degeneration in
some situations where axon damage involves degeneration
of the neurone as well.
23.
Chromosomal Abnormalities
Importantchromosomal abnormalities include those
where there is extra chromosomal material e.g.
Trisomy 13, 18 and 21 which are associated with
mental retardation.
Sex chromosomes’ disorders such as Kleinfelter’s
syndrome (XXY) and Turner’s syndrome (XO) are also
associated with mental retardation.
Down’s syndrome is a trisomy 21 disorder that occurs
due to non-disjunction during meiosis in one of the
parents. It is the most common chromosomal disorder
and it is the commonest cause of mental retardation.
The brain is usually small
24.
NeuralTube Defects
Defectsof the neural tube occur due to
damage during the 4th week of foetal
development as a result of genetic and
environmental factors.
The defects can be diagnosed pre-natally
by presence of increased feto proteins
level in blood and increased amniotic fluid
on ultra sound scan.
25.
1.Anencephaly
Anencephaly affectsmore females than males in
the ratio of 3:1.
The head is retroflexed and appears to sit on
the shoulders with the cranial vault missing and
a flattened base of the skull.
The brain is represented by disorganized mass
of glia, malformed brain and choroid plexus.The
area cerebrovaseulosa that sits on the base of
the skull is covered by a thin smooth membrane.
It results form failure of neural tube closure.
27.
2. Spinal Bifida
Defects of the spinal cord resulting from failure of
fusion (incomplete closure) of neural arches are
called spina bifida.
Spina bifida are malformations of the vertebral
column involving incomplete embryologic closure
of one or more of the vertebral arches
(rachiochisis).
The vertebral defect is associated with defect in
the neural tube structures and their coverings.
Majority of these malformations occur in the
lumbosacral region
29.
Spina Bifida Occulta
In spina bifida occulta there is only vertebral bone
defect with no abnormality of the spinal cord and its
meninges.
It is seen in 175 of normal adults where it appears as
absence of one or more spinous processes
radiologically.
It is limited to the lumbosacral region.The site of the
bone defect is marked by a small dimple covered by
skin which may show abnormal pigmentation (mole), a
hairy patch or a dermal sinus. In majority of the cases
spina bifida occulta is asymptomatic but neurological
disturbances may develop in adult life.
31.
Spina Bifida Cystica
In spina bifida cystica, the vertebral bony defect is large
and the spinal cord and its meninges appear as a
distinct cystic swelling over the affected site as revealed
through the skin defect.
The defect in the skin allows herniation of the
meninges or the spinal cord or both.
Herniation of the meninges alone through the bony
defect results in formation of a meningocele which is
less common (10 – 20%) and involves only meninges,
vertebral arches and the skin. the herniation sac
consists of the dura and arachnoid.
The spinal cord is virtually normal
33.
3. Myelomeningocele
Myelomeningoceleis the commonest (80 – 90) is a
more serious condition that involves herniation of
meninges and the abnormal spinal cord or its roots
through the defect and is attached to the posterior
wall of the sac.
The dura and the skin in the sac are deficient. Other
abnormalities associated with this malformation are
syringomyelia (myelocele) or diastematomyelia.
In syringomyelia there is defective closure of the
spinal canal so that the sac consists of an open flat
neural tissue plate without skin covering and the
cerebral spinal fluid (CSF) leaks through it.
34.
Myelomeningocele andmyelocele are
associated with poor quality of life due to
varying degrees of neurological defects
The sequelae include bladder and bowel
dysfunction (incontinence), motor and
sensory defects (flaccid areflexic
weakness of the legs), paraplegia, lumbar
kyphosis and moderate-to-severe mental
retardation
36.
Herniation ofbrain tissue and meninges
through a midline defect in the cranial
cavity in the region of the occipital bone
or fronto-ethmoid junction may result in
encephalocele and cranial meningocele.
It affects more females than males.At the
occipital region the encephalocele
protrudes through either the foramen
magnum or squamous occipital bone.
37.
4: Syringomyelia andSyringobulbia
A syrinx is a fluid filled cavity in the cord
(syringomyelia) or brain stem (syringobulbia).
The cavity may be fusiform or irregular. It begins with
grey matter of spinal cord dorsal to the central canal.
The syrinx is surrounded by glial tissue. The cavity
may communicate with spinal canal and is lined with
ependymal cells.
Fibres of lateral spinothalamic tract and involvement
in the cavity result in clinical effects such as loss of
pain and temperature sensation in the affected region
38.
They arecaused by trauma, ischaemia and
tumours and cause compression of the
white matter tracts resulting in neurological
disability.
The clinical features are due to compression
of spinal nerve tracts resulting in wasting of
intrinsic muscles of the hands, spastic
weakness in the legs, loss of pain and
temperature sensation but with
preservation of touch
39.
Malformations of theCerebellum
1.Arnold-Chiari Malformations
These are malformations of the brain
involving the brain stem, cerebellum and
base of skull as described by Arnold-
Chiari.
The primary problem is elongation of the
medulla and part of the vermis of the
cerebellum resulting from failure of
pontine flexture to form.
40.
In theArnold-Chiari malformation, there
is an abnormality of the hind brain and
cerebellum associated with a lumbar
myelomeningocele and hydrocephalus.
The major components of the Arnold-
Chiari malformation include
41.
1. Caudaldisplacement and distortion of
the medulla which appears narrow, S-
shaped and elongated with much of it
lying below the level of the foramen
magnum.The displacement includes part
of the 4th ventricle
42.
2. Displacementof vermis of the
cerebellum through the foramen magnum
into the upper portion of the spinal cord.
There is lengthening and herniation of
cerebellum vermis and cerebellar tonsils
through the foramen magnum resulting in
formation of a mass over the upper
cervical cord
43.
Malformations of WholeBrain
1. Microcephaly
Microcephaly is a condition with the brain
weighing less than 1000 gm in adults or less
than 2 standard deviation mean normal weight
for age and sex. It results from degeneration,
destructive or congenital conditions. Causes
include - Congenital infections – Rubella,
Toxoplasmosis, Cytomegalovirus;Toxins,
Irradiation, Metabolic disorders and
chromosomal abnormality
44.
2. Megalencephaly
Thebrain weighs more than 1700 gm or
more or more than 2.5 standard
deviation of mean normal for age and sex.
It may be primary or secondary.
Secondary megalencephaly is due to
metabolic disorders
45.
Hydrocephalus
Hydrocephalus meansincreased volume of
cerebrospinal fluid (CSF) within the cranial cavity
accompanied by dilatation of the ventricles.
In internal hydrocephalus the increased
volume of CSF is within the ventricular
system which becomes enlarged (dilated).
Internal hydrocephalus is associated with
increased intracranial pressure. In external
hydrocephalus, excess CSF collects in the
subarachnoid space.
46.
If theCSF can flow freely from the
ventricular system to the subarachnoid
space, this is described as communicating
hydrocephalus and if it does not circulate
then it is called non-communicating
hydrocephalus.
Compensatory hydrocephalus (ex vacuo)
occurs when the increased volume of CSF
is compensatory to loss of brain tissue
47.
Cerebrospinal Fluid (CSF)– Source
and Circulation
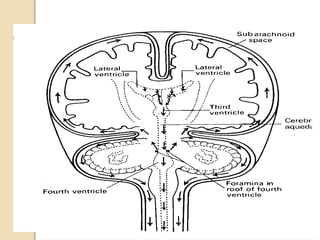
The total volume of CSF produced is 120 –
150 mls.
It is mainly produced by choroid plexus in the
two lateral, 3rd and 4th ventricles and a small
portion is formed on the surface of the brain
and spinal cord.
The CSF formed in the lateral ventricles
flows through the foramina of Munro to the
3rd ventricle and from here it flows through
the aqueduct of Sylvias to the 4th ventricle.
48.
The CSFthen passes through the
foramina of Magendi and Luschka of the
4th ventricle to reach the subarachnoid
space of the brain and spreads through
the subarachnoid space over the surface
of the spinal cord.
The CSF is then absorbed into the blood
by the arachnoid villi present along the
dural venous sinuses.
50.
Mechanisms of Hydrocephalus
In hydrocephalus, the volume of CNS is
increased and the ventricles are dilated.
In majority of the cases there is an increase in
intracranial pressure. There are three main
mechanisms responsible for development of
hydrocephalus namely:
1. Overproduction of CSF
2. Obstruction of the flow of CSF
(commonest)
3. Defective or deficient reabsorption
51.
Overproduction of CSF
The choroids plexus secretes more CSF
to compensate for any external leak, but
overproduction is not a cause of
hydrocephalus
52.
Obstruction of theflow of CSF
The sites particularly vulnerable to
obstruction are the aqueduct of Sylvius,
foramina of Magendi and Luschka and the
subarachnoid space between the midbrain
and forebrain (interposition of tentorium
cerebelli).
53.
Defective reabsorption
NormallyCSF is absorbed into venous
sinus via the arachnoid granulation.
Existence of pathology such as scarring
following inflammation, haemorrhage
obliterates the absorption sites reducing
their absorption capacity.
Primary Hydrocephalus
Thecommonest mechanism is obstruction to the
flow of CSF hence the term obstructive
hydrocephalus
The terms non-communicating and
communicating hydrocephalus are used to
denote the site of obstruction.
The site of obstruction is more important than
the nature or size of obstruction e.g. a small
lesion in a critical site adjacent to an
interventricular foramen of Munro or the
aqueduct in the midbrain produces
hydrocephalus rapidly.
56.
Non-communicating
Hydrocephalus
The siteof obstruction of CSF flow pathway is in
the 3rd ventricle or at the exit foramen in the
4th ventricle.
The ventricular system enlarges and CSF cannot
pass into the subarachnoid space. Obstruction of
CSF at the foramen of Munro results in
enlargement of one lateral ventricle while that at
the 3rd ventricle or the aqueduct results in
enlargement of both ventricles. Obstruction at
the exit of the 4th ventricle results in
enlargement of the entire ventricular system.
2.Acquired non-communicating hydrocephalus
Occurs from an expanding lesion within the cranial
cavity: -
a) Tumours adjacent to the ventricular system e.g.
ependyoma, choroid plexus papilloma and
medulloblastoma
b) Inflammatory lesions e.g. cerebral abscess and
meningitis
c) Haemorrhage – parencymal haemorrhage,
intraventricular haemorrhage, epidural haematoma
and subdural haematoma
59.
Communicating Hydrocephalus
Obstructionto CSF flow is in the
subarachnoid space at the base of the
brain and results in enlargement of the
entire ventricular system but CSF flows
freely between dilated ventricles and the
spinal cord and that is why it is called
communicating hydrocephalus.
The causes of communicating
hydrocephalus are non-obstructive
60.
Causes
1. Overproduction ofCSF – choroid plexus
papilloma
2. Deficient reabsorption of CSF – post
meningitis, dural sinus thrombosis and
sequelae of subarachnoid haemorrhage
(the arachnoid granulations may be partly
obliterated by macrophages containing
haemosiderin).
61.
Secondary Hydrocephalus
Secondaryhydrocephalus is less common
and is defined as compensatory increase
in CSF due to loss of neural tissue
without increase in intracranial pressure
e.g. flowing cerebral atrophy and
infarction.
This is also called hydrocephalus ex
vacuo.
62.
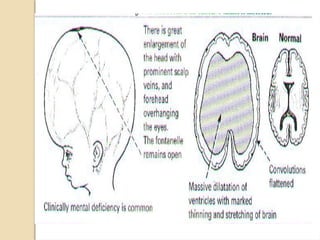
Pathologic Changes
Gross
Ventriculardilatation
Thinning and stretching of the brain
Engorged scalp veins overlying the enlarged head
Open fontanelles
Microscopy
Damage to ependymal lining of the ventricles
Periventricular interstitial oedema
63.
CLINICAL FEATURES
Infants
Acceleratedenlargement of the head
Anterior fontanelle –wide open and bulging
Scalp vein are dilated
Broad forehead
Eyes may deviate downwards (sunset eyes sign)
Long tract signs – brisk tendon reflexes,
spasticity and clonus (especially of the lower
extremities)
64.
Older children
Cranialsutures partially closed
Skull percussion – “cracked pot” –
Macewen sign – indicates separation
of sutures