






















































Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 1
DIALYSIS UNIT
EXCELLENCE MANUAL
Global Standards for Renal Replacement Therapy Excellence, Patient Safety, and Quality
Healthcare
A Comprehensive Reference for
THE MULTIDISCIPLINARY DIALYSIS CARE TEAM
Nephrologists • Dialysis Nurses & Technicians • Vascular Access Teams • Renal Dietitians & Allied Dialysis Care
Professionals
“Three Times a Week, for Years, We Become the Kidneys That No Longer Work — Every
Access Protected, Every Session Precise, Every Patient's Life Sustained.”
Dr J L Meena
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 2
DEDICATION
This book is dedicated to all those who are committed to advancing healthcare through the quiet, relentless
precision of a therapy that must be delivered correctly not once, but three times a week, for years, sometimes
for an entire lifetime.
To Every Dialysis Patient
For whom every needle placed correctly, every session's fluid removal calculated precisely, and every vascular
access protected from infection represents not a single treatment but a sustained, lifelong partnership with a
team that stands between them and the kidney function they have lost.
To Every Family Supporting a Dialysis Patient
For whom this therapy becomes a permanent rhythm of family life, and who deserve a team that treats their
loved one's long journey with the same rigour on the thousandth session as on the first.
To My Family
For their unwavering love, patience, and encouragement, which have been the foundation of this journey.
To My Mentors & Teachers
For inspiring my passion, guiding my path, and instilling in me the understanding that dialysis is not an
emergency intervention but a sustained discipline, where consistency across years matters as much as
precision within any single session.
To My Colleagues & Friends
For their support, collaboration, and shared dedication to a unit where the same exacting standard is applied
to session one thousand and one as it was to session one.
To Every Member of the Dialysis Unit Team
Nephrologists, dialysis nurses and technicians, vascular access specialists, and every professional who has
cannulated a fistula with the same care on a Tuesday afternoon as they would in the most watched procedure
in the hospital — the guardians of a therapy that never gets to rest.
Your vigilance, your technical precision, and your sustained commitment across years of repeated sessions
are the silent pillars of a healthcare system that gives every patient with kidney failure the fullest possible
chance at a full life. This book is for you, and because of you. Thank you to everyone who has been a part
of this journey.
Dr J L Meena
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 3
FOREWORD
There is a category of clinical excellence that is tested not by a single dramatic crisis, but by relentless
repetition: the same vascular access cannulated correctly, session after session, for years. The same precise
calculation of fluid removal, balanced against a heart that may not tolerate too much or too little. The same
rigorous infection control applied to a needle stick and a blood circuit exposed to bacteria, exactly as carefully
on the thousandth session as on the first. Dialysis is not typically an emergency — it is a sustained, lifelong
discipline, and it is precisely this sustained nature that makes excellence in the Dialysis Unit so demanding:
complacency is the genuine enemy, not crisis, and the team's challenge is to bring the same exacting standard
to routine that any other unit brings only to emergency.
The “Dialysis Unit Excellence Manual: Global Standards for Renal Replacement Therapy Excellence, Patient
Safety, and Quality Healthcare” has been developed to provide a comprehensive professional framework for
the multidisciplinary Dialysis Unit team — nephrologists, dialysis nurses and technicians, vascular access
specialists, renal dietitians, and allied dialysis care professionals — working together to sustain the therapy
that has, quite literally, replaced the function of a failed organ for patients who depend on it for the rest of
their lives.
This manual brings together internationally recognized principles of vascular access care and cannulation
technique, dialysis adequacy monitoring, fluid and dry weight management, bloodborne pathogen infection
control, intradialytic complication recognition and response, water treatment quality assurance,
anticoagulation management during dialysis, and continuous quality improvement specific to renal
replacement therapy. It is built around globally accepted accreditation frameworks — WHO and KDIGO/KDOQI
clinical practice guidelines, NABH, JCI, and CMS Conditions for Coverage for End-Stage Renal Disease facilities
— to provide a rigorous, regulation-compliant framework for Dialysis Unit excellence.
The chapters of this manual guide the Dialysis Unit team through every dimension of the role — from vascular
access assessment and cannulation, through dialysis session monitoring and complication management, to
infection control, water treatment quality, and the professional conduct that defines excellence across every
category of renal replacement therapy: hemodialysis, peritoneal dialysis, and every patient whose survival
depends on this therapy being delivered correctly, without exception, for as long as their kidneys do not
recover.
The Dialysis Unit is not simply a treatment room where a machine filters blood — it is a distinct discipline built
on the understanding that a therapy delivered repeatedly, for years, demands protection against the
complacency that repetition can breed, that a vascular access is a patient's lifeline requiring the same sterile
discipline every single time it is accessed, and that the water used to prepare dialysate must meet purity
standards as rigorous as any pharmaceutical product, because it will enter a patient's bloodstream directly,
multiple times a week, for years. Their work is defined by a sustained vigilance that must never lapse into
routine, because for this therapy, routine is exactly where preventable harm begins.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 4
It is hoped that this manual will serve as an indispensable resource for Nephrologists, Dialysis Nurses and
Technicians, Vascular Access Teams, Renal Dietitians, hospital administrators, quality heads, and all those
committed to building a healthcare system where renal replacement therapy is delivered with the precision,
consistency, and compassion that a lifelong, repeated therapy demands.
“Three Times a Week, for Years, We Become the Kidneys That No Longer Work — Every Access
Protected, Every Session Precise, Every Patient's Life Sustained.”
With Best Wishes, Dr J L Meena
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 5
TABLE OF CONTENTS
FOREWORD............................................................................................................................................3
LIST OF ABBREVIATIONS........................................................................................................................7
MANUAL MOTTO...................................................................................................................................9
CHAPTER 1: Introduction.....................................................................................................................10
Purpose...........................................................................................................................................................10
Objectives .......................................................................................................................................................11
Vision & Mission .............................................................................................................................................13
CHAPTER 2: Role of the Dialysis Unit Team in Quality Healthcare ....................................................14
Vascular Access Assessment & Cannulation...................................................................................................14
Dialysis Adequacy & Prescription Management.............................................................................................14
Fluid & Dry Weight Management...................................................................................................................15
Bloodborne Pathogen Infection Control.........................................................................................................15
Water Treatment & Dialysate Quality ............................................................................................................16
Intradialytic Complication Management ........................................................................................................16
Anticoagulation During Dialysis ......................................................................................................................16
CKD-MBD, Anemia & Nutrition Management ................................................................................................17
CHAPTER 3: Professional Standards for the Dialysis Unit Team ........................................................17
Professional Appearance & Behaviour ...........................................................................................................17
Communication Standards .............................................................................................................................18
Confidentiality & Information Security...........................................................................................................19
Ethical Standards ............................................................................................................................................19
Time Management, Teamwork & Continuous Learning.................................................................................20
CHAPTER 4: Patient-Centered Communication in the Dialysis Unit...................................................21
The A-T-C-R-C Communication Model............................................................................................................21
Communicating with Patients on Lifelong Therapy........................................................................................22
CHAPTER 5: Patient Safety and Renal Replacement Therapy Standards...........................................24
The R-T-A-C-A Framework ..............................................................................................................................24
Daily Quality Standards Checklist ...................................................................................................................26
CHAPTER 6: Confidentiality, Privacy, and Information Security ........................................................27
Privacy in the Shared Dialysis Bay Environment.............................................................................................27
Cybersecurity of Dialysis Information Systems...............................................................................................28
CHAPTER 7: Standard Operating Procedures (SOPs)..........................................................................29
SOP 1: Pre-Dialysis Assessment and Machine Setup ......................................................................................29
SOP 2: Vascular Access Cannulation Technique .............................................................................................29
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 6
SOP 3: Intradialytic Monitoring and Documentation......................................................................................30
SOP 4: Hypotension and Intradialytic Complication Response.......................................................................30
SOP 5: Anticoagulation Management (Heparin Protocol) ..............................................................................31
SOP 6: Bloodborne Pathogen Precautions and Isolation................................................................................31
SOP 7: Water Treatment and Dialysate Quality Testing.................................................................................32
SOP 8: Dialyzer Reprocessing/Reuse (Where Applicable) ..............................................................................32
SOP 9: Needle-Stick and Bloodborne Exposure Response..............................................................................33
SOP 10: Vascular Access Complication and Emergency Response .................................................................33
CHAPTER 8: Communication with Special Groups..............................................................................34
CHAPTER 9: Handling Difficult Situations ...........................................................................................37
CHAPTER 10: Emergency Response — Critical Dialysis Presentations...............................................40
CHAPTER 11: Digital Competency for the Dialysis Unit......................................................................43
CHAPTER 12: Daily Dialysis Unit Checklist ..........................................................................................45
CHAPTER 13: Key Performance Indicators (KPIs)................................................................................47
CHAPTER 14: Top 20 Do's & Top 20 Don'ts.........................................................................................49
CHAPTER 15: Dialysis Unit Professional Pledge..................................................................................52
CONCLUSION........................................................................................................................................55
REFERENCES.........................................................................................................................................57
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 7
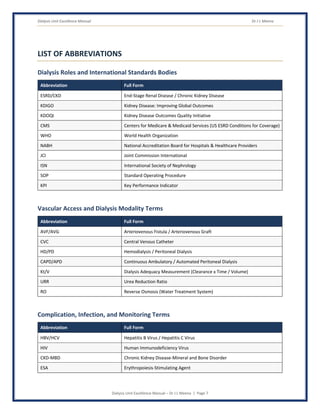
LIST OF ABBREVIATIONS
Dialysis Roles and International Standards Bodies
Abbreviation Full Form
ESRD/CKD End-Stage Renal Disease / Chronic Kidney Disease
KDIGO Kidney Disease: Improving Global Outcomes
KDOQI Kidney Disease Outcomes Quality Initiative
CMS Centers for Medicare & Medicaid Services (US ESRD Conditions for Coverage)
WHO World Health Organization
NABH National Accreditation Board for Hospitals & Healthcare Providers
JCI Joint Commission International
ISN International Society of Nephrology
SOP Standard Operating Procedure
KPI Key Performance Indicator
Vascular Access and Dialysis Modality Terms
Abbreviation Full Form
AVF/AVG Arteriovenous Fistula / Arteriovenous Graft
CVC Central Venous Catheter
HD/PD Hemodialysis / Peritoneal Dialysis
CAPD/APD Continuous Ambulatory / Automated Peritoneal Dialysis
Kt/V Dialysis Adequacy Measurement (Clearance x Time / Volume)
URR Urea Reduction Ratio
RO Reverse Osmosis (Water Treatment System)
Complication, Infection, and Monitoring Terms
Abbreviation Full Form
HBV/HCV Hepatitis B Virus / Hepatitis C Virus
HIV Human Immunodeficiency Virus
CKD-MBD Chronic Kidney Disease-Mineral and Bone Disorder
ESA Erythropoiesis-Stimulating Agent
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 8
Abbreviation Full Form
PTH Parathyroid Hormone
DDS Dialysis Disequilibrium Syndrome
BFR/QB Blood Flow Rate
Governance and Documentation Terms
Abbreviation Full Form
SBAR Situation, Background, Assessment, Recommendation
RCA Root Cause Analysis
CAPA Corrective and Preventive Action
EMR/HIS Electronic Medical Record / Hospital Information System
MLC Medico-Legal Case
Recommended Note for Manual
The abbreviations in this manual assist Nephrologists, Dialysis Nurses and Technicians, Vascular Access Teams,
Renal Dietitians, hospital administrators, quality professionals, and all healthcare staff in understanding
commonly used terms related to renal replacement therapy, vascular access, and dialysis quality standards.
Quick Reference – Most Frequently Used Abbreviations
● AVF/AVG/CVC – Vascular Access Types
● HD/PD – Hemodialysis / Peritoneal Dialysis
● Kt/V, URR – Dialysis Adequacy Measures
● HBV/HCV/HIV – Bloodborne Pathogens Requiring Precaution
● CKD-MBD – Chronic Kidney Disease-Mineral and Bone Disorder
● ESA – Erythropoiesis-Stimulating Agent
● DDS – Dialysis Disequilibrium Syndrome
● RO – Reverse Osmosis Water Treatment
● SOP – Standard Operating Procedure
● KPI – Key Performance Indicator
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 9
MANUAL MOTTO
“Three Times a Week, for Years,”
“We Become the Kidneys That No Longer Work —”
“Every Access Protected, Every Session Precise.”
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 10
CHAPTER 1: INTRODUCTION
1. Purpose
Dialysis is unlike almost every other therapy in medicine in one defining respect: it is not delivered once, in a
single decisive intervention, but repeated — three or more times a week, for years, sometimes for an entire
remaining lifetime. This repetition is precisely what makes excellence in the Dialysis Unit so demanding and so
easily eroded: the vascular access cannulated correctly nine hundred times can still be damaged by a single
careless insertion on the nine hundred and first. The water used to prepare dialysate, tested and passed for
months, can still transmit harm the one time a contamination is missed. The team's genuine challenge is not
merely technical competence, but sustained vigilance — bringing the same rigorous discipline to a routine
Tuesday afternoon session as to the most watched procedure in the hospital, because for a therapy delivered
this many times, routine is exactly where preventable harm begins.
The World Health Organization and the International Society of Nephrology, alongside KDIGO and KDOQI
clinical practice guidelines, recognize that structured vascular access care, rigorous dialysis adequacy
monitoring, and disciplined infection control are directly and measurably linked to reductions in dialysis-related
mortality and morbidity. Research consistently demonstrates that dialysis facilities applying rigorous
cannulation technique, systematic water treatment quality assurance, and disciplined bloodborne pathogen
precautions achieve dramatically and measurably better patient outcomes and access longevity than facilities
relying on inconsistent or complacent practice. In institutions where the Dialysis Unit team applies systematic
vascular access protection, precise fluid management, and rigorous infection control sustained across every
single session, patient survival and quality of life are demonstrably and measurably better. The investment in
Dialysis Unit excellence is, without qualification, one of the highest-yield investments any healthcare system
can make — protecting not a single crisis, but years, and often decades, of sustained life for patients whose
kidneys no longer function.
Why the Dialysis Unit Team Is Critical to Healthcare Quality
● Provides the sustained renal replacement therapy that directly substitutes for lost kidney function,
delivered repeatedly across years.
● Protects vascular access — the patient's literal lifeline — through meticulous cannulation technique
sustained across hundreds of sessions.
● Applies rigorous dialysis adequacy monitoring that ensures each session genuinely removes the toxins
and fluid the patient's failed kidneys cannot.
● Maintains disciplined bloodborne pathogen infection control in an environment where blood exposure
is inherent to every session.
● Ensures water treatment and dialysate quality meets pharmaceutical-grade purity standards, given
direct bloodstream exposure multiple times weekly.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 11
● Recognizes and responds to intradialytic complications (hypotension, cramps, arrhythmia) that can
occur during any session.
● Manages the long-term complications of kidney failure — CKD-mineral bone disorder, anemia,
malnutrition — that shape quality of life across years of therapy.
● Maintains regulatory compliance with national dialysis facility standards and international
accreditation guidelines.
● Contributes to accreditation compliance (NABH, JCI, CMS Conditions for Coverage) for dialysis facility
standards.
Key Responsibilities of the Dialysis Unit Team
● Conducting systematic pre-dialysis assessment and vascular access evaluation for every session.
● Applying meticulous aseptic cannulation technique for every vascular access, every time.
● Monitoring dialysis adequacy (Kt/V, URR) and adjusting prescription to meet evidence-based targets.
● Calculating and managing fluid removal precisely, balancing dry weight targets against haemodynamic
tolerance.
● Applying rigorous bloodborne pathogen precautions and isolation protocols for hepatitis B, hepatitis
C, and HIV-positive patients.
● Maintaining water treatment system quality assurance and dialysate testing per regulatory schedule.
● Recognizing and responding immediately to intradialytic complications.
● Managing anticoagulation during dialysis to prevent circuit clotting while minimizing bleeding risk.
● Coordinating CKD-MBD, anemia, and nutritional management across the long-term course of therapy.
● Engaging in continuous professional development to maintain competence in evolving renal
replacement therapy evidence.
2. Objectives
1. Protect Vascular Access as the Patient's Lifeline
Every vascular access must be assessed, cannulated, and cared for with meticulous, sustained precision,
recognizing that access failure directly threatens the patient's ability to receive life-sustaining therapy. This is
the Dialysis Unit's primary patient safety obligation.
How to Achieve:
● Apply systematic vascular access assessment before every cannulation.
● Apply meticulous aseptic cannulation technique consistently, without exception, regardless of how
routine the session feels.
● Rotate cannulation sites appropriately to preserve long-term access integrity.
2. Ensure Every Session Achieves Adequate Dialysis
● Monitor dialysis adequacy (Kt/V, URR) systematically per defined schedule.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 12
● Adjust dialysis prescription based on adequacy monitoring and clinical status.
● Calculate and manage fluid removal precisely against dry weight targets.
3. Maintain Disciplined Infection Control
● Apply standard precautions and bloodborne pathogen protocols rigorously for every patient, every
session.
● Apply appropriate isolation protocols for hepatitis B, hepatitis C, and HIV-positive patients per
institutional and regulatory policy.
● Maintain rigorous hand hygiene and aseptic technique throughout every session.
4. Ensure Water Treatment and Dialysate Quality
● Maintain water treatment system quality assurance per regulatory testing schedule.
● Test dialysate quality systematically and respond immediately to any deviation.
5. Recognize and Respond to Intradialytic Complications Promptly
● Monitor haemodynamic status continuously throughout every session.
● Apply standardized response protocols for hypotension, cramps, and other complications.
● Maintain rehearsed emergency response readiness for cardiac arrest or severe complication during
dialysis.
6. Maintain Regulatory and Accreditation Compliance
● Comply with national dialysis facility standards and international accreditation guidelines.
● Maintain NABH/JCI and, where applicable, CMS Conditions for Coverage documentation standards.
● Participate in accreditation surveys with complete, auditable dialysis care records.
3. Vision
Vision Statement
“To build and maintain a Dialysis Unit where every vascular access is protected with meticulous, sustained
precision, every session achieves genuine dialysis adequacy, water treatment and infection control never lapse
into complacency, and no patient is ever harmed by a preventable access failure, dosing error, or infection
transmission across the entire course of their lifelong therapy.”
4. Mission
Mission Statement
“To deliver safe, precise, evidence-based, and sustained renal replacement therapy that protects patients from
harm through meticulous vascular access care, rigorous infection control, and disciplined dialysis adequacy
monitoring, while maintaining regulatory compliance and enabling the healthcare organization to provide
quality dialysis care with the same exacting standard on the thousandth session as on the first.”
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 13
Expected Outcomes of an Excellent Dialysis Unit Practice
● 100% of cannulations performed using meticulous aseptic technique with documented site
assessment.
● Dialysis adequacy (Kt/V/URR) monitored per defined schedule and meeting evidence-based targets for
100% of patients.
● Water treatment and dialysate quality testing completed per regulatory schedule with 100%
compliance.
● Bloodborne pathogen precautions and isolation protocols applied consistently for 100% of applicable
patients.
● Vascular access complication and infection rates maintained at or below institutional/national
benchmark.
● Complete, accurate, and NABH/JCI/CMS-compliant dialysis care documentation.
● All significant dialysis-related adverse events reviewed with documented RCA and CAPA.
● Full compliance with national dialysis facility standards and international accreditation guidelines.
The Dialysis Unit team sustains a therapy that must be delivered correctly not once, but across years of
repeated sessions — their vascular access precision protects a patient's literal lifeline, their infection
control discipline never lapses into the complacency that repetition can breed, and their sustained vigilance
across the thousandth session, as much as the first, is what gives every dialysis patient the fullest possible
chance at a full life.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 14
CHAPTER 2: ROLE OF THE DIALYSIS UNIT TEAM IN QUALITY
HEALTHCARE
1. Vascular Access Assessment and Cannulation
Overview
The vascular access — arteriovenous fistula, graft, or central venous catheter — is often described as a dialysis
patient's lifeline, and its protection through meticulous, sustained cannulation technique is the single most
consequential daily responsibility of the Dialysis Unit.
Responsibilities
● Apply systematic vascular access assessment (inspection, palpation, auscultation for bruit/thrill)
before every cannulation.
● Apply meticulous aseptic cannulation technique consistently, without exception, regardless of session
routine.
● Rotate cannulation sites using rope-ladder or buttonhole technique per protocol to preserve long-
term access integrity.
● Recognize and escalate signs of access complication (infection, stenosis, thrombosis) promptly.
2. Dialysis Adequacy and Prescription Management
Overview
Dialysis adequacy monitoring ensures that each session genuinely achieves the toxin and fluid removal a
patient's failed kidneys can no longer provide — an under-dialyzed patient faces measurably worse long-term
outcomes.
Responsibilities
● Monitor dialysis adequacy (Kt/V, URR) systematically per defined schedule.
● Adjust dialysis prescription (duration, blood flow rate, dialysate flow rate) based on adequacy
monitoring and clinical status.
● Coordinate with the nephrologist for prescription changes based on evolving clinical need.
3. Fluid and Dry Weight Management
Overview
Precise fluid removal calculation, balanced against a patient's individualized dry weight target, is essential to
prevent both the complications of fluid overload and the haemodynamic instability of excessive removal.
Responsibilities
● Assess and reassess dry weight targets systematically based on clinical status.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 15
● Calculate fluid removal precisely for each session based on interdialytic weight gain and dry weight
target.
● Monitor for signs of both under- and over-correction throughout the session.
4. Bloodborne Pathogen Infection Control
Overview
The Dialysis Unit environment involves inherent blood exposure at every session, making disciplined
bloodborne pathogen infection control a continuous, non-negotiable clinical function.
Responsibilities
● Apply standard precautions rigorously for every patient, every session, without exception.
● Apply appropriate isolation protocols (dedicated machines, separate stations) for hepatitis B, hepatitis
C, and HIV-positive patients per institutional and regulatory policy.
● Apply rigorous hand hygiene and glove changes between every patient contact.
5. Water Treatment and Dialysate Quality
Overview
Water used to prepare dialysate must meet purity standards as rigorous as pharmaceutical products, given
that it enters a patient's bloodstream directly, multiple times weekly, for years.
Responsibilities
● Maintain water treatment (reverse osmosis) system quality assurance per regulatory testing schedule.
● Test dialysate chemical and microbiological quality systematically.
● Respond immediately to any water or dialysate quality deviation, halting affected treatment as
required.
6. Intradialytic Complication Management
Overview
Intradialytic hypotension, cramps, and other complications can occur during any session, requiring continuous
monitoring and standardized, rapid response.
Responsibilities
● Monitor haemodynamic status (blood pressure, heart rate) continuously throughout every session.
● Apply standardized response protocols for hypotension, cramps, nausea, and other common
complications.
● Recognize and respond immediately to rare but serious complications (arrhythmia, air embolism,
dialysis disequilibrium syndrome).
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 16
7. Anticoagulation During Dialysis
Overview
Anticoagulation prevents clotting of the extracorporeal circuit during dialysis while requiring careful
individualization to avoid excessive bleeding risk.
Responsibilities
● Apply individualized anticoagulation (typically heparin) protocols based on patient bleeding risk.
● Monitor for circuit clotting and adjust anticoagulation per protocol.
● Apply heparin-free or citrate protocols for patients with genuine bleeding risk contraindications.
8. CKD-MBD, Anemia, and Nutrition Management
Overview
The long-term complications of kidney failure — mineral bone disorder, anemia, and malnutrition — shape
quality of life across years of dialysis therapy and require sustained, coordinated management.
Responsibilities
● Coordinate CKD-MBD management (phosphate binders, vitamin D, PTH monitoring) per evidence-
based protocol.
● Coordinate anemia management (ESA, iron supplementation) per evidence-based targets.
● Coordinate renal dietitian involvement for individualized nutritional management.
How the Dialysis Unit Team Contributes to Quality Healthcare
● By protecting vascular access meticulously, the team sustains a patient's literal lifeline across years of
repeated therapy.
● By monitoring dialysis adequacy rigorously, the team ensures each session genuinely substitutes for
lost kidney function.
● By maintaining disciplined infection control, the team prevents bloodborne pathogen transmission in
an environment of inherent blood exposure.
● By ensuring water treatment quality, the team protects patients from contamination entering their
bloodstream directly.
● By managing long-term complications, the team protects quality of life across the entire course of a
patient's therapy.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 17
The Dialysis Unit team sustains a therapy that never gets to rest — their vascular access precision protects
a patient's lifeline across hundreds of sessions, their infection control discipline never lapses into the
complacency repetition can breed, and their water treatment vigilance protects the purity of everything
that enters a patient's bloodstream, session after session, for years.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 18
CHAPTER 3: PROFESSIONAL STANDARDS FOR THE DIALYSIS UNIT TEAM
Dialysis practice requires an uncommon combination of meticulous technical precision sustained across years
of repetition, disciplined infection control in an environment of inherent blood exposure, genuine long-term
partnership with patients whose therapy defines a permanent rhythm of their lives, and unwavering resistance
to the complacency that routine repetition can breed. The standards that govern Dialysis Unit practice derive
from renal patient safety science, infection control principles, and the unique responsibility of sustaining life-
replacing therapy across a patient's remaining lifetime.
1. Professional Appearance
Standards
Attire and Identification
● Wear appropriate clinical attire, PPE, and ID badge as per hospital infection control policy, given the
significant blood exposure risk inherent to every session.
● Follow strict standard precautions dress code, including appropriate gloving and gowning for every
patient contact.
Professional Presence
● Maintain a calm, reassuring, and consistent demeanor across every session, recognizing patients' long-
term, repeated relationship with the unit.
● Model sustained meticulous practice that resists the complacency repetition can breed.
2. Professional Behaviour
Expected Behaviours
Precision Discipline
● Never cannulate without complete, systematic vascular access assessment first.
● Never allow fluid removal calculation to be estimated rather than precisely calculated.
Infection Control Discipline
● Never bypass standard precautions or isolation protocols, regardless of how familiar a patient or how
routine a session feels.
● Apply the same rigorous hand hygiene and aseptic technique on the thousandth session as on the first.
Accountability
● Own every cannulation decision, every fluid removal calculation, and every complication response
made for patients under Dialysis Unit care.
● Report and disclose critical incidents and adverse events honestly and promptly.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 19
Collaborative Respect
● Treat every member of the multidisciplinary Dialysis Unit team — nephrologist, nurse, technician,
dietitian — as an essential, equal safety partner.
● Treat every patient as a genuine long-term partner in their own care, recognizing their years of
accumulated experience with their own body's response to dialysis.
Patient-Centered Focus
● Every clinical decision is ultimately about the patient's sustained survival and quality of life across years
of therapy — not merely completing today's session.
3. Communication Standards
Communication with Patients
● Communicate dialysis adequacy, prescription changes, and long-term prognosis honestly and with
genuine partnership.
● Explain every intervention and its rationale in clear, non-technical language, recognizing patients'
accumulated familiarity with their own therapy.
● Support genuine patient involvement in their own care, including dry weight target discussions and
symptom reporting.
Communication Within the Team
● Communicate rapidly and clearly during intradialytic complications using closed-loop communication.
● Use structured handover tools (SBAR or equivalent) for every shift change and transfer of care.
● Escalate any deterioration or safety concern immediately and directly.
Written Communication Standards
● Dialysis documentation must be accurate, contemporaneous, and complete, reflecting precise fluid
removal, vital signs, and adequacy parameters.
● Vascular access assessment and cannulation records must be complete for every session.
● Water treatment and dialysate quality testing records must be complete and audit-ready.
4. Confidentiality and Information Security
Overview
Dialysis care involves sensitive bloodborne pathogen status and long-term chronic disease information,
requiring particular confidentiality discipline throughout a patient's sustained relationship with the unit.
Responsibilities
● Discuss patient information only in appropriate clinical settings and only with those who have a
legitimate need to know.
● Protect access credentials for EMR/HIS and dialysis information systems.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 20
● Apply particular discretion for bloodborne pathogen status, given both medical and social sensitivity.
5. Ethical Standards
Core Ethical Principles for Dialysis Unit Practice
Non-Maleficence
● Never allow a known vascular access risk or infection control lapse to persist unaddressed.
● Never proceed with cannulation or intervention without genuine informed consent, except in genuine
emergency.
Beneficence
● Apply evidence-based care consistently, recognizing the cumulative impact of care quality across years
of therapy.
Honesty and Transparency
● Communicate prognosis and complications honestly, including honest disclosure of adverse events.
Justice and Equity
● Apply the same rigorous standard to every patient, regardless of how long they have been in the unit's
care or their background.
6. Time Management and Prioritization
Clinical Priority Framework
● Immediate/Emergency: Cardiac arrest, severe hypotension, suspected air embolism, access
haemorrhage — immediate response, no delay.
● Urgent: Significant intradialytic complication, suspected access complication — prompt assessment
and escalation.
● Routine: Scheduled monitoring, routine cannulation, nutritional counselling — managed per defined
schedule, with unwavering consistency.
7. Teamwork and Collaboration
Work Effectively With
● Vascular surgery — for access creation, revision, and complication management.
● Nephrology — for prescription management and long-term clinical care.
● Renal dietitian — for individualized nutritional management.
● Infection control — for bloodborne pathogen precautions and isolation protocol compliance.
● Transplant services — for coordinated transplant referral and evaluation.
● Quality department — for incident reporting, RCA, and accreditation support.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 21
8. Professional Competence and Continuous Learning
Areas of Competence
● Vascular access assessment and meticulous cannulation technique.
● Dialysis adequacy calculation and prescription management.
● Water treatment quality assurance and dialysate testing methodology.
● Intradialytic complication recognition and response.
● Anticoagulation management during dialysis.
● FMEA, RCA, and CAPA methodologies for dialysis-specific quality improvement.
Continuous Learning
● Maintain current certification in dialysis-specific competencies and emergency response.
● Maintain current knowledge of evolving renal replacement therapy evidence and guidelines (KDIGO,
KDOQI, ISN).
● Engage with national and international nephrology and dialysis professional bodies.
● Participate regularly in dialysis emergency simulation and cannulation skills training.
● Participate in NABH, JCI, and CMS Conditions for Coverage accreditation training.
Professional Standards Checklist
● Have I completed systematic vascular access assessment before every cannulation today?
● Have I applied meticulous aseptic technique for every cannulation, without exception?
● Have I calculated fluid removal precisely for every patient today?
● Have I applied standard precautions and isolation protocols consistently?
● Have I monitored every patient's haemodynamic status continuously throughout their session?
● Have I reported any incident or safety concern through the appropriate system?
Dialysis Unit professionalism is sustained precision held to an unwavering standard across years of
repetition — the team that never cannulates without assessment, never bypasses infection control for
familiarity, and never lets today's routine session receive less rigour than the first is the team every dialysis
patient depends upon for a lifeline that must hold, session after session, for as long as they need it.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 22
CHAPTER 4: PATIENT-CENTERED COMMUNICATION IN THE DIALYSIS
UNIT
Communication in the Dialysis Unit occurs within a relationship unlike almost any other in healthcare: a patient
the team will see three times a week, for years, whose life has been reorganized around dialysis sessions, and
whose accumulated experience of their own body's response to therapy deserves genuine respect as clinical
information. This sustained relationship demands communication that remains genuinely attentive across the
thousandth conversation as much as the first, resisting the drift toward routine that repetition can bring to
even the most caring team.
Why Communication Quality Matters in the Dialysis Unit
● A patient's report of a symptom, dismissed as routine after years of familiarity, may be the first sign of
a genuine complication.
● Long-term dialysis patients often possess substantial accumulated knowledge of their own condition,
and communication that fails to respect this partnership undermines both trust and safety.
● Honest communication about dialysis adequacy and prescription changes supports genuine patient
engagement in their own long-term care.
● Poor communication about vascular access care can lead to patient behaviours that jeopardize access
longevity.
The A-T-C-R-C Communication Model for the Dialysis Unit
A — Acknowledge
Definition
Acknowledge the patient's long-term experience and the reality of dialysis as a permanent rhythm of their life,
genuinely and without dismissiveness, even in a routine session.
Examples
● “I know you've been coming here for years and know your body well — tell me what's different about
how you're feeling today.”
T — Listen (Respect Accumulated Patient Knowledge)
Definition
Listen genuinely to the patient's own observations about their access, their symptoms, and their response to
therapy, treating this as valuable clinical information.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 23
C — Clarify (Explain Adequacy and Prescription Changes)
Definition
Explain dialysis adequacy results, prescription changes, and their rationale in clear, non-technical language.
Examples
● “Your latest numbers show we need to adjust your session slightly — here's what that means and
why.”
R — Respond (Provide Honest, Actionable Information)
Definition
Respond to questions about long-term prognosis, access care, and lifestyle honestly and with genuine
partnership.
C — Confirm (Verify Understanding, Especially for Access Care)
Definition
Confirm genuine understanding, particularly for vascular access self-care instructions and warning signs
requiring urgent attention.
Communicating with Patients on Lifelong Therapy
Principles for Sustained Relationship Communication
● Resist the drift toward routine, brief interaction that repetition can bring — every session deserves
genuine attention.
● Respect the patient's accumulated expertise regarding their own body's response to dialysis as
valuable clinical information.
● Communicate dry weight target discussions and fluid management collaboratively, recognizing the
patient's daily experience of thirst and fluid restriction.
● Provide consistent messaging across the team to avoid confusing a patient managing a complex, long-
term condition.
Communicating About Vascular Access Care
Principles
● Provide clear, repeated education on access self-care, given the critical importance of access longevity.
● Communicate warning signs (infection, thrombosis, aneurysm) requiring urgent attention clearly and
repeatedly.
● Support genuine patient partnership in access protection, recognizing they are the primary daily
guardian of their own access between sessions.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 24
Communicating During Intradialytic Complications
Principles
● Communicate calmly and honestly during hypotension or other complications, avoiding alarm while
providing genuine reassurance.
● Explain the cause and management of complications in accessible language.
Common Dialysis Unit Communication Mistakes to Avoid
● Dismissing a long-term patient's reported symptom as “the usual” without genuine assessment.
● Providing inconsistent dietary or fluid restriction guidance across different team members.
● Failing to explain the rationale behind prescription or dry weight changes.
● Treating routine sessions as opportunities for reduced communication attentiveness.
Communication in the Dialysis Unit must sustain genuine attentiveness across a relationship measured in
years, not visits — the team that respects patients' accumulated expertise, explains every change honestly,
and resists the drift toward routine dismissiveness protects patients through a therapy that becomes a
permanent, lifelong partnership.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 25
CHAPTER 5: PATIENT SAFETY AND RENAL REPLACEMENT THERAPY
STANDARDS
Patient safety in the Dialysis Unit is uniquely defined by sustained consistency — a unit that protects vascular
access meticulously, monitors adequacy rigorously, and maintains infection control discipline without lapse
across thousands of repeated sessions produces measurably better long-term survival and quality of life than
one where standards erode into routine familiarity. The R-T-A-C-A framework applies with particular intensity
to the sustained, repetition-resistant nature of dialysis practice.
1. RESPECT
Definition
Treating every vascular access and every patient's long-term partnership in care as equally deserving of the
Dialysis Unit's full rigour, regardless of how many times a session has been repeated.
How the Dialysis Unit Demonstrates Respect
● Respect for the Vascular Access: Apply the same meticulous cannulation care to session one thousand
as to session one.
● Respect for Accumulated Patient Knowledge: Value patients' own observations about their access and
symptoms as genuine clinical information.
● Respect for Every Team Member's Vigilance: Value the technician's continuous monitoring as highly
as the nephrologist's prescription decisions.
● Equal Service Standards: Apply the same rigorous protocol to every patient, regardless of how long
they have been in the unit's care.
2. TIMELINESS
Definition
Recognizing and responding to intradialytic complications and vascular access concerns within timeframes that
protect patient safety during and between sessions.
Why Timeliness Is a Patient Safety Issue
Intradialytic hypotension unaddressed can progress to genuine haemodynamic compromise within minutes. A
vascular access infection unaddressed can progress to sepsis. Time in the Dialysis Unit, though the therapy
itself is scheduled and repeated, remains genuinely critical within any single session's complications.
Dialysis Unit Timeliness Standards
● Intradialytic complication response: immediate upon recognition, no delay.
● Vascular access complication escalation: prompt, per defined protocol.
● Water treatment/dialysate quality deviation response: immediate treatment halt where indicated.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 26
3. ACCURACY
Definition
Calculating every fluid removal target precisely, assessing every vascular access systematically, and testing
every water/dialysate sample rigorously, sustained without deviation across thousands of repeated sessions.
Why Accuracy Is Non-Negotiable in the Dialysis Unit
An inaccurate fluid removal calculation can cause dangerous hypotension or inadequate fluid clearance. An
inconsistently applied cannulation technique can shorten a vascular access's functional lifespan, threatening a
patient's future access options. Accuracy in the Dialysis Unit, sustained across years of repetition, is what
separates safe renal replacement therapy from a therapy degraded by the complacency repetition can breed.
Areas Requiring Dialysis Unit Accuracy
● Fluid Removal Calculation: Every session's ultrafiltration target must be calculated precisely against
dry weight and interdialytic weight gain.
● Vascular Access Assessment: Every cannulation must be preceded by systematic, genuine assessment,
not assumption based on familiarity.
● Water/Dialysate Testing: Every quality test must be conducted rigorously per regulatory schedule.
● Documentation: Every dialysis record must accurately and completely reflect precise parameters and
clinical findings.
4. COMPASSION
Definition
Recognizing that every dialysis patient is navigating a permanent reorganization of their life around this
therapy, and that genuine, sustained compassion across years of repeated sessions is itself a core component
of excellent renal replacement care.
How the Dialysis Unit Demonstrates Compassion
● Sustain Genuine Attentiveness: Resist the drift toward routine interaction that years of repetition can
bring.
● Support Emotional Adjustment to Lifelong Therapy: Recognize the profound life adjustment dialysis
dependency represents.
● Respect Fluid and Dietary Restriction Burden: Approach restriction counselling with genuine empathy
for its daily difficulty.
● Extend Compassion to Long-Term Complications: Support patients navigating CKD-MBD, anemia, and
other chronic complications with sustained care.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 27
5. ACCOUNTABILITY
Definition
Taking full professional responsibility for every cannulation decision, every fluid removal calculation, and every
complication response made across the entire, sustained course of a patient's therapy.
Dialysis Unit Accountability Standards
● Every cannulation, fluid calculation, and clinical assessment is documented with the responsible team
member's identification.
● Never allow a known vascular access risk or infection control lapse to go unaddressed.
● Report every critical incident and adverse dialysis event honestly through the quality reporting system.
● Participate in RCA for significant incidents with complete clinical honesty.
● Participate in quality audits and accreditation surveys with accurate, complete dialysis care records.
The R-T-A-C-A Framework in the Dialysis Unit
Standard Core Focus in the Dialysis Unit
Respect Vascular access and patient partnership honoured equally across every repeated session
Timeliness Immediate complication response; prompt access concern escalation
Accuracy Precise fluid calculation, systematic access assessment, rigorous water testing
Compassion Sustained attentiveness resisting routine drift; support for lifelong adjustment
Accountability Every decision owned and documented; every incident honestly reviewed
Daily Quality Standards Checklist for the Dialysis Unit
● Complete systematic vascular access assessment before every cannulation.
● Apply meticulous aseptic technique for every cannulation, without exception.
● Calculate fluid removal precisely for every patient.
● Apply standard precautions and isolation protocols consistently.
● Monitor haemodynamic status continuously throughout every session.
● Document every clinical assessment and intervention completely.
● Report any incident or safety concern through the quality reporting system.
In the Dialysis Unit, patient safety is measured across years of sustained consistency — a family experiences
it as a vascular access that lasted a decade because it was cannulated correctly every single time, and a
loved one who lived fully because a team's vigilance never once relaxed into routine.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 28
CHAPTER 6: CONFIDENTIALITY, PRIVACY, AND INFORMATION
SECURITY
The Dialysis Unit presents a distinctive confidentiality environment: patients typically receive treatment in a
shared bay of multiple stations, often alongside the same fellow patients for years, while managing sensitive
bloodborne pathogen status and chronic disease information requiring particular discretion.
1. Privacy in the Shared Dialysis Bay Environment
Responsibilities
● Use available privacy measures for sensitive conversations, even within a shared, open bay
environment.
● Never discuss one patient's case within earshot of another patient's station.
● Conduct sensitive discussions (bloodborne pathogen status, prognosis) in as private a space as
available.
2. Confidentiality of Bloodborne Pathogen Status
Overview
Hepatitis B, hepatitis C, and HIV status carry particular medical and social sensitivity, requiring heightened
confidentiality discipline alongside necessary clinical isolation protocols.
Responsibilities
● Handle bloodborne pathogen status information with heightened confidentiality and discretion.
● Apply necessary isolation protocols without unnecessarily disclosing the underlying reason to other
patients.
● Communicate only the clinically necessary information to the wider care team.
3. Clinical Data and EMR/HIS Confidentiality
Responsibilities
● Access only the patient records necessary for current dialysis care responsibilities.
● Never discuss a patient's clinical information with anyone outside the legitimate care team.
● Follow hospital IT and cybersecurity policy for all EMR/HIS and dialysis information system access.
● Never leave dialysis unit workstations unlocked or logged in when unattended.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 29
4. Cybersecurity of Dialysis Information Systems
Why Cybersecurity Is a Patient Safety Issue
Dialysis information systems store the precise fluid removal, adequacy, and prescription data upon which safe
therapy depends, across years of accumulated patient records. A compromised system risks both sensitive data
breach and, if clinical or prescription data is corrupted, direct patient safety harm.
Responsibilities
● Use only authorized, unique login credentials for all EMR/HIS and dialysis monitoring system access.
● Never share login credentials with colleagues, regardless of workload pressure.
● Never connect personal devices to hospital clinical networks without IT authorization.
● Report any suspected unauthorized access or cybersecurity anomaly to IT security immediately.
5. Confidentiality for High-Profile and Vulnerable Patients
Responsibilities
● Maintain the same confidentiality standard for high-profile or notorious patients as for every other
patient.
● Never disclose patient identity, diagnosis, or condition to media or unauthorized persons.
Confidentiality Checklist for the Dialysis Unit Team
● Use available privacy measures for sensitive conversations within the shared bay environment.
● Handle bloodborne pathogen status with heightened discretion.
● Use only authorized credentials for EMR/HIS and monitoring systems.
● Never connect personal devices to hospital clinical networks without IT authorization.
In the Dialysis Unit, confidentiality must be actively maintained within a shared, open bay environment,
for information — particularly bloodborne pathogen status — that carries genuine social as well as medical
sensitivity across a patient's long-term, sustained relationship with the unit.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 30
CHAPTER 7: STANDARD OPERATING PROCEDURES (SOPs) FOR THE
DIALYSIS UNIT
Objectives of Dialysis Unit SOPs
● Ensure consistent, safe, and precise renal replacement therapy for every patient, every session.
● Minimize patient harm through systematic, documented vascular access, infection control, and
complication response protocols.
● Support NABH/JCI/CMS accreditation compliance for dialysis facility standards.
● Provide a defensible clinical and legal framework for incident investigation and quality improvement.
SOP 1: Pre-Dialysis Assessment and Machine Setup
Purpose
To ensure systematic pre-session assessment and safe machine preparation for every session.
Procedure
● Step 1: Conduct Pre-Dialysis Assessment — assess weight, vital signs, and clinical status before every
session.
● Step 2: Verify Machine Setup — verify dialysis machine setup, dialysate composition, and alarm
function.
● Step 3: Calculate Fluid Removal — calculate precise ultrafiltration target based on dry weight and
interdialytic weight gain.
● Step 4: Document — document the complete pre-dialysis assessment.
Quality Standards
● 100% of sessions include documented pre-dialysis assessment and fluid removal calculation.
SOP 2: Vascular Access Cannulation Technique
Purpose
To protect vascular access integrity through meticulous, consistent cannulation technique.
Procedure
● Step 1: Assess the Access — conduct systematic assessment (inspection, palpation, auscultation)
before every cannulation.
● Step 2: Apply Aseptic Technique — apply meticulous skin preparation and aseptic cannulation
technique.
● Step 3: Rotate Sites — apply rope-ladder or buttonhole technique per protocol to preserve access
integrity.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 31
● Step 4: Secure and Monitor — secure needles appropriately and monitor for infiltration.
● Step 5: Document — document the complete cannulation assessment and technique.
Quality Standards
● 100% of cannulations include documented pre-cannulation access assessment.
SOP 3: Intradialytic Monitoring and Documentation
Purpose
To ensure continuous, systematic monitoring throughout every dialysis session.
Procedure
● Step 1: Monitor Vital Signs — monitor blood pressure, heart rate, and clinical status per defined
schedule.
● Step 2: Monitor Machine Parameters — monitor blood flow rate, dialysate flow, and ultrafiltration
rate continuously.
● Step 3: Document Throughout — document monitoring findings per defined schedule throughout the
session.
● Step 4: Recognize and Respond — recognize and respond immediately to any deviation.
Quality Standards
● 100% of sessions include complete, per-schedule intradialytic monitoring documentation.
SOP 4: Hypotension and Intradialytic Complication Response
Purpose
To ensure immediate, standardized response to common intradialytic complications.
Procedure
● Step 1: Recognize the Complication — recognize hypotension, cramps, or other complications
promptly.
● Step 2: Apply Immediate Response — apply standardized response (fluid bolus, ultrafiltration
reduction, positioning) per protocol.
● Step 3: Reassess — reassess response and escalate if symptoms persist.
● Step 4: Document — document the complication and complete response.
Quality Standards
● 100% of intradialytic complications include documented standardized response.
SOP 5: Anticoagulation Management (Heparin Protocol)
Purpose
To prevent circuit clotting while minimizing bleeding risk through individualized anticoagulation.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 32
Procedure
● Step 1: Assess Bleeding Risk — assess individual bleeding risk before every session's anticoagulation
plan.
● Step 2: Apply Individualized Protocol — apply standard, reduced, or heparin-free protocol per patient
risk profile.
● Step 3: Monitor for Clotting — monitor the circuit for clotting throughout the session.
● Step 4: Document — document the anticoagulation protocol applied and any adjustment.
Quality Standards
● 100% of sessions include documented individualized anticoagulation risk assessment.
SOP 6: Bloodborne Pathogen Precautions and Isolation
Purpose
To prevent bloodborne pathogen transmission through rigorous, consistent precautions.
Procedure
● Step 1: Apply Standard Precautions — apply standard precautions for every patient, every session,
without exception.
● Step 2: Apply Isolation Protocol — apply dedicated machine/station isolation for hepatitis B, hepatitis
C, or HIV-positive patients per policy.
● Step 3: Apply Rigorous Hand Hygiene — apply hand hygiene and glove changes between every patient
contact.
● Step 4: Document — document isolation protocol application.
Quality Standards
● 100% compliance with isolation protocols for applicable patients.
SOP 7: Water Treatment and Dialysate Quality Testing
Purpose
To ensure water and dialysate quality meets pharmaceutical-grade purity standards.
Procedure
● Step 1: Conduct Scheduled Testing — conduct water treatment system chemical and microbiological
testing per regulatory schedule.
● Step 2: Test Dialysate — test dialysate quality systematically per defined schedule.
● Step 3: Respond to Deviation — halt affected treatment and escalate immediately upon any quality
deviation.
● Step 4: Document — maintain complete, audit-ready water/dialysate quality testing records.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 33
Quality Standards
● 100% compliance with regulatory water/dialysate testing schedule.
SOP 8: Dialyzer Reprocessing/Reuse (Where Applicable)
Purpose
To ensure safe, standardized dialyzer reprocessing where institutional policy permits reuse.
Procedure
● Step 1: Apply Standardized Reprocessing — apply standardized cleaning, testing, and disinfection
protocol.
● Step 2: Verify Performance — verify dialyzer performance (fibre bundle volume) meets reuse criteria.
● Step 3: Label and Track — label and track each dialyzer to the correct individual patient.
● Step 4: Document — document each reprocessing cycle completely.
Quality Standards
● 100% compliance with standardized reprocessing protocol where reuse is practiced.
SOP 9: Needle-Stick and Bloodborne Exposure Response
Purpose
To ensure immediate, appropriate response to occupational bloodborne exposure.
Procedure
● Step 1: Apply Immediate First Aid — wash the exposure site immediately per protocol.
● Step 2: Report Immediately — report the exposure to occupational health/infection control
immediately.
● Step 3: Assess and Treat — assess source patient status and initiate post-exposure prophylaxis as
indicated.
● Step 4: Document — document the complete exposure and response.
Quality Standards
● 100% of needle-stick exposures reported and managed within the institutionally defined timeframe.
SOP 10: Vascular Access Complication and Emergency Response
Purpose
To ensure immediate, appropriate response to vascular access complications and emergencies.
Procedure
● Step 1: Recognize the Complication — recognize access haemorrhage, infection, or thrombosis
promptly.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 34
● Step 2: Apply Immediate Response — apply direct pressure for haemorrhage or escalate for suspected
infection/thrombosis.
● Step 3: Coordinate Vascular Surgery — coordinate urgent vascular surgery consultation as indicated.
● Step 4: Document — document the complication and complete response.
Quality Standards
● 100% of vascular access complications include documented immediate response and escalation.
Dialysis Unit SOP Daily Compliance Checklist
● Pre-dialysis assessment and fluid removal calculation completed for every session today.
● Vascular access assessment completed before every cannulation.
● Standard precautions and isolation protocols applied consistently.
● Water/dialysate quality testing completed per schedule.
● Any incident or safety concern reported through the appropriate system.
SOPs in the Dialysis Unit are the operating instructions for sustaining a lifeline across years of repeated
sessions. When followed consistently, they are the systematic foundation of vascular access protection,
infection control, and precise fluid management for every patient in the unit's care.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 35
CHAPTER 8: COMMUNICATION WITH SPECIAL GROUPS
The Dialysis Unit team communicates across an unusually sustained range of circumstances — from a newly
diagnosed patient facing the shock of lifelong dialysis dependency, to a decade-long patient managing the
accumulated complications of chronic kidney disease, to a family supporting a loved one through a
permanently reorganized life, to transplant services coordinating a patient's path toward a different future.
Excellent dialysis practice requires adapted communication for each of these circumstances.
1. Newly Diagnosed Dialysis Patients
Overview
Patients newly starting dialysis face a profound life adjustment, often compounded by the shock of a recent
diagnosis of kidney failure.
Communication Guidelines
● Provide clear, structured education on what dialysis involves, delivered with patience and repetition.
● Acknowledge the emotional weight of this life transition genuinely.
● Support gradual, realistic adjustment rather than overwhelming with excessive information at once.
2. Long-Term Dialysis Patients
Overview
Patients with years of dialysis experience bring substantial accumulated knowledge and deserve genuine
partnership, not routine, dismissive interaction.
Communication Guidelines
● Respect their accumulated expertise regarding their own body's response to therapy.
● Maintain genuine attentiveness, resisting the drift toward routine familiarity.
● Engage them as partners in ongoing prescription and care decisions.
3. Pediatric Dialysis Patients and Families
Overview
Children requiring dialysis face particular developmental and family challenges, requiring coordination with
pediatric nephrology expertise.
Communication Guidelines
● Communicate with parents as primary decision-making partners while engaging the child
appropriately for their age.
● Support family adjustment to a child's lifelong or transitional dialysis dependency.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 36
4. Patients Facing Transplant Evaluation
Overview
Patients being evaluated for kidney transplant navigate hope alongside the uncertainty of waiting, requiring
supportive, honest communication.
Communication Guidelines
● Coordinate clearly with transplant services regarding evaluation status and timeline.
● Support realistic hope while maintaining continued excellent dialysis care throughout the waiting
period.
5. Families and Caregivers
Overview
Families supporting a dialysis patient navigate their own version of the permanent life reorganization dialysis
brings.
Communication Guidelines
● Include family members appropriately in education regarding fluid restriction, dietary management,
and access care support.
● Recognize and support the caregiver burden of sustained, long-term illness support.
6. Patients Considering Peritoneal Dialysis or Home Therapy
Overview
Patients considering alternative dialysis modalities require thorough, unbiased education to make genuinely
informed choices.
Communication Guidelines
● Provide balanced, complete information on all appropriate dialysis modality options.
● Support genuine patient choice based on their lifestyle, values, and clinical circumstances.
7. Vascular Surgery and Interventional Radiology Teams
Communication Guidelines
● Communicate access complications and concerns clearly and promptly for coordinated intervention.
● Coordinate access creation and revision planning collaboratively.
8. Hospital Administration and Quality/Accreditation Bodies
Communication Guidelines
● Present vascular access outcomes, adequacy compliance, and infection rate data in management-
accessible formats.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 37
● Advocate for necessary resources with clear patient safety justification.
Universal Dialysis Unit Communication Principles
● Communicate with sustained genuine attentiveness, resisting the drift toward routine interaction.
● Respond to every reported symptom and every patient's genuine concern with appropriate
seriousness.
● Always respect patients' accumulated experience of their own therapy.
● Document every significant clinical communication completely.
The Dialysis Unit team that communicates with equal genuine attentiveness toward a newly diagnosed
patient's shock and a decade-long patient's accumulated expertise serves every stakeholder at maximum
impact — sustained clinical excellence delivered alongside the compassion that a permanent, lifelong
therapy demands.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 38
CHAPTER 9: HANDLING DIFFICULT SITUATIONS
Common Difficult Situations for the Dialysis Unit Team
● A patient develops significant intradialytic hypotension unresponsive to first-line measures.
● A vascular access shows signs of infection or thrombosis.
● A patient consistently exceeds fluid restriction, creating recurring complications.
● Water treatment system testing reveals a quality deviation.
● A needle-stick or bloodborne exposure occurs.
● A patient declines a recommended prescription change.
● A long-term patient's condition suggests the therapy is no longer meeting their goals of care.
● A colleague's cannulation technique or clinical judgment raises concern.
● Machine capacity constraints require difficult scheduling decisions.
● A patient with bloodborne pathogen status requires isolation the patient finds stigmatizing.
Core Principles for Handling Difficult Situations
1. Sustained Vascular Access and Infection Control Integrity Are Paramount
In every difficult situation, protecting the vascular access and maintaining infection control drive every decision
— these must never be compromised for administrative or interpersonal convenience.
2. Apply Standardized Protocols, Resisting Complacency
The routine nature of dialysis is precisely why standardized protocols matter most — resist the temptation to
shortcut a familiar process.
3. Escalate Immediately and Persistently
A genuine safety concern is not resolved until it reaches someone who can act on it — escalate through
alternative channels if the first attempt does not produce a response.
4. Document Everything
Every difficult clinical situation must be contemporaneously documented — what was found, what was
communicated, what decisions were made, and by whom.
Handling Refractory Intradialytic Hypotension
Steps
● Apply escalating standardized response (fluid bolus, ultrafiltration reduction/pause, positioning) per
protocol.
● Escalate to physician assessment if symptoms persist despite standard measures.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 39
● Review and adjust dry weight target and ultrafiltration profile for future sessions.
Handling Suspected Vascular Access Infection or Thrombosis
Steps
● Recognize signs promptly and escalate for urgent clinical assessment.
● Coordinate urgent vascular surgery consultation as indicated.
● Apply alternative access (temporary catheter) if the primary access requires urgent intervention.
Handling Recurrent Fluid Restriction Non-Adherence
Steps
● Engage the patient genuinely to understand barriers to adherence, without judgment.
● Involve the renal dietitian and, where appropriate, psychosocial support.
● Collaborate on realistic, sustainable strategies rather than repeated instruction alone.
Handling a Water Treatment Quality Deviation
Steps
● Halt affected treatment immediately upon identifying a deviation.
● Escalate to engineering/water treatment specialists and institutional leadership immediately.
● Coordinate patient notification and any necessary clinical follow-up per protocol.
● Conduct thorough review to identify and correct the root cause.
Handling a Needle-Stick or Bloodborne Exposure
Steps
● Apply immediate first aid and report to occupational health without delay.
● Assess source patient status and initiate post-exposure prophylaxis per protocol as indicated.
● Conduct thorough review to strengthen future exposure prevention.
Handling a Patient Declining a Recommended Prescription Change
Steps
● Explain the clinical rationale clearly and without coercion.
● Ensure genuine understanding through teach-back or equivalent confirmation.
● Respect the patient's informed decision while continuing to monitor and support.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 40
Handling a Long-Term Patient's Goals of Care Reassessment
Steps
● Involve nephrology, palliative care, and the patient/family in an honest, structured conversation.
● Communicate prognosis honestly while supporting the patient's own values and wishes.
● Support the patient's decision, whatever it may be, with genuine compassion.
Handling Concern About a Colleague's Cannulation Technique
Steps
● Address any immediate patient safety concern directly and without delay.
● Raise the concern through appropriate professional and educational channels.
● Escalate to department leadership if the concern is serious or unresolved.
Handling Machine Capacity Constraints
Steps
● Apply objective, clinical-need-based criteria for scheduling decisions.
● Coordinate with hospital operations and, where necessary, regional dialysis network capacity.
● Communicate transparently with affected patients about any necessary schedule adjustment.
Handling Isolation Protocols a Patient Finds Stigmatizing
Steps
● Explain the clinical rationale for isolation clearly and with genuine sensitivity.
● Apply isolation protocols consistently while minimizing unnecessary visibility of the underlying reason
to other patients.
● Support the patient's emotional experience of isolation with genuine compassion.
The CALM Model for the Dialysis Unit
● C – Control the immediate haemodynamic or access-related risk.
● A – Acknowledge the clinical and emotional reality accurately.
● L – Lead with evidence — dialysis protocols, adequacy criteria, and infection control standards.
● M – Manage through documented escalation channels when needed.
Difficult situations in the Dialysis Unit are always, ultimately, tests of whether sustained protocol discipline
holds firm against the complacency that years of repetition can breed. The team that never compromises
vascular access integrity, never bypasses infection control for familiarity, and escalates persistently until
genuine safety is restored is fulfilling the highest professional obligation of renal replacement therapy.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 41
CHAPTER 10: EMERGENCY RESPONSE — CRITICAL DIALYSIS
PRESENTATIONS
Overview
While the majority of dialysis sessions proceed without incident, certain presentations demand the Dialysis
Unit team's most immediate, standardized, and rehearsed response — scenarios where the difference
between a coordinated, protocol-driven response and an improvised one is measured directly in patient
survival.
Critical Presentations Requiring Immediate Response
● Cardiac arrest during dialysis.
● Severe, refractory intradialytic hypotension.
● Suspected air embolism.
● Vascular access haemorrhage.
● Dialysis disequilibrium syndrome.
● Anaphylactoid reaction (dialyzer/membrane reaction).
● Severe hyperkalemia presenting for emergency dialysis.
● Hemolysis during dialysis.
● Severe allergic/anaphylactic reaction.
● Fire or water treatment system failure affecting patient safety.
1. Cardiac Arrest During Dialysis
Immediate Response
● Stop the blood pump and clamp the lines immediately (return blood if haemodynamically appropriate
per protocol).
● Initiate high-quality CPR immediately per current ACLS guidelines.
● Activate the emergency response team and apply defibrillation if indicated.
2. Severe, Refractory Intradialytic Hypotension
Steps
● Stop ultrafiltration immediately and apply fluid bolus per protocol.
● Position the patient appropriately (Trendelenburg or equivalent) per protocol.
● Escalate to physician assessment if hypotension does not respond to standard measures.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 42
3. Suspected Air Embolism
Steps
● Stop the blood pump and clamp the venous line immediately.
● Position the patient in left lateral decubitus with head down (Trendelenburg) per protocol.
● Administer high-flow oxygen and activate emergency medical response immediately.
4. Vascular Access Haemorrhage
Steps
● Apply immediate direct pressure to the bleeding site.
● Assess haemodynamic status and escalate for surgical intervention if bleeding is not controlled.
● Coordinate blood product support if significant blood loss occurs.
5. Dialysis Disequilibrium Syndrome
Steps
● Recognize early signs (headache, nausea, confusion) promptly, particularly in first-time or high-urea
patients.
● Reduce dialysis efficiency (blood flow rate, session duration) immediately upon recognition.
● Escalate for seizure management per protocol if severe disequilibrium progresses.
6. Anaphylactoid/Membrane Reaction
Steps
● Stop the blood pump immediately upon recognizing a reaction.
● Do not return the blood in the circuit if a Type A (severe, IgE-mediated) reaction is suspected.
● Administer emergency treatment (antihistamines, epinephrine as indicated) per protocol.
7. Severe Hyperkalemia (Emergency Dialysis)
Steps
● Confirm the diagnosis and ECG changes promptly.
● Coordinate immediate emergency dialysis initiation with appropriate prescription adjustment.
● Apply continuous cardiac monitoring throughout the emergency session.
8. Hemolysis During Dialysis
Steps
● Recognize signs (chest pain, back pain, dark-coloured blood in the circuit) immediately.
● Stop the blood pump immediately and do not return the blood in the circuit.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 43
● Investigate and correct the underlying cause (water quality, mechanical issue) before resuming.
9. Severe Allergic/Anaphylactic Reaction
Steps
● Stop the dialysis session immediately upon recognizing anaphylaxis.
● Administer epinephrine immediately per weight-based protocol.
● Support airway, breathing, and circulation aggressively.
10. Fire or Water Treatment System Failure
Steps
● Activate the facility emergency response plan immediately.
● Safely discontinue affected treatments per emergency protocol.
● Coordinate patient safety and, where necessary, evacuation per institutional plan.
Emergency Response: Key Performance Targets
Emergency Scenario Maximum Response Time Key Action
Cardiac Arrest Immediate Stop pump; clamp lines; initiate
high-quality CPR
Suspected Air Embolism Immediate Clamp venous line; Trendelenburg
position; high-flow oxygen
Vascular Access Haemorrhage Immediate Direct pressure; assess for surgical
escalation
Anaphylactoid Reaction Immediate Stop pump; do not return blood;
administer treatment
Severe Hypotension Immediate Stop UF; fluid bolus; position;
escalate if refractory
Emergency Preparedness Checklist for the Dialysis Unit
● Emergency medications and resuscitation equipment verified and accessible at every station.
● Air embolism and haemorrhage response protocols known to every team member.
● Regular participation in dialysis-specific emergency simulation training.
Emergency preparedness in the Dialysis Unit is not a policy statement — it is the immediate, standardized,
rehearsed response that determines survival in the rare but genuine crisis that can occur during any
session, however routine the thousands that preceded it may have been.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 44
CHAPTER 11: DIGITAL COMPETENCY FOR THE DIALYSIS UNIT
Objectives
● Enable the Dialysis Unit team to use dialysis machine, monitoring, and clinical information systems
accurately, securely, and efficiently.
● Leverage technology to improve adequacy tracking, fluid management precision, and coordinated
communication.
● Manage the cybersecurity of dialysis information systems as a core patient safety function.
Core Digital Competencies for the Dialysis Unit
1. Dialysis Machine and Monitoring Systems
Essential Skills
● Configure and monitor dialysis machine parameters (blood flow, dialysate flow, ultrafiltration rate)
accurately.
● Recognize and respond to machine-generated alarms promptly, applying independent clinical
judgment.
2. Electronic Adequacy Tracking Systems
Essential Skills
● Enter and track dialysis adequacy (Kt/V, URR) data systematically.
● Generate adequacy trend reports supporting prescription management.
3. Electronic Medical Record (EMR) / Hospital Information System (HIS)
Essential Skills
● Document pre-dialysis assessment, intradialytic monitoring, and complications accurately and in real
time.
4. Water Treatment Monitoring Systems
Essential Skills
● Use water treatment system monitoring and testing documentation systems accurately.
5. AI-Assisted Fluid Management and Prediction
Awareness
● AI and predictive analytics tools are increasingly applied to intradialytic hypotension prediction and
fluid management optimization.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 45
● Understand and appropriately leverage these tools while maintaining independent clinical judgment
— AI tools are decision-support, not a substitute for continuous bedside vigilance.
6. Telemedicine for Remote Nephrology Consultation
Essential Skills
● Use telemedicine platforms for remote nephrology consultation where applicable, particularly for
satellite dialysis facilities.
7. Cybersecurity and Information Security
Personal Digital Security Responsibilities
● Use unique, strong credentials for all EMR/HIS and dialysis monitoring system logins.
● Lock or log out of workstations whenever stepping away, even briefly.
● Never connect personal devices to hospital clinical networks.
● Report all cybersecurity anomalies to IT security immediately.
Digital Competency Checklist
● Navigate dialysis machine, adequacy tracking, and EMR/HIS systems for all core functions without
assistance.
● Generate accurate adequacy and complication trend reports.
● Apply basic cybersecurity practices to all clinical system access.
● Know the downtime procedure for machine/EMR system failure.
Digital competency for the Dialysis Unit team is the ability to integrate precise, sustained clinical judgment
with the machine monitoring, adequacy tracking, and predictive systems that modern renal replacement
therapy increasingly depends upon — using technology to extend, never replace, the continuous vigilance
that defines safe dialysis care across thousands of repeated sessions.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 46
CHAPTER 12: DAILY DIALYSIS UNIT CHECKLIST
Objectives
● Provide a structured daily framework for safe, precise, and sustained renal replacement therapy.
● Ensure every vascular access, infection control, and monitoring obligation is addressed every shift.
● Support accurate clinical documentation and departmental performance data quality.
PART A: START-OF-SHIFT CHECKLIST
Personal and Professional Readiness
● Appropriate clinical attire, PPE, and ID badge displayed.
● EMR/HIS and dialysis machine monitoring systems functional and accessible.
Handover and Readiness Review
● Reviewed structured handover from previous shift, including any patients with recent complications.
● Verified emergency medications and resuscitation equipment are stocked and functional.
● Verified water treatment system status and testing schedule current.
PART B: PRE-DIALYSIS ASSESSMENT CHECKLIST
● Weight, vital signs, and clinical status assessed for every patient before session start.
● Fluid removal target calculated precisely for every patient.
● Vascular access assessed systematically before every cannulation.
PART C: CANNULATION AND SESSION SETUP CHECKLIST
● Aseptic cannulation technique applied for every access, without exception.
● Dialysis machine settings verified against the prescribed order.
● Anticoagulation protocol applied per individualized bleeding risk assessment.
PART D: INTRADIALYTIC MONITORING CHECKLIST
● Vital signs monitored per defined schedule throughout every session.
● Machine parameters monitored continuously.
● Any complication recognized and responded to immediately.
PART E: INFECTION CONTROL CHECKLIST
● Standard precautions applied for every patient contact.
● Isolation protocols applied consistently for applicable patients.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 47
● Hand hygiene compliance maintained between every patient contact.
PART F: WATER TREATMENT AND EQUIPMENT CHECKLIST
● Water/dialysate quality testing completed per schedule.
● Dialysis machines verified functional and disinfected per protocol.
PART G: SAFETY AND INCIDENT CHECKLIST
● Any incident, near-miss, or complication reported through the appropriate system.
● CAPA actions from previous incidents reviewed for completion.
PART H: END-OF-SHIFT CHECKLIST
● All clinical records updated and complete for the shift.
● Structured handover prepared for the incoming shift.
● Clinical systems securely logged out.
Daily Self-Assessment for the Dialysis Unit Team
● Did we complete systematic vascular access assessment before every cannulation today?
● Did we apply meticulous aseptic technique for every cannulation, without exception?
● Did we calculate fluid removal precisely for every patient?
● Did we apply standard precautions and isolation protocols consistently?
● Did we communicate honestly and with genuine attentiveness with every patient?
A consistent, structured daily routine — from start-of-shift equipment verification to end-of-shift handover
— transforms individual clinical precision into a systemic dialysis safety programme that operates reliably
across every shift, every session, and every patient whose lifeline depends on this unit's sustained vigilance.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 48
CHAPTER 13: KEY PERFORMANCE INDICATORS (KPIs) FOR THE DIALYSIS
UNIT
Objectives
● Measure vascular access outcomes, dialysis adequacy, and infection control performance objectively.
● Enable data-driven continuous improvement in Dialysis Unit practice.
● Support NABH/JCI/CMS accreditation standards for dialysis facility care.
● Demonstrate the value and patient safety impact of the Dialysis Unit to institutional leadership.
Categories of Dialysis Unit KPIs
1. Vascular Access KPIs
KPI Definition Target
AVF/AVG Prevalence Rate % of patients dialyzing with a fistula or graft (vs. catheter) Maximize per
KDOQI/institutional
target
Catheter-Related Bloodstream
Infection Rate
Infections per 1,000 catheter-days At or below
institutional/national
benchmark
Vascular Access Complication Rate % of sessions with a documented access complication Minimize; track and
trend
2. Dialysis Adequacy KPIs
KPI Definition Target
Kt/V Target Achievement Rate % of patients meeting evidence-based Kt/V target ≥ 90% (or
institutional target)
URR Target Achievement Rate % of patients meeting evidence-based URR target ≥ 90% (or
institutional target)
Adequacy Monitoring Compliance % of patients with adequacy monitored per defined
schedule
100%
3. Infection Control KPIs
KPI Definition Target
Bloodstream Infection Rate Access-related bloodstream infections per 100
patient-months
At or below
institutional/national
benchmark
Hand Hygiene Compliance % compliance with hand hygiene protocol on audit ≥ 95%
Isolation Protocol Compliance % compliance with required isolation for bloodborne
pathogen-positive patients
100%
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 49
4. Water Treatment and Safety KPIs
KPI Definition Target
Water/Dialysate Quality Testing
Compliance
% of scheduled tests completed per regulatory
requirement
100%
Intradialytic Hypotension Rate % of sessions with clinically significant hypotension Minimize; track and
trend
Needle-Stick/Exposure Reporting
Timeliness
% of exposures reported within required timeframe 100%
5. Outcome and Governance KPIs
KPI Definition Target
Hospitalization Rate Hospital admissions per patient-year among dialysis
patients
At or below
institutional/national
benchmark
RCA Completion Rate % of significant adverse events with completed RCA 100%
Transplant Referral Rate % of eligible patients referred for transplant
evaluation
Track and maximize
Using KPIs for Continuous Improvement
● Review all Dialysis Unit KPIs regularly at departmental quality and governance meetings.
● Analyse vascular access, adequacy, and infection trends to identify targeted process improvements.
● Use benchmarking data to compare performance against national/international standards.
● Present KPI data to hospital management to demonstrate the patient safety impact of Dialysis Unit
excellence.
Dialysis Unit KPIs translate sustained, repetition-resistant vigilance into institutional accountability —
demonstrating that the investment in vascular access protection, dialysis adequacy monitoring, and
infection control discipline is a measurable, trackable, life-sustaining patient safety programme across
years of repeated therapy.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 50
CHAPTER 14: TOP 20 DO'S & TOP 20 DON'TS FOR THE DIALYSIS UNIT
Introduction
The Dialysis Unit team sustains a therapy that must be delivered correctly not once, but three or more times a
week, for years. Their daily professional decisions — about vascular access precision, infection control
discipline, and resistance to the complacency repetition can breed — determine whether every patient's
lifeline holds for as long as they need it. These Do's and Don'ts provide the practical daily architecture of Dialysis
Unit excellence.
TOP 20 DO'S FOR THE DIALYSIS UNIT
● 1. Assess Vascular Access Systematically Before Every Cannulation — Never assume based on
familiarity.
● 2. Apply Meticulous Aseptic Technique Every Time — Session one thousand deserves the same rigour
as session one.
● 3. Calculate Fluid Removal Precisely — Every patient, every session, based on genuine dry weight
assessment.
● 4. Apply Standard Precautions Consistently — Regardless of how well you know the patient.
● 5. Apply Isolation Protocols Rigorously — For every bloodborne pathogen-positive patient, every time.
● 6. Monitor Vital Signs Continuously Throughout Every Session — Complications can occur without
warning.
● 7. Test Water and Dialysate Quality Per Regulatory Schedule — Without exception, without shortcuts.
● 8. Respect Patients' Accumulated Knowledge of Their Own Bodies — Their observations are genuine
clinical information.
● 9. Monitor Dialysis Adequacy Systematically — Kt/V and URR tracked per defined schedule.
● 10. Apply Individualized Anticoagulation Risk Assessment — Before every session's protocol.
● 11. Rotate Cannulation Sites Appropriately — To preserve long-term access integrity.
● 12. Respond to Every Complication Immediately — Hypotension, cramps, and rare emergencies alike.
● 13. Report Every Needle-Stick or Exposure Immediately — Without delay, without minimization.
● 14. Sustain Genuine Attentiveness Across Every Session — Resist the drift toward routine interaction.
● 15. Debrief After Every Significant Event — Consolidate learning while it is fresh.
● 16. Provide Structured Handover for Every Shift Change — SBAR or equivalent, every time.
● 17. Coordinate Genuinely with Vascular Surgery and Nephrology — No single discipline manages
access complications alone.
● 18. Support Transplant Referral for Eligible Patients — Every patient deserves this pathway explored.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 51
● 19. Report Every Near-Miss Honestly — Including your own, especially in infection control.
● 20. Continue Learning — Renal replacement therapy evidence evolves. The team that does not learn
continuously treats today's patients with yesterday's protocols.
TOP 20 DON'TS FOR THE DIALYSIS UNIT
● 1. Don't Cannulate Without Systematic Access Assessment — Familiarity is not a substitute for genuine
evaluation.
● 2. Don't Let Aseptic Technique Slip for a Familiar Patient — Every session carries the same infection
risk.
● 3. Don't Estimate Fluid Removal — Precise calculation protects against dangerous hypotension or
inadequate clearance.
● 4. Don't Bypass Standard Precautions for Convenience — Blood exposure risk is inherent to every
session.
● 5. Don't Skip Isolation Protocols Because a Patient Seems Well — Bloodborne pathogen risk doesn't
depend on appearance.
● 6. Don't Let Monitoring Lapse During a Busy Shift — Complications don't wait for convenient timing.
● 7. Don't Skip or Delay Water/Dialysate Testing — Contamination enters the bloodstream directly.
● 8. Don't Dismiss a Long-Term Patient's Reported Symptom — Years of familiarity don't reduce clinical
significance.
● 9. Don't Skip Scheduled Adequacy Monitoring — Under-dialysis has genuine, measurable long-term
consequences.
● 10. Don't Apply a Standard Anticoagulation Protocol Without Individual Risk Assessment — Bleeding
risk varies significantly.
● 11. Don't Cannulate the Same Site Repeatedly Without Rotation — This shortens access lifespan.
● 12. Don't Delay Response to a Recognized Complication — Even routine hypotension deserves prompt,
standardized action.
● 13. Don't Delay Reporting a Needle-Stick or Exposure — Post-exposure prophylaxis has a time-
sensitive window.
● 14. Don't Let Repetition Erode Genuine Attentiveness — Complacency is the real enemy in dialysis
care.
● 15. Don't Skip Team Debriefing After a Critical Event — Unprocessed events repeat their gaps.
● 16. Don't Hand Over Complex Patients Informally — Structure protects against critical omissions.
● 17. Don't Manage Access Complications in Isolation — Coordinate across every specialty involved.
● 18. Don't Overlook Transplant Referral Opportunities — This pathway can transform a patient's future.
● 19. Don't Hide or Minimize a Near-Miss — Suppressed incidents cannot drive the improvement that
prevents recurrence.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 52
● 20. Don't Practice Outside Current Renal Replacement Therapy Evidence — Personal habit or outdated
method must never override current best practice.
Dialysis Unit Golden Rules
● Assess before you cannulate — every time, regardless of familiarity.
● Apply the same rigour to session one thousand as session one — repetition is not permission for
shortcuts.
● Calculate fluid removal precisely — estimation risks genuine harm.
● Never bypass standard precautions — blood exposure risk never diminishes.
● Test water and dialysate on schedule — contamination enters the bloodstream directly.
● Respect patients' accumulated expertise — they know their own bodies best.
● Monitor adequacy systematically — under-dialysis has real consequences.
● Respond to every complication immediately — no delay, no dismissal.
● Report every near-miss — honestly, including your own.
● Never stop learning — today's renal evidence is not yesterday's.
Daily Commitment Statement
“Today, I will assess every vascular access systematically before cannulation, apply meticulous aseptic
technique without exception, calculate fluid removal precisely, apply standard precautions and isolation
protocols consistently, and treat this session with the same genuine attentiveness as the very first — because
every patient's lifeline depends on my sustained vigilance, session after session, for as long as they need it.”
The Top 20 Do's and Top 20 Don'ts are the daily professional architecture of Dialysis Unit excellence —
each shaped by the understanding that renal replacement therapy is patient safety management practiced
against the singular challenge of sustained repetition, and that there are no minor lapses when a patient's
lifeline must hold for years.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 53
CHAPTER 15: DIALYSIS UNIT PROFESSIONAL PLEDGE
Introduction
A Dialysis Unit Professional Pledge is a formal, collective commitment to uphold the highest standards of
vascular access protection, infection control discipline, and sustained vigilance across years of repeated
therapy. It serves as a daily affirmation that every cannulation performed with care, every fluid target
calculated precisely, and every precaution applied consistently is an act of professional purpose in service of a
lifeline that must hold for as long as a patient needs it.
Official Dialysis Unit Professional Pledge
“We solemnly pledge that as the Dialysis Unit team, we will fulfil our collective and individual responsibilities
with the highest standards of technical precision, sustained vigilance, and unwavering commitment to every
patient whose life depends on renal replacement therapy delivered correctly, session after session, for as long
as they need it.
We will assess every vascular access systematically before every cannulation, apply meticulous aseptic
technique without exception, and never allow the familiarity of a thousandth session to erode the rigour we
brought to the first, knowing that this access is our patient's literal lifeline and that its protection is our primary
daily responsibility.
We will calculate every fluid removal target precisely, monitor every session continuously, and apply standard
precautions and bloodborne pathogen protocols consistently for every patient, every time, knowing that this
environment carries inherent blood exposure risk that never diminishes, however routine a session may feel.
We will maintain the water treatment and dialysate quality that enters our patients' bloodstream directly,
testing rigorously per regulatory schedule and responding immediately to any deviation, knowing that this
purity standard protects patients who trust us with their blood multiple times a week, for years.
We will monitor dialysis adequacy systematically, respond immediately to every intradialytic complication, and
respect the accumulated expertise our long-term patients bring to their own care, treating them as genuine
partners rather than routine cases.
We will report every incident and near-miss honestly, resist the complacency that sustained repetition can
breed, and continuously expand our knowledge and skill, knowing that renal replacement therapy evidence
evolves and that the team that does not learn continuously treats today's patients with yesterday's protocols.
With sustained precision, unwavering infection control discipline, and genuine compassion for every patient
whose life has been permanently reorganized around this therapy, we pledge to be the Dialysis Unit team that
protects every lifeline entrusted to our care, for as long as it is needed.”
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 54
Daily Commitment Statement
“Today, we commit to assessing every vascular access before cannulation, applying meticulous aseptic
technique without exception, calculating fluid removal precisely, applying infection control protocols
consistently, and treating every session with genuine attentiveness — because every patient's lifeline depends
on our sustained vigilance, together.”
Core Values Reflected in the Pledge
1. Vascular Access as Sacred Trust
Meticulous, sustained cannulation care protecting a patient's literal lifeline.
2. Sustained Precision
Fluid calculation and clinical assessment held to the same rigour across every repeated session.
3. Infection Control Discipline
Standard precautions and isolation protocols applied consistently, never eroded by familiarity.
4. Water and Dialysate Purity
Pharmaceutical-grade quality standards for everything entering a patient's bloodstream.
5. Patient Partnership
Genuine respect for patients' accumulated knowledge of their own bodies and therapy.
6. Accountability
Every decision owned and documented; every incident honestly reviewed.
7. Continuous Learning
Renal replacement therapy evidence evolves. Professional competence requires perpetual learning.
When the Pledge Should Be Recited
● At the beginning of every new Dialysis Unit team member's appointment.
● At quality governance and morbidity/mortality review meetings.
● At NABH/JCI/CMS accreditation preparation events.
● As a periodic collective affirmation, particularly following a significant adverse event.
Dialysis Unit Oath of Sustained Vigilance
“We pledge to bring the same precision to the thousandth session as to the first — protecting every vascular
access, every drop of purified water, and every patient's trust across years of therapy that never gets to rest.”
Dialysis Unit Signature Commitment
This pledge is recited collectively by the multidisciplinary Dialysis Unit team and may be individually signed by:
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 55
Name: ___________________________
Role: Nephrologist / Dialysis Nurse / Dialysis Technician / Vascular Access Specialist / Renal Dietitian
Department: Dialysis Unit
Registration/Employee ID: _______________
Signature: ________________________
Date: ____________________________
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 56
CONCLUSION
Few therapies in medicine demand what dialysis demands of the team delivering it: not a single moment of
decisive excellence, but sustained excellence repeated three or more times a week, for years, sometimes for
an entire remaining lifetime. The genuine challenge of this discipline is not, in the end, technical complexity —
it is resistance to the complacency that any task performed thousands of times can breed. A vascular access
cannulated correctly nine hundred times can still be damaged by carelessness on the nine hundred and first.
This manual has returned, again and again, to a single principle: the same rigour applied to the first session
must be applied to every session that follows, for as long as a patient depends on this therapy.
Throughout this manual, we have explored the full scope of Dialysis Unit professional practice — from vascular
access assessment and meticulous cannulation, through dialysis adequacy monitoring, fluid management, and
bloodborne pathogen infection control, to water treatment quality assurance, intradialytic complication
response, and the professional conduct that defines excellence across a therapy delivered repeatedly across
years. These responsibilities collectively define a discipline that demands both exacting technical precision and
a genuinely sustained partnership with patients whose lives have been permanently reorganized around this
treatment.
The Importance of the Dialysis Unit Team in Healthcare Quality
● The lifeline protector — sustaining vascular access integrity through meticulous cannulation across
hundreds of repeated sessions.
● The precision practitioner — calculating every fluid removal target exactly, session after session,
without deviation.
● The infection control guardian — maintaining rigorous bloodborne pathogen precautions in an
environment of inherent blood exposure.
● The purity keeper — ensuring water and dialysate quality meets pharmaceutical-grade standards for
direct bloodstream entry.
● The complacency resistor — bringing the same rigour to the thousandth session as to the first.
● The sustained partner — supporting patients through a permanent, lifelong reorganization of their
existence around this therapy.
Final Commitment
“As the Dialysis Unit team, we commit to assessing every vascular access systematically, applying meticulous
aseptic technique without exception, calculating fluid removal precisely, maintaining rigorous infection control,
and upholding every safety standard without deviation — because every patient's lifeline depends on the same
vigilance we bring to session one thousand as to session one.”
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 57
Final Motto
“Three Times a Week, for Years, We Become the Kidneys That No Longer Work — Every Access Protected,
Every Session Precise, Every Patient's Life Sustained.”
Together, We Sustain What the Body No Longer Can — Ensuring Every Lifeline Holds, Every Session
Counts, and Every Patient Lives Fully.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 58
REFERENCES
Global Accreditation and Regulatory Standards
● World Health Organization (WHO) – Guidelines on Infection Prevention and Control in Dialysis Settings.
● Joint Commission International (JCI) – JCI Accreditation Standards for Hospitals: Care of Patients (COP)
Chapter, including Dialysis Care Requirements.
● National Accreditation Board for Hospitals & Healthcare Providers (NABH, India) – Standards for
Dialysis Unit Services (5th Edition).
● Centers for Medicare & Medicaid Services (CMS, US) – Conditions for Coverage for End-Stage Renal
Disease Facilities.
Clinical Practice Guidelines for Renal Replacement Therapy
● Kidney Disease: Improving Global Outcomes (KDIGO) – Clinical Practice Guidelines for Chronic Kidney
Disease and Dialysis.
● Kidney Disease Outcomes Quality Initiative (KDOQI) – Clinical Practice Guidelines for Hemodialysis and
Vascular Access.
● International Society of Nephrology (ISN) – Global Kidney Health Guidelines.
Vascular Access Standards
● KDOQI – Clinical Practice Guideline for Vascular Access.
● Vascular Access Society – Guidelines on Arteriovenous Fistula and Graft Creation and Cannulation
Technique.
Infection Control and Bloodborne Pathogen Standards
● Centers for Disease Control and Prevention (CDC) – Recommendations for Preventing Transmission of
Infections Among Chronic Hemodialysis Patients.
● Association for Professionals in Infection Control and Epidemiology (APIC) – Guide to Infection
Prevention in Hemodialysis Settings.
Water Treatment and Dialysate Quality Standards
● Association for the Advancement of Medical Instrumentation (AAMI) – Standards for Water Treatment
and Dialysate Quality for Hemodialysis.
● International Organization for Standardization (ISO) – ISO 23500 Standards for Preparation of Dialysis
Fluids.
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 59
Dialysis Adequacy and Nutritional Standards
● KDOQI – Clinical Practice Guideline for Hemodialysis Adequacy.
● KDOQI – Clinical Practice Guideline for Nutrition in Chronic Kidney Disease.
● KDIGO – Clinical Practice Guideline for the Diagnosis, Evaluation, Prevention, and Treatment of CKD-
Mineral and Bone Disorder (CKD-MBD).
Indian Regulatory and National Framework
● Indian Society of Nephrology (ISN-India) – Clinical Practice Guidelines for Dialysis Care.
● Ministry of Health and Family Welfare, Government of India – Pradhan Mantri National Dialysis
Programme Operational Guidelines.
● National Medical Commission (NMC) – Code of Medical Ethics Regulations Applicable to Nephrology
Care.
● Clinical Establishments (Registration and Regulation) Act, India – Applicable Dialysis Facility Regulatory
Requirements.
Quality Improvement and Patient Safety Frameworks
● Institute for Healthcare Improvement (IHI) – Framework for Patient Safety and Quality Improvement
in Dialysis Care.
● World Health Organization – Global Patient Safety Action Plan 2021–2030.
● United States Renal Data System (USRDS) – Benchmarking and Outcomes Reporting Standards.
Cybersecurity and Digital Health Records
● NIST Cybersecurity Framework – Applied to Healthcare Dialysis Information Systems.
● HL7 International – Health Level Seven Data Interchange Standards.
This manual has been developed using internationally recognized principles and best practices from WHO
Infection Prevention Guidelines for Dialysis Settings, JCI Care of Patients Standards, NABH Dialysis Unit
Standards, CMS Conditions for Coverage for ESRD Facilities, KDIGO and KDOQI Clinical Practice Guidelines,
AAMI/ISO Water Treatment and Dialysate Quality Standards, CDC Bloodborne Pathogen Prevention Guidelines,
Indian Society of Nephrology Guidelines, the Pradhan Mantri National Dialysis Programme, and applicable
Indian statutory and regulatory requirements. Institutions should verify current versions of all cited guidelines
and regulatory requirements, as clinical protocols and accreditation standards are subject to periodic revision.
ॐ जय माता द( ॐ
Dialysis Unit Excellence Manual Dr J L Meena
Dialysis Unit Excellence Manual – Dr J L Meena | Page 60
END OF MANUAL
Thank You
This manual has been prepared with the vision to empower the multidisciplinary Dialysis Unit team with global
standards, best practices, and professional guidance to ensure safe, precise, and sustained care for every
patient dependent on renal replacement therapy.
Our Commitment Continues
The journey of learning never ends. As renal replacement therapy evidence evolves and dialysis science
advances, our commitment to patient safety, precision, infection control, and compassion must remain
unwavering — across every session, for as long as our patients need us.
Together, We Build Trust
Every vascular access protected, every fluid target calculated precisely, every precaution applied consistently,
and every patient treated with genuine, sustained attentiveness contributes to one greater purpose — a lifeline
that holds, session after session, for years of life this unit's vigilance makes possible.
“Three Times a Week, for Years, We Become the Kidneys That No Longer Work — Every Access
Protected, Every Session Precise, Every Patient's Life Sustained.”
REMEMBER: Safety is our priority • Precision is our discipline • Consistency is our standard • The access is
our trust • Learning is our journey
Thank you for being a part of this vital mission. Your dedication makes a difference every day.
Dr J L Meena