Dental Implant
Screw Loosening
WhyIt Happens, How to Prevent It, and How to Manage It
Ev i d ence- B as ed Cl i n i ca l U p date
Question: Can implant screws ever be permanently tightened?
No. Every screw begins losing preload immediately after tightening.
2.
Why Should WeCare?
Screw Loosening Remains a Common Complication
Mechanical Complication Mean Incidence (Goodacre et
al., 2003)
Prosthesis screw loosening 7%
Abutment screw loosening 6%
Clinical Consequences
Prosthesis mobility
Patient dissatisfaction
Plaque accumulation
Peri-implant inflammation
Screw fracture
Abutment fracture
Implant fracture
26%
of abutment screws require retightening after Year 1
Reference: Goodacre CJ et al. J Prosthet Dent. 2003;90:121–132.
3.
The Mechanism —The Entire Story
Torque Applied
Screw Elongation
Preload Generated
Functional Loading
Preload Loss
Micromotion
Screw Loosening
Screw Fracture
Key Message
Screw loosening is a manifestation of
preload loss.
Every phase of the cascade from torque application to screw fracture
is preventable if preload is optimally generated and maintained
throughout the prosthetic lifecycle.
Clinical Diagram: Implant–Abutment–Crown Complex
(Torque → Preload → Functional Failure Cascade)
Reference: Haack JE et al. Int J Oral Maxillofac Implants. 1995;10(5):529–536.
4.
Understanding Preload —The Most Important Concept
Preload Defined
The clamping force that holds the implant body and
abutment in intimate contact at the implant–abutment
interface.
Preload Torque (via screw elongation)
∝
Optimal Preload = ~75% of screw yield strength
Below this → insufficient clamping. Above → plastic deformation &
fracture.
Factors Affecting Preload
Applied Torque
Primary driver of preload magnitude
Screw Material
Ti vs. gold vs. steel alloys
Thread Geometry
Pitch, depth, engagement length
Surface Roughness
Asperities cause settling loss
Friction Coefficient
Between mating surfaces
Reference: Haack JE et al. 1995.
5.
Applied Torque &The Settling Effect
Applied Torque
20 Ncm
↓ Increasing torque ↓
30 Ncm
Results in:
Greater screw elongation
Greater preload generated
Greater resistance to loosening
Settling Effect (Embedment Relaxation)
Microscopic surface irregularities flatten under load —
causing immediate preload loss.
2–10% preload loss within minutes after
tightening
Clinical Protocol:
1 Torque to target (manufacturer spec)
2 Wait 5–10 minutes
3 Re-torque to restore lost preload
Use calibrated torque wrench
Never rely on hand tightening
References: Haack 1995; Breeding 1993; Siamos 2002.
6.
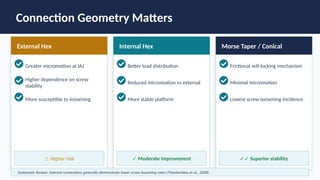
Connection Geometry Matters
ExternalHex
Greater micromotion at IAJ
Higher dependence on screw
stability
More susceptible to loosening
⚠ Higher risk
Internal Hex
Better load distribution
Reduced micromotion vs external
More stable platform
✓ Moderate improvement
Morse Taper / Conical
Frictional self-locking mechanism
Minimal micromotion
Lowest screw loosening incidence
✓✓ Superior stability
Systematic Review: Internal connections generally demonstrate lower screw loosening rates (Theoharidou et al., 2008).
7.
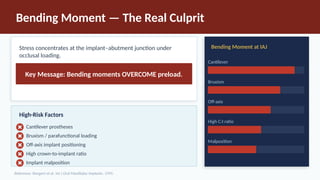
Bending Moment —The Real Culprit
Stress concentrates at the implant–abutment junction under
occlusal loading.
Key Message: Bending moments OVERCOME preload.
High-Risk Factors
Cantilever prostheses
Bruxism / parafunctional loading
Off-axis implant positioning
High crown-to-implant ratio
Implant malposition
Bending Moment at IAJ
Cantilever
Bruxism
Off-axis
High C:I ratio
Malposition
Reference: Rangert et al. Int J Oral Maxillofac Implants. 1995.
8.
High-Risk Clinical Situations
WhenScrew Loosening Is Most Likely
Single Implant
Molar Crowns
The most frequently reported scenario.
Molar region experiences the highest
occlusal forces.
High Bruxers &
Parafunctional
Cyclic overloading exceeds design
parameters. Bruxism associated with
increased technical complications.
Very High Short Implants
(<8 mm)
Higher stress concentration at the implant–
abutment interface. Less bone-implant
contact.
High
Narrow Diameter
Implants
Reduced resistance to bending forces. More susceptible to lateral
loading.
High Cantilever
Prostheses
Magnifies bending moments exponentially. The single highest-risk
prosthetic design.
Extreme
Reference: Lobbezoo F et al. J Oral Rehabil. 2006; Goodacre CJ et al. 2003.
9.
Prosthetic Design CanPrevent Loosening
Implant-Protected Occlusion
REDUCE
Cuspal inclination
Reduces lateral forces on the implant
Occlusal table width
Dykema's Principle: reduce by up to 40% buccolingually
Cantilever length
Every mm of cantilever magnifies bending
CENTRALIZE
Occlusal contacts
Fossa contacts preferred; minimize cusp tips
Axial loading
Direct forces along implant long axis
Clinical Pearl
Narrow occlusal tables reduce
shearing forces on retaining
screws.
Dykema's Principle
Reduce buccolingual width of the
implant crown by up to 40%
compared to the natural tooth.
Night Guards
Mandatory for confirmed bruxers to
reduce cyclic loading.
Reference: Misch CE. Contemporary Implant Dentistry. 4th ed. Elsevier; 2020.
10.
Clinical Management Algorithm:"My Implant Is Loose"
1 Determine What Is Loose
Crown? Abutment? Implant? Careful
clinical exam first.
2 Radiograph & Assessment
Check for abutment gap, screw fracture,
bone loss, or prosthetic misfit.
3 Remove & Inspect
Remove restoration. Inspect screw
threads, internal connection, and
titanium surfaces.
4 Clean the Connection
Eliminate blood, debris, old cement. Use
appropriate irrigation.
5 Retorque
Follow manufacturer's torque
specification with calibrated wrench.
Wait 5–10 min, then retorque.
6 Adjust Occlusion
Check and correct occlusal contacts in
centric and excursions.
Reference: Goodacre CJ et al. J Prosthet Dent. 2003.
11.
When Should YouReplace the Screw?
Replace the Screw If …
Multiple loosening episodes (recurrent)
Thread wear observed on inspection
Screw head distortion visible
Any visible deformation of the screw body
Evidence of metal fatigue (surface cracking)
Critical Warning
Repeated loosening often PRECEDES
fracture.
Never Continue Retightening
Indefinitely
A repeatedly loosening screw is a warning
sign of inadequate preload or excessive
bending — address the cause, not just the
symptom.
Treat recurrent loosening as a prosthetic red flag requiring full occlusal re-evaluation and implant status assessment.
12.
Prevention Checklist —Before Final Prosthesis Delivery
Confirm complete seating radiographically Seating
Clean implant connection (blood, debris, cement) Cleaning
Use calibrated torque wrench to manufacturer specTorque
Retorque after 5–10 minute wait (settling effect) Torque
Narrow occlusal table (reduce by up to 40%) Occlusion
Reduce cusp inclination and sharp cusp tips Occlusion
Eliminate cantilever extensions where possible Design
Prescribe night guard for confirmed bruxers Bruxism
Replace repeatedly loosened screws
Maintena
nce
13.
Take-Home Messages
1 Lossof preload is the primary mechanism of screw loosening.
Every clinical decision should preserve or restore preload.
2 Settling effect explains why retorquing is mandatory.
Torque → wait 5–10 min → retorque. Non-negotiable.
3 Internal conical connections resist loosening best.
Choose connection geometry informed by evidence.
4 Control bending moments through occlusion & design.
Occlusal table, cantilever, and implant axis all matter.
5 Recurrent loosening is a warning sign — not just a screw problem.
Investigate the cause: overload, misfit, or system failure.
Evidence-Based Clinical Update | Dental Implant Screw Loosening
14.
Final Discussion —Clinical Decision
Which Is More Important?
A. Tighten harder
Increasing torque beyond optimal range leads to:
• Screw plastic deformation
• Thread stripping
• Screw fracture
This is NOT the answer.
VS
B. Preserve preload & minimize bending
This is the central principle underlying ALL
prevention and management of implant screw
loosening.
• Use calibrated torque
• Retorque after settling
• Minimize bending moments
• Design for axial loading
Answer: B — Preserving preload and minimizing bending moments is the central principle underlying all
prevention and management of implant screw loosening.
15.
References (Vancouver Style)
GoodacreCJ, Bernal G, Rungcharassaeng K, Kan JYK. Clinical complications with implants and implant prostheses. J Prosthet Dent. 2003;90(2):121–132.
Haack JE, Sakaguchi RL, Sun T, Coffey JP. Elongation and preload stress in dental implant abutment screws. Int J Oral Maxillofac Implants. 1995;10(5):529–536.
Breeding LC, Dixon DL, Sadler JP, McKay ML. Mechanical considerations for the implant tooth-abutment connection. J Prosthet Dent. 1993;70(6):510–513.
Siamos G, Winkler S, Boberick KG. Relationship between implant preload and screw loosening on implant-supported prostheses. J Oral Implantol.
2002;28(2):67–73.
Theoharidou A, Petridis HP, Tzannas K, Garefis P. Abutment screw loosening in single-implant restorations: a systematic review. Int J Oral Maxillofac Implants.
2008;23(4):681–690.
Rangert B, Krogh PH, Langer B, Van Roekel N. Bending overload and implant fracture. Int J Oral Maxillofac Implants. 1995;10(3):326–334.
Lobbezoo F, Brouwers JEIG, Cune MS, Naeije M. Dental implants in patients with bruxing habits. J Oral Rehabil. 2006;33(2):152–159.
Jung RE et al. Systematic review of survival and complications of single crowns on implants. Clin Oral Implants Res. 2012;23(Suppl 6):2–21.
Pjetursson BE et al. Comparison of tooth-supported and implant-supported FDPs. Clin Oral Implants Res. 2007;18(Suppl 3):97–113.
Misch CE. Contemporary Implant Dentistry. 4th ed. Elsevier; 2020.
Misch CE. Dental Implant Prosthetics. 3rd ed. Elsevier; 2021.

 Most read