4
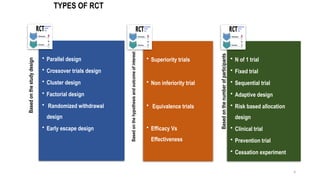
TYPES OF RCT
Based
on
the
study
design
•Parallel design
• Crossover trials design
• Cluster design
• Factorial design
• Randomized withdrawal
design
• Early escape design
Based
on
the
hypothesis
and
outcome
of
interest
• Superiority trials
• Non inferiority trial
• Equivalence trials
• Efficacy Vs
Effectiveness
Based
on
the
number
of
participants
• N of 1 trial
• Fixed trial
• Sequential trial
• Adaptive design
• Risk based allocation
design
• Clinical trial
• Prevention trial
• Cessation experiment
5.
5
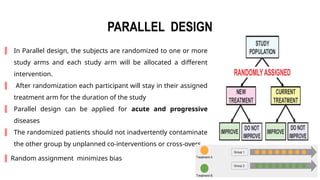
PARALLEL DESIGN
║ InParallel design, the subjects are randomized to one or more
study arms and each study arm will be allocated a different
intervention.
║ After randomization each participant will stay in their assigned
treatment arm for the duration of the study
║ Parallel design can be applied for acute and progressive
diseases
║ The randomized patients should not inadvertently contaminate
the other group by unplanned co‑interventions or cross‑overs.
║ Random assignment minimizes bias
6.
Wagh M, MukhiJ, Sontakke S, Dhok A, Turankar A, Kalikar M. Comparative evaluation of efficacy and
tolerability of apremilast and methotrexate in patients of moderate-to-severe palmoplantar
psoriasis: A randomized, parallel, open-label clinical trial. Indian J Pharmacol. 2023 Nov-Dec;55(6):356-362.
doi: 10.4103/ijp.ijp_190_23. PMID: 38174531; PMCID: PMC10821693.
The study was a randomized, prospective, parallel-group, open-label study conducted in patients with
moderate-to-severe palmoplantar psoriasis.
They were randomized into two groups, methotrexate (n = 19) or apremilast (22) for 16 weeks.
Primary efficacy parameter was reduction in modified palmoplantar psoriasis area and severity index
(mPPPASI) score from week 0 to week 16.
7.
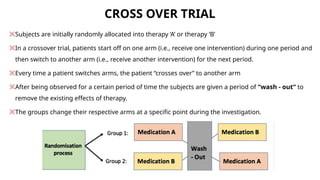
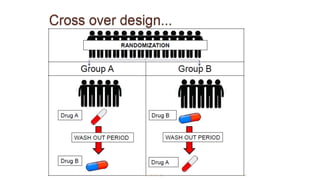
CROSS OVER TRIAL
Subjectsare initially randomly allocated into therapy ‘A’ or therapy ‘B’
In a crossover trial, patients start off on one arm (i.e., receive one intervention) during one period and
then switch to another arm (i.e., receive another intervention) for the next period.
Every time a patient switches arms, the patient “crosses over” to another arm
After being observed for a certain period of time the subjects are given a period of “wash - out” to
remove the existing effects of therapy.
The groups change their respective arms at a specific point during the investigation.
9.
9
PRE REQUISITES OFCROSS OVER DESIGN
Disease – chronic (asthma, osteoarthritis) stable
Drugs with relatively short half-life & short treatment periods are considered
Effects of drug should develop fully within treatment period
Washout periods -sufficiently long for complete reversibility of drug effect
Wash out period- five half lives of drug
10.
10
• Treatment sequencingand patient assignment: The sequence in which
treatments are administered should ideally be assigned randomly. This protects
against conscious and unconscious bias by ensuring that there are no
systematic differences between patients receiving A/B versus B/A.
• Crossover rules and timing of measurements:
Time-dependent -the treatment switch takes place after a specified length of
time),
Disease-state dependent -the treatment switch is determined by the clinical
characteristics of the patient
11.
Crossover designs maybe used in clinical trials
in the following situations where
1. Objective measures and interpretable data
for both efficacy and safety are obtained.
2. Chronic (relatively stable) disease are
under study.
3. Prophylactic drugs with relatively short
half-life are being investigated.
4. Relatively short treatment periods are
considered.
5. Baseline and washout periods are feasible.
12.
12
CROSS OVER TRIAL-STRENGTHS
Each patient serves as his own control reduces the confounding covariates
Each patient gets both drugs but the order in which the patient gets each drug is
randomized
Removes “patient effect ”thereby reducing variability and increasing precision of
estimation
Requires a small sample size
Under assumption of no carryover effect, design provides more information than
simple parallel design
13.
CROSS OVER TRIAL-LIMITATIONS
Crossover trials can only be conducted on chronic diseases persists for a longer
period
There might be a carry-over effect of the previous intervention on to the effect
of the next intervention ,interactions between treatment and
study-period/sequence.
Statistical tests have been suggested in order to test the carry-over risk, but a
great chance of a type-II error persists.
It is difficult to estimate the time required in order for the intervention to be
fully washed-out.
14.
CARRY OVER EFFECTS& WASH OUT PERIOD
• A carryover effect is defined as the effect of the treatment from the previous time
period on the response at the current time period and may yiels statistical bias
• The incorporation of lengthy washout periods in the experimental design can
diminish the impact of carryover effects.
• A washout period is defined as the time between treatment periods. Instead of
immediately stopping and then starting the new treatment, there will be a period
of time where the treatment from the first period where the drug is washed out of
the patient's system.
• The length of the washout period usually is determined as some multiple of the
half-life of the pharmaceutical product within the population of interest equivalent
to 5 (or more) times the length of the half-life of the drug concentration in the
blood
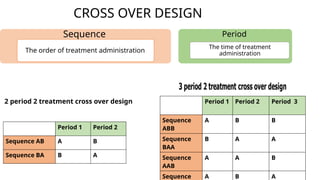
CROSS OVER DESIGN
Sequence
Theorder of treatment administration
Period
The time of treatment
administration
Period 1 Period 2
Sequence AB A B
Sequence BA B A
2 period 2 treatment cross over design Period 1 Period 2 Period 3
Sequence
ABB
A B B
Sequence
BAA
B A A
Sequence
AAB
A A B
Sequence A B A
21.
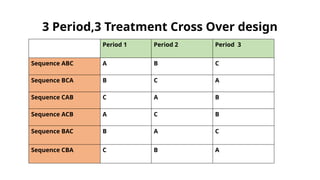
3 Period,3 TreatmentCross Over design
Period 1 Period 2 Period 3
Sequence ABC A B C
Sequence BCA B C A
Sequence CAB C A B
Sequence ACB A C B
Sequence BAC B A C
Sequence CBA C B A
22.
CROSS OVER DESIGNBASED ON UNIFORMITY
• Uniform within sequence
Each treatment appears the same number of times within each sequence
• Uniform within period
Each treatment appears the same number of times within each period
Based on uniformity
Latin square design
23.
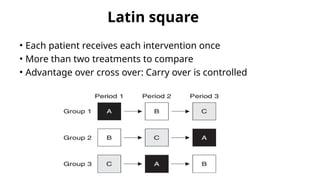
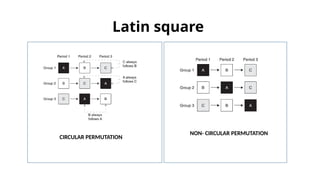
Latin square
• Eachpatient receives each intervention once
• More than two treatments to compare
• Advantage over cross over: Carry over is controlled
24.
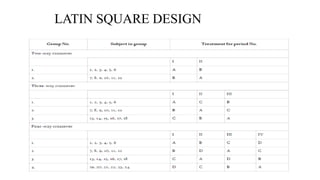
LATIN SQUARE DESIGN
•The Latin-square design plans the clinical trial so that each subject receives each drug
product only once, with adequate time between medications for the elimination of the drug
from the body.
• In this design, each subject is his own control, and subject-to-subject variation is reduced.
• Moreover, variation due to sequence, period, and treatment (formulation) are reduced, so
that all patients do not receive the same drug product on the same day and in the same
order.
• Possible carryover effects from any particular drug product are minimized by changing the
sequence or order in which the drug products are given to the subject.
• Thus, drug product B may be followed by drug product A, D, or C .
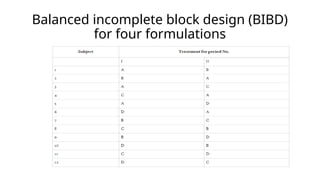
Incomplete block design(BIBD)
• More than 3 formulations, Latin square design will not be ethically advisable.
Because each volunteer may require drawing of too many blood samples. If each
volunteer expected to receive at least two formulation, then such a study can be
carried out using BIBD.
• It eliminates many of the difficulties encountered with the Latin square design.
• In this, each subject receives not more than two formulations, each formulation is
administered the same number of times and each pair of formulations occurs
together in the same number of subjects.
• In this design, as discussed above, each subject receives two formulations, each
formulation is administered six times and each pair of formulations occurs together
in two subjects (the pairs are AB, AC, AD, BC, BD, and CD).
Replicate Crossover-study design
•For highly variable drugs.
• It allows comparisons of within-subject variances.
• It reduces the number of subjects needed.
• Four-period, two-sequence, two-formulation design (recommended) or Three-
sequence, three-period, single-dose, partially replicated.
• Replicated crossover designs are used for the determination of individual
bioequivalence, to estimate within-subject variance for both the Test and
Reference drug products, and to provide an estimate of the subject-by-
formulation interaction variance.
• Generally, a four-period, two-sequence, two-formulation design is recommended
by the FDA.
30.
PERIOD 1 23 4
GROUP 1 T R T R
GROUP 2 R T R T
Where,
R = reference
T = treatment
The same reference and the same test are each given twice to the same
subject. Other sequences are possible. In this design, Reference-to-
Reference and Test-to-Test comparisons may also be made.
Impact of ReplacingSmear Microscopy with Xpert MTB/RIF for Diagnosing
Tuberculosis in Brazil: A Stepped-Wedge Cluster-Randomized Trial . PLoS Med.
2014 Dec; 11(12): e1001766.
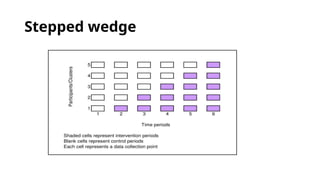
Stepped-wedge design with 14 clusters (study laboratories with serviced clinics)
and eight monthly measurement periods.
Replacing smear microscopy with Xpert MTB/RIF in Brazil increased confirmation
of pulmonary TB
33.
Stepped wedge
Strengths:
• Efficiency:Units act as their own control, so fewer units needed
(same as cross-over design)
• Power is relatively insensitive to Coefficient of variation
• Power can be maximize the number of steps
• Logistical or financial - cannot introduce the intervention in all
units at once
• Evaluate the community effectiveness of an intervention
previously shown to be efficacious in an individually randomized
trial or in a different setting
• Systematically evaluate new program
• To study the effect of time on intervention effectiveness (i.e.
seasonality, time since introduction)
Limitations
• Intervals should be long
enough to capture the full
treatment effect
• Multiple data collection
points required
• Effect of variation with
time
• Complex data analysis
24/03/2025 35
WILLIAMS DESIGN
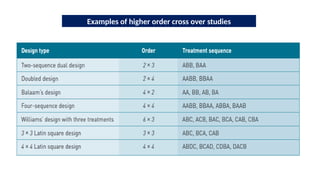
Whenthere are more than two treatments to be compared, a
complete crossover design is called William’s design.
I. William’s design with three treatments
ACB BAC CBA
BCA CAB ABC
II. William’s design with four treatments
ADBC BACD CBDA DCAB
36.
36
N of 1trial
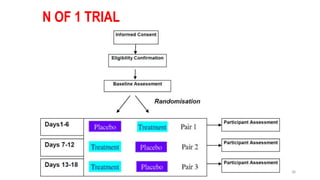
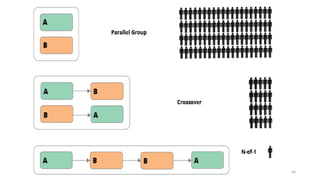
Multiple crossover trials, usually randomized and blinded, conducted in a single
patient.
N-of-1 trials are a specific form of randomized designs characterized by periodic
switching from active treatment to placebo or between active treatments(("withdrawal-
reversal" designs)
Done when there is doubt about whether a treatment is really providing benefit to the
patient.
By prescribing multiple episodes of treatment, n-of-1 trials increase precision of
measurement and control for treatment-by-time interaction
37.
N of 1design
• Indications :
• Substantial clinical uncertainty
• Chronic or frequently recurring symptomatic condition
• Treatment with rapid onset and minimal carryover
• Contraindications :
• Rapidly progressive condition
• Treatment with slow onset or prolonged carryover
• Patient or clinician insufficiently interested in reducing therapeutic uncertainty to justify
effort
40
SERIAL CONTROLLED N-OF-1TRIALS OF TOPICAL
VITAMIN E AS PROPHYLAXIS FOR CHEMOTHERAPY-
INDUCED ORAL MUCOSITIS IN PAEDIATRIC PATIENTS.
Sung L1
, Tomlinson GA, Greenberg ML, Koren G, Judd P, Ota S, Feldman BM
40.
24/03/2025 41
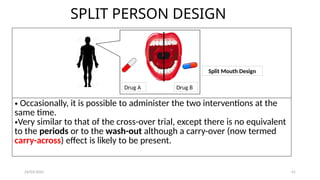
SPLIT PERSONDESIGN
• Occasionally, it is possible to administer the two interventions at the
same time.
•Very similar to that of the cross-over trial, except there is no equivalent
to the periods or to the wash-out although a carry-over (now termed
carry-across) effect is likely to be present.
Drug A Drug B
Split Mouth Design
41.
24/03/2025 42
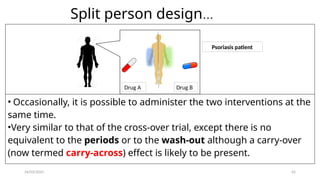
Split persondesign...
Drug A Drug B
Psoriasis patient
• Occasionally, it is possible to administer the two interventions at the
same time.
•Very similar to that of the cross-over trial, except there is no
equivalent to the periods or to the wash-out although a carry-over
(now termed carry-across) effect is likely to be present.
42.
24/03/2025 43
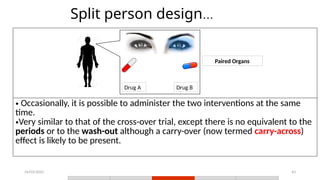
Split persondesign...
• Occasionally, it is possible to administer the two interventions at the same
time.
•Very similar to that of the cross-over trial, except there is no equivalent to the
periods or to the wash-out although a carry-over (now termed carry-across)
effect is likely to be present.
Drug A Drug B
Paired Organs
43.
High-dose Valacyclovir DecreasesPlasma HIV-1 RNA More Than Standard-dose Acyclovir in
HIV-1, HSV-2 Positive Persons: a Randomized, Crossover Trial.
J Acquir Immune Defic Syndr. 2013 Jun 1; 63(2): 201–208.
Valacyclovir 1000 mg twice daily or Acyclovir 400 mg twice daily for 12 weeks, followed by a two week
washout
HSV DNA was measured from daily self-collected genital swabs for the initial 4 weeks of each arm and
HIV-1 RNA was quantified from weekly plasma samples
High-dose valacyclovir reduces plasma HIV-1 RNA levels more than standard-dose acyclovir in HIV-1/HSV-2
seropositive persons not receiving antiretroviral therapy
44.
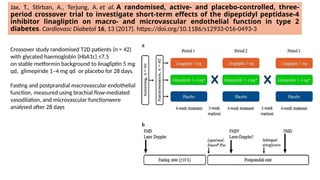
Jax, T., Stirban,A., Terjung, A. et al. A randomised, active- and placebo-controlled, three-
period crossover trial to investigate short-term effects of the dipeptidyl peptidase-4
inhibitor linagliptin on macro- and microvascular endothelial function in type 2
diabetes. Cardiovasc Diabetol 16, 13 (2017). https://doi.org/10.1186/s12933-016-0493-3
Crossover study randomised T2D patients (n = 42)
with glycated haemoglobin (HbA1c) ≤7.5
on stable metformin background to linagliptin 5 mg
qd, glimepiride 1–4 mg qd or placebo for 28 days.
Fasting and postprandial macrovascular endothelial
function, measured using brachial flow-mediated
vasodilation, and microvascular functionwere
analysed after 28 days
45.
46
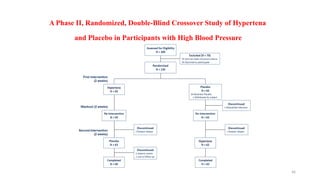
A Phase II,Randomized, Double-Blind Crossover Study of Hypertena
and Placebo in Participants with High Blood Pressure
46.
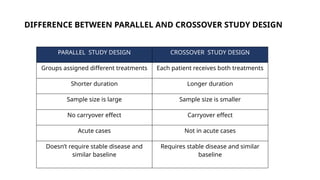
DIFFERENCE BETWEEN PARALLELAND CROSSOVER STUDY DESIGN
PARALLEL STUDY DESIGN CROSSOVER STUDY DESIGN
Groups assigned different treatments Each patient receives both treatments
Shorter duration Longer duration
Sample size is large Sample size is smaller
No carryover effect Carryover effect
Acute cases Not in acute cases
Doesn’t require stable disease and
similar baseline
Requires stable disease and similar
baseline
49
ADVANTAGES OF CROSSOVER TRIALS
• Patient effect – reduces inter patient variability since same patient serves as control and
increases precision of estimation
• Requires less sample size
• Provides unbiased result with proper randomization
• Improves on the ethical considerations since all subjects are exposed to both therapies at
some point
• Applied for phase I and phase II studies
49.
50
DISADVANTAGES OF CROSSOVER TRAILS
• Carryover effect-the effect of a treatment in one period may carry over into the next period.
• Period effect- patients vary from one period to another. The disease may naturally
progress, regress, or fluctuate in severity.
• Not useful for acute disease
• Needs to determine appropriate length of washout period
• Blinding – subjects able to compare drugs
• Assessing adverse events
• High dropout rates
• Not suitable for Behavioral/educational interventions
• The order in which the therapies are given may elicit psychological response
Editor's Notes
#2 1948:First published RCT on Streptomycin Treatment of Pulmonary Tuberculosis
#7 A crossover design is a modified randomized block design in which each block receives >1 treatment at different dosing periods.
patient A is randomized to receive Treatment #1 for a period of time. After completing Treatment #1, the patient then “crosses over” and receives Treatment #2. Usually between treatments is a period of time called a washout when no treatment is delivered. Outcomes are examined during and/or after each treatment.
#8 A researcher wants to compare the efficacy of the drug Valsartan with Losartan, both given to treat high blood pressure BUT fears there might be a substantial risk of confounding
She recruits 120 participants into her study and randomly allocates them into 60 participants in group A and 60 participants in group B.
At first, participants in group A will receive Valsartan for two weeks and group B will receive Losartan for a period of two weeks.
There will be a wash-out period of 4 weeks in which the study participants will not receive Losartan or Valsartan.
After that, group A will receive Iosartan for two weeks and group B will receive Valsartan for two weeks.
#12 Opportunity to receive both treatments (or be assured of receiving active treatment at some point) is attractive to patients
#13 There are some short-term illnesses or acute conditions that might be cured once they are treated and there are treatments that will have a permanent effect (i.e. surgery) on the patient. It is usually not possible to perform crossover trials in such cases.
crossover trials are mostly used in studying chronic diseases
type-II error (falsely accepting the null hypothesis, here: falsely accepting the hypothesis that there is no interaction between treatment and study-period or study-group) persists
While it might be relatively simple to estimate the wash-out period when the intervention is given as a drug looking at the half-life of the studied medications, things become a lot trickier when the interventions include psychological therapies, for example.
#14 An example is when a pharmaceutical treatment causes permanent liver damage so that the patients metabolize future drugs differently. Another example occurs if the treatments are different types of educational tests. Then subjects may be affected permanently by what they learned during the first period.
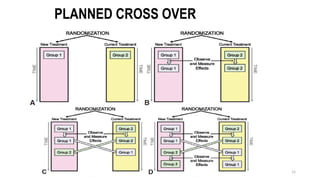
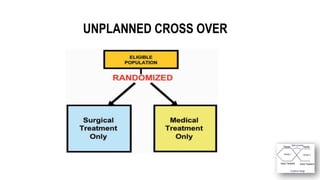
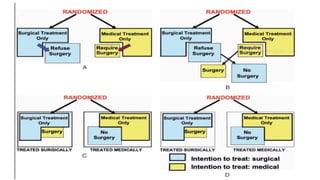
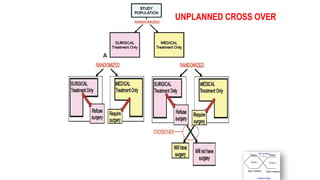
#17 In a trial to assess the efficacy of surgical Vs medical treatment in IHD
Some patients initially randomly allocated to surgical
or medical options, may start having second thoughts and
may decide to finally take the other form of therapy to which
they were originally not allocated;
or
Some patients initially allocated to medical group may deteriorate and may then be given surgery. Such crossovers may lead to serious objections as regards the validity of the trial.
#24 For randomizations of treatments in Latin squares, For the comparison of two formulations, a 2 X 2 Latin square (N = 2) consists of two patients each taking two formulations (A and B) on two different occasions in two “orders”.
The balancing of order (A-B or B-A) takes care of time trends or other ‘‘period’’ effects, if present. (A period effect is a difference in response due to the occasion on which the treatment is given, independent of the effect due to the treatment).
The 2 X 2 Latin square shown above is familiar to all who have been involved in bioavailability/bioequivalence studies. In these studies, the 2 X 2 Latin square is repeated several times to include a sufficient number of patients. Thus the crossover design can be thought of as a repetition of the 2 X 2 Latin square.
#26 The time intervals should be spaced so that the peak blood concentration, the total area under the curve, and the absorption and elimination phases of the curve may be well described.
The crossover design is a type of Latin square. In a Latin square the number of treatments equals the number of patients.
In addition, another factor, such as order of treatment, is included in the experiment in a balanced way.
The net result is an N X N array (where N is the number of treatments or patients) of N letters such that a given letter appears only once in a given row or column. This is most easily shown pictoriall
#31 the order in which the intervention is received is randomised
#49 There is no guarantee that washout periods will completely control for carryover effects.
Long washout periods might unavoidably increase the duration of the experiment.
Ethical concerns (how long can a patient be refused treatment during a washout period) and incomplete knowledge (what washout
period length is sufficient) may sometimes lead to inadequate washout periods.
Within each unit, or patient, responses to therapy are likely to be correlated (eg, a single patient’s response to treatment A is correlated with that patient’s response to treatment B; the responses are not independent). This causes complexities in both the design and the analysis
#50 There is no guarantee that washout periods will completely control for carryover effects.
Long washout periods might unavoidably increase the duration of the experiment.
Ethical concerns (how long can a patient be refused treatment during a washout period) and incomplete knowledge (what washout
period length is sufficient) may sometimes lead to inadequate washout periods.
Within each unit, or patient, responses to therapy are likely to be correlated (eg, a single patient’s response to treatment A is correlated with that patient’s response to treatment B; the responses are not independent). This causes complexities in both the design and the analysis
Finally, if either of the therapy cures
the disease in toto (as an antibiotic for infectious disease) then,
naturally, no cross over can be done.