Critical Probing Depths in Periodontal Therapy: Surgical vs Non-Surgical Outcomes
Analysis of critical probing depths in periodontal treatment comparing modified Widman flap surgery and scaling/root planing, highlighting effects on attachment levels and importance of plaque control during maintenance.
Critical Probing Depths in Periodontal Therapy: Surgical vs Non-Surgical Outcomes
1.
J O UR N A L C L U B P R E S E N TAT I O N
Department of Periodontology
“Critical Probing Depths”
in Periodontal Therapy
Lindhe J, Socransky SS, Nyman S, Haffajee A, Westfelt E — J Clin Periodontol 1982; 9: 323–336
GUIDED BY
Dr. [Guide Name]
Professor and Guide
PRESENTED BY
Dr. [Presenter Name]
MDS
2.
ARTICLE OVERVIEW
“Critical probingdepths” in periodontal therapy
J. Lindhe, S. S. Socransky, S. Nyman, A. Haffajee, E. Westfelt
Department of Periodontology, Faculty of Odontology, University of Gothenburg, Sweden — and Forsyth Dental Center, Boston, MA, USA
JOURNAL
Journal of Clinical
Periodontology
YEAR
1982
VOLUME / PAGES
Vol 9, pp. 323–336
STUDY TYPE
Split-mouth clinical
trial
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 2
3.
ABSTRACT
▪ 15 patientswith moderately advanced periodontal disease; split-mouth design.
▪ One side: scaling and root planing + modified Widman flap (MWF). Other side: scaling and root planing alone (RPL).
▪ 0–6 months = healing phase (recall every 2 weeks); 6–24 months = maintenance phase (recall every 3 months).
▪ Regression analysis used to calculate “critical probing depths” (CPD) for each treatment.
▪ CPD: RPL = 2.9 mm vs MWF = 4.2 mm (P < 0.01)
▪ Surgery caused more attachment loss than non-surgical therapy in initially shallow pockets, but more gain in initially deep pockets.
▪ During maintenance (12 & 24 months), probing depths and attachment levels stayed stable — but oral hygiene mattered more than the
original treatment method: plaque-free sites stayed shallow; plaque-harbouring sites lost further attachment.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 3
4.
INTRODUCTION
▪ Long-term studies(Knowles 1973; Ramfjord et al.; Lindhe & Nyman 1975; Badersten et al. 1981) show both surgical and non-surgical
therapy can succeed when maintenance care is well designed.
▪ Recent work suggested probing-depth reduction and attachment gain can be achieved by hygiene instruction + scaling/root planing alone
— implying surgery's added benefit must be tested against a non-surgical control.
▪ Loss of attachment after therapy has been linked to initial probing depth: shallow pockets tend to lose attachment; deep pockets tend to
gain it — and this “critical” threshold may depend on the treatment modality.
▪ Waerhaug (1978) and others: subgingival plaque is difficult to eliminate by instrumentation in pockets deeper than 4–5 mm — raising questions about
long-term maintenance of deep sites.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 4
5.
AIMS OF THESTUDY
1 Calculate the critical probing depth (CPD) values for one surgical (MWF) and one non-surgical (RPL) method of periodontal
therapy.
2 Monitor, during an 18-month maintenance period, sites with probing depths >4 mm with respect to gingival inflammation
and attachment level changes.
3 Evaluate the effect of oral hygiene status on probing depths and attachment levels during maintenance, in patients recalled
for prophylaxis every 3 months.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 5
6.
MATERIALS & METHODS
Subjectsand study design
SUBJECTS
▪ 15 individuals, 32–57 years
▪ Referred for treatment of moderately advanced periodontal
disease
▪ Department of Periodontology, University of Gothenburg
BASELINE EXAMINATION
▪ Oral hygiene status (Plaque Index; Silness & Löe 1964)
▪ Gingival conditions (Gingival Index; Löe & Silness 1963)
▪ Probing depths and attachment levels — all teeth present
SPLIT-MOUTH DESIGN
▪ Right / left jaw side, randomly selected
▪ MWF group: scaling & root planing + modified Widman flap
(Ramfjord & Nissle 1974)
▪ RPL group (contralateral quadrants): scaling & root planing
only
▪ Healing phase: 0–6 months, recall every 2 weeks
▪ Maintenance phase: 6–24 months, recall every 3 months
▪ Reexaminations at 6, 12 and 24 months; same
surfaces/points as baseline
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 6
7.
STATISTICAL ANALYSIS
▪ Mean,standard deviation and 95% confidence intervals computed by standard methods.
▪ Significance of difference of means determined using the t-test.
▪ Regression analysis:
– Independent (X-axis) variable: initial probing depth
– Dependent variable: change in attachment level during healing
– Slope and X-intercept computed with 95% confidence intervals
– X-intercept = the “critical probing depth” (CPD)
▪ Significance of differences in slope and X-intercept between treatments was also calculated.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 7
8.
RESULTS
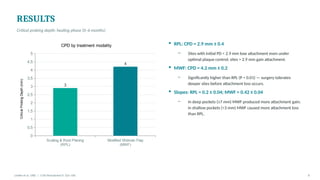
Critical probing depth:healing phase (0–6 months)
Scaling & Root Planing
(RPL)
Modified Widman Flap
(MWF)
0
0.5
1
1.5
2
2.5
3
3.5
4
4.5
5
3
4
CPD by treatment modality
Critical
Probing
Depth
(mm)
▪ RPL: CPD = 2.9 mm ± 0.4
– Sites with initial PD < 2.9 mm lose attachment even under
optimal plaque control; sites > 2.9 mm gain attachment.
▪ MWF: CPD = 4.2 mm ± 0.2
– Significantly higher than RPL (P < 0.01) — surgery tolerates
deeper sites before attachment loss occurs.
▪ Slopes: RPL = 0.2 ± 0.04; MWF = 0.42 ± 0.04
– In deep pockets (≥7 mm) MWF produced more attachment gain;
in shallow pockets (<3 mm) MWF caused more attachment loss
than RPL.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 8
9.
RESULTS
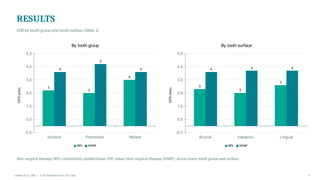
CPD by toothgroup and tooth surface (Table 1)
Incisors Premolars Molars
-0.5
0.5
1.5
2.5
3.5
4.5
5.5
3
3
4
4
5
4
By tooth group
RPL MWF
CPD
(mm)
Buccal Interprox. Lingual
-0.5
0.5
1.5
2.5
3.5
4.5
5.5
3
3
3
4 4 4
By tooth surface
RPL MWF
CPD
(mm)
Non-surgical therapy (RPL) consistently yielded lower CPD values than surgical therapy (MWF), across every tooth group and surface.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 9
10.
RESULTS
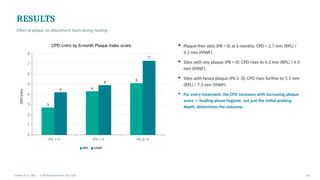
Effect of plaqueon attachment levels during healing
PlI = 0 PlI > 0 PlI 2–3
0
1
2
3
4
5
6
7
8
3
4
5
4
5
7
CPD (mm) by 6-month Plaque Index score
RPL MWF
CPD
(mm)
▪ Plaque-free sites (PlI = 0) at 6 months: CPD = 2.7 mm (RPL) /
4.2 mm (MWF).
▪ Sites with any plaque (PlI > 0): CPD rises to 4.3 mm (RPL) / 4.9
mm (MWF).
▪ Sites with heavy plaque (PlI 2–3): CPD rises further to 5.1 mm
(RPL) / 7.3 mm (MWF).
▪ For every treatment, the CPD increases with increasing plaque
score — healing-phase hygiene, not just the initial probing
depth, determines the outcome.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 10
11.
RESULTS
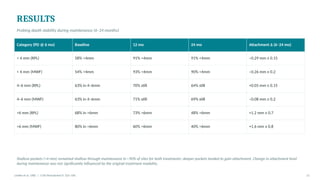
Probing depth stabilityduring maintenance (6–24 months)
Category (PD @ 6 mo) Baseline 12 mo 24 mo Attachment Δ (6–24 mo)
< 4 mm (RPL) 58% <4mm 91% <4mm 91% <4mm –0.29 mm ± 0.15
< 4 mm (MWF) 54% <4mm 93% <4mm 90% <4mm –0.26 mm ± 0.2
4–6 mm (RPL) 63% in 4–6mm 70% still 64% still +0.05 mm ± 0.15
4–6 mm (MWF) 63% in 4–6mm 71% still 69% still –0.08 mm ± 0.2
>6 mm (RPL) 68% in >6mm 73% >6mm 48% >6mm +1.2 mm ± 0.7
>6 mm (MWF) 80% in >6mm 60% >6mm 40% >6mm +1.6 mm ± 0.8
Shallow pockets (<4 mm) remained shallow through maintenance in ~90% of sites for both treatments; deeper pockets tended to gain attachment. Change in attachment level
during maintenance was not significantly influenced by the original treatment modality.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 11
12.
RESULTS
Effect of plaqueduring maintenance
PLAQUE-FREE SITES (PlI = 0)
▪ 82–94% of plaque-free sites (RPL & MWF) remained <4 mm at
6, 12 and 24 months.
▪ Little or no attachment change during 18-month maintenance
(−0.16 to −0.18 mm).
▪ Plaque control after active therapy maintains shallow, stable
pockets.
PLAQUE-HARBOURING SITES (PlI > 0)
▪ Only 37–55% of plaque-positive sites stayed <4 mm; the rest
were in the 4–6 mm or >6 mm categories.
▪ Attachment loss during maintenance: –0.72 mm ± 0.2 (MWF)
and –0.55 mm ± 0.15 (RPL).
▪ Difference between plaque-free and plaque-positive sites
was statistically significant (P < 0.05).
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 12
13.
DISCUSSION
▪ Confirms earlierfindings: sites with initially deep pockets gain attachment, while initially shallow pockets tend to lose attachment following
therapy (Ramfjord et al.; Knowles et al. 1979, 1980; Pihlstrom et al. 1981).
▪ Regression analysis quantified this as a critical probing depth (CPD) — below it, loss is likely; above it, gain is likely — and showed the CPD is
significantly higher for surgical (MWF, 4.2 mm) than non-surgical (RPL, 2.9 mm) therapy.
▪ Clinical implication: patients with mostly shallow pockets may be better served by a non-surgical approach; patients with mostly deep pockets
may gain more attachment from surgical treatment.
▪ Findings by Knowles et al. (1979) and Pihlstrom et al. (1981) using the same modified Widman technique support this pattern of loss <4 mm
and gain in deeper sites.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 13
14.
DISCUSSION
Using CPD topredict outcomes — worked example
A single premolar with initial probing depths: buccal 1 mm, mesial 6 mm, lingual 2 mm, distal 5 mm.
Buccal
Initial PD: 1 mm
MWF: −1.4 mm
loses (< CPD)
Mesial
Initial PD: 6 mm
MWF: +0.7 mm
gains (> CPD)
Lingual
Initial PD: 2 mm
MWF: −1.2 mm
loses (< CPD)
Distal
Initial PD: 5 mm
MWF: +0.2 mm
gains (> CPD)
If treated with MWF surgery:
net total change ≈ –1.7 mm attachment (loss)
If treated with RPL alone:
net total change ≈ +0.1 mm attachment (gain)
Regression-derived CPDs can act as a chairside guide to the expected net effect of a treatment modality on a given tooth — not a guarantee for any single patient.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 14
15.
DISCUSSION
Maintenance care androot-surface plaque
▪ Probing depths and attachment levels obtained after active therapy were maintained — or further improved — during 18 months of 3-monthly
prophylaxis, regardless of whether therapy had been surgical or non-surgical.
▪ Waerhaug (1978), Rabbani et al. (1981) and Tabita et al. (1981): root surfaces in pockets >3–5 mm may retain microscopic plaque/calculus even
after thorough instrumentation.
▪ Listgarten et al. (1978): subgingival scaling and root planing in sites >5 mm effectively reduced inflammation and probing depth, with a resulting
microbiota (coccoid cells, non-motile rods) compatible with gingival health.
▪ Key message: the level of oral hygiene during healing and maintenance is more critical to the outcome than which initial therapy
(surgical vs non-surgical) was used.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 15
16.
CONCLUSION
▪ The criticalprobing depth (CPD) for non-surgical scaling and root planing (2.9 mm) is significantly smaller than for scaling and
root planing combined with modified Widman flap surgery (4.2 mm).
▪ In patients with mostly shallow pockets, non-surgical therapy limits unnecessary attachment loss; in patients with mostly deep
pockets, surgical therapy yields more attachment gain.
▪ Once healing is complete, the quality of long-term maintenance — specifically plaque control — outweighs the initial choice of
surgical vs non-surgical therapy in determining probing depth and attachment stability.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 16
17.
REFERENCES
▪ Lindhe, J.,Socransky, S. S., Nyman, S., Haffajee, A. & Westfelt, E. (1982) “Critical probing depths” in periodontal therapy. Journal of Clinical Periodontology 9, 323–
336.
▪ Ramfjord, S. P. & Nissle, R. R. (1974) The modified Widman flap. Journal of Periodontology 45, 601–607.
▪ Knowles, J. W., Burgett, F. G., Nissle, R. R., Shick, R. A., Morrison, E. C. & Ramfjord, S. P. (1979) Results of periodontal treatment related to pocket depth and
attachment level. Journal of Periodontology 50, 225–233.
▪ Waerhaug, J. (1978) Healing of the dento-epithelial junction following subgingival plaque control. II. Journal of Periodontology 49, 119–134.
▪ Listgarten, M. A., Lindhe, J. & Helldén, L. (1978) Effect of tetracycline and/or scaling on human periodontal disease. Journal of Clinical Periodontology 5, 246–271.
▪ Badersten, A., Nilvéus, R. & Egelberg, J. (1981) Effect of nonsurgical periodontal therapy. I. Journal of Clinical Periodontology 8, 57–72.
▪ Pihlstrom, B. L., Ortiz-Campos, C. & McHugh, R. B. (1981) A randomized four-year study of periodontal therapy. Journal of Periodontology 52, 227–242.
Lindhe et al. 1982 | J Clin Periodontol 9: 323–336 17



 Most read

 Most read




 Most read





