Pharmacology of
Pharmacology of
Corticosteroids
Corticosteroids
Dr. D. K. Brahma
Dr. D. K. Brahma
Department of Pharmacology
NEIGRIHMS, Shillong
NEIGRIHMS, Shillong
Steroids
Steroids
Steroids are fast catching up with antibiotics
as the most abused class of drugs today
High doses of corticosteroids and
other immunosuppressive agents may cause AIDS
Introduction
Introduction
• The adrenal produces various classes of
hormones, each of which aid in dealing with the
stress faced by animals and people almost daily
• At least two of these groups –
Glucocorticoids and Mineralocorticoids
are necessary for life
• Corticosteroids or corticoids refer to natural
gluco- and mineralo-corticoids and their
synthetic analogues
Contents
Contents
 History and Biosynthesis
History and Biosynthesis
 Mechanism of action
Mechanism of action
 Physiological and Pharmacological actions
Physiological and Pharmacological actions
 Pharmacokinetics and preparations
Pharmacokinetics and preparations
 Uses – therapeutic and diagnostic
Uses – therapeutic and diagnostic
 Dosage schedule and withdrawal
Dosage schedule and withdrawal
 Adverse reactions and contraindications
Adverse reactions and contraindications
 Precautions during therapy
Precautions during therapy
 Contraindications
Contraindications
History
History
 1855 – Addison`s disease
1855 – Addison`s disease
 1856 – Adrenal glands essential for life
1856 – Adrenal glands essential for life
 1930 – Cortex > medulla
1930 – Cortex > medulla
 1932 – Cushing’s syndrome
1932 – Cushing’s syndrome
 1952 – Aldosterone
1952 – Aldosterone
Anatomy
Anatomy
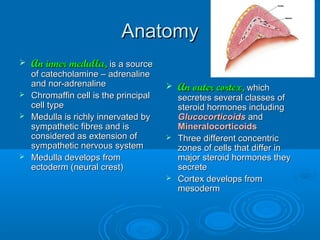
 An inner medulla,
An inner medulla, is a source
is a source
of catecholamine – adrenaline
and nor-adrenaline
and nor-adrenaline
 Chromaffin cell is the principal
Chromaffin cell is the principal
cell type
cell type
 Medulla is richly innervated by
Medulla is richly innervated by
sympathetic fibres and is
considered as extension of
sympathetic nervous system
 Medulla develops from
Medulla develops from
ectoderm (neural crest)
 An outer cortex,
An outer cortex, which
which
secretes several classes of
steroid hormones including
Glucocorticoids
Glucocorticoids and
and
Mineralocorticoids
Mineralocorticoids
 Three different concentric
Three different concentric
zones of cells that differ in
major steroid hormones they
secrete
secrete
 Cortex develops from
Cortex develops from
mesoderm
mesoderm
Adrenal Cortex
Adrenal Cortex
 The adrenal cortex is a factory of steroid hormones
The adrenal cortex is a factory of steroid hormones
 10 – 30 different steroids are synthesized from this
10 – 30 different steroids are synthesized from this
tissue, but two classes are of importance
Steroid Class
Steroid Class Prototype
Prototype Physiological effect
Physiological effect
Mineralocorticoid
Mineralocorticoid Aldosterone (z. glomerulosa)
Aldosterone (z. glomerulosa) Na, K and water
Na, K and water
homeostasis
homeostasis
Glucocorticoid
Glucocorticoid Hydrocortisone or cortisol (z. fasciculata)
Hydrocortisone or cortisol (z. fasciculata)
Corticosterone
Corticosterone
Glucose and many
Glucose and many
other homeostasis
other homeostasis
Adrenal cortex also produces sex steroids – Androgens,
Dehydroepiandrosterone (DHEA) – z. reticularis
Biosynthesis
Biosynthesis
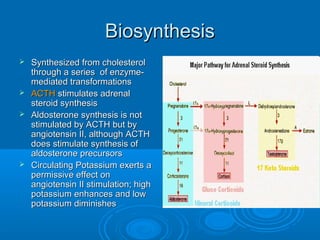
 Synthesized from cholesterol
Synthesized from cholesterol
through a series of enzyme-
mediated transformations
 ACTH
ACTH stimulates adrenal
stimulates adrenal
steroid synthesis
steroid synthesis
 Aldosterone synthesis is not
Aldosterone synthesis is not
stimulated by ACTH but by
angiotensin II, although ACTH
does stimulate synthesis of
aldosterone precursors
 Circulating Potassium exerts a
Circulating Potassium exerts a
permissive effect on
angiotensin II stimulation; high
potassium enhances and low
potassium diminishes
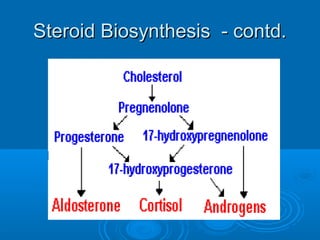
Steroid Biosynthesis - contd.
Basal Secretion
Basal Secretion
Group
Group Hormone
Hormone Daily
Daily
Glucocorticoids
Glucocorticoids Cortisol
Cortisol
Corticosterone
Corticosterone
5 – 30 mg
5 – 30 mg
2 – 5 mg
2 – 5 mg
Mineralocorticoids
Mineralocorticoids Aldosterone
Aldosterone
11- deoxycorticosterone
5 – 150 mcg
5 – 150 mcg
Trace
Trace
Sex Hormones
Sex Hormones
Androgen
Androgen
Progestogen
Progestogen
Oestrogen
Oestrogen
DHEA
DHEA
Progesterone
Progesterone
Oestradiol
Oestradiol
15 – 30 mg
15 – 30 mg
0.4 – 0.8 mg
0.4 – 0.8 mg
Trace
Trace
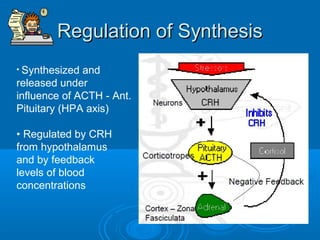
Regulation of Synthesis
• Synthesized and
released under
influence of ACTH - Ant.
Pituitary (HPA axis)
• Regulated by CRH
from hypothalamus
and by feedback
levels of blood
concentrations
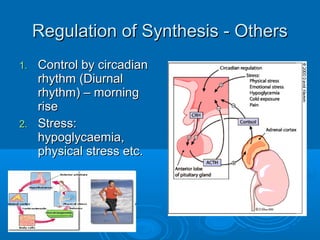
1.
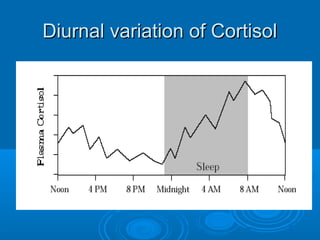
1. Control by circadian
Control by circadian
rhythm (Diurnal
rhythm (Diurnal
rhythm) – morning
rhythm) – morning
rise
rise
2.
2. Stress:
Stress:
hypoglycaemia,
hypoglycaemia,
physical stress etc.
Regulation of Synthesis - Others
Diurnal variation of Cortisol
Glucocorticoids - MOA
 Not stored:
Not stored:

rate of synthesis = rate of release
 Synthesize rhythmically and controlled by
Synthesize rhythmically and controlled by
irregular pulses of ACTH, influenced by light and
major pulses occur early in the morning and
after meals
after meals
 Glucocorticoids act via their receptors located in
Glucocorticoids act via their receptors located in
nucleus (GR)
nucleus (GR)
 GRs are widely distributed and located almost in
GRs are widely distributed and located almost in
all cells of the body
 They are made up of almost 800 amino acids
They are made up of almost 800 amino acids
Glucocorticoids - MOA
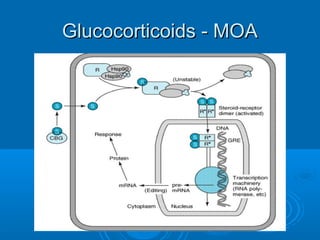
 GR receptors are located in the cytoplasm
GR receptors are located in the cytoplasm
 One GR receptor has a DNA binding domain and a
One GR receptor has a DNA binding domain and a
ligand binding domain along with stabilizing proteins
(HSP 90 and HSP 70)
(HSP 90 and HSP 70)
 This receptor is incapable of activating transcription
This receptor is incapable of activating transcription
 Binding of free steroid molecule to GR forms an unstable
Binding of free steroid molecule to GR forms an unstable
compound
compound
 Therefore HSP and other proteins get dissociated
Therefore HSP and other proteins get dissociated
 The S+GR complex enters the nucleus and binds to
The S+GR complex enters the nucleus and binds to
Glucocorticoids response element (GRE) on gene and
regulate transcription by RNA polymerase II and others
 The resulting mRNA is transported to cytoplasm for
The resulting mRNA is transported to cytoplasm for
production of protein and bring about final response
Glucocorticoids - MOA
Actions
Actions
Numerous and widespread actions:
 Carbohydrate, lipid and protein metabolism
Carbohydrate, lipid and protein metabolism
 Fluid and electrolyte balance
Fluid and electrolyte balance
 Normal functioning of CVS, immune system, kidneys, skeletal muscles and nervous system
Normal functioning of CVS, immune system, kidneys, skeletal muscles and nervous system
 Provides resistance to stress and noxious stimuli and environmental changes
Provides resistance to stress and noxious stimuli and environmental changes
 Permits and facilitates the actions of other hormones
Permits and facilitates the actions of other hormones
 Direct Actions
Direct Actions
 Permissive Actions
Permissive Actions
• Lipolytic effects
• Effect on BP
• Effect on bronchial muscles
• (e.g.,sympathomimetic amine)
Actions of Corticosteroids -
Mineralocorticoid
Mineralocorticoid
 Aldosterone is the prototype of mineralocorticoid effects
Aldosterone is the prototype of mineralocorticoid effects
 Acts on the distal tubule to enhance absorption of Na+
Acts on the distal tubule to enhance absorption of Na+
 Increase excretion of K+ and H
Increase excretion of K+ and H
 Similar effects occur in colon, sweat gland and salivary
Similar effects occur in colon, sweat gland and salivary
gland
gland
 Deficiency of mineralocorticoid action leads to
Deficiency of mineralocorticoid action leads to –
–
dilutional hyponatraemia, hyperkalamia, acidosis,
massive loss of Na+ and decreased EFC volume
(essential for survival)
 Hyperaldosterinism:
Hyperaldosterinism: Positive Na+ balance, expansion of
Positive Na+ balance, expansion of
ECF, increased plasma Na, hypokalaemia, alkalosis and
progressive rise in BP – hypertension, myocardial
fibrosis etc.
fibrosis etc.
Glucocorticoid actions -
Carbohydrate & protein metabolism
 Profound effect on carbohydrate and protein metabolism
Profound effect on carbohydrate and protein metabolism
– aimed at protecting glucose dependent tissues (brain
and heart)
and heart)
 Promotes glycogen deposition in liver and stimulate it to
Promotes glycogen deposition in liver and stimulate it to
form glucose from amino acids – gluconeogenesis
 In peripheral tissues decreases utilization of glucose,
In peripheral tissues decreases utilization of glucose,
increase protein breakdown and activate lipolysis – form
amino acids and glycerol for gluconeogenesis
 All these results in -
All these results in -

Diabetes like stat resistant to insulin – increased glucose release
from liver + decreased peripheral glucose utilization

Negative Nitrogen balance (catabolic effect) – amino acid used
up in gluconeogenesis – increased urea production

Mobilization of amino acids – muscles, thinning of bone and skin
Actions:
Actions: Carbohydrate and protein metabolism
Carbohydrate and protein metabolism
 Gluconeogenesis
Gluconeogenesis

Peripheral actions
Peripheral actions (mobilize AA & glucose and
(mobilize AA & glucose and
glycogen)
glycogen)

Hepatic actions
Hepatic actions
 Peripheral utilization of glucose
Peripheral utilization of glucose
 Glycogen deposition in liver
Glycogen deposition in liver
(activation of hepatic glycogen synthase)
Negative nitrogen balance & hyperglycaemia
Fat Metabolism
Fat Metabolism
 Redistribution of fats in different areas of the
Redistribution of fats in different areas of the
body
body
 Due to permissive facilitation of effects of other
Due to permissive facilitation of effects of other
agents – GH, glucagons, Adr, thyroxine and
insulin
insulin

Deposition of fats in face, neck and shoulder – moon
face/buffalo hump
face/buffalo hump

Glucocorticoids facilitated hormone sensitive lipolysis
action of GH and Adr. + Glucocorticoids mediated
increased insulin = net result is insulin mediated
lipogenesis and fat deposition

Peripheral adipocytes are less sensitive to insulin, but
in face and neck predominant action – fat deposition
Actions of Glucocorticoids
 Water excretion:
Water excretion:

Glucocorticoids play important role in maintaining normal GFR - in
adrenal insufficiency capacity to excrete water is lost – water intoxication
 Calcium Balance:
Calcium Balance:

Decrease absorption of Ca++ in GIT and increased excretion – calcium
depletion -
depletion - osteoporosis
osteoporosis
 Skeletal muscle:
Skeletal muscle:

Normal muscular activity needs Glucocorticoids at its optimum level

Excess level leads to muscular weakness and wasting

Muscular weakness occurs in both Hypocorticism (due to hypodynamic
circulation) and hypercorticism – due to hypokalaemia
 CNS:
CNS:

Euphoria – in pharmacological doses

Addison's disease – apathy, depression and psychosis

High doses – induce seizure
Actions of Glucocorticoids
 CVS:
CVS: Permissive role on pressor effect with Adr and angiotensin
Permissive role on pressor effect with Adr and angiotensin

Maintain tone of arterioles and myocardial contractility

Adrenal insufficiency leads to low cardiac output and arteriolar dilatation
and poor response to adrenaline

Cardiovascular collapse – along with mineralocorticoids
 Blood and lymphoid tissues:
Blood and lymphoid tissues:

Destruction of lymphoid tissue – modest in normal persons

In presence of malignancy of lymphatic cells – lytic actions are
significant (apoptosis) – used in lymphomas
significant (apoptosis) – used in lymphomas (Basis of Use)
(Basis of Use)

Minor effects on haemoglobin and RBCs – protect against haemolysis of
RBCs –
RBCs – Increase in number of RBCs
Increase in number of RBCs

Decreases the numbers of circulating lymphocytes, monocytes,
eosinophils and basophils but increases Polymorphs
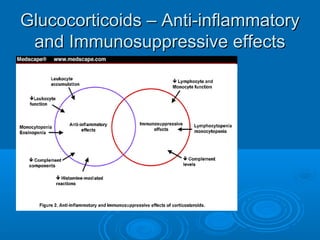
Glucocorticoids – anti-inflammatory
and immunosuppressive effects
 Suppress inflammatory response to all noxious stimuli:
Suppress inflammatory response to all noxious stimuli:
Pathogens, chemical,physical and immune mediated
stimuli, hypersensitivity
 Underlying cause of disease is not corrected
Underlying cause of disease is not corrected
 Reduction in cardinal signs of inflammation
Reduction in cardinal signs of inflammation
 Anti-inflammatory effects are non—specific and covers
Anti-inflammatory effects are non—specific and covers
all components of inflammation:

Effects on concentration, distribution and functions of peripheral
leukocytes – increased neutrophils & their activity

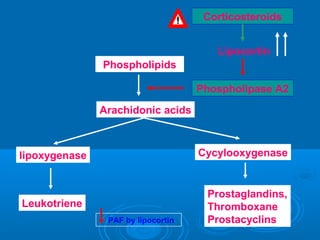
In macrophages: reduction of arachidonic acid metabolites
(mediators) like PG, LT and PAF synthesis that results from
activation of phospholipase A2
Basis of exogenous use of most clinical uses
Glucorticoids - Multiple
Mechanisms
 Recruitment of WBC & monocyte - macrophage into
Recruitment of WBC & monocyte - macrophage into
affected area & elaboration of chemotactic substances
 Lipocortin: decreased production of PG, LT and PAF
Lipocortin: decreased production of PG, LT and PAF
 Negative regulation of COX 2: inducible PG
Negative regulation of COX 2: inducible PG
production
production
 Negative regulation of genes in cytokines of
Negative regulation of genes in cytokines of
macrophages, endothelial cells and lymphocytes:
production of IL (1, 2, 3, 6), TNF
production of IL (1, 2, 3, 6), TNFα
α, GM-CSF etc. –
, GM-CSF etc. –
fibroblast proliferation and T-lymphocyte function –
interference with chemotaxis
Contd.
Contd.
 In endothelial cells-Endothelial leucocyte adhesion
In endothelial cells-Endothelial leucocyte adhesion
molecule
molecule (ELAM)
(ELAM) and other
and other CAM
CAM are inhibited –
are inhibited –
adhesion and localization of leucocytes interfered
 Release of histamine from basophils is inhibited
Release of histamine from basophils is inhibited
 Decreased production of
Decreased production of collagenase
collagenase – prevention of
– prevention of
tissue destruction
tissue destruction
 Decreased functioning of
Decreased functioning of osteoblasts
osteoblasts and increased
and increased
activity of
activity of osteoclastic
osteoclastic activity -
activity - osteoporosis
osteoporosis
 Decreased IgG production
Decreased IgG production
 Decreased generation of induced nitric oxide
Decreased generation of induced nitric oxide
Phospholipids
Arachidonic acids
lipoxygenase Cycylooxygenase
Leukotriene
Prostaglandins,
Thromboxane
Prostacyclins
Phospholipase A2
Lipocortin
Corticosteroids
PAF by lipocortin
Immunosuppressive & anti-allergic
actions
actions
 Suppresses all types of hypersensitivity &
Suppresses all types of hypersensitivity &
allergic phenomenon
allergic phenomenon
 At High dose: Interfere with all steps of
At High dose: Interfere with all steps of
immunological response
 Causes greater suppression of CMI (graft
Causes greater suppression of CMI (graft
rejection & delayed hypersensitivity)
 Transplant rejection: antigen expression from
Transplant rejection: antigen expression from
grafted tissues, delay revascularization,
sensitisation of T lymphocytes etc.
Glucocorticoids – Anti-inflammatory
and Immunosuppressive effects
Glucocorticoids - Pharmacokinetics
 Therapeutically given by various routes – orally, IM, IV,
Therapeutically given by various routes – orally, IM, IV,
topically
topically
 Hydrocortisone undergoes high first pass metabolism
Hydrocortisone undergoes high first pass metabolism
 Oral bioavailability of synthetic corticoids is high
Oral bioavailability of synthetic corticoids is high
 Both, endogenous and therapeutically administered GC
Both, endogenous and therapeutically administered GC
are bound to Corticosteroid Binding Globulin (CBG)
 Synthetic steroids have to undergo reduction in liver to
Synthetic steroids have to undergo reduction in liver to
active compounds
active compounds
 Metabolized in liver and excreted in urine
Metabolized in liver and excreted in urine
 Exogenously administered hydrocortisone has t1/2 of 1.5
Exogenously administered hydrocortisone has t1/2 of 1.5
Hrs
Hrs
Steroid Preparations
 An ideal GC should have no
An ideal GC should have no
mineralocorticoid activity
 Structural changes to the basic cortisol
Structural changes to the basic cortisol
molecule resulted in a number of
compounds with
compounds with

Minimal mineralocorticoid activity

Greater potency
Greater potency

Longer duration of action
Important agents
Important agents
 Injectable:
Injectable:
Betamethasone Dexamethasone
Prednisolone Methylprednisolone
Hydrocortisone Triamcinolone
 Oral:
Oral:
Betamethasone Fludricortisone
Prednisolone Prednisone
Methylprednisolone
Methylprednisolone
 Topical:
Topical:
Betamethasone Clobetasol
Flucinolone Mometasone
 Inhalation:
Inhalation:
Beclomethasone Budesonide
Flunisolode
Flunisolode
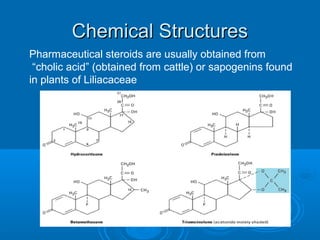
Chemical Structures
Chemical Structures
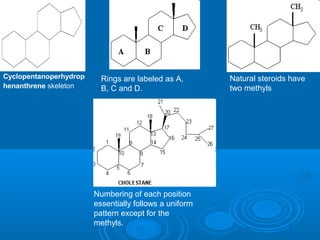
Pharmaceutical steroids are usually obtained from
“cholic acid” (obtained from cattle) or sapogenins found
in plants of Liliacaceae
Cyclopentanoperhydrop
henanthrene skeleton
Rings are labeled as A,
B, C and D.
Natural steroids have
two methyls
Numbering of each position
essentially follows a uniform
pattern except for the
methyls.

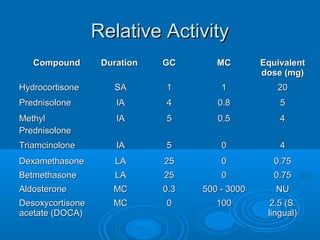
Relative Activity
Relative Activity
Compound
Compound Duration
Duration GC
GC MC
MC Equivalent
Equivalent
dose (mg)
dose (mg)
Hydrocortisone
Hydrocortisone SA
SA 1
1 1
1 20
20
Prednisolone
Prednisolone IA
IA 4
4 0.8
0.8 5
5
Methyl
Methyl
Prednisolone
Prednisolone
IA
IA 5
5 0.5
0.5 4
4
Triamcinolone
Triamcinolone IA
IA 5
5 0
0 4
4
Dexamethasone
Dexamethasone LA
LA 25
25 0
0 0.75
0.75
Betmethasone
Betmethasone LA
LA 25
25 0
0 0.75
0.75
Aldosterone
Aldosterone MC
MC 0.3
0.3 500 - 3000
500 - 3000 NU
NU
Desoxycortisone
Desoxycortisone
acetate (DOCA)
acetate (DOCA)
MC
MC 0
0 100
100 2.5 (S.

2.5 (S.
lingual)
lingual)
Corticosteroids - Clinical
Pharmacology
Pharmacology
Therapeutic uses
Therapeutic uses
 A number of diverse disease states respond to
A number of diverse disease states respond to
GCs
GCs
 Physiologic doses of Corticosteroids are used
Physiologic doses of Corticosteroids are used
for replacement therapy in primary and
secondary adrenal insufficiency such as
Addison`s disease
Addison`s disease
 Supraphysiologic doses are used for their anti-
Supraphysiologic doses are used for their anti-
inflammatory effects in arthritis, asthma and
inflammatory bowel disease
 In organ transplant patients and those with
In organ transplant patients and those with
autoimmune disorders corticosteroids are used
for their immunosuppressive effects
Replacement Therapy
Replacement Therapy
 Adrenal insufficiency – acute/chronic
Adrenal insufficiency – acute/chronic

Abrupt withdrawal of steroid therapy

Chronic infections – Tuberculosis

Autoimmune adrenal disease

Surgery, Hemorrhage and AIDS
 Congenital adrenal hyperplasia
Congenital adrenal hyperplasia

Congenital disorder due to deficiency of 21-
hydroxylse enzyme – no cortisol but ACTH –
increased androgen production
CAH
Replacement Therapy
Replacement Therapy
 Acute adrenal insufficiency
Acute adrenal insufficiency

IV replacement of sodium chloride and fluid

IV hydrocortisone 100 mg stat followed by100 mg
every 8 Hrs – maximal daily rate of secretion
(alternatively, dexamethasone can be used)
 Chronic adrenal insufficiency
Chronic adrenal insufficiency

Hydrocortisone
Hydrocortisone

Prednisolone or dexamethasone – long acting

Fludrocortisone for mineralocorticoid effects
 Congenital adrenal hyperplasia
Congenital adrenal hyperplasia

Hydrocortisone 0.6 mg/kg in divided doses – to
maintain feedback suppression
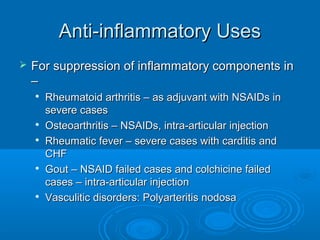
Anti-inflammatory Uses
 For suppression of inflammatory components in
For suppression of inflammatory components in
–
–

Rheumatoid arthritis – as adjuvant with NSAIDs in
severe cases
severe cases

Osteoarthritis – NSAIDs, intra-articular injection

Rheumatic fever – severe cases with carditis and
CHF
CHF

Gout – NSAID failed cases and colchicine failed
cases – intra-articular injection

Vasculitic disorders: Polyarteritis nodosa
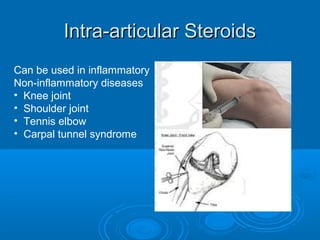
Intra-articular Steroids
Can be used in inflammatory
Non-inflammatory diseases
• Knee joint
• Shoulder joint
• Tennis elbow
• Carpal tunnel syndrome
Autoimmune diseases
Autoimmune diseases
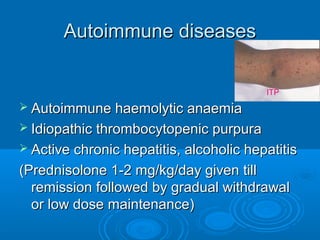
 Autoimmune haemolytic anaemia
Autoimmune haemolytic anaemia
 Idiopathic thrombocytopenic purpura
Idiopathic thrombocytopenic purpura
 Active chronic hepatitis, alcoholic hepatitis
Active chronic hepatitis, alcoholic hepatitis
(Prednisolone 1-2 mg/kg/day given till
remission followed by gradual withdrawal
or low dose maintenance)
ITP
Renal diseases
Renal diseases
 Nephrotic syndrome in children
Nephrotic syndrome in children
 Renal disease secondary to SLE
Renal disease secondary to SLE
 Renal sarcoidosis
Renal sarcoidosis
 Glomerulonephritis – membranous type
Glomerulonephritis – membranous type
(Life saving importance – usually given in
large doses followed by tapering to
maintenance dose)
maintenance dose)
SLE
Organ Transplant
Organ Transplant
 Combined with other
Combined with other
immunosuppressants – cyclosporin,
azathioprine
azathioprine
 For prolonged use:
For prolonged use:
 Prednisolone or methylprednisolone are
Prednisolone or methylprednisolone are
used
used

Intermediate duration of action

Can be easily tapered

Can be converted to an alternate regime
Allergic Disorders
Allergic Disorders
 Exhibit a delayed response in allergies (1-2 hrs
Exhibit a delayed response in allergies (1-2 hrs
even in IV injection)
 In anaphylaxis, angioneurotic oedema and
In anaphylaxis, angioneurotic oedema and
serum sickness etc. – adrenaline is the choice
 Seasonal allergies, bee sting, drug allergies –
Seasonal allergies, bee sting, drug allergies –

Allergic reactions can be suppressed by
corticosteroids as supplements
 Intranasal administration in allergic rhinitis -
Intranasal administration in allergic rhinitis -
budesonide and flunisolide
Bronchial Asthma
Bronchial Asthma
 The increased recognition of the immunological and
The increased recognition of the immunological and
inflammatory nature of Bronchial asthma has led to the
use of corticosteroids
 In severe asthma attacks
In severe asthma attacks
IV hydrocortisone Methylprednisolone
Oral prednisolone
Oral prednisolone
 Acute attacks:
Acute attacks:
*Inhaled beclmethasone, budesonide, flunisolide
alone or combined with beta-2 agonists/ipratropium
*Oral steroids
*Oral steroids
Infectious Diseases
Infectious Diseases
 Indicated only in severe infective diseases
Indicated only in severe infective diseases
to tide over crisis or prebent complictions

AIDS and pneumocystis carinii pneumonia

In haemophilus influenza meningitis to reduce
neurological complications

Tubercular meningitis

Lepra reaction
Lepra reaction

Scepticaemia
Scepticaemia
Lepra reaction
Ocular Diseases
Ocular Diseases
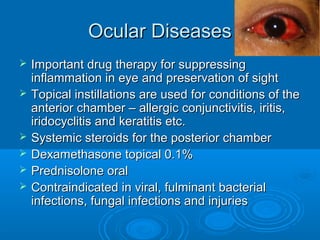
 Important drug therapy for suppressing
Important drug therapy for suppressing
inflammation in eye and preservation of sight
 Topical instillations are used for conditions of the
Topical instillations are used for conditions of the
anterior chamber – allergic conjunctivitis, iritis,
iridocyclitis and keratitis etc.
 Systemic steroids for the posterior chamber
Systemic steroids for the posterior chamber
 Dexamethasone topical 0.1%
Dexamethasone topical 0.1%
 Prednisolone oral
Prednisolone oral
 Contraindicated in viral, fulminant bacterial
Contraindicated in viral, fulminant bacterial
infections, fungal infections and injuries
Skin Diseases
Skin Diseases
 The largest application of steroid therapy
The largest application of steroid therapy
 Topical forms are widely used in many
Topical forms are widely used in many
eczematous skin diseases
 Systemic therapy are also required and
Systemic therapy are also required and
may be life saving in

Pemphigus vulgaris
Pemphigus vulgaris

Exfoliative dermatitis

Stevens-Johnson syndrome
Pemphigus
vulgaris
GIT
GIT
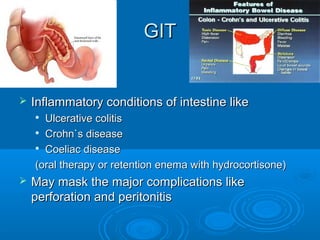
 Inflammatory conditions of intestine like
Inflammatory conditions of intestine like

Ulcerative colitis
Ulcerative colitis

Crohn`s disease
Crohn`s disease

Coeliac disease
Coeliac disease
(oral therapy or retention enema with hydrocortisone)
 May mask the major complications like
May mask the major complications like
perforation and peritonitis
Malignancy
Malignancy
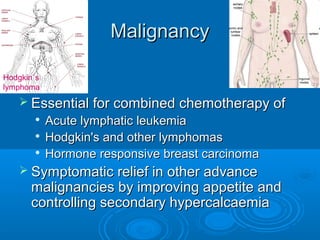
 Essential for combined chemotherapy of
Essential for combined chemotherapy of

Acute lymphatic leukemia

Hodgkin's and other lymphomas

Hormone responsive breast carcinoma
 Symptomatic relief in other advance
Symptomatic relief in other advance
malignancies by improving appetite and
controlling secondary hypercalcaemia
Hodgkin`s
lymphoma
Cerebral Oedema
Cerebral Oedema
 Cerebral oedema due to tumors
Cerebral oedema due to tumors
(neoplasms)
(neoplasms)
 Traumatic and poststroke oedema (?)
Traumatic and poststroke oedema (?)
(Dexamethasone or betamethasone is
preferred because no Na+ retaining
activity)
activity)
 Other CNS conditions - spinal chord injury,
Other CNS conditions - spinal chord injury,
Bell`s palsy and neurocysticercosis
 (Oral Prednisolone is the preferred drug)
(Oral Prednisolone is the preferred drug)
Other Uses
Other Uses
 Antiemetic – with ondansetron
Antiemetic – with ondansetron
 Acute mountain sickness
Acute mountain sickness
 Aspiration pneumonia, pulmonary oedema
Aspiration pneumonia, pulmonary oedema
from drowning
from drowning
 Hyperthyroidism – thyroid storm
Hyperthyroidism – thyroid storm
Adverse Effects
Adverse Effects
 Two types:
Two types:

From abrupt withdrawal

Chronic therapeutic use of high dose
 Withdrawal
Withdrawal

Flare up of underlying disease

Suppression of HPA axis and acute adrenal
insufficiency
insufficiency

Increased ICT and papilloedema
Adverse Effects
Adverse Effects
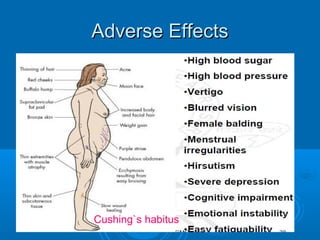
Cushing`s habitus
Other Important Adverse Effects
 Fluid and Electrolyte Disturbance – Na and water
Fluid and Electrolyte Disturbance – Na and water
retention
retention
 Precipitation of Diabetes mellitus – hyperglycemia
Precipitation of Diabetes mellitus – hyperglycemia
 Increased susceptibility to infections – immune response
Increased susceptibility to infections – immune response
suppression
suppression
 Peptic ulceration – bleeding & perforation
Peptic ulceration – bleeding & perforation
 Osteoporosis – flat spongy bones
Osteoporosis – flat spongy bones
 Osteonecrosis – avascular necrosis of head of femur,
Osteonecrosis – avascular necrosis of head of femur,
humorous etc.
humorous etc.
 Myopathy – weakness of muscles
Myopathy – weakness of muscles
 Cataract – posterior sub capsular
Cataract – posterior sub capsular
 Glaucoma – prolonged topical therapy
Glaucoma – prolonged topical therapy
 Growth retardation – in children
Growth retardation – in children
Contraindications
Contraindications
 Say no to any drug formulation combined with
Say no to any drug formulation combined with
steroids
steroids
 Remember that STEROIDS are life saving drugs
Remember that STEROIDS are life saving drugs
 Note the following conditions where u have to be
Note the following conditions where u have to be
extremely cautious:
extremely cautious:

Peptic ulcer
Peptic ulcer

Hypertension and Diabetes mellitus

Viral and fungal infections

Tuberculosis and other diseases

Osteoporosis
Osteoporosis

Epilepsy and psychosis

CHF and renal failure
Choosing a Steroid
Choosing a Steroid
 Benefit/risk ratio is a major consideration
Benefit/risk ratio is a major consideration
 Drugs with primary glucocorticoid activity
Drugs with primary glucocorticoid activity
are used
are used
 Minimal dose to achieve the desired
Minimal dose to achieve the desired
effects is chosen
effects is chosen
 Topical or local therapy is preferred
Topical or local therapy is preferred
whenever possible
whenever possible
Choosing a Steroid – contd.
• Once daily dosing is usually
Once daily dosing is usually
preferred for oral glucocorticoids
• Large steroid doses are
Large steroid doses are
administered in divided doses to
reduce local GIT effects
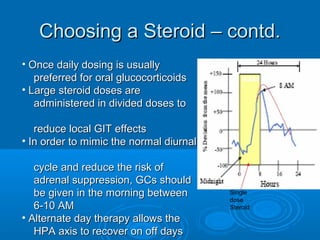
• In order to mimic the normal diurnal
In order to mimic the normal diurnal
cycle and reduce the risk of
adrenal suppression, GCs should
be given in the morning between
6-10 AM
6-10 AM
• Alternate day therapy allows the
Alternate day therapy allows the
HPA axis to recover on off days
Single
dose
Steroid
Withdrawal of Steroid Therapy
 Taper the dose to reduce GC dose by 2.5-5 mg of
Taper the dose to reduce GC dose by 2.5-5 mg of
prednisolone equivalent daily
 Once the GC dose is reduced to 5 mg of prednisolone
Once the GC dose is reduced to 5 mg of prednisolone
equivalent, the patient may be switched to a shorter
acting agent for further tapering
 Intermediate acting corticosteroids allow for more flexible
Intermediate acting corticosteroids allow for more flexible
dosing schedule
dosing schedule

Have potent glucocorticoid effects

Causes lesser suppression of HPA axis

Causes less GIT irritation

Preferred for oral therapy

Prednisolone, methylprednisolone and triacinolone have a half
life of 12-36 Hrs, are available in a number of dosage forms
Adrenocorticosteroid Inhibitors
 Metyrapone:
Metyrapone: 11 beta-hydroxylase
11 beta-hydroxylase enzyme inhibitor –
enzyme inhibitor –
used in Cushing`s syndrome and test of pituitary
efficiency
efficiency
 Aminoglutethemide:
Aminoglutethemide: Stops conversion of cholesterol to
Stops conversion of cholesterol to
pregnelone
pregnelone (Medical adrenalectomy)
(Medical adrenalectomy) – Breast cancers
– Breast cancers
 Mifepristone:
Mifepristone: Progesterone antagonist
Progesterone antagonist
 Spironolactone:
Spironolactone: Aldosterone antagonist
Aldosterone antagonist
 Ketoconazole:
Ketoconazole: Inhibits synthesis of all hormones in
Inhibits synthesis of all hormones in
testes and adrenal cortex – used in Cushing`s
syndrome and also in hirsutism in female
Must Know!
Must Know!
 Biosynthesis and Regulation of
Biosynthesis and Regulation of
Corticosteroids
Corticosteroids
 Mechanism of action of Corticosteroids
Mechanism of action of Corticosteroids
 Name of commonly used Glucocorticoids
Name of commonly used Glucocorticoids
 Anti-inflammatory and
Anti-inflammatory and
immunosuppressive actions of
Glucocorticoids
Glucocorticoids
 Important Adverse effects of
Important Adverse effects of
Corticosteroids
Corticosteroids
 Therapeutic uses of Corticosteroids
Therapeutic uses of Corticosteroids
Thank You
Thank You