


CORTICOSTEROIDS - AN
INTRODUCTION
Christopher Fowler
Department of Pharmacology and Clinical
Neuroscience, Umeå University, Umeå
Sweden
November 2017
Synopsis
Endogenous glucocorticoid production
Glucocorticoid receptors
Pharmacological effects of glucocorticoids
Disclaimer
Glucocorticoids as anti-inflammatory agents
Why dose-tapering after prolonged
glucocorticoid treatment?
Disclaimer
This short presentation is designed to give
the pharmacological background to the use
of corticosteroids for the treatment of
inflammation. It does not give treatment
recommendations and should not be used as
such. Further, the information is accurate as
of November 2017. If you are reading this is
in 2022, things may have changed!
Christopher Fowler
Endogenous
glucocorticoid
(GC) and
mineralocorticoid
(MC) production
Hypothalamus
Anterior pituitary
CRF
ACTH
Adrenal cortex
GC MC
+
+
--
Note the regulatory feedback
loops. We’ll get back to
those later
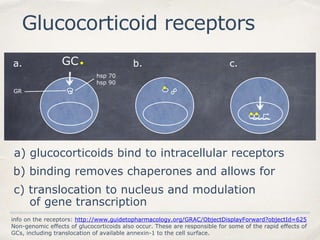
Glucocorticoid receptors
info on the receptors: http://www.guidetopharmacology.org/GRAC/ObjectDisplayForward?objectId=625
Non-genomic effects of glucocorticoids also occur. These are responsible for some of the rapid effects of
GCs, including translocation of available annexin-1 to the cell surface.
GC
hsp 70
hsp 90
GR
a. b. c.
a) glucocorticoids bind to intracellular receptors
b) binding removes chaperones and allows for
c) translocation to nucleus and modulation
of gene transcription
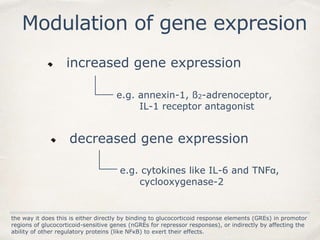
Modulation of gene expresion
the way it does this is either directly by binding to glucocorticoid response elements (GREs) in promotor
regions of glucocorticoid-sensitive genes (nGREs for repressor responses), or indirectly by affecting the
ability of other regulatory proteins (like NFκB) to exert their effects.
increased gene expression
e.g. annexin-1, ß2-adrenoceptor,
IL-1 receptor antagonist
decreased gene expression
e.g. cytokines like IL-6 and TNFα,
cyclooxygenase-2
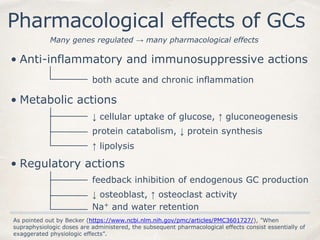
Pharmacological effects of GCs
Many genes regulated → many pharmacological effects
• Anti-inflammatory and immunosuppressive actions
both acute and chronic inflammation
• Metabolic actions
↓ cellular uptake of glucose, ↑ gluconeogenesis
protein catabolism, ↓ protein synthesis
↑ lipolysis
• Regulatory actions
feedback inhibition of endogenous GC production
↓ osteoblast, ↑ osteoclast activity
Na+ and water retention
As pointed out by Becker (https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3601727/), ”When
supraphysiologic doses are administered, the subsequent pharmacological effects consist essentially of
exaggerated physiologic effects”.
GCs as anti-inflammatory drugs
Anti-inflammatory
Immunosuppressive
actions
Metabolic actions
Regulatory actions
§In asthma, inhaled glucocorticoids will not only reach the lungs, but also affect the throat, rendering
it sensitive to opportunistic infections (usually Candida). That is why patients should gargle after
inhalation, to dilute out the GC that didn’t reach the lungs.
😀
😡
😡
Strategy to minimise
unwanted effects:
local treatment
(when possible)
skin (e.g. treatment of eczema)
😡
lungs (treatment of asthma)
potent and effective
increased sensitivity
to infections§
e.g. hyperglycaemia
e.g. osteoporosis
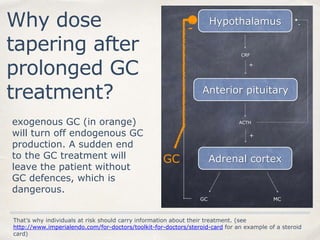
Why dose
tapering after
prolonged GC
treatment?
Hypothalamus
Anterior pituitary
CRF
ACTH
Adrenal cortex
GC MC
+
+
-
-
GC
exogenous GC (in orange)
will turn off endogenous GC
production. A sudden end
to the GC treatment will
leave the patient without
GC defences, which is
dangerous.
That’s why individuals at risk should carry information about their treatment. (see
http://www.imperialendo.com/for-doctors/toolkit-for-doctors/steroid-card for an example of a steroid
card)
Corticosteroids- an introduction