




CONSTIPATION
PRESENTED BY
SWATILEKHA DAS
M.SC NURSING (Medical-
Surgical )
ASST. PROFESSOR
Constipation
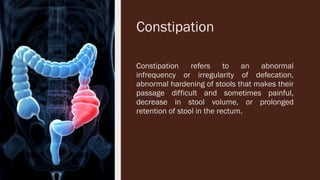
Constipation refers to an abnormal
infrequency or irregularity of defecation,
abnormal hardening of stools that makes their
passage difficult and sometimes painful,
decrease in stool volume, or prolonged
retention of stool in the rectum.
RISK FACTORS
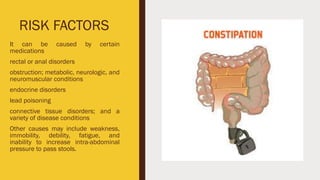
It can be caused by certain
medications
rectal or anal disorders
obstruction; metabolic, neurologic, and
neuromuscular conditions
endocrine disorders
lead poisoning
connective tissue disorders; and a
variety of disease conditions
Other causes may include weakness,
immobility, debility, fatigue, and
inability to increase intra-abdominal
pressure to pass stools.
Constipation develops when people do not take the time or ignore the urge to defecate
or as the result of dietary habits (low consumption of fiber and inadequate fluid intake),
lack of regular exercise, and a stress-filled life. Perceived constipation is a subjective
problem that occurs when an individual’s bowel elimination pattern is not consistent
with what he or she perceives as normal. Chronic laxative use contributes to this
problem.
CLINICAL MANIFESTATIONS
■ Fewer than three bowel movements per week, abdominal distention, and pain and
pressure
■ Decreased appetite, headache, fatigue, indigestion, sensation of incomplete emptying
■ Straining at stool; elimination of small volume of hard, dry stool
■ Complications such as hypertension, hemorrhoids and fissures, fecal impaction, and
megacolon
Assessment and Diagnostic Findings
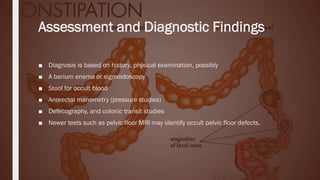
■ Diagnosis is based on history, physical examination, possibly
■ A barium enema or sigmoidoscopy
■ Stool for occult blood
■ Anorectal manometry (pressure studies)
■ Defecography, and colonic transit studies
■ Newer tests such as pelvic floor MRI may identify occult pelvic floor defects.
Medical
Management
Treatment should target
the underlying cause of
constipation and aim to
prevent recurrence,
including education,
bowel habit training,
increased fiber and fluid
intake, and judicious use
of laxatives.
Discontinue laxative
abuse; increase fluid
intake; include fiber in
diet; try biofeedback,
exercise routine to
strengthen abdominal
muscles.
If laxative is necessary,
use bulk-forming agents,
saline and osmotic
agents, lubricants,
stimulants, or fecal
softeners.
Specific medication
therapy to increase
intrinsic motor function
(eg, cholinergics,
cholinesterase inhibitors,
or pro-kinetic agents).
NURSING MANAGEMENT
Use tact and respect with patient when talking about bowel habits and obtaining health history. Note the following:
Onset and duration of constipation, current and past elimination patterns, patient’s expectation of normal bowel
elimination, and lifestyle information (eg, exercise and activity level, occupation, food and fluid intake, and stress level).
Past medical and surgical history, current medications, his-tory of laxative or enema use.
Report of any of the following: rectal pressure or fullness, abdominal pain, straining at defecation, and flatulence.
Sets specific goals for teaching; goals for the patient include restoring or maintaining a regular pattern of elimination by
responding to the urge to defecate, ensuring adequate intake of fluids and high-fiber foods, learning about methods to
avoid constipation, relieving anxiety about bowel elimination patterns, and avoiding compli-cations.
Constipation easy explanation