Comprehensive Pharmacovigilance for Ayurveda Drugs: Safety, Monitoring, and Regulatory Framework
BAMS second professional topic in Rasashastra evum bhaishaya Kalpana subect NCISM topic 26 ,with obectives Explore pharmacovigilance principles, ADR identification, monitoring methods, and the regulatory network ensuring safe use of Ayurvedic medicines, including the updated AyushSuraksha Portal and national reporting systems.
Comprehensive Pharmacovigilance for Ayurveda Drugs: Safety, Monitoring, and Regulatory Framework
1.
TOPIC 26 ·Dr. Kiran Sures h Edayath
Pharmacovigilance for
Ayurveda Drugs
Department of Rasashastra evam Bhaishajya Kalpana (RSBK)
Future Institute of Ayurvedic Medical Sciences (FIAMS), Future University, Bareilly
AyUG-RB Dr.Kiran S Edayath · Topic 26 · Pharmacovigilance for Ayurveda Drugs 1
2.
6 Learning Objectives
1Describe the term Pharmacovigilance & its importance for Ayurvedic drugs. CO2 CO4 CO5
2 Explain the status & central sector scheme of PV for ASU&H drugs. CO4 CO5
3 Define Adverse Drug Reactions (ADR) and its types. CO4 CO5
4 Identify and monitor ADRs. CO2 CO4 CO5
5 Discuss the safe & efficacious use of Ayurvedic drugs. CO2 CO4
6 Debate on ADR of ASU drugs. CO4 CO5
AyUG-RB Dr.Kiran S Edayath · Topic 26 · Pharmacovigilance for Ayurveda Drugs 2
3.
SECTION 1 OF6
Meaning & Importance of Pharmacovigilance
Learning Objective 1 · CO2, CO4, CO5
AyUG-RB Dr.Kiran S Edayath · Topic 26 · Pharmacovigilance for Ayurveda Drugs 3
4.
1.1 WHAT DOESTHE TERM MEAN?
Pharmaco-Vigilance — “Watching Over Drugs”
PHARMAKON
Greek · “drug” + VIGILARE
Latin · “to keep watch”
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 4
5.
1.1 WHAT DOESTHE TERM MEAN?
Pharmaco-Vigilance — “Watching Over Drugs”
PHARMAKON
Greek · “drug” + VIGILARE
Latin · “to keep watch”
PHARMACOVIGILANCE
WHO Definition
The science and activities relating to detection, assessment, understanding, and prevention of adverse effects
or any drug-related problem.
AyUG-RB Dr.Kiran S Edayath · Topic 26 · Pharmacovigilance for Ayurveda Drugs 5
6.
1.3 & 1.6
WhyPharmacovigilance Matters
WHY PV IS NEEDED (in general)
Trials use small, short-duration samples — rare ADRs surface only after wide
use.
Provides continuous benefit–risk assessment of marketed medicines.
Protects public health via early safety signals.
WHY IT MATTERS SPECIFICALLY FOR AYURVEDA
“Safe-by-default” is a false assumption — suppresses ADR detection.
Poly-herbal / herbo-mineral formulations = complex causality tracing.
100,000+ formulations demand a systematic approach
Builds global credibility & regulator trust for Ayurvedic medicine.
Classical Acknowledgment of Risk — Charaka Samhita
A medicine correctly used acts like nectar; wrongly used, it can act like poison, a weapon, fire, or a thunderbolt. Ayurveda never claimed medicines to be inherently risk-
free.
AyUG-RB Dr.Kiran S Edayath · Topic 26 · Pharmacovigilance for Ayurveda Drugs 6
7.
SECTION 2 OF6
Status & Central Sector Scheme for ASU&H PV
Learning Objective 2 · CO4, CO5
AyUG-RB Dr.Kiran S Edayath · Topic 26 · Pharmacovigilance for Ayurveda Drugs 7
8.
2.1 HOW WEGOT HERE
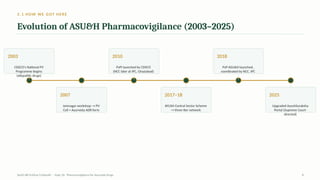
Evolution of ASU&H Pharmacovigilance (2003–2025)
2003
CDSCO's National PV
Programme begins
(allopathic drugs)
2007
Jamnagar workshop → PV
Cell + Ayurveda ADR form
2010
PvPI launched by CDSCO
(NCC later at IPC, Ghaziabad)
2017–18
AYUSH Central Sector Scheme
→ three-tier network
2018
PvP-ASU&H launched,
coordinated by NCC, IPC
2025
Upgraded AyushSuraksha
Portal (Supreme Court-
directed)
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 8
9.
2.2 THE ESCALATIONCHAIN
The Three-Tier PV Network for ASU&H
TIER 3 · FRONTLINE
Peripheral Pharmacovigilance Centres (PPvCs)
97 ASU&H teaching institutions / hospitals nationwide
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 9
2.2 THE ESCALATIONCHAIN
The Three-Tier PV Network for ASU&H
TIER 3 · FRONTLINE
Peripheral Pharmacovigilance Centres (PPvCs)
97 ASU&H teaching institutions / hospitals nationwide
TIER 2 · INTERMEDIARY
Intermediary Pharmacovigilance Centres (IPvCs)
5 institutes — NIA Jaipur, ITRA Jamnagar, NIUM Bengaluru, NIS Chennai, NIH Kolkata
TIER 1 · APEX
National PV Coordination Centre (NPvCC)
All India Institute of Ayurveda (AIIA), New Delhi → informs Ministry of AYUSH for regulatory action
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 11
12.
2.3 & 2.5
PvP-ASU&HProgramme & the AyushSuraksha Portal
Network of PPvCs at ASU&H teaching institutions & hospitals nationwide
Builds scientific ADR/AE reporting culture among practitioners, teachers, students
Targets heavy-metal content in Rasa aushadhis, poly-herbal interactions & quality issues
Embeds PV training into BAMS/BUMS/BSMS/BHMS curricula under NCISM's CBME
30 May 2025 — AyushSuraksha Portal
Supreme Court–directed (WP Civil 645/2022): a real-time, centralised dashboard tracking ADRs and misleading ads, letting State Licensing Authorities log complaints
— and opening direct ADR reporting to consumers and the public for the first time.
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 12
13.
SECTION 3 OF6
Adverse Drug Reaction (ADR) — Definition &
Types
Learning Objective 3 · CO4, CO5
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 13
14.
3.1 DEFINITION
What Countsas an Adverse Drug Reaction?
“A response to a drug that is noxious and unintended, occurring at doses normally used for prophylaxis, diagnosis, or
therapy of disease, or for modification of physiological function.”
— World Health Organization (WHO)
By Severity
Mild · Moderate · Severe · Lethal
By Onset
Acute (<60 min) · Sub-acute (1–24 hrs) · Latent (>2
days)
By Organ System
WHO-ART or MedDRA classification
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 14
15.
3.2 RAWLINS–THOMPSON SYSTEM
TheA–F Classification of ADRs
A — Augmented
Dose-dependent, predictable; common, low mortality
e.g. Hypoglycaemia with insulin
B — Bizarre
Dose-independent, unpredictable, immunological
e.g. Anaphylaxis with penicillin
C — Chronic
Related to cumulative dose, long-term therapy
e.g. Analgesic nephropathy
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 15
16.
3.2 RAWLINS–THOMPSON SYSTEM
TheA–F Classification of ADRs
A — Augmented
Dose-dependent, predictable; common, low mortality
e.g. Hypoglycaemia with insulin
B — Bizarre
Dose-independent, unpredictable, immunological
e.g. Anaphylaxis with penicillin
C — Chronic
Related to cumulative dose, long-term therapy
e.g. Analgesic nephropathy
D — Delayed
Manifests after some time, even post-stop
e.g. Teratogenicity, carcinogenesis
E — End of use
Occurs on abrupt withdrawal
e.g. Benzodiazepine withdrawal seizures
F — Failure
Unexpected therapeutic failure
e.g. OCP failure with enzyme inducers
Mnemonic: A-B-C-D-E-F = Augmented · Bizarre · Chronic · Delayed · End-of-use · Failure
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 16
17.
3.4 A RELATEDCONCEPT
Drug Interactions — Drug-Drug, Herb-Drug, Herb-Herb
A drug interaction occurs when the effect of one substance is altered by the presence of another — a drug, food, or herb.
Pharmacokinetic
Affects absorption, distribution, metabolism, or
excretion.
Pharmacodynamic
Additive, synergistic, or antagonistic effect at the
site of action.
Example
NSAIDs + anticoagulants → increased bleeding risk.
ASU&H Significance
Since many patients take Ayurvedic medicines alongside allopathic treatment, herb-drug interaction monitoring is a critical part of ASU&H pharmacovigilance.
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 17
18.
SECTION 4 OF6
Identification & Monitoring of ADRs
Learning Objective 4 · CO2, CO4, CO5
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 18
19.
4.1 DETECTION TOOLKIT
Methodsof ADR Detection & Monitoring
Spontaneous Reporting
Voluntary reports by professionals/patients — backbone
of PvPI/PvP-ASU&H
Intensive Hospital Monitoring
Records all ADRs in a defined hospital population
Cohort Event Monitoring
Prospective study following a defined patient cohort
Case-Control Studies
Compares drug exposure with/without a reaction
Record Linkage
Cross-links prescription & outcome databases
Meta-analysis & Data Mining
Statistical signal detection across large databases
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 19
20.
4.3 FROM BEDSIDETO REGULATOR
The ADR Reporting Workflow
WHAT TO REPORT
• All suspected ADRs, alone or in combination
• Hospitalisation, death, life-threat, disability, congenital anomaly
• Even minor / common reactions
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 20
21.
4.3 FROM BEDSIDETO REGULATOR
The ADR Reporting Workflow
WHAT TO REPORT
• All suspected ADRs, alone or in combination
• Hospitalisation, death, life-threat, disability, congenital anomaly
• Even minor / common reactions
WHO / WHERE
• Any healthcare professional can report
• Standard form → nearest PPvC / IPvC
• AyushSuraksha Portal (2025): direct public reporting too
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 21
22.
4.3 FROM BEDSIDETO REGULATOR
The ADR Reporting Workflow
WHAT TO REPORT
• All suspected ADRs, alone or in combination
• Hospitalisation, death, life-threat, disability, congenital anomaly
• Even minor / common reactions
WHO / WHERE
• Any healthcare professional can report
• Standard form → nearest PPvC / IPvC
• AyushSuraksha Portal (2025): direct public reporting too
PROCESSING FLOW
PPvC
receives
IPvC
causality (WHO-UMC)
NPvCC / AIIA
aggregates nationally
Ministry of AYUSH
regulatory action
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 22
23.
4.4 JUDGING THELINK
Causality Assessment & Severity Grading
Certain Probable Possible Unlikely Conditional Unassessable
WHO-UMC Scale — from most to least likely the drug caused the event
Naranjo Algorithm (1981)
10-question scored tool:
Score ≥9 Definite · 5–8 Probable · 1–4 Possible · ≤0 Doubtful
Severity (Hartwig & Siegel, 7 levels)
Mild (1–2) → Moderate (3–4b) → Severe (5–7)
Severe = intensive care, permanent harm, or death.
Every ADR record documents 4 dimensions: Causality + Severity + Seriousness + Preventability
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 23
24.
SECTION 5 OF6
Safe & Efficacious Use of Ayurvedic Drugs
Learning Objective 5 · CO2, CO4
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 24
25.
5.1 THE CLASSICALSAFETY FRAMEWORK
What Classical text Says About Safe Use
“A medicine correctly understood and used acts like nectar; wrongly used, it can act like poison, a weapon, fire, or a thunderbolt.” — Charaka Samhita,
Sutrasthana Ch. 1
Drug-Related Factors
Prakriti · Guna · Karma/Prabhava · Desha · Ritu
Grahitam (harvesting) · Nihitam (storage) · Upaskritam (processing)
Patient-Related Factors
Prakriti (constitution) · Vayas (age) · Vikriti (disease state)
Satmya · Satva · Ahara-shakti · Vyayama-shakti · Sara · Sanhanan · Bala
Rasashastra Safeguard: Bhasmas & herbo-mineral formulas require strict Shodhana (purification) & Marana (incineration) — deviation was recognised even in
antiquity as a cause of toxicity.
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 25
26.
SECTION 6 OF6
Debate on ADR of ASU Drugs
Learning Objective 6 · CO4, CO5
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 26
27.
6.1 DEBATE PREP
PresentChallenges in Ayurvedic Pharmacovigilance
(i) DETECTION
• ‘Inherently safe’ belief delays ADR recognition
• Little ADR coverage in curriculum
• Safety data not organised for retrieval
• Multi-system use complicates causality
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 27
28.
6.1 DEBATE PREP
PresentChallenges in Ayurvedic Pharmacovigilance
(i) DETECTION
• ‘Inherently safe’ belief delays ADR recognition
• Little ADR coverage in curriculum
• Safety data not organised for retrieval
• Multi-system use complicates causality
(ii) ASSESSMENT
• Data scattered, non-digitised
• Multi-ingredient — hard to isolate cause
• PK/toxicokinetic data largely unavailable
• Few trained in both Ayurveda + PV
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 28
29.
6.1 DEBATE PREP
PresentChallenges in Ayurvedic Pharmacovigilance
(i) DETECTION
• ‘Inherently safe’ belief delays ADR recognition
• Little ADR coverage in curriculum
• Safety data not organised for retrieval
• Multi-system use complicates causality
(ii) ASSESSMENT
• Data scattered, non-digitised
• Multi-ingredient — hard to isolate cause
• PK/toxicokinetic data largely unavailable
• Few trained in both Ayurveda + PV
(iii) PREVENTION
• 100,000+ formulations, informal sector
• Conventional–traditional communication gap
• Patients don't disclose Ayurvedic use
• Limited UG/PG attention; low industry incentive
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 29
30.
6.2 & 6.3WAY FORWARD
Strengthening PV — National Level & Future Scope
Embed PV formally into BAMS/PG curricula (NCISM competency-based) Mandate ADR reporting with clear regulatory backing
Develop Ayurveda-specific causality tools for poly-herbal complexity Leverage technology — apps, crowdsourced monitoring, digital records
Build a centralised PV research repository; run patient-awareness drives Pursue international collaboration to align with global PV standards
Pharmacovigilance completes the Quality – Safety – Efficacy triad essential for the scientific credibility and global acceptance of Ayurvedic
pharmaceutical science.
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 30
31.
Thank You
Department ofRSBK, FIAMS · Future University, Bareilly · AyUG-RB Dr.Kiran S Edayath, III BAMS
AyUG-RB Dr.Kiran S Edayath · Topic 26· Pharmacovigilance for Ayurveda Drugs 31