Comprehensive Pharmacology of Anti-Arrhythmic Drugs in Cardiovascular Therapy
Detailed overview of anti-arrhythmic drug classes, mechanisms, therapeutic uses, adverse effects, and contraindications in managing cardiac arrhythmias and improving heart rhythm and function.
Comprehensive Pharmacology of Anti-Arrhythmic Drugs in Cardiovascular Therapy
2.
PHARMACOLOGY OF DRUGSACTING ON THE CARDIOVASCULAR SYSTEM
ANTI-ARRHYTHMIC DRUGS
Introduction
Cardiac arrhythmias are disturbances in the normal rhythm, rate, or
conduction of the heartbeat resulting from abnormalities in impulse
generation or impulse conduction.
They may occur due to enhanced automaticity, triggered activity,
or re-entry mechanisms.
Anti-arrhythmic drugs are agents that restore and maintain normal
sinus rhythm by modifying the electrical activity of the myocardium.
The primary objectives of anti-arrhythmic therapy are to:
Restore normal cardiac rhythm.
Prevent recurrence of arrhythmias.
Improve cardiac output.
Reduce symptoms such as palpitations and syncope (temporary
loss of consciousness when blood flow to the brain drops)
Prevent sudden cardiac death.
3.
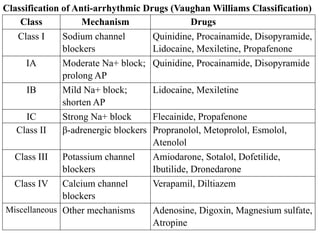
Classification of Anti-arrhythmicDrugs (Vaughan Williams Classification)
Class Mechanism Drugs
Class I Sodium channel
blockers
Quinidine, Procainamide, Disopyramide,
Lidocaine, Mexiletine, Propafenone
IA Moderate Na+ block;
prolong AP
Quinidine, Procainamide, Disopyramide
IB Mild Na+ block;
shorten AP
Lidocaine, Mexiletine
IC Strong Na+ block Flecainide, Propafenone
Class II β-adrenergic blockers Propranolol, Metoprolol, Esmolol,
Atenolol
Class III Potassium channel
blockers
Amiodarone, Sotalol, Dofetilide,
Ibutilide, Dronedarone
Class IV Calcium channel
blockers
Verapamil, Diltiazem
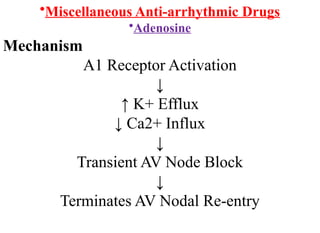
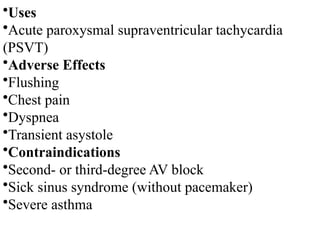
Miscellaneous Other mechanisms Adenosine, Digoxin, Magnesium sulfate,
Atropine
CLASS I -ANTI-ARRHYTHMIC DRUGS
Sodium Channel Blockers
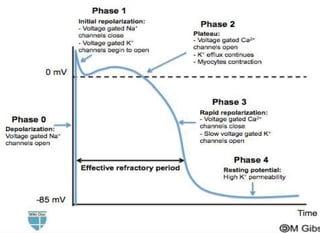
•These drugs inhibit fast sodium channels responsible for phase 0 depolarization in atrial and
ventricular muscle
Class IA Drugs
Drugs:- Quinidine, Procainamide, Disopyramide
Mechanism of Action
Administration
↓
Blocks fast Na+ channels
↓
Slows Phase 0 depolarization
↓
↓ Conduction velocity
↓
Blocks K+ channels
↓
Prolongs Action Potential Duration
↓
↑ Effective Refractory Period
↓
Suppresses Re-entry Circuits
↓
Restoration of Normal Cardiac Rhythm
7.
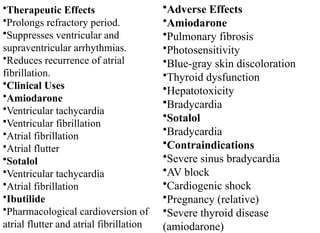
•Therapeutic Effects
•Decreases myocardialexcitability.
•Slows conduction velocity.
•Prolongs refractory period.
•Prevents re-entry arrhythmias.
•Clinical Uses
•Atrial fibrillation (a common type of irregular heart rhythm (arrhythmia)
where the upper chambers of the heart (the atria) beat chaotically and out
of sync with the lower chambers (the ventricles).)
•Atrial flutter (a type of fast heart rhythm)
•Supraventricular tachycardia
•Ventricular tachycardia
•Adverse Effects
•Quinidine
•Cinchonism (tinnitus, headache, dizziness)
•Diarrhea
•QT prolongation
•Hypotension
8.
•Procainamide
•Drug-induced lupus (rednessof skin)
•Agranulocytosis (the bone marrow stops making enough
neutrophils, a vital type of white blood cell that fights bacterial
and fungal infections.)
•Hypotension
•Disopyramide
•Dry mouth
•Urinary retention
•Constipation
•Heart failure
•Contraindications
•Complete heart block
•Long QT syndrome
•Severe hypotension
•Heart failure
9.
•Class IB Drugs
•Drugs:Lidocaine, Mexiletine
•Mechanism of Action
Drug Administration
↓
Blocks Na+ channels in ischemic myocardium
↓
Shortens Action Potential Duration
↓
Suppresses abnormal automaticity
↓
Decreases ventricular ectopic activity (extra or early
heartbeats)
↓
Controls Ventricular Arrhythmias
10.
•Therapeutic Effects
•Reduces ventricularexcitability
•Suppresses ectopic pacemakers.
•Minimal effect on normal myocardium.
•Clinical Uses
•Acute ventricular tachycardia
•Ventricular arrhythmias after myocardial infarction
•Digitalis-induced ventricular arrhythmias
•Adverse Effects
•Tremor (an involuntary, rhythmic shaking movement)
•Drowsiness
•Confusion
•Convulsions (body muscles contract and relax fast and repeatedly)
•Contraindications
•Severe SA block
•AV block
•Hypersensitivity
11.
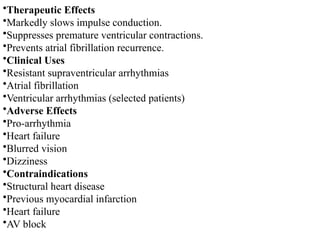
•Class IC Drugs
•Drugs:-Flecainide, Propafenone
•Mechanism of Action
Administration
↓
Marked Na+ Channel Block
↓
Marked slowing of conduction
↓
Suppresses ectopic impulses
↓
Terminates Re-entry
↓
Maintains Sinus Rhythm


 Most read





 Most read


 Most read