Vitamin Deficiency Disorders
Nutritional
Bsc Nursing 2nd semester
Mr. Govinda Gajbhiye
Bsc Nursing MSc Nursing MA clinical
psychologist
Assistant Professor
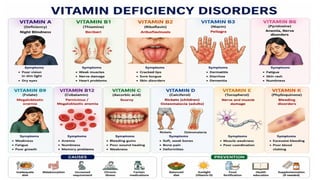
Introduction of Vitamin Deficiency Disorders
Vitamin deficiency disorders are clinical conditions that result from an
inadequate intake, absorption, utilization, or increased requirement of one or
more vitamins. Vitamins are essential organic micronutrients required in small
amounts for normal growth, metabolism, tissue maintenance, immune function,
and overall health. Deficiency of specific vitamins produces characteristic signs
and symptoms, such as night blindness (vitamin A deficiency), beriberi (vitamin
B₁ deficiency), pellagra (vitamin B₃ deficiency), scurvy (vitamin C deficiency),
rickets (vitamin D deficiency), and bleeding disorders (vitamin K deficiency).
These disorders are preventable through a balanced diet, food fortification,
nutrition education, and appropriate vitamin supplementation.
Vitamin A deficiency Disorders
Introduction:-
Vitamin A deficiency is one of the most common nutritional deficiency
disorders, particularly among children and pregnant women in developing
countries. It occurs when the body does not receive sufficient vitamin A or is
unable to absorb or utilize it properly. Vitamin A is essential for normal vision,
maintenance of epithelial tissues, immune function, growth, and
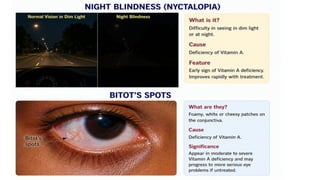
reproduction. Deficiency primarily affects the eyes, leading to night
blindness, xerophthalmia, Bitot's spots, and keratomalacia, and
Definition
Vitamin A deficiency is a nutritional disorder caused by a lack of vitamin
A in the body, leading to impaired vision, reduced immunity, and
epithelial tissue damage."
According to the World Health Organization (WHO):
"Vitamin A deficiency is a condition resulting from inadequate vitamin A
to meet the body's physiological needs, leading to impaired vision,
reduced immunity, and an increased risk of illness and death.”
According to WHO- consequences and implications?
● Night blindness is one of the first signs of vitamin A deficiency. In its more severe
forms, vitamin A deficiency contributes to blindness by making the cornea very
dry, thus damaging the retina and cornea.
● An estimated 250 000–500 000 children who are vitamin A-deficient become blind
every year, and half of them die within 12 months of losing their sight.
● Deficiency of vitamin A is associated with significant morbidity and mortality from
common childhood infections, and is the world’s leading preventable cause of
childhood blindness.
● Vitamin A deficiency also contributes to maternal mortality and other poor
outcomes of pregnancy and lactation. It also diminishes the ability to fight
infections.
● mild, subclinical deficiency can be a problem, because it may increase children's
risk for respiratory and diarrhoeal infections, decrease growth rates, slow bone
development and decrease the likelihood of survival from serious illness.
Vitamin A Deficiency – Causes
● Vegetarian diet (low intake of vitamin A-rich animal
foods)
● Zinc deficiency
● Faulty infant feeding and improper weaning practices
● Infectious diarrhea
● Use of skimmed milk (devoid of vitamin A)
● Protein-Energy Malnutrition (PEM)
Etiology
● Vegetarian diet (Low intake of vitamin A-rich animal foods)
Strict vegetarians may not consume foods containing retinol (preformed
vitamin A) such as liver, eggs, milk, and fish.
Although plant foods contain beta-carotene, poor intake or poor conversion
to vitamin A can lead to deficiency.
● Zinc deficiency
Zinc is essential for the absorption, transport, and metabolism of vitamin A.
Zinc deficiency reduces the release of vitamin A from the liver, increasing the
risk of deficiency.
● Faulty infant feeding and improper weaning practices
Delayed breastfeeding, lack of colostrum, early cessation of breastfeeding,
and delayed or inadequate complementary feeding reduce vitamin A intake.
Children become more susceptible to deficiency during rapid growth.
Etiology
● Infectious diarrhea
Recurrent diarrhea decreases the absorption of vitamin A and increases its
loss from the body.
Poor appetite during illness further reduces vitamin A intake.
● Use of skimmed milk
Vitamin A is a fat-soluble vitamin present in the fat portion of milk.
Skimmed milk has almost all fat removed, so it contains very little vitamin A.
● Protein-Energy Malnutrition (PEM)
In PEM, intake of protein and calories is inadequate.
Protein is needed to transport vitamin A in the blood, and malnutrition also
reduces liver stores of vitamin A, leading to deficiency.
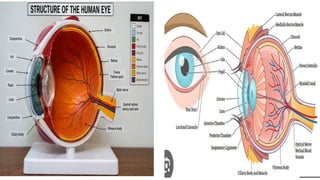
Signs and Symptoms of Vitamin A Deficiency
● Vitamin A deficiency mainly affects the eyes.
● High-risk groups: Children below 3 years, pregnant
women, and lactating mothers.
● In India, about 0.8–1.0% of preschool children have
night blindness and Bitot's spots.
Sign and symptoms of Vitamin A Deficiency
● Skin Manifestations
Dry, rough, scaly skin.
Follicular hyperkeratosis (phrynoderma or "toad
skin").
● Growth and Development
Growth retardation in children.
Delayed bone growth.
● Immune System
Frequent infections due to reduced immunity.
Recurrent respiratory infections.
Recurrent diarrhea.
● Epithelial Changes
Dryness of mucous
membranes.
Poor wound healing.
Increased susceptibility to
infections.
● General Manifestations
Loss of appetite.
Weakness and fatigue.
Increased risk of severe illness
and death in young children.
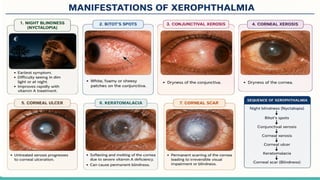
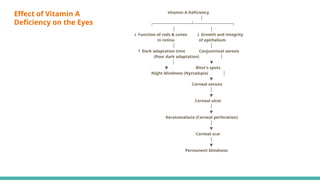
Effect of Vitamin A
Deficiency on the Eyes
Vitamin A Deficiency
│
┌────────────────┴────────────────┐
│ │
↓ Function of rods & cones Growth and integrity
↓
in retina of epithelium
│ │
↑ Dark adaptation time Conjunctival xerosis
(Poor dark adaptation) │
│ ▼
▼ Bitot's spots
Night blindness (Nyctalopia) │
▼
Corneal xerosis
│
▼
Corneal ulcer
│
▼
Keratomalacia (Corneal perforation)
│
▼
Corneal scar
│
▼
Permanent blindness
Treatment of Vitamin A Deficiency
Short-term treatment
Oral administration of a large dose of Vitamin A
(Retinol palmitate):
Immediately after diagnosis: Give 2 lakh IU (200,000
IU) of Vitamin A orally.
After 1–4 weeks: Give another 2 lakh IU (200,000 IU)
orally.
Note: Infants receive age-appropriate lower doses as
per national/WHO guidelines.
Treatment
1. Vitamin A Supplementation (Therapeutic Dose)
Children aged 12 months or older:
200,000 IU orally on Day 1
200,000 IU on Day 2
200,000 IU after 2 weeks
Infants 6–11 months:
100,000 IU orally on the same schedule (Day 1, Day 2, after 2 weeks)
Infants below 6 months:
50,000 IU orally on the same schedule
If the child cannot swallow or has persistent vomiting, an intramuscular
water-miscible vitamin A preparation may be used.
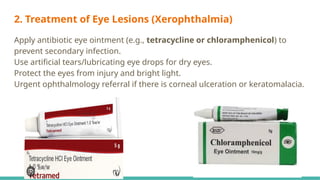
2. Treatment of Eye Lesions (Xerophthalmia)
Apply antibiotic eye ointment (e.g., tetracycline or chloramphenicol) to
prevent secondary infection.
Use artificial tears/lubricating eye drops for dry eyes.
Protect the eyes from injury and bright light.
Urgent ophthalmology referral if there is corneal ulceration or keratomalacia.
3. Nutritional Management
4. Treat Associated Illnesses
1.measles
Vitamin A (WHO therapeutic dose)
Paracetamol 10–15 mg/kg/dose every 4–6 hours for fever
Antibiotics only if there is a secondary bacterial infection (e.g., pneumonia or otitis media).,
2. Diarrhea
ORS (Oral Rehydration Solution) after each loose stool
Zinc
<6 months: 10 mg once daily for 10–14 days
≥6 months: 20 mg once daily for 10–14 days
IV fluids if severe dehydration.
3. Respiratory Tract Infection
Amoxicillin 40–50 mg/kg/day orally in divided doses for mild bacterial infection (or as per local
guideline)
Severe pneumonia: Ampicillin + Gentamicin or Ceftriaxone (hospital treatment)
Paracetamol for fever.
4. Intestinal Worms
Albendazole
1–2 years: 200 mg single dose
≥2 years: 400 mg single dose
Alternatively, Mebendazole 100 mg twice daily for 3 days (or 500 mg single dose).
Role of Nurses in Prevention and
Management of Vitamin A Deficiency
● Assess nutritional status of children and identify those at risk of vitamin A deficiency.
● Recognize early signs and symptoms such as night blindness, Bitot's spots, and
xerophthalmia.
● Administer vitamin A supplements according to national guidelines.
● Promote exclusive breastfeeding for the first 6 months and continued breastfeeding with
complementary feeding.
● Educate parents and caregivers about vitamin A-rich foods and proper child-feeding practices.
● Monitor growth and development regularly and identify malnutrition early.
● Encourage complete immunization, especially against measles.
● Treat and refer children with severe deficiency, eye complications, or associated illnesses
promptly.
● Promote hygiene, sanitation, and deworming to reduce infections that worsen vitamin A
deficiency.
● Maintain records and participate in community nutrition programs and health education
activities.