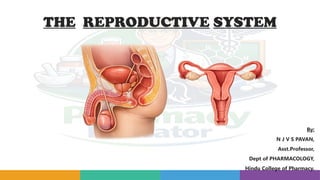
THE REPRODUCTIVE SYSTEM
By:
N J V S PAVAN,
Asst.Professor,
Dept of PHARMACOLOGY,
Hindu College of Pharmacy.
Purpose:
1.Continuation of Species Ensures survival of a species by producing new individuals.
2.Transmission of Genetic Material Passes DNA from one generation to the next, preserving traits.
3.Variation & Evolution Sexual reproduction introduces genetic variation, which drives adaptation
and evolution.
FEMALE REPRODUCTIVE SYSTEM
‍
⚕️
‍
️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
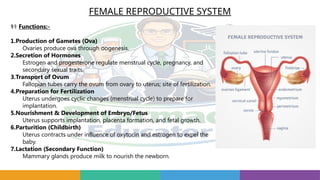
⚕️Functions:-
1.Production of Gametes (Ova)
Ovaries produce ova through oogenesis.
2.Secretion of Hormones
Estrogen and progesterone regulate menstrual cycle, pregnancy, and
secondary sexual traits.
3.Transport of Ovum
Fallopian tubes carry the ovum from ovary to uterus; site of fertilization.
4.Preparation for Fertilization
Uterus undergoes cyclic changes (menstrual cycle) to prepare for
implantation.
5.Nourishment & Development of Embryo/Fetus
Uterus supports implantation, placenta formation, and fetal growth.
6.Parturition (Childbirth)
Uterus contracts under influence of oxytocin and estrogen to expel the
baby.
7.Lactation (Secondary Function)
Mammary glands produce milk to nourish the newborn.
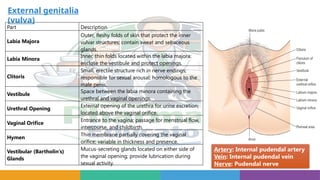
External genitalia
(vulva)
Part Description
Labia Majora
Outer, fleshy folds of skin that protect the inner
vulvar structures; contain sweat and sebaceous
glands.
Labia Minora
Inner, thin folds located within the labia majora;
enclose the vestibule and protect openings.
Clitoris
Small, erectile structure rich in nerve endings;
responsible for sexual arousal; homologous to the
male penis.
Vestibule
Space between the labia minora containing the
urethral and vaginal openings.
Urethral Opening
External opening of the urethra for urine excretion;
located above the vaginal orifice.
Vaginal Orifice
Entrance to the vagina; passage for menstrual flow,
intercourse, and childbirth.
Hymen
Thin membrane partially covering the vaginal
orifice; variable in thickness and presence.
Vestibular (Bartholin’s)
Glands
Mucus secreting glands located on either side of
‑
the vaginal opening; provide lubrication during
sexual activity.
Artery: Internal pudendal artery
Vein: Internal pudendal vein
Nerve: Pudendal nerve
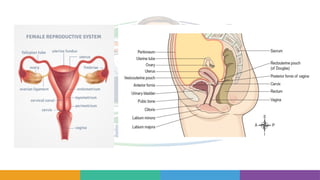
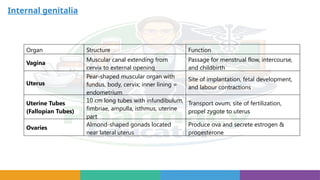
Internal genitalia
Organ Structure Function
Vagina
Muscular canal extending from
cervix to external opening
Passage for menstrual flow, intercourse,
and childbirth
Uterus
Pear shaped muscular organ with
‑
fundus, body, cervix; inner lining =
endometrium
Site of implantation, fetal development,
and labour contractions
Uterine Tubes
(Fallopian Tubes)
10 cm long tubes with infundibulum,
fimbriae, ampulla, isthmus, uterine
part
Transport ovum, site of fertilization,
propel zygote to uterus
Ovaries
Almond shaped gonads located
‑
near lateral uterus
Produce ova and secrete estrogen &
progesterone
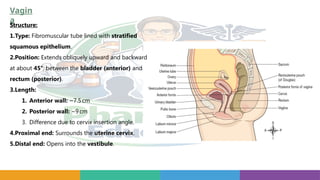
Vagin
a
Structure:
1.Type: Fibromuscular tube lined with stratified
squamous epithelium.
2.Position: Extends obliquely upward and backward
at about 45°, between the bladder (anterior) and
rectum (posterior).
3.Length:
1. Anterior wall: ~7.5cm
2. Posterior wall: ~9cm
3. Difference due to cervix insertion angle.
4.Proximal end: Surrounds the uterine cervix.
5.Distal end: Opens into the vestibule.
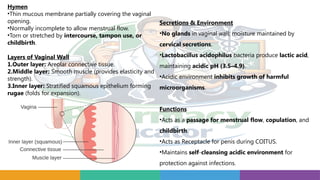
Hymen
•Thin mucous membrane partially covering the vaginal
opening.
•Normally incomplete to allow menstrual flow.
•Torn or stretched by intercourse, tampon use, or
childbirth.
Layers of Vaginal Wall
1.Outer layer: Areolar connective tissue.
2.Middle layer: Smooth muscle (provides elasticity and
strength).
3.Inner layer: Stratified squamous epithelium forming
rugae (folds for expansion).
Secretions & Environment
•No glands in vaginal wall; moisture maintained by
cervical secretions.
•Lactobacillus acidophilus bacteria produce lactic acid,
maintaining acidic pH (3.5–4.9).
•Acidic environment inhibits growth of harmful
microorganisms.
Functions
•Acts as a passage for menstrual flow, copulation, and
childbirth.
•Acts as Receptacle for penis during COITUS.
•Maintains self cleansing acidic environment
‑ for
protection against infections.
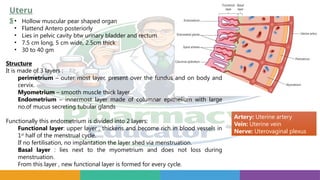
Uteru
s• Hollow muscular pear shaped organ
• Flattend Antero posteriorly
• Lies in pelvic cavity btw urinary bladder and rectum
• 7.5 cm long, 5 cm wide, 2.5cm thick
• 30 to 40 gm
Structure
It is made of 3 layers :
perimetrium – outer most layer, present over the fundus and on body and
cervix.
Myometrium – smooth muscle thick layer.
Endometrium – innermost layer made of columnar epithelium with large
no.of mucus secreting tubular glands
Functionally this endometrium is divided into 2 layers:
Functional layer: upper layer , thickens and become rich in blood vessels in
1st
half of the menstrual cycle.
If no fertilisation, no implantation the layer shed via menstruation.
Basal layer : lies next to the myometrium and does not loss during
menstruation.
From this layer , new functional layer is formed for every cycle.
Artery: Uterine artery
Vein: Uterine vein
Nerve: Uterovaginal plexus
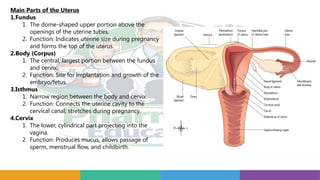
Main Parts of the Uterus
1.Fundus
1. The dome shaped upper portion above the
‑
openings of the uterine tubes.
2. Function: Indicates uterine size during pregnancy
and forms the top of the uterus.
2.Body (Corpus)
1. The central, largest portion between the fundus
and cervix.
2. Function: Site for implantation and growth of the
embryo/fetus.
3.Isthmus
1. Narrow region between the body and cervix.
2. Function: Connects the uterine cavity to the
cervical canal; stretches during pregnancy.
4.Cervix
1. The lower, cylindrical part projecting into the
vagina.
2. Function: Produces mucus, allows passage of
sperm, menstrual flow, and childbirth.
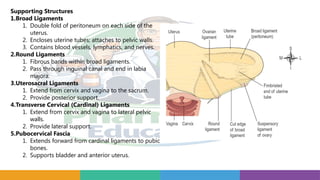
Supporting Structures
1.Broad Ligaments
1. Double fold of peritoneum on each side of the
uterus.
2. Encloses uterine tubes; attaches to pelvic walls.
3. Contains blood vessels, lymphatics, and nerves.
2.Round Ligaments
1. Fibrous bands within broad ligaments.
2. Pass through inguinal canal and end in labia
majora.
3.Uterosacral Ligaments
1. Extend from cervix and vagina to the sacrum.
2. Provide posterior support.
4.Transverse Cervical (Cardinal) Ligaments
1. Extend from cervix and vagina to lateral pelvic
walls.
2. Provide lateral support.
5.Pubocervical Fascia
1. Extends forward from cardinal ligaments to pubic
bones.
2. Supports bladder and anterior uterus.
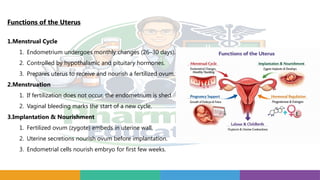
Functions of the Uterus
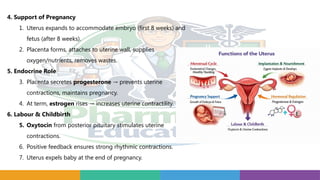
1.Menstrual Cycle
1. Endometrium undergoes monthly changes (26–30 days).
2. Controlled by hypothalamic and pituitary hormones.
3. Prepares uterus to receive and nourish a fertilized ovum.
2.Menstruation
1. If fertilization does not occur, the endometrium is shed.
2. Vaginal bleeding marks the start of a new cycle.
3.Implantation & Nourishment
1. Fertilized ovum (zygote) embeds in uterine wall.
2. Uterine secretions nourish ovum before implantation.
3. Endometrial cells nourish embryo for first few weeks.
4. Support of Pregnancy
1. Uterus expands to accommodate embryo (first 8 weeks) and
fetus (after 8 weeks).
2. Placenta forms, attaches to uterine wall, supplies
oxygen/nutrients, removes wastes.
5. Endocrine Role
3. Placenta secretes progesterone prevents uterine
→
contractions, maintains pregnancy.
4. At term, estrogen rises increases uterine contractility.
→
6. Labour & Childbirth
5. Oxytocin from posterior pituitary stimulates uterine
contractions.
6. Positive feedback ensures strong rhythmic contractions.
7. Uterus expels baby at the end of pregnancy.
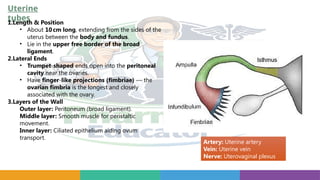
Uterine
tubes
1.Length & Position
• About 10cm long, extending from the sides of the
uterus between the body and fundus.
• Lie in the upper free border of the broad
ligament.
2.Lateral Ends
• Trumpet shaped
‑ ends open into the peritoneal
cavity near the ovaries.
• Have finger like projections (fimbriae)
‑ — the
ovarian fimbria is the longest and closely
associated with the ovary.
3.Layers of the Wall
Outer layer: Peritoneum (broad ligament).
Middle layer: Smooth muscle for peristaltic
movement.
Inner layer: Ciliated epithelium aiding ovum
transport.
Artery: Uterine artery
Vein: Uterine vein
Nerve: Uterovaginal plexus
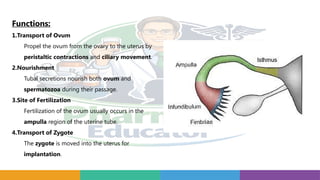
Functions:
1.Transport of Ovum
Propel the ovum from the ovary to the uterus by
peristaltic contractions and ciliary movement.
2.Nourishment
Tubal secretions nourish both ovum and
spermatozoa during their passage.
3.Site of Fertilization
Fertilization of the ovum usually occurs in the
ampulla region of the uterine tube.
4.Transport of Zygote
The zygote is moved into the uterus for
implantation.
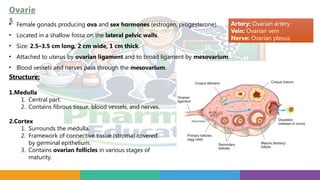
Ovarie
s
• Female gonads producing ova and sex hormones (estrogen, progesterone).
• Located in a shallow fossa on the lateral pelvic walls.
• Size: 2.5–3.5 cm long, 2 cm wide, 1 cm thick.
• Attached to uterus by ovarian ligament and to broad ligament by mesovarium.
• Blood vessels and nerves pass through the mesovarium.
Structure:
1.Medulla
1. Central part.
2. Contains fibrous tissue, blood vessels, and nerves.
2.Cortex
1. Surrounds the medulla.
2. Framework of connective tissue (stroma) covered
by germinal epithelium.
3. Contains ovarian follicles in various stages of
maturity.
Artery: Ovarian artery
Vein: Ovarian vein
Nerve: Ovarian plexus
Functional Activity:
•Before puberty: Ovaries inactive; contain primordial follicles.
•After puberty: Follicles mature cyclically (~every 28 days).
•Ovulation: Mature (Graafian) follicle ruptures, releasing ovum into
peritoneal cavity.
•Corpus luteum: Formed from ruptured follicle; secretes hormones.
•Corpus albicans: Fibrous scar left after corpus luteum regresses.
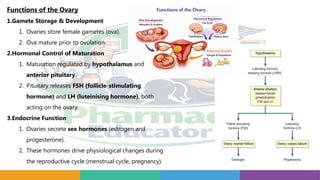
Functions of the Ovary
1.Gamete Storage & Development
1. Ovaries store female gametes (ova).
2. Ova mature prior to ovulation.
2.Hormonal Control of Maturation
1. Maturation regulated by hypothalamus and
anterior pituitary.
2. Pituitary releases FSH (follicle stimulating
‑
hormone) and LH (luteinising hormone), both
acting on the ovary.
3.Endocrine Function
1. Ovaries secrete sex hormones (estrogen and
progesterone).
2. These hormones drive physiological changes during
the reproductive cycle (menstrual cycle, pregnancy).
Puberty in the Female
1.Age of Onset:
• Usually between 12–14 years.
• Marks the menarche — beginning of the childbearing period.
2.Hormonal Control:
• Anterior pituitary secretes FSH and LH (gonadotrophins).
• These stimulate the ovaries to mature and function.
3.Physical Changes:
1. Maturation of uterus, uterine tubes, and ovaries.
2. Menstrual cycle and ovulation begin.
3. Breast development and enlargement.
4. Growth of pubic and axillary hair.
5. Increase in height and widening of pelvis.
6. Fat deposition in hips and breasts.
The reproductive
cycle
Cycle Characteristics: Averages 28 days (ranging from
26 to 30 days) and occurs regularly between menarche
and menopause. Changes take place concurrently in the
ovaries and uterine lining.
Negative Feedback Loop: The cycle is strictly regulated
by negative feedback mechanisms.
Hypothalamus: Secretes luteinising hormone-releasing
hormone (LHRH), which directs the anterior pituitary.
•Feedback response: Stimulated by high levels of
oestrogen alone (first half of cycle) but suppressed by
oestrogen and progesterone together (second half of
cycle).
Anterior Pituitary: Secretes two key hormones:
• FSH: Predominantly active in the first half;
suppressed after ovulation to prevent other follicles
from maturing.
• LH: Triggers ovulation and corpus luteum
development.
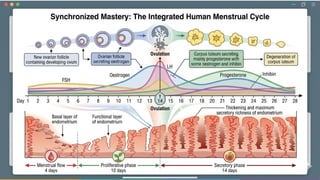
PHASES OF THE CYCLE
Menstrual Phase (≈4 days)
• Occurs when the ovum is not fertilised.
• The corpus luteum from the previous cycle degenerates.
• Progesterone and oestrogen fall sharply the functional layer of the endometrium (dependent on these
→
hormones) sheds.
• Menstrual flow consists of: secretions from endometrial glands, endometrial cells, blood from degenerating
capillaries, and the unfertilised ovum.
• Low hormone levels allow the hypothalamus and pituitary to resume activity FSH rises new cycle begins.
→ →
Proliferative Phase (≈10 days)
• FSH stimulates an ovarian follicle to grow toward maturity secretes increasing oestrogen.
→
• Estrogen endometrium thickens, becomes highly vascular, and rich in mucus-secreting glands
→
(preparing to receive a fertilised ovum).
• Mid cycle: Rising estrogen triggers an LH surge.
‑
• LH surge triggers ovulation (marking the end of this phase).
→
Secretory Phase (≈14 days)
• LH ruptured follicle develops into the corpus luteum secretes progesterone, some estrogen, and inhibin.
→ →
• Progesterone endometrium becomes oedematous (swollen with fluid) and secretory glands produce
→
increased watery mucus.
• Widespread Lubrication: Watery mucus increases in the cervix, glands of the uterine tubes, and cervical
glands that lubricate the vagina aids sperm passage.
→
• Fertile Window Constraints: * Ovum is viable/fertilisable for as little as 8 hours.
• Spermatozoa are capable of fertilising for about 24 hours, although they can survive for several days
in the reproductive tract.
• Observable signs: Cervical mucus becomes thin, watery, and elastic; body temperature rises by about 1°C
immediately following ovulation; some experience mid cycle abdominal discomfort (due to follicle rupture).
‑
• Progesterone + estrogen + inhibin suppress the hypothalamus and anterior pituitary FSH & LH fall
→ →
prevents new follicular development.
•If no fertilization falling LH causes corpus luteum to die (it depends on LH for survival) hormone levels fall
→ →
menstruation begins.
→
If Fertilisation Occurs
• No breakdown of the endometrium and no menstruation.
• The fertilised ovum (zygote) travels through the uterine tube to the uterus where it embeds in the wall.
• The embryo secretes human chorionic gonadotrophin (hCG), which is structurally similar to anterior
pituitary LH.
• hCG maintains the corpus luteum intact.
•Corpus luteum continues progesterone & estrogen secretion for the first 3–4 months, actively inhibiting
the maturation of further ovarian follicles.
• Placenta eventually develops and takes over hormone production (estrogen, progesterone, and
gonadotrophins).
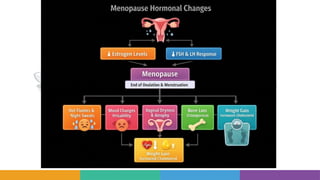
Menopaus
e
Age of Onset & Timeline
•Usually occurs between 45 and 55 years.
•Marks the definitive end of the childbearing (reproductive) period.
•Duration: May occur suddenly or develop over a period of years (sometimes as long as 10 years).
Underlying Process & Hormonal Mechanism
•Primary Cause: Driven by a progressive reduction in estrogen levels as the number of functional follicles in
the ovaries naturally declines with age.
•Hormonal Resistance: The ovaries gradually become less responsive to FSH (follicle-stimulating hormone)
and LH (luteinizing hormone).
•Final Transition: Ovulation and the menstrual cycle become irregular and eventually cease entirely.
Associated Phenomena & Systemic Changes
•Vasomotor Changes: Short-term and unpredictable episodes of vasodilation leading to flushing (hot flashes),
sweating, and palpitations—causing discomfort and disrupting normal sleep patterns.
•Anatomical Atrophy: Atrophy of the sex organs, shrinkage of the breasts, and a gradual thinning of the skin.
•Hair Changes: Axillary (underarm) and pubic hair become sparse.
•Psychological Impact: Episodes of uncharacteristic behavior, such as irritability and mood changes.
•Skeletal Health: Loss of bone mass that predisposes postmenopausal women to osteoporosis .
•Cardiovascular Health: A slow increase in blood cholesterol levels, which elevates the risk of cardiovascular
disease to the same level seen in men of the same age.
Secondary / Induced Causes
•Artificial Menopause: The exact same physiological changes can be triggered artificially following bilateral
irradiation (radiation therapy) or the surgical removal of the ovaries.
MALE REPRODUCTIVE SYSTEM:
‍
⚕️
‍
️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
⚕️
‍
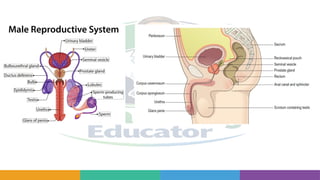
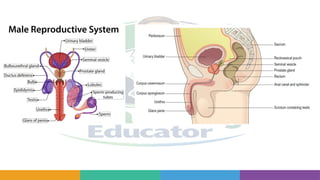
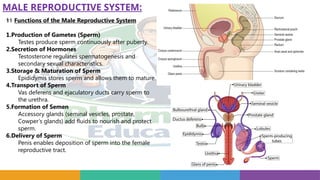
⚕️Functions of the Male Reproductive System
1.Production of Gametes (Sperm)
Testes produce sperm continuously after puberty.
2.Secretion of Hormones
Testosterone regulates spermatogenesis and
secondary sexual characteristics.
3.Storage & Maturation of Sperm
Epididymis stores sperm and allows them to mature.
4.Transport of Sperm
Vas deferens and ejaculatory ducts carry sperm to
the urethra.
5.Formation of Semen
Accessory glands (seminal vesicles, prostate,
Cowper’s glands) add fluids to nourish and protect
sperm.
6.Delivery of Sperm
Penis enables deposition of sperm into the female
reproductive tract.
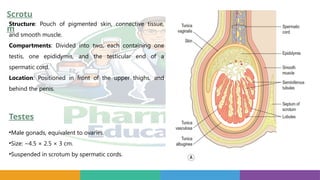
Structure: Pouch of pigmented skin, connective tissue,
and smooth muscle.
Compartments: Divided into two, each containing one
testis, one epididymis, and the testicular end of a
spermatic cord.
Location: Positioned in front of the upper thighs, and
behind the penis.
Scrotu
m
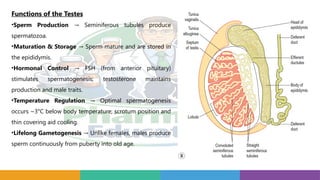
Testes
•Male gonads, equivalent to ovaries.
•Size: ~4.5 × 2.5 × 3 cm.
•Suspended in scrotum by spermatic cords.
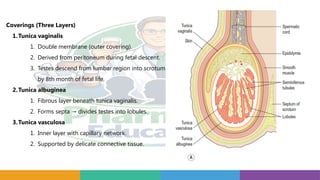
Coverings (Three Layers)
1.Tunica vaginalis
1. Double membrane (outer covering).
2. Derived from peritoneum during fetal descent.
3. Testes descend from lumbar region into scrotum
by 8th month of fetal life.
2.Tunica albuginea
1. Fibrous layer beneath tunica vaginalis.
2. Forms septa divides testes into lobules.
→
3.Tunica vasculosa
1. Inner layer with capillary network.
2. Supported by delicate connective tissue.
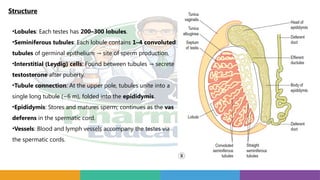
Structure
•Lobules: Each testes has 200–300 lobules.
•Seminiferous tubules: Each lobule contains 1–4 convoluted
tubules of germinal epithelium site of sperm production.
→
•Interstitial (Leydig) cells: Found between tubules secrete
→
testosterone after puberty.
•Tubule connection: At the upper pole, tubules unite into a
single long tubule (~6 m), folded into the epididymis.
•Epididymis: Stores and matures sperm; continues as the vas
deferens in the spermatic cord.
•Vessels: Blood and lymph vessels accompany the testes via
the spermatic cords.
Functions of the Testes
•Sperm Production Seminiferous tubules produce
→
spermatozoa.
•Maturation & Storage Sperm mature and are stored in
→
the epididymis.
•Hormonal Control FSH (from anterior pituitary)
→
stimulates spermatogenesis; testosterone maintains
production and male traits.
•Temperature Regulation Optimal spermatogenesis
→
occurs ~3°C below body temperature; scrotum position and
thin covering aid cooling.
•Lifelong Gametogenesis Unlike females, males produce
→
sperm continuously from puberty into old age.
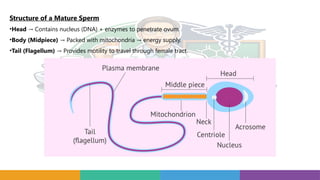
Structure of a Mature Sperm
•Head Contains nucleus (DNA) + enzymes to penetrate ovum.
→
•Body (Midpiece) Packed with mitochondria energy supply.
→ →
•Tail (Flagellum) Provides motility to travel through female tract.
→
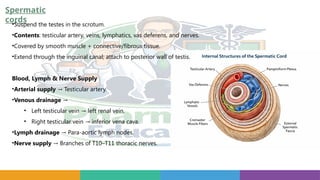
Spermatic
cords
•Suspend the testes in the scrotum.
•Contents: testicular artery, veins, lymphatics, vas deferens, and nerves.
•Covered by smooth muscle + connective/fibrous tissue.
•Extend through the inguinal canal; attach to posterior wall of testis.
Blood, Lymph & Nerve Supply
•Arterial supply Testicular artery.
→
•Venous drainage →
• Left testicular vein left renal vein.
→
• Right testicular vein inferior vena cava.
→
•Lymph drainage Para aortic lymph nodes.
→ ‑
•Nerve supply Branches of T10–T11 thoracic nerves.
→
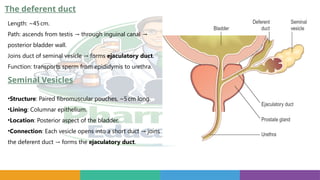
The deferent duct
Length: ~45cm.
Path: ascends from testis through inguinal canal
→ →
posterior bladder wall.
Joins duct of seminal vesicle forms
→ ejaculatory duct.
Function: transports sperm from epididymis to urethra.
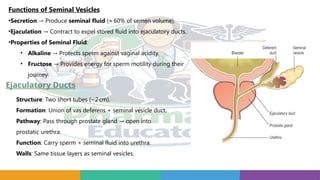
Seminal Vesicles
•Structure: Paired fibromuscular pouches, ~5cm long.
•Lining: Columnar epithelium.
•Location: Posterior aspect of the bladder.
•Connection: Each vesicle opens into a short duct joins
→
the deferent duct forms the
→ ejaculatory duct.
Functions of Seminal Vesicles
•Secretion Produce
→ seminal fluid (≈60% of semen volume).
•Ejaculation Contract to expel stored fluid into ejaculatory ducts.
→
•Properties of Seminal Fluid:
• Alkaline Protects sperm against vaginal acidity.
→
• Fructose Provides energy for sperm motility during their
→
journey.
Ejaculatory Ducts
Structure: Two short tubes (~2cm).
Formation: Union of vas deferens + seminal vesicle duct.
Pathway: Pass through prostate gland open into
→
prostatic urethra.
Function: Carry sperm + seminal fluid into urethra.
Walls: Same tissue layers as seminal vesicles.
Functions of the Prostate
•Secretion Produces thin, milky fluid (~30% of semen volume).
→
•Appearance Gives semen its characteristic milky look.
→
•Clotting enzyme Thickens semen in the vagina.
→
•Purpose Helps retain semen near the cervix, increasing chances
→
of fertilization.
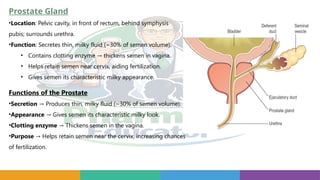
Prostate Gland
•Location: Pelvic cavity, in front of rectum, behind symphysis
pubis; surrounds urethra.
•Function: Secretes thin, milky fluid (~30% of semen volume).
• Contains clotting enzyme thickens semen in vagina.
→
• Helps retain semen near cervix, aiding fertilization.
• Gives semen its characteristic milky appearance.
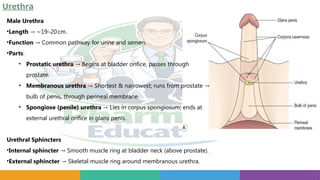
Urethra
Male Urethra
•Length ~19–20cm.
→
•Function Common pathway for urine and semen.
→
•Parts:
• Prostatic urethra Begins at bladder orifice, passes through
→
prostate.
• Membranous urethra Shortest & narrowest; runs from prostate
→ →
bulb of penis, through perineal membrane.
• Spongiose (penile) urethra Lies in corpus spongiosum; ends at
→
external urethral orifice in glans penis.
Urethral Sphincters
•Internal sphincter Smooth muscle ring at bladder neck (above prostate).
→
•External sphincter Skeletal muscle ring around membranous urethra.
→
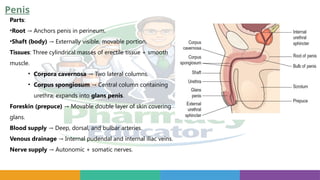
Penis
Parts:
•Root Anchors penis in perineum.
→
•Shaft (body) Externally visible, movable portion.
→
Tissues: Three cylindrical masses of erectile tissue + smooth
muscle.
• Corpora cavernosa Two lateral columns.
→
• Corpus spongiosum Central column containing
→
urethra; expands into glans penis.
Foreskin (prepuce) Movable double layer of skin covering
→
glans.
Blood supply Deep, dorsal, and bulbar arteries.
→
Venous drainage Internal pudendal and internal iliac veins.
→
Nerve supply Autonomic + somatic nerves.
→
Functions
•Erection Parasympathetic stimulation arteriolar
→ →
dilation + venoconstriction erectile tissue fills with blood.
→
•Reproduction Provides pathway for semen (sperm +
→
fluids).
•Sperm fate If not ejaculated, sperm lose fertility over
→
months and are reabsorbed by epididymis.
Ejaculation Process
•Triggered during male orgasm.
•Pathway: Sperm expelled from epididymis deferent duct ejaculatory duct urethra.
→ → →
•Mechanism:
• Powerful rhythmic contractions of smooth muscle in vas deferens (sympathetic control).
• Seminal vesicles + prostate also contract add their secretions.
→
•Result: Semen emitted through external urethral sphincter.
Semen Composition
•Spermatozoa ~10% of ejaculate.
→
•Seminal fluid 50–60% (alkaline, fructose rich).
→ ‑
•Prostatic fluid 20–30% (milky, clotting enzyme).
→
•Mucus from urethra.
→
•Volume 2–5mL per ejaculate.
→
•Sperm count ~40–100 million per mL.
→
•pH Slightly alkaline neutralizes vaginal acidity.
→ →
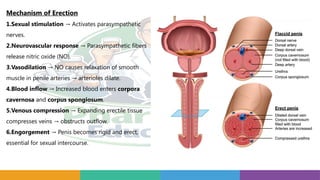
Mechanism of Erection
1.Sexual stimulation Activates parasympathetic
→
nerves.
2.Neurovascular response Parasympathetic fibers
→
release nitric oxide (NO).
3.Vasodilation NO causes relaxation of smooth
→
muscle in penile arteries arterioles dilate.
→
4.Blood inflow Increased blood enters
→ corpora
cavernosa and corpus spongiosum.
5.Venous compression Expanding erectile tissue
→
compresses veins obstructs outflow.
→
6.Engorgement Penis becomes rigid and erect,
→
essential for sexual intercourse.
Method Who Uses How It’s Used Advantages
Disadvantage
s
When to Use
Safety
Precautions
Rhythm/Natural
(Calendar,
Withdrawal)
Couples with
regular cycles
Avoid sex during
fertile days /
withdraw before
ejaculation
No cost, natural
Very unreliable,
high failure
If cycles are
predictable
Not suitable for
irregular cycles
Barrier
(Condoms,
Diaphragm,
Cervical Cap,
Sponge)
Men & women
Worn before
intercourse
Prevents
pregnancy &
STIs (condoms),
inexpensive
May slip/tear,
irritation
Anytime, esp. for
STI protection
Use new
condom each
act; avoid oil-
based lubricants
with latex
Chemical
(Spermicides)
Women
Foams, jellies,
sponges
Easy, inexpensive
Messy, irritation,
lower
effectiveness
Backup method
Use with barrier
for better
protection
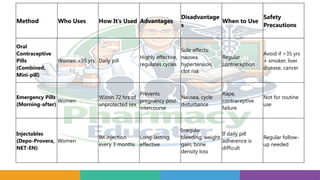
Methods of Contraception
Oral
Contraceptive
Pills
(Combined,
Mini-pill)
Women <35 yrs Daily pill
Highly effective,
regulates cycles
Side effects:
nausea,
hypertension,
clot risk
Regular
contraception
Avoid if >35 yrs
+ smoker, liver
disease, cancer
Emergency Pills
(Morning-after)
Women
Within 72 hrs of
unprotected sex
Prevents
pregnancy post-
intercourse
Nausea, cycle
disturbance
Rape,
contraceptive
failure
Not for routine
use
Injectables
(Depo-Provera,
NET-EN)
Women
IM injection
every 3 months
Long-lasting,
effective
Irregular
bleeding, weight
gain, bone
density loss
If daily pill
adherence is
difficult
Regular follow-
up needed
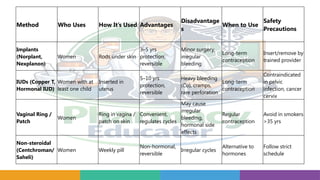
Method Who Uses How It’s Used Advantages
Disadvantage
s
When to Use
Safety
Precautions
Implants
(Norplant,
Nexplanon)
Women Rods under skin
3–5 yrs
protection,
reversible
Minor surgery,
irregular
bleeding
Long-term
contraception
Insert/remove by
trained provider
IUDs (Copper T,
Hormonal IUD)
Women with at
least one child
Inserted in
uterus
5–10 yrs
protection,
reversible
Heavy bleeding
(Cu), cramps,
rare perforation
Long-term
contraception
Contraindicated
in pelvic
infection, cancer
cervix
Vaginal Ring /
Patch
Women
Ring in vagina /
patch on skin
Convenient,
regulates cycles
May cause
irregular
bleeding,
hormonal side
effects
Regular
contraception
Avoid in smokers
>35 yrs
Non-steroidal
(Centchroman/
Saheli)
Women Weekly pill
Non-hormonal,
reversible
Irregular cycles
Alternative to
hormones
Follow strict
schedule
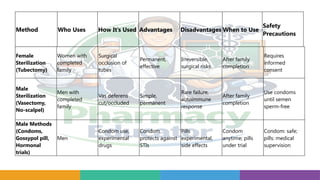
Method Who Uses How It’s Used Advantages
Disadvantage
s
When to Use
Safety
Precautions
Female
Sterilization
(Tubectomy)
Women with
completed
family
Surgical
occlusion of
tubes
Permanent,
effective
Irreversible,
surgical risks
After family
completion
Requires
informed
consent
Male
Sterilization
(Vasectomy,
No-scalpel)
Men with
completed
family
Vas deferens
cut/occluded
Simple,
permanent
Rare failure,
autoimmune
response
After family
completion
Use condoms
until semen
sperm-free
Male Methods
(Condoms,
Gossypol pill,
Hormonal
trials)
Men
Condom use,
experimental
drugs
Condom
protects against
STIs
Pills
experimental,
side effects
Condom
anytime; pills
under trial
Condom: safe;
pills: medical
supervision
Method Who Uses How It’s Used Advantages Disadvantages When to Use
Safety
Precautions
Comprehensive Overview of the Female Reproductive System and Its Functions