ANTIPSYCHIATRY MOVEMENT
DR HARI RAM SEDAI
3RD
YEAR RESIDENT
DEPARTMENT OF PSYCHIATRY
NMCTH/ BIRGUNJ
Contents
Introduction
Historical Background
Origins of the Anti-Psychiatry Movement
Major Thinkers and Their Contributions
Decline of Anti-Psychiatry
Critical Psychiatry
Limitations and Criticism
Summary
Introduction
 Psychiatry
• Term coined in 1808 by German physician and anatomist Johann
Christian Reil (1759 –1813).
• Greek word Psyche: soul, iatry: medical treatment.
• Branch of medicine which focuses on the diagnosis, treatment and
prevention of mental, emotional and behavioral disorders. ( APA 2019 )
Antipsychiatry
• The term “anti-psychiatry” was coined in 1912 by Bernhard
Beyer.
• David Cooper (1931–1986), South African Psychiatrist
popularized the term in a controversial book entitled
‘Psychiatry and Anti-Psychiatry’ (1967).
• Emerged as an international movement during 1960s.
• A movement that encompasses a diverse set of theories and
practices that challenge and stand against the fundamental
theories and practices of Psychiatry. David Cooper (1931–1986)
 Common Understanding:
• The antipsychiatry movement isn't a single organization.
• A critical stance against mainstream psychiatry.
• Not a unified ideology but a collection of related criticisms.
• Represents a paradigm shift in understanding mental health.
• Collection of critics, activists, former patients, and sometimes
even psychiatrists themselves who challenge the very foundations
of psychiatric practice.
Anti-psychiatry demonstration in Edinburgh, Scotland,
June 2005.
Occupy the American Psychiatric Association in
Philadelphia, Pennsylvania, May 6, 2012.
 The movement includes:
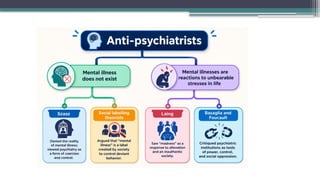
• Radical psychiatrists like R.D. Laing and Thomas Szasz.
• Philosophers like Michel Foucault.
• Sociologists like Erving Goffman.
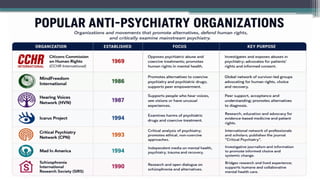
• Thousands of former patients and social activist who formed the survivor
movement.
• They argue that Psychiatrist are not merely treating diseases; and are
enforcing social norms.
• Psychiatrist are deciding who is 'mad' and who is 'sane' based on cultural
values, not biological facts.
Why a Psychiatrist Should Care
• The critique has shaped public perception and policy.
• It raises core ethical questions about our practice.
• It forces us to examine our own assumptions and power.
• By engaging with it, we can strengthen our practice and rebuild
trust."
Why Does Antipsychiatry Persist?
 Root Causes of Ongoing Criticism:
1. Historical Legacy:
• Dark history of asylums, lobotomies, ECT abuses
• Trauma passed down through generations
• Cultural memory of institutional abuses
2. Stigma:
• Mental illness still stigmatized
• People fear being labeled
• Distrust of psychiatric institutions
3. Complexity:
• Brain is the most complex organ
• No simple tests like blood work
• Uncertainty invites skepticism
4. Power Dynamics:
• Psychiatric evaluation involves judgment
• Coercive treatment possible
• Power imbalance concerns
5. Pharmaceutical Industry:
• Conflicts of interest
• Aggressive marketing
• Questionable practices
The 'Original Sin' of Psychiatry
 The Asylum Era (Early 19th
Century):
• Initially seen as humane progress.
 Protected mentally ill from:
 Homelessness
 Persecution
 Neglect
 Victimization
 Imprisonment
 The Problem:
• Conditions deteriorated over time.
• Overcrowding and underfunding.
• Abuse and neglect became common.
• Blamed on psychiatry, not society.
 The Reality:
• Era of almost complete ignorance about brain disorders.
• No effective treatments available.
• Poor funding from society.
• Psychiatry was practicing in a vacuum.
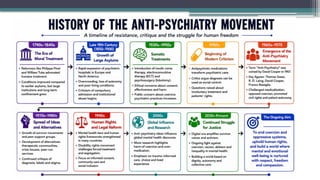
The Emergence of Antipsychiatry
• Early Critics:
1) Former Patients:
• Clifford Beers (1876)
• Wrote ’A Mind That Found Itself’ (1908)
• Advocated for improvements in state hospital conditions
• Generated antipsychiatry sentiments.
• His story inspired others who had been institutionalized to speak
out about their experiences.
2) Neurologists:
• Some in new specialty of neurology supported antipsychiatry.
• Saw psychiatry as unscientific and lack of rigor of neurology.
3) Religious Groups:
• First Church of Christ, Scientist
• Rejected medical approaches
• Preferred spiritual healing
 Henry Cotton - The Bizarre Psychiatrist
• American Psychiatrist, Trenton State Hospital in New
Jersey.
• Developed a theory called 'focal sepsis'— idea that
mental illness was caused by infections in various body
parts.
• Removed teeth, tonsils, colons, and even sex organs from
patients, believing this would cure their mental illness.
• Fueled Antipsychiatry movement.
Racism and Discrimination in Diagnosis
 Drapetomania (19th Century):
• Shows how psychiatry can be misused when social and political beliefs
are mistaken for medical facts.
• Created by Dr. Samuel Cartwright in 1851.
• Mental illness in which slave possessed irrational desire for freedom and
tendency to try to escape.
 Antipsychiatry Arguments:
• This shows medicalization of social problems
• Evidence of institutional racism in medicine
• Abuse of diagnostic power
• Psychiatry as tool of oppression
Perceived Misdeeds - Psychoanalysis
• Critique of Freudian Theory
 Antipsychiatry Arguments:
• Psychoanalysis is unscientific
• Cannot be proven or disproven
• Concepts are untestable
• Can be harmful to patients
• Prolonged treatment without evidence
• Expensive and time-consuming
Perceived Misdeeds - Homosexuality
• Homosexuality listed as mental disorder in DSM-I (1952) and DSM-II
(1968)
• Activists, including gay psychiatrists and antipsychiatry advocates,
challenged this classification.
• Removed by APA vote in 1973
• The antipsychiatry movement uses this historical example to
argue that many conditions might be social constructs.
Perceived Misdeeds - Arbitrary Diagnoses
 The Critique:
• DSM criteria based on committee consensus
• Lacks valid, objective scientific evidence
• No biomarkers for most conditions
• Diagnostic categories may be arbitrary
• Diagnostic disagreements are common
• Different psychiatrists give different diagnoses
Perceived Misdeeds - Pharmaceutical Industry
Complicity
• Antipsychiatry Claims:
• Psychiatrists are complicit with drug companies
• Drugs of dubious efficacy (e.g., antidepressants)
• Drugs of questionable safety (e.g., antipsychotics)
• Financial conflicts of interest
• Academic psychiatrists doing industry-funded research
• Ghostwriting of journal articles
• Drug companies influence prescribing
 The Response:
• Research grants go to universities, not individuals
• Drug education strictly follows FDA-approved labels
• Expert speakers educate, not promote
• Medications have shown benefit for serious conditions
• Safeguards and transparency increased
Igniting influences of Antipsychiatry
Michel Foucault
David Cooper
R.D. Laing
Erving Goffman
Thomas Szasz
Franco Basaglia
• One Flew Over the Cuckoo's Nest is
perhaps the most powerful cultural
artifact of the antipsychiatry movement.
• It humanized institutionalized patients
and challenged abuses of power.
• But it also spread harmful stereotypes,
distorted treatments like ECT, and
contained inexcusable racism and sexism.
Michel Foucault (1926-1884)
• French philosopher and social theorist
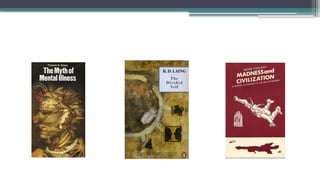
• ‘Madness and civilization’ – A history of insanity in
the age of reason, 1964.
• This books explains how society's understanding
and treatment of "madness“.
• Conceptions of madness are not discoveries but
cultural construction of a given time and place
varying in civilization to civilization/time to time.
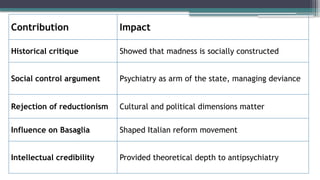
Contribution Impact
Historical critique Showed that madness is socially constructed
Social control argument Psychiatry as arm of the state, managing deviance
Rejection of reductionism Cultural and political dimensions matter
Influence on Basaglia Shaped Italian reform movement
Intellectual credibility Provided theoretical depth to antipsychiatry
Critique of Foucault
• Overstates the role of power and understates the reality of
suffering.
• His work is philosophically dense and offers no practical
clinical alternatives.
• Ignores the genuine therapeutic intentions of many clinicians.
Thomas Szasz (1920-2012)
• Hungarian-American psychiatrist and
psychoanalyst.
• Mentioned each person has the right to
bodily and mental self ownership and the
right to be free from violence from others.
• In 1961, he gave testimony before US senate
where he argued use of mental hospitals
violated doctor patient relationship.
• Szasz's foundational argument: Mental illness is a metaphor, not a
biological disease.
• A "disease" requires a demonstrable biological pathology (lesion,
infection, genetic defect).
• Depression, anxiety, and schizophrenia lack such markers; they are
"problems in living"—responses to trauma, poverty, relationship
breakdown, and existential despair.
• Collaborated with church of scientology to form citizens commission on
human rights in 1969.
Critique of Szasz
• Ignores the reality of severe suffering and disability.
• Fails to account for genetic and neurobiological evidence.
• His position is often seen as philosophical extremism, not
clinical pragmatism.
R.D. Laing (1927–1989)
• Key Concept: Psychosis is a meaningful, rational
response to an irrational world.
• Core Arguments:
• Schizophrenia is not a brain disease but a strategy
for surviving an impossible family environment.
• The "schizophrenogenic" family—characterized by
contradictory messages, emotional coldness, and
covert hostility—drives the person into psychosis.
• The "double-bind" theory: a person receives conflicting
messages (e.g., "Be yourself" but "Don't be so independent") and
cannot escape the contradiction.
• The "divided self": the person splits their identity to protect
their authentic self from a threatening external world.
Critique of Laing
• Blamed families, especially mothers, causing immense guilt
and harm.
• Lacked rigorous scientific evidence.
• Romanticized psychosis, ignoring its devastating consequences.
Erving Goffman (1922–1982)
• Professor of Sociology, Social Psychologist
• Key Concept: Mental institutions create "total
institutions" that strip patients of identity.
 Core Arguments:
• Psychiatric hospitals are "total institutions" —places where
people are cut off from the outside world and subjected
to rigid routines.
• Patients undergo "mortification of the self" —they lose
their identity, privacy, and dignity.
• The "institutionalization" process makes patients dependent,
passive, and unable to function outside.
• The system is iatrogenic—it creates disability rather than
curing it.
Franco Basaglia (1924–1980)
• Psychiatrist, Neurologist born in Italy
• Key Concept:
• "Psychiatric institutions are places of violence and social
exclusion.
• They must be abolished, not reformed.”
• Law 180 – closed asylums in Italy
• Core Arguments:
• Institutionalized psychiatric care is inherently abusive and
inevitably leads to social isolation .
• The asylum is fundamentally a "total institution" —architecturally
and functionally similar to a prison, designed to "discipline and
punish" rather than heal .
• Violence of the institution: The lived body, the originary identity of
a person, and their experiences and thoughts are replaced by those
of the institution, which becomes the patient's new "body" .
• The causes of psychiatric disorder are essentially social in nature—
psychiatry and the treatment of the mentally ill cannot be divorced
from the wider social and political context
Critique of Basaglia
• Critics argue he denied the biological reality of mental illness, maintaining that
only political struggle and reviving the patient's aggressiveness could be valid
"treatments" .
• Law 180 "forgot" long-term patients—many were discharged into communities
with insufficient support, becoming homeless or neglected.
• Insufficient psychiatric beds in general hospitals created crisis points for acute
patients .
• Some argue he romanticized madness and ignored the real suffering of severe
mental illness.
The Decline of Antipsychiatry Ideas
 Adoption Studies:
• Children adopted away from schizophrenic parents still develop schizophrenia
• Shows genetic, not environmental, cause
• The Danish adoption studies are classic
 Twin Studies:
• Identical twins: 50% concordance
• Fraternal twins: 20% concordance
• Shows strong genetic basis
 Family Studies:
• Relatives of schizophrenics have higher risk
• Even if raised apart
• Again shows genetic basis
 Biological Markers:
• Brain imaging shows structural differences
• Neurochemistry differences
• Neurodevelopmental differences
The 1970s - Legal and Political Victories
• Changes in Mental Health Law
• Key Legal Victories:
1) Right to Treatment:
• Courts ruled patients have right to treatment, not just confinement
• Wyatt v. Stickney (1972)
• Promoted treatment in least restrictive setting
• Right to Refuse Treatment:
• Courts recognized patient rights
• Informed consent requirements
• Limits on involuntary treatment
2) Deinstitutionalization:
• Shift from hospitals to community
• Community Mental Health Centers Act (1963)
• But inadequate funding
3) Patient Rights:
• Right to humane treatment
• Right to privacy
• Right to freedom from abuse
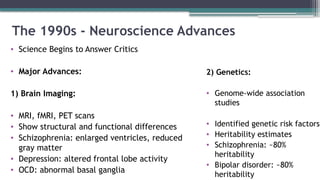
The 1990s - Neuroscience Advances
2) Genetics:
• Genome-wide association
studies
• Identified genetic risk factors
• Heritability estimates
• Schizophrenia: ~80%
heritability
• Bipolar disorder: ~80%
heritability
• Science Begins to Answer Critics
• Major Advances:
1) Brain Imaging:
• MRI, fMRI, PET scans
• Show structural and functional differences
• Schizophrenia: enlarged ventricles, reduced
gray matter
• Depression: altered frontal lobe activity
• OCD: abnormal basal ganglia
4) Evidence-Based Medicine:
• Randomized controlled trials
• Meta-analyses
• Practice guidelines
• Treatment algorithms
3) Molecular Biology:
• Neurotransmitter systems
identified
• Receptor subtypes discovered
• Medications target specific
receptors
• Understanding of mechanisms
Pharmaceutical Industry - The Current Battleground
 Antipsychiatry Claims:
• Industry controls psychiatric research
• Academic psychiatrists are paid off
• Drugs are ineffective or dangerous
• Psychiatry is a corporate tool
• Clinical guidelines are industry-influenced
• Negative trials are hidden
 The Reality Check:
• Research grants go to universities, not individuals
• FDA approval requires rigorous trials
• Education follows FDA-approved labels
• Medications have proven benefit for serious conditions
• Transparency has increased
 The Gray Areas:
• Industry funding of professional organizations
• Continuing medical education influence
• Ghostwriting and publication bias
• Marketing practices
• Conflicts of interest management
The Critical Psychiatry Network
• The Critical Psychiatry Network has recently been formed to provide a
network to develop a critique of the current psychiatric system.
• Aim is to avoid the polarisation of psychiatry and anti-psychiatry.
• 0ffers constructive criticism of clinical psychiatry and of the aims and
organisation of mental health services.
• The Critical Psychiatry Network (CPN) started in the UK in 1999 but now
extends globally.
 Important concerns are:
• Implications of the medical or biological model of mental disorder.
• Overuse and misunderstanding of psychopharmaceuticals.
• Recognition of the central part relationship that plays role in
psychological therapies.
• Tensions between social control functions and patient’s best
interests.
• Socio-political influences on psychological well-being.
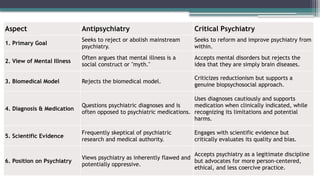
Aspect Antipsychiatry Critical Psychiatry
1. Primary Goal
Seeks to reject or abolish mainstream
psychiatry.
Seeks to reform and improve psychiatry from
within.
2. View of Mental Illness
Often argues that mental illness is a
social construct or "myth."
Accepts mental disorders but rejects the
idea that they are simply brain diseases.
3. Biomedical Model Rejects the biomedical model.
Criticizes reductionism but supports a
genuine biopsychosocial approach.
4. Diagnosis & Medication
Questions psychiatric diagnoses and is
often opposed to psychiatric medications.
Uses diagnoses cautiously and supports
medication when clinically indicated, while
recognizing its limitations and potential
harms.
5. Scientific Evidence
Frequently skeptical of psychiatric
research and medical authority.
Engages with scientific evidence but
critically evaluates its quality and bias.
6. Position on Psychiatry
Views psychiatry as inherently flawed and
potentially oppressive.
Accepts psychiatry as a legitimate discipline
but advocates for more person-centered,
ethical, and less coercive practice.
Positive Impacts of Antipsychiatry
1. Exposed Abuses in Institutions:
• Documented neglect and abuse
• Led to reforms
• Protected patient rights
2. Advocated for Patients' Rights:
• Right to humane treatment
• Right to refuse treatment
• Informed consent
• Legal protections
3. Challenged Over-medicalization:
• Not all problems are diseases
• Social and cultural factors matter
• Caution about labeling
4) Pushed for Community Alternatives:
• Deinstitutionalization
• Community mental health
• Less restrictive settings
5. Demanded Informed Consent:
• Risk disclosure
• Alternative treatments
• Patient involvement in decisions
6. Questioned Industry Influence:
• Transparency
• Conflict of interest management
• Publication of all trials
Negative Impacts of Antipsychiatry
1. Stigma Against Psychiatry:
• Deters people from seeking help
• Undermines trust in doctors
• Discourages treatment adherence
2. Deterred People from Seeking Help:
• Avoidance of treatment
• Worse outcomes
• Unnecessary suffering
3. Promoted Antimedication
Ideology:
• Discourages effective
treatment
• Leads to relapse
• Increases suffering
4. Deinstitutionalization
Without Support:
• Homelessness
• Incarceration
• Death from neglect
• 5. Blamed Families Unjustly:
• "Schizophrenogenic parents"
• Unnecessary guilt
• Harm to families
6. Undermined Biological Research:
• Skepticism about medication
• Reduced research funding
• Slower progress
Summary
• The Anti-Psychiatry Movement emerged in the 1960s as a response
to concerns about coercion, institutionalization, and violations of
patients' rights.
• It challenged traditional psychiatric practices and promoted
human rights, patient autonomy, informed consent, and
community-based care.
• Although many of its scientific claims remain controversial, the
movement prompted important ethical and legal reforms in
mental health care.
• Advances in neuroscience, genetics, and evidence-based
medicine have strengthened the scientific foundation of modern
psychiatry.
• Contemporary psychiatry integrates the valuable ethical lessons
of anti-psychiatry with evidence-based diagnosis and treatment.
• The future of psychiatry lies in delivering compassionate,
patient-centered, recovery-oriented, and scientifically
grounded mental health care.
References
• Nasrallah HA. The antipsychiatry movement: who and why. Curr Psychiatry.
2011;10(12):4-6,53.
• Cooper D. Psychiatry and Anti-Psychiatry. London: Tavistock Publications; 1967.
• Nasser M. The rise and fall of anti-psychiatry. Psychiatr Bull. 1995;19(12):743-746.
• Middleton H, Moncrieff J. Critical psychiatry: a brief overview. BJPsych Adv.
2019;25(1):47-54.
• Burston D. Psychiatry and anti-psychiatry: history, rhetoric and reality. Eidos. A
Journal for Philosophy of Culture. 2018;2(2):75-88.
Only way to be a better psychiatrist is to
listen to our most vocal critics, understand
their pain, and integrate their wisdom into our
practice.
‘This is not an attack on our profession; it is
an act of love for it’.