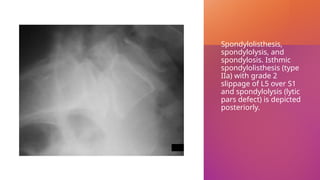
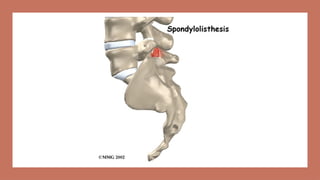
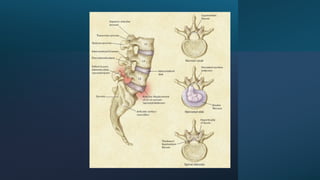
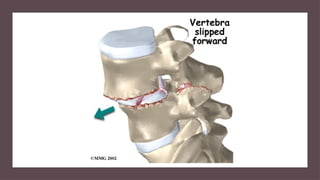
Comprehensive Overview of Spondylolisthesis: Types, Diagnosis, and Clinical Features
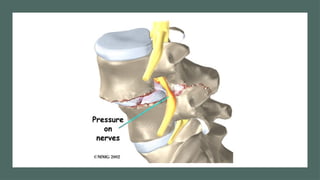
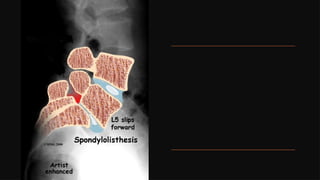
Spondylolisthesis denotes the slippage of one vertebra relative to the one below.
Anterolisthesis (More common)
Retrolisthesis.
Detailed presentation on spondylolisthesis, including its types, pathophysiology, diagnosis, clinical presentation, grading and epidemiology.
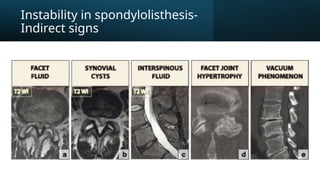
Instability in
spondylolisthesis-
Direct sign
•Functional flexion/extension radiographs are
considered the gold standard for diagnosing the
presence of instability in the setting of
spondylolisthesis
Pathophysiolo
gy
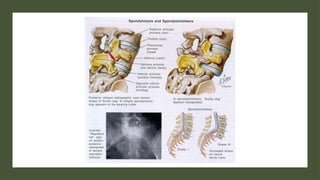
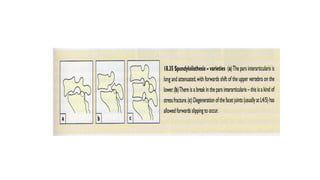
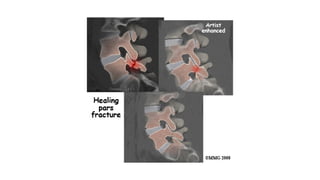
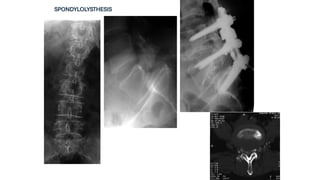
• Spondylolysis isa defect in the pars interarticularis that
may or may not be accompanied by forward translation
of one vertebra relative to another (spondylolisthesis).
10.
Types
• Wiltse, Macnab,and Newman developed a classification to help outline causes of
vertebral translation in an anterior direction.
• Their categories include the following:
• Type I: Congenital spondylolisthesis
• Type II: Isthmic spondylolisthesis
• Type III: Degenerative spondylolisthesis
• Type IV: Traumatic spondylolisthesis
• Type V: Pathologic spondylolisthesis
13.
Type I:
Congenital
spondylolisthe
sis
• Thisis characterized by presence
of dysplastic sacral facet joints
allowing forward translation of
one vertebra relative to another.
Orientation of facets in an axial or
sagittal plane may allow for
forward translation, producing
undue stress on the pars,
resulting in a fracture.
Type III:
Degenerative
spondylolisthesi
s
• Thisis commonly caused by
intersegmental instability produced by
facet arthropathy. This variation usually
occurs in the adult population and, in
most cases, does not progress beyond
a grade I spondylolisthesis.
Type V:
Pathologic
spondylolisthe
sis
• Anybone disorder may
destabilize the facet mechanism
producing pathologic
spondylolisthesis.
• Iatrogenic spondylolisthesis, lastly,
may occur if an overzealous
surgeon performs too great of a
facetectomy.
18.
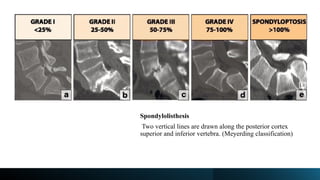
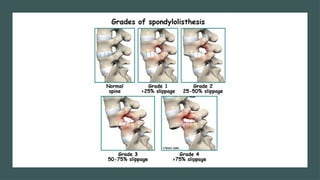
• The mostcommonly used grading system for spondylolisthesis is the one proposed by
Meyerding in 1947.
• The degree of slippage is measured as the percentage of distance the anteriorly
translated vertebral body has moved forward relative to the superior end plate of the
vertebra below.
• Classifications use the following grading system:
• Grade 1: 1- 25% slippage
• Grade 2: 26-50% slippage
• Grade 3: 51-75% slippage
• Grade 4: 76-100% slippage
• Grade 5: Greater than 100% slippage
20.
Frequency
• Wiltse andBeutler each reported an incidence of 6-7% for
isthmic spondylolysis.
• Up to 5% of children aged 5-7 years have been found to
have spondylolysis, many of whom are asymptomatic. The
incidence increases up to the 7% by age 18.
• Athletic activities requiring repetitive hyperextension and
rotation or repetitive combined flexion-extension
predispose some athletes to developing pars defects.
Gymnasts, linemen in college football, weight lifters, javelin
throwers, pole-vaulters, and judoists are most commonly
affected.
• Approximately 82% of cases of isthmic spondylolisthesis
occur at L5-S1.
• Another 11.3% occur at L4-L5. Congenital defects,
including spina bifida occulta, have been linked to
occurrence of isthmic spondylolisthesis. Scoliosis has
been found to occur along with spondylolysis as well.
21.
• Roughly 50%of all cases of spondylolysis
are not associated with spondylolisthesis.
• Degenerative spondylolisthesis occurs
more frequently with increasing age.
• The L4-L5 interspace is affected 6-10 more
times than any other level.
• Sacralization of L5 is frequently seen with
L4-5 degenerative spondylolisthesis.
22.
Mortality/
Morbidity
• Increased mortalityis not associated with
spondylolisthesis. While some patients may
have persistent low back pain, significant
disability is rare unless the patient has severe
neurologic compromise that has not been
addressed.
• The most common morbidity is persistent low
back pain or nerve impingement. Because disk
degeneration is accelerated at the sight of level
of the spondylolysis, diskogenic pain may occur.
• Degenerative spondylolisthesis produces
characteristic arthritic symptoms that may
worsen with age.
23.
Sex
• Beutler etal noted a 2:1 male-to-female ratio of
occurrence in asymptomatic patients with
spondylolysis.
• Females with isthmic spondylolytic lesions
appear to be more prone to progressive
displacement and may need surgical
intervention more often than males.
• Congenital spondylolisthesis (dysplastic
type) occurs with a 2:1 female-to-male ratio
with symptoms beginning around the
adolescent growth spurt. These comprise
about 14-21% of all cases of
spondylolisthesis.
• Degenerative spondylolisthesis occurs
more commonly in females with a 5:1
female-to-male ratio. The incidence
increases after age 40 years.
24.
Age
• Acute isthmicspondylolysis often occurs during
the first and second decades of life. Most cases
occur before the patient reaches age 15 years.
• In rare cases, acute spondylolysis may be seen
in early adulthood. Younger patients are at higher
risk than older patients for developing
progressive spondylolisthesis.
• The risk for progression in adults is rare when the
lesion is at L5. In contrast, lesions at L4-5 may
progress into adulthood because of increased
sagittal rotation, shear translation, and axial
rotation at this segment.
25.
• Congenital/dysplastic spondylolisthesis
hasbeen documented in children as
young as 3.5 months. More commonly,
congenital spondylolistheses go
undiagnosed until later in life after an
individual has been ambulating for quite
some time.
• Degenerative spondylolisthesis occurs
most commonly after age 40 years.
26.
History
• Isthmic spondylolisthesis
•Symptoms often occur around the time of an
adolescent growth spurt.
• Some report acute onset of focal low back
pain during activity, while others have more
insidious onset.
• Radiating pain may extend to the buttocks or
thigh.
• Pain may be more significant and have
mechanical characteristics with higher
grades of spondylolisthesis.
28.
• In mostcases, patients do not complain of
symptoms suggesting neurologic deficit
with lower grades of spondylolisthesis.
Radicular pain becomes more common
with larger slips.
• Complaints of radiating pain below the level
of the knee associated with numbness and
tingling in a dermatomal distribution would
suggest the presence a radiculopathy
resulting from either the foraminal stenosis
that occurs with spondylolisthesis or a
concomitant herniated disk.
• Nerve root impingement from the
fibrocartilaginous bar that forms at the sight
of the lysis may occur. High degrees of
spondylolisthesis may present with
neurogenic claudication or symptoms
suggesting cauda equina impingement.
30.
• The patient'spain usually is provoked by activity, particularly back
extension activities.
• Patients with acute spondylolysis tend to demonstrate poor tolerance
of activities requiring excessive spine loading, including running and
jumping. Sitting usually is better tolerated.
• A large percentage of patients with spondylolysis are asymptomatic.
Progression of a spondylolisthesis also may occur without
symptoms.
32.
• Degenerative spondylolisthesis
•The pain begins insidiously and may be achy in character. Pain is located
in the low back and posterior thighs.
• Neurogenic claudication may be present as well, with lower extremity
symptoms being made worse with activity and better with rest.
• Symptoms are often chronic and progressive, although patients may
experience periods of remission.
33.
• Dysplastic spondylolisthesis:Symptoms present much like
isthmic spondylolisthesis, but neurologic compromise is more
likely.
• Traumatic spondylolisthesis
• Patients present with acute pain associated with trauma.
• If a slip is severe enough, cauda equina compression may occur and
present with classic symptoms including bowel and bladder dysfunction,
radicular symptoms, or neurogenic claudication.
• Pathologic spondylolisthesis: Symptoms may be insidious in
onset and associated with radicular pain/claudication.
34.
Physical Findings
• Isthmicspondylolisthesis
• Hamstring tightness is observed almost universally, even in low-grade
spondylolisthesis.
• Lumbar spasm may be present.
• A palpable step-off is noted with slips equal to or greater than grade 2.
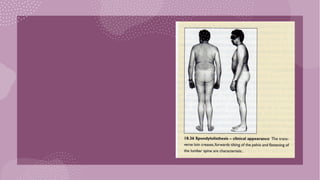
• With higher degrees of spondylolisthesis, an increased lumbosacral
kyphosis is seen (50% or greater) along with a compensatory
thoracolumbar lordosis. Truncal shortening may be present. With severe
slips, the rib cage may rest on the iliac crest.
36.
• Dermatomal weaknessmay be present if a radiculopathy or an
element of stenosis is present.
• A waddling gait may be noted secondary to hamstring tightness
producing a shortened stride length.
• If spondylolisthesis is not present, spondylolysis presents with
paraspinal spasm, pain provocation with lumbar spine extension, and
tight hamstrings.
37.
• Degenerative spondylolisthesis
•These patients present with less prominent physical findings. Pain often is
provoked with lumbar spine extension.
• If lumbar stenosis is present, then reflexes may be diminished. Radicular
findings also may be present.
39.
• Congenital/dysplastic spondylolisthesis:
Physicalfindings are similar to those described
above for isthmic spondylolisthesis.
• Traumatic and pathologic spondylolisthesis
• These patients also present with similar findings.
• A good neurologic evaluation is important.
40.
Causes
• A geneticpredisposition to isthmic spondylolisthesis is
believed to be linked with patients having a thin pars or
subtle hypoplastic facet joints. Family members have a
reported incidence of 28-69%.
• Activities requiring lumbar extension stress increase the
risk. Patients with spina bifida occulta are known to
have a higher occurrence.
41.
• Degenerative spondylolisthesisis caused by facet degeneration
accompanied by disk degeneration most commonly at the level of
L4-L5. Some studies identify sagittally oriented facets as more
prone to arthritic change.
• Congenital spondylolisthesis is due to dysplastic sacral or lower
lumbar segments. Dysplastic facets or abnormal orientation of
the facet joints are the cause for spondylolisthesis.
42.
• Traumatic spondylolisthesisis rare. In theory, severe hyperextension
stress placed on the pars could produce fracture and instability. One
should keep in mind that hyperflexion-distraction forces can cause
facet dislocation and spondylolisthesis.
• Pathologic spondylolisthesis can occur as a result of any bone lesion
that might weaken the posterior elements. Generalized skeletal
diseases including osteomalacia, syphilitic disease, and Von
Recklinghausen disease are some reported causes. Bony destructive
lesions, including tumor or infection, are other potential causes.
Imaging Studies
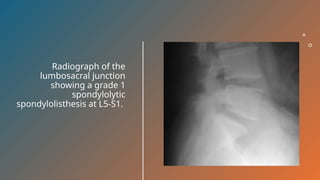
• Radiography
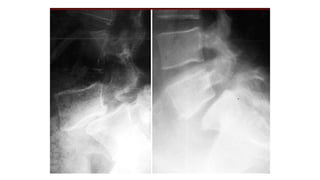
•Initial workup includes anteroposterior, lateral (done
while standing), and spot view radiographs of the
lumbar spine and lumbosacral junction.
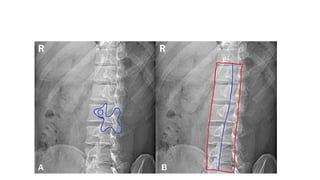
• Oblique views may provide additional information
but are not obligatory.
• Flexion/extension views increase the sensitivity of
radiographic studies and give the clinician some
idea of the degree of instability that may be present.
• Percentage of slip and slip angle (calculated by
measuring the angle formed by a line drawn from
superior endplate inferiorly and the inferior endplate
at the segment of involvement) are clinically
valuable.
• Radiographic studiesallow visualization and grading of spondylolisthesis but may
not always reveal the presence of an isolated spondylolysis (without
spondylolisthesis).
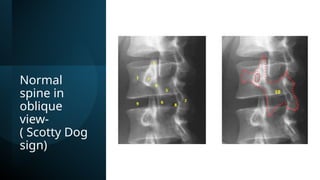
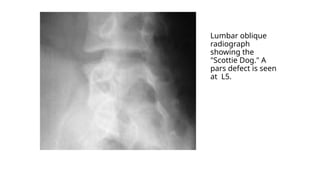
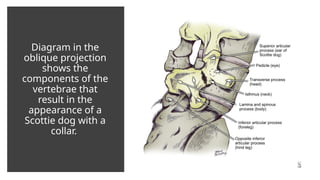
• The 'Scottie dog' whose neck is broken can be seen on the oblique films when
there is a classic spondylolysis.
Diagram in the
obliqueprojection
shows the
components of the
vertebrae that
result in the
appearance of a
Scottie dog with a
collar.
53.
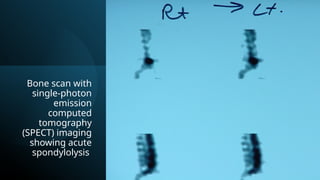
• Bone scan
•Bone scan with single-photon emission computed tomography (SPECT) imaging
is helpful and often helps to direct management.
• If the bone scan is positive, then the lesion is metabolically active. The physician
may consider bracing, since healing is still in progress.
• A cold scan in the context of documented spondylolysis indicates that healing is
complete; therefore, bracing is of limited utility.
• Computed tomography(CT) scan[13]
• CT scan performed with 1 mm sections, including coronal and sagittal
reconstructions, allows for better visualization of the spondylolytic defect.
• CT scan not only documents the presence and severity of spondylolysis, but it
can help rule out more serious causes for a positive bone scan.
• Myelogram/CT studies are helpful in delineating the severity of central stenosis.
Nerve root cut-off often is observed in the presence of radiculopathy.
56.
• Magnetic resonanceimaging (MRI)
• MRI may visualize edema in the marrow
around the sight of an acute spondylolytic
defect.
• MRI also is helpful in identifying the
presence of nerve root compression as a
result of foraminal or central canal
stenosis.
57.
Other Tests
• Electromyographymay provide 1 more
modality for identifying a concomitant
radiculopathy or polyradiculopathy (ie,
stenosis), which may be present as a
result of spondylolisthesis.
Physical
Therapy
Most patients withlow-grade isthmic
spondylolisthesis and degenerative
spondylolisthesis can be treated
conservatively.
If an isthmic lesion is acute, the patient should
be restricted from provocative activities or
sports until they are asymptomatic.
Physical therapy is an integral part of the
patient's rehabilitation process. The most
accepted protocol includes activity and
exercise that reduces extension stress.
The goals ofexercise are to improve
abdominal strength and increase flexibility.
Since tight hamstrings are almost always
part of the clinical picture, appropriate
hamstring stretching is important.
Instruction in pelvic tilt exercises may help
reduce any postural component causing
increased lumbar lordosis.
Myofascial release may play a role as well
in reducing pain from the surrounding soft
tissues.
65.
If conservative treatmentis indicated for
congenital spondylolisthesis, the above
principles apply.
Adequate work up must be completed for
pathologic causes of spondylolisthesis
prior to treating with conservative means.
Traumatic spondylolisthesis most often
requires surgical stabilization.
66.
Surgical
Interventio
n
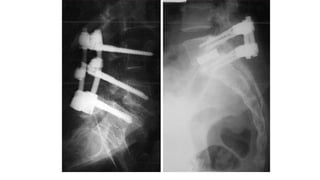
Surgical treatment isindicated when any type of
spondylolisthesis is accompanied by a neurologic
deficit.
Persistent disabling back pain after conservative
management may be considered an indication.
High-grade slips (greater than 50%) more
commonly require surgical intervention.
Traumatic spondylolisthesis is rare but almost
always requires surgical stabilization.
67.
Surgery
• Surgery isused when the slip is severe and when symptoms are not
relieved with nonsurgical treatments.
• Symptoms that cause an abnormal walking pattern, changes in bowel or
bladder function, or steady worsening in nerve function require surgery.
• Deterioration of symptoms is common in patients with a history of
significant neurologic symptoms who don't have surgery to correct the
problem.
• If a reasonable trial of conservative care (three months or more) does not
improve things and/or if quality of life is significantly reduced, then
surgery may be the next best solution.
68.
The main types
ofsurgery for
spondylolisthes
is include:
laminectomy
(decompression)
posterior fusion with or
without instrumentation
posterior lumbar
interbody fusion
69.
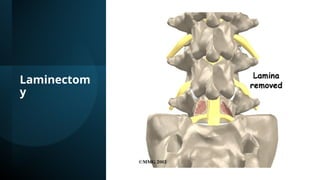
Laminecto
my
When the vertebraslips forward, the nearby nerves that exit the
spine can become pinched or irritated.
In addition, the size of the spinal canal in the problem area
shrinks, placing pressure on the nerves inside the canal. To fix
this, the lamina of the bony ring is removed to ease pressure on
the nerves.
The procedure to remove the lamina and release pressure on the
nerves is called laminectomy.
Decompression alone is usually not advised. Studies show
much better results when the operation is combined with a
fusion of the involved vertebrae.
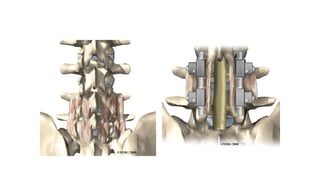
Posterior
Fusion with
Instrumentati
on
A spinalfusion is normally done
immediately after laminectomy for
spondylolisthesis.
The fusion procedure is designed to fuse
the two vertebrae into one bone and stop
the slippage from worsening.
The fusion is used to lock the vertebrae in
place and stop movement between the
vertebrae, easing mechanical pain.
When combined with laminectomy surgery
(mentioned earlier), fusion helps relieve
nerve compression.
72.
• In thisprocedure, the surgeon lays small grafts of bone over the back of
the problem vertebrae. Sometimes fusion is done just with bone graft
material. This is a fusion without fixation (non-instrumentation).
• Instrumentation is the use of metal plates or screws to stabilize the
segment during healing. Most surgeons combine fusion with
instrumentation to prevent the two vertebrae from moving. This protects
the graft so it can heal better and faster.
• Outcomes are improved when decompression is combined with fusion
(compared with decompression alone). Fusion and functional
improvement are even better when spinal instrumentation is used.
• There are fewer long-term problems with pain and pseudoarthrosis.
74.
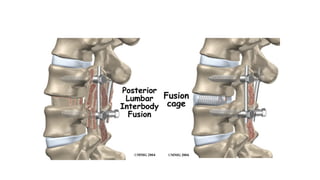
Posterior
Lumbar
Interbody
Fusion
When fusion surgeryis needed for mild spondylolisthesis (up to 50 percent
slippage), posterior lumbar interbody fusion may be considered. In this
procedure, the problem vertebrae are fused from the anterior (front) and
posterior (back).
Combining fusion of both portions of the spine increases the fusion surface
area and improves the fusion rate. The surgeon works from the back of the
spine and removes the disc between the problem vertebrae. Bone graft
material is inserted from the back of the spine into the space between the two
vertebrae where the disc was removed (the interbody space).
The graft may be held in place with a special fusion cage that spreads and
holds the vertebrae apart. Surgeons usually apply some form of
instrumentation (described above) on the back of the vertebrae.
In some cases, additional strips of bone graft are placed along the back
surfaces of the vertebrae to be fused. This increases the mechanical strength
of the spine.
76.
Fusion
with
Biologics
New materials forfusion are being developed and
tested. For example, bone morphogenetic proteins
(BMP) mixed with bone graft in a putty is under
investigation. This substance may help reduce the
need for instrumentation with fusion.
BMP helps promote faster and more bone growth in
the unstable spinal segment. Studies of safety and
effectiveness of this material have been very
favorable so far.
Without the need to harvest bone graft and place
instrumentation, surgical time is much less with
BMP putty. And the fusion rate is much higher with
BMP alone compared with fusion alone or fusion
with fixation.
77.
Motion-
Sparing
Technologi
es
The Food andDrug Administration (FDA) is reviewing the
use of devices inserted without invasive surgery to limit
vertebral motion. For example, a special titanium implant
has been designed to fit between the spinous processes
of the vertebrae in lower back.
These motion-sparing devices are currently used with
patients who have spinal stenosis (narrowing of the
spinal canal or foramen).
With spondylolisthesis, the goal is to reduce the load on
the disc and facets while increasing the space inside the
spinal canal and foramen, thus relieving symptoms. The
vertebral segment is stabilized enough to prevent further
progression of the spondylolisthesis.
Other
Treatment
Bracing for acuteisthmic
spondylolysis/spondylolisthesis is controversial, but it
has been shown in some studies to reduce symptoms
and to facilitate healing.
Most sources discuss use of a thoracolumbosacral
spinal orthosis or modified Boston Brace for low-grade
slips or for isolated spondylolytic lesions (without
spondylolisthesis).
Some sources advocate more extensive bracing with
inclusion of most of the thorax (to the nipple line) and
the thighs. Recommend use of the device for 3-6
months.
Steroid injections for pars pain have been advocated by
some physicians. Epidural steroid injections may help
radicular pain or neurogenic claudication.
84.
• Treatment fordegenerative
spondylolisthesis may include bracing,
facet or epidural steroid injections,
along with the above mentioned
physical therapy approach.
85.
Medication
• The goalof medication in care of
spondylolysis or spondylolisthesis of
any type is to mitigate pain.
• NSAIDs are used most commonly
while narcotic analgesics are used for
breakthrough pain.
86.
Further
Outpatien
t Care
• Becauserisk of progression exists in
younger patients with isthmic or
congenital spondylolisthesis, obtain serial
radiographs on a semiannual basis to rule
out the possibility of progression if
symptoms are persistent.
87.
Inpatient & Outpatient
Medications
•Anti-inflammatories and other analgesics
are the only medications used in the care of
patients with spondylolysis or
spondylolisthesis.
88.
Deterrenc
e
• Prevention ofisthmic spondylolisthesis
may be difficult in athletes who must
perform repetitive activities requiring
hyperextension.
• The best prevention is to avoid repetitive
hyperextension if at all possible, since this
activity appears to place athletes at the
greatest risk.
89.
Complicatio
ns
The most commoncomplication of
spondylolisthesis of any type is nerve root
impingement/radiculopathy at the level of
spondylolisthesis.
Spinal stenosis and cauda equina syndrome
may occur when a significant slip has occurred.
Disk degeneration occurs at the level of the
spondylolisthesis faster than at other levels of
the spine, increasing the risk of diskogenic low
back pain.
90.
Nonsurgical
Rehabilitati
on
1
Back pain
associated with
spondylolisthesi
swill gradually
improve in up to
one-third of all
patients.
Slippage of one
vertebra over
the other does
not increase in
this group.
Worsening of
symptoms is not
expected in
patients who
don't have
neurologic
symptoms at
the time of
diagnosis.
2
Nonsurgical
treatment for
spondylolisthesi
s commonly
involves
physical therapy
a few times
each week for
four to six
weeks. In some
cases, patients
may need a few
additional
weeks of care.
3
The first goal of
treatment is to
control
symptoms.
4
Physiotherapist
works with
patient to find
positions and
movements that
ease pain.
Treatments of
heat, cold,
ultrasound, and
electrical
stimulation may
be used to calm
pain and muscle
spasm.
5
Patients are
shown how to
stretch tight
muscles,
especially the
hamstring
muscles.
91.
• As patientsrecover, they gradually advance in a series of strengthening exercises
for the abdominal and low back muscles. Working these core muscles helps
patients move easier and lessens the chances of future pain and problems.
• A primary purpose of therapy is to help you learn how to take care of symptoms
and prevent future problems.
• Patient is given a home program of exercises to continue improving flexibility,
posture, endurance, and low back and abdominal strength. The therapist will also
describe strategies that can be used if symptoms flare up.
93.
Rehabilitati
on After
Surgery
Rehabilitation aftersurgery is more complex. Patients who have
surgery for spondylolisthesis usually stay in the hospital for a few
days afterward.
Some surgeons require patients to wear a rigid brace or cast for up
to four months after fusion surgery for spondylolisthesis. Patients
who've had fusion surgery for a severe slip may also be required to
stay off their feet for four months.
After lumbar fusion surgery for spondylolisthesis, patients must
normally wait four months before beginning a rehabilitation
program. This delay is needed to give the fusion a chance to start
healing. Patients typically need to attend therapy sessions for six to
eight weeks and should expect full recovery to take at least 12
months.
94.
• Ideally, patientsare able to return to their previous activities. However, some
patients may need to modify or discontinue certain activities to avoid future
problems.
• The therapist will continue to be a resource for patient. But patient will be in charge
of doing exercises as part of an ongoing home program.
95.
Prognosis
• In general,patients with grade 1 or grade 2 isthmic slips do quite
well with conservative management. Patients may return to play
once they are asymptomatic.
• A flexion-based home exercise protocol is vital. Overall long-term
outcome is quite favorable, specifically with lower grades of
listhesis not accompanied by neurologic impairment.
• Higher grades of isthmic spondylolisthesis have a variable
prognosis with regard to persistent low back pain.
• Surgical intervention does provide nice improvement in
claudication or radicular symptoms.
• Diskogenic pain may produce more persistent lower lumbar
discomfort.
96.
• Patients withdegenerative spondylolisthesis seem to have persistent waxing and
waning pain originating from the facet joints.
• Surgical decompression for neurologic compromise has a high rate of success in
relieving lower extremity symptoms.
97.
Patient Education
• Athletesinvolved in higher risk sports should be educated about the risk of
developing a spondylolysis.
• Instruction regarding an appropriate home exercise program, including a flexion-
based spine exercise protocol and hamstring stretching, should be a part of
treatment.