Comprehensive Overview of Presbyopia: Causes, Types, and Clinical Management
Detailed insights into presbyopia including its pathophysiology, types, symptoms, and methods for determining near addition for effective vision correction.
Introduction
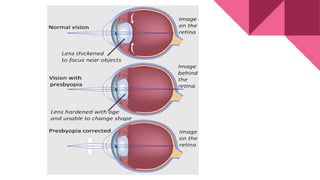
● Presbyopia (eyesightof old age) is not an error of refraction but a
condition of physiological insufficiency of accommodation due to
reduced amplitude, leading to a progressive fall in near vision.
● Begins between 40 and 45 years
● Complete loss of accommodation by 5th to 6 th decade.
4.
Pathophysiology
To understand thePathophysiology of presbyopia ,a working knowledge about
accommodation is mandatory.
● Near point (punctumproximum):Nearest point at which small objects can be
seen clearly.
● Far point (punctumremotum): Farthest point that can be seen clearly.
● Range of amplitude : Distance between the near point and far point
● Amplitude of accommodation (A):Difference between the dioptric
power ,needed to focus at near point (P) and to focus at far point (R ).i.e A=P-R
5.
Pathophysiology contd
In emmetropiceye far point is infinity and near point varies with age.
● 7cm at the age of 10 years .
● 25cm at the age of 40 years.
● 33cm at the age of 45 years.
● At the age of 10 yrs ,amplitude of accommodation (A)=P-R
.i.e100/7-1/infinity
=14D
6.
Pathophysiology contd
● Sincewe usually keep the book at about 25cm ,so we can read
comfortably up to the age of 40 years.
● After 40 years the NPA decrease beyond normal working or
reading range leading to presbyopia.
7.
Causes of presbyopia
●Age related changes in the lens like decrease in the
elasticity of lens capsule and progressive changes in size
and hardness of lens.
● Age related decline in ciliary muscle power.
8.
Causes of prematurepresbyopia.
● Uncorrected hypermetropia
● Premature sclerosis of the crystalline lens
● General lack of strength causing presenile weakness of ciliary
muscle
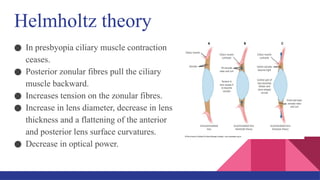
Helmholtz theory
● Inpresbyopia ciliary muscle contraction
ceases.
● Posterior zonular fibres pull the ciliary
muscle backward.
● Increases tension on the zonular fibres.
● Increase in lens diameter, decrease in lens
thickness and a flattening of the anterior
and posterior lens surface curvatures.
● Decrease in optical power.
11.
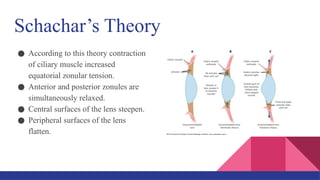
Schachar’s Theory
● Accordingto this theory contraction
of ciliary muscle increased
equatorial zonular tension.
● Anterior and posterior zonules are
simultaneously relaxed.
● Central surfaces of the lens steepen.
● Peripheral surfaces of the lens
flatten.
12.
Catenary Theory
● Proposedby coleman
● According to this theory, initially ciliary muscle contracts.
● Initiates pressure gradient between vitreous and aqueous compartments.
● Ant capsule and zonule form trampoline shape .
● Radius of curvature steepens on the center of the lens with slight flattening
of the peripheral ant lens.
Incipient presbyopia
● Borderline,beginning, early or pre-presbyopia
● Earliest stage when symptoms or difficulty are first encountered in near
vision.
● More difficulty in dim illumination while can do well in bright
illumination.
● Patient’s history suggests a need for a reading add, but pt. performs
visually on testing and ,given the choice ,may prefer to remain uncorrected.
15.
Functional presbyopia
● Whenfaced with gradually declining AA and continued near
task demands, adult pts. eventually report visual difficulties
● The interaction between the pt.'s AA and the patient's near
vision demands is critical.
● The age at which presbyopic becomes symptomatic varies.
● Due to variations in distance vision status , environment, task
requirements, nutrition, or disease state.
16.
Premature Presbyopia
● Presbyopiaoccuring at an earlier age than expected for normal population.
● Usually associated with ocular diseases, nutritional deficiencies or ingestion
of certain drugs.
● Uncorrected hyperopia.
● Premature sclerosis of crystalline lens.
17.
Nocturnal Presbyopia
● Nearvision difficulties result from an apparent decrease in the
AA in dim light.
● Increased pupil size and decreased depth of field are usually
responsible for this reduction in the range of clear near vision in
dim light.
18.
Manifest presbyopia
Presbyopia withsome amplitude of accommodation present
Absolute presbyopia
Presbyopia with amplitude of accommodation completely absent
Symptoms
● Difficulty innear vision.
Patients start complaining of vision for small print and finer
objects at the usual reading distance. So the patient begins to hold
the head back and the book slightly at a greater distance.
Such problems occurs initially in the evening and dim light and
later even in good light .
Finally, the near work becomes an impossibility.
● Asthenopic symptoms like headache due to fatigue of ciliary muscle.
● Intermittent diplopia due to associated disturbances of convergence.
Methods of determiningnear add
● Addition based on amplitude of accommodation
● Tentative addition based on age
● Plus build-up method
● Bichrome method
● Cross-cylinder method
● Relative accommodation method
● Dynamic Retinoscopy
23.
● Amplitude ofaccommodation decreases with age
● Presbyopia is reported when NPA exceeds 22cm i.e. AA=4.50D(Donders)
● Presbyopia exists when amplitude of accomodation is less than 5D( Morgan)
● Measured by push up method or the minus lens to blur method
● For older person, AA can be measured with the pt.’s addition
● The amount of the add is then subtracted from the result of the test
● Amount of new add. should permit a certain percentage (50%) of the AA to
remain in reserve.
1)Tentative add based on amplitude of
accomodation
24.
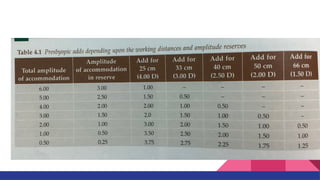
Adjustment for workdistance
● Power of the presbyopic add should be adjusted taking into consideration the
working distance required by a particular patient and the remaining amplitude.
● For example, in a patient in late 40s with only 3D total amplitude left, the
following adds give varying work distance and leave comfortable (50%)
amount of accommodation in reserve.
+2.5 D : 25cm
+1.5D : 33cm
+1.0D : 40cm
+0.5D : 50cm
26.
Example
Working distance (WD)=40cm
AA=2.00D
What should be the near addition?
Accomodation required for WD=2.50D
Accomodation in reserve =1.00D
Amount of accomodation left=1.00D
Amount of near addition=2.50-1.00D=1.50D
27.
2) Tentative additionbased on age
● Amplitude of accomodation to age (Hofstetter)
Maximum =25.0 - 0.4(age)
Probable=18.5-0.3(age)
Minimum=15.0-0.25(age)
Amount of near add calculated by holding certain amount of
accomodation in reserve.
● Rule of 4’s
Amplitude =4*4-(Age/4)
28.
3) Plus buildup method
● Works best when the corrected VA is normal at distance.
● Can be done binocularly or monocularly.
● Plus lenses are increased in steps of 0.25D to the amount necessary to first
read the desired letters at a customary working distance.
● The power of add is then increased in 0.25D steps to the amount preferred by
the pt.
● Monocular build-up usually lands in more amount of near addition since less
accommodation is available because of a lack of convergence accommodation.
29.
4) Bichrome method
●Based on natural chromatic aberration of eye
● Widely used for determining spherical component of distant correction
● When an ametropic eye is out of focus for distance,
red target is clear in myopia
green target in hyperopia
● The same principles apply at near distance
● For presbyopic pts. red & green are focused behind the retina with red farther away
● For Uncorrected or undercorrected presbyopic pt.
letters on green background clearer
● An overcorrection for a near target
the letters on red background clearer
30.
Bichrome method
• Pt.'sdistance correction is placed on a trial frame
• Bichrome target is placed at habitual near distance (40cm)
• Tell the pt. to look at letters on both Green and red background carefully
• Ask the pt. which side has the sharper and clearer letters
- Green clear: add plus in 0.25 step
- red clear : remove plus
- until pt. sees letters equally clear in both background
31.
Demerits of Bichromemethod
• With the older patients,
the crystalline lens becomes markedly yellow
blue green light being partially absorbed and scattered
gives a red bias to the test
• Difficult in protanopic patient; since the red background will appear much dimmer
than the green
• Precaution : the subject is instructed to emphasize on clarity of letters and not the
background
32.
The cross cylindermethod
● Jacques, an optometrist, introduced the cross cylinder test for
determining presbyopia and prescribing corrective lenses.
● The test uses a cross target with three heavy black lines on each
limb, placed 40 cm in front of the patient.
● A cross cylinder (+0.50 D x180-0.50 x 90º) is introduced before
each eye, and the patient reports clarity or blurring of the bars.
● If the patient can accommodate adequately, both bars fall
equally relative to the retina; if presbyopic (cannot
accommodate enough), the horizontal bar falls closer to the
retina.
33.
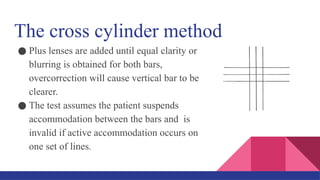
The cross cylindermethod
● Plus lenses are added until equal clarity or
blurring is obtained for both bars,
overcorrection will cause vertical bar to be
clearer.
● The test assumes the patient suspends
accommodation between the bars and is
invalid if active accommodation occurs on
one set of lines.
34.
6) Relative accomodationmethod
● NRA: measure of maximum ability to relax accommodation while maintaining
clear, single binocular vision of a test object at a specified distance
● PRA : measure of the maximum ability to accommodate while maintaining clear,
single binocular vision of a target at a specified distance
● The difference between the NRA and the PRA is called the relative
accommodative amplitude
35.
Relative accomodation method
●Based on the concept of placing the accommodative demand in the middle
of the range of relative accommodation
● To measure NRA and PRA,
pt.'s distance refraction and a tentative add is placed in the phoropter
(Trial frame)
the near point test card is placed at the reading distance (usually 40 cm)
36.
Relative accomodation method
●NRA is determined by adding plus power lenses binocularly until
the pt. is no longer able to read the fine print on the test card
● PRA is determined by adding minus power lenses until the pt. is
no longer able to read the fine print
● Near add = (NRA+PRA)/2
37.
Example
● Suppose pt.can read fine print with +1.00D add
● Blurring occurs when add increased to +2.00D and reduced to
+0.50D
● Range of clear vision is 1.50D (from +2.00D to +0.50D add)
● Final add is (+0.50+2.0)/2= +1.25D
38.
7) Dynamic retinoscopy
●Determine lag of accommodation
● Reduce amount of lag by +0.50 to +0.75D
● Prescribe remaining as addition for near
39.
Comparing methods ofdetermining
addition in presbyopes
● All the techniques display similar behaviour and provide a tentative addition
close to the final addition
● Among the methods used, the age-expected procedure is recommended, as this
technique produce results that correlate best with the final add
● Likelihood of error is high and supports the idea that any tentative add has to be
adjusted according to the particular needs of each pt.
40.
An evaluation ofestimation methods for
determining addition in presbyopes
● All the methods used display similar behavior and provide a
tentative addition close to the final addition
● Every tentative addition should be adjusted according to the
particular needs of the patient
41.
Determination of finaladdition
● Customary near working distance
● Nature of the near work
● Physical nature of the patient
● Illumination level
● Status of the accommodation-convergence relationship
● Change in the amount of the addition
42.
Treatment
1. Optical correctionof presbyopia
● Done by supplementing accommodation with convex
lenses of appropriate power ,required for a clear and
comfortable near vision.
● Difference between the distance correction and the
strength needed for near vision is called the add.
● The values in the table are just rough estimates for
Presbyopic addition. The actual values may differ
according to patients nature of near work.
Age Addition
power
40 years +1.00D
43 years +1.25D
45 years +1.50D
48 years +1.75D
50 years +2.00D
55 years +2.25D to
+ 2.50D
60 years +2.50 D to
+3.00D
43.
Basic principle forpresbyopic
correction
● Always find out refractive error for distance and first correct it.
● Find out the presbyopic correction needed in each eye
separately and add it to the distance correction.
● The presbyopic add prescribed should leave about 50% of the
accomodation in reserve.
● Near point should be fixed by taking due consideration for
profession of the patient.
44.
● The weakestconvex lens with which an individual can see
clearly and comfortably with both the eye ( binocularly) at the
near point should be prescribed ,since overcorrection will also
result in asthenopic symptoms.
● An additional correction for the intermediate distance may be
required ,if it is necessary for the patient to see clearly at that
length .Various focal (progressive ) lens are good option.
45.
Modes of prescribingpresbyopic
add
1. Spectacles
● Single vision reading glasses
● Bifocal glasses
● Trifocal glasses
● Multifocal or Varifocal glasses
If patient has no significant distance refractive error, the best
correction is single vision reading glasses of the proper strength .
If patient has a significant refractive error , then two pairs of glasses
are required or a bifocal or multifocal lenses may be prescribed.
47.
Drawbacks of readingglasses
● Very annoying to switch between regular glasses and reading glasses, and
also to put on and take off their reading glasses all day long.
● Reading glasses need to be carried everywhere , so may be forgotten or
misplaced.
● Even those who are used to wearing glasses, do not like the segments of
bifocal.
● The new no line progressive addition eye glasses look better, but still these
are glasses and also cause distorted vision to left and right .Also ,these are
expensive.
48.
2. Contact lenses
Bifocalcontact lenses are available in many soft and rigid gas permeable lense
design.
Both are available in multifocal ,monovision, and bifocal correction.
● Multifocal contact lenses, correct intermediate distance and also to treat
astigmatism.
● Monovision, where one eye wears a near vision contact lens and the other
eye wears a distance vision contact lens.
49.
● Modified monovision,a single vision lens is in one eye and a bifocal lens in
the other eye or two bifocal lenses with different near vision power.
● Hybrid bifocal fit, one contact lens with distance zone in the center and the
other with a near zone in the center, both lenses have an intermediate zone in
the surrounding area .Useful for patient with strong presbyopia.
Note
One thing to remember is that presbyopia does progress overtime and so contact
lens and glass prescription have to be increased with time.
50.
3.Surgical treatment ofpresbyopia
A . Corneal procedures
a. Non ablative corneal procedures
○ Monovision conductive keratoplasty
○ Laser thermal keratoplasty
b. Laser ablation corneal procedures
● Monovision hyperopic or myopic LASIK
● Presbyopic bifocal LASIK
● Presbyopic multifocal LASIK
● PRESBYOND Laser Blended Vision
51.
. c. Cornealinlay
● Acufocus inlay
● Biovision
● Presbylens
● refractive annular and lenticule
● Multifocal refractive inlay
● Presbyopic allogenic refractive lenticule
● Raindrop near vision inlay
d. Intracor treatment
52.
B. Lens basedprocedures or intraocular refractive procedures
● RLE (refractive lens exchange)
● Monovision with IOLs
● PRLs(post chamber phakic refractive lens)
53.
C. Sclera basedprocedures
● Ant ciliary sclerotomy with tissue barriers
● Scleral spacing procedure
● Sclera ablation with Erbium
54.
Reference
❤❤https://healthkura.com/presbyopia-near-addition/❤❤ ,
AK Khurana optics and theories of refraction,
AK Khurana comprehensive ophthalmology
http://www.oculist.net/downaton502/prof/ebook/duanes/pages/v1/v1c0
38.html#:~:text=one%20set%20of-,lines.,-One%20investigator11%20used
%20an"lines."