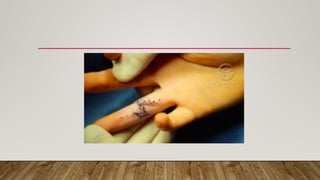
POST-BURN DEFORMITIES
PROF. MRS REGI PHILIP
MT.ZION COLLEGE OF NURSING,ADOOR
INTRODUCTION
• Severe or deep burns lead to acquired post-burn deformities—most
notably joint contractures, hypertrophic scars, and web-space adherence—
caused by skin shrinkage and healing abnormalities. Burn injuries can
leave behind severe deformities that not only affect physical appearance
but also significantly impair mobility and daily functioning.
• These deformities often result from contractures, hypertrophic scars, or
skin graft complications and can involve any part of the body, including
the face, hands, neck, torso and limbs.
BURN DEFORMITIES
• Burn deformities typically result from severe thermal injuries, electrical burns, chemical burns,
or delayed wound healing. These deformities can manifest as:
• Contractures: Thick, tightened skin that restricts movement, especially in joints or along flexor
surfaces.
• Hypertrophic Scars and Keloids: Thick, raised and often itchy scars that form at the injury site.
• Scar Bands: Restrictive scar tissue that limits motion and flexibility.
• Skin Graft Deformities: Irregular or uneven scars after skin graft procedures.
• Pigmentary Changes: Discoloration or patchy pigmentation in affected areas.
COMMON POST-BURN DEFORMITIES
• Contractures: Tight, thickened bands of scar tissue that cross joints,
restricting movement (e.g., locking the elbow, knee, or neck in a bent
position).
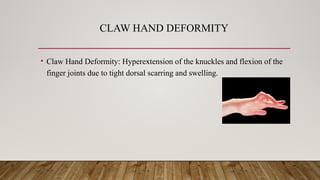
• Claw Hand Deformity: Hyperextension of the knuckles and flexion of the
finger joints due to tight dorsal scarring and swelling.
• Microstomia: Severe tightening and shrinking of the tissue around the
mouth, making eating and oral hygiene difficult.
COMMON POST-BURN DEFORMITIES
• Ectropion: Eyelid scarring that pulls the lid outward,
exposing and endangering the eye.
• Syndactyly: Fingers or toes sticking and healing
together due to circumferential skin loss.
CONTRACTURES
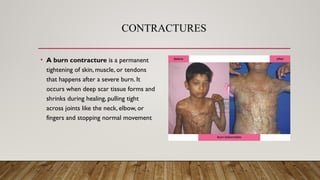
• A burn contracture is a permanent
tightening of skin, muscle, or tendons
that happens after a severe burn. It
occurs when deep scar tissue forms and
shrinks during healing, pulling tight
across joints like the neck, elbow, or
fingers and stopping normal movement
CONTRACTURES
• Causes and Risks
• Deep second-degree or third-degree skin damage.
• Scars taking a long time to heal.
• Staying too long in a "position of comfort" (like curled up) rather than a straight position.
• Skipping physical therapy or splinting
PREVENTION AND NON-SURGICAL CARE
• Prevention and Non-Surgical Care
• Stretching: Do daily range-of-motion exercises to keep tissue flexible.
• Splints: Wear custom splints to hold joints in a straight, anti-deformity
position.
• Pressure: Use pressure garments early on to flatten raised scars.
• Massage: Massage the healing skin to break up tight fibers
SURGICAL TREATMENT
• Release Surgery: A doctor cuts or removes the tight scar tissue
to open the joint.
• Skin Grafts: Healthy skin is moved from another part of the
body to cover the open space left by the release.
• Flaps: Local tissue or muscle is shifted to restore a healthy layer
of skin and blood flow
CLAW HAND DEFORMITY
• Claw Hand Deformity: Hyperextension of the knuckles and flexion of the
finger joints due to tight dorsal scarring and swelling.
CLAW HAND DEFORMITY
• Claw hand deformity is a condition
where the fingers curl into a claw-like
shape due to nerve damage and muscle
imbalance in the hand. It features bent
middle and finger tips (interphalangeal
flexion) alongside pulled-back base
joints (metacarpophalangeal
hyperextension), commonly tied to ulnar
nerve injury
• Signs and Symptoms
• Fingers stuck or bent in a claw posture
(frequently the ring and little fingers)
• Trouble straightening or extending the fingers
• Numbness, tingling, or loss of feeling in the hand
and specific fingers
• Weak grip and loss of fine motor coordination
• Wasting or thinning of the small muscles in the
palm and between bones
CAUSES AND TREATMENT
• Treatment Options
• Wearing dynamic splints or anti-claw braces to
realign joints
• Physical and occupational hand therapy for
stretching and strengthening
• Medications for pain or inflammation
management
• Surgical interventions including nerve repair,
tendon release, or tendon transfers
MICROSTOMIA
• Microstomia is a medical condition defined by an abnormally small
mouth opening. It can be congenital (present at birth, often linked to
genetic syndromes like Freeman-Sheldon syndrome) or acquired later in
life due to severe facial burns, trauma, cancer surgery, or systemic
hardening of the skin from scleroderma
• Microstomia: Severe tightening and shrinking of the tissue around the
mouth, making eating and oral hygiene difficult.
CAUSES AND TYPES
• Congenital factors: Inherited craniofacial
syndromes and genetic abnormalities.
• Acquired scarring: Severe thermal, electrical, or
chemical facial burns.
• Systemic disease: Autoimmune conditions like
systemic sclerosis (scleroderma) causing perioral
tissue tightening.
• Medical interventions: Head and neck radiation,
or surgical removal of orofacial tumors
TREATMENT AND MANAGEMENT
• Common Symptoms
• Eating challenges: Trouble biting into food,
chewing, or swallowing.
• Speech limitations: Difficulty articulating certain
sounds or words clearly.
• Oral hygiene barriers: Inability to brush and floss
properly, leading to high dental decay risk.
• Clinical constraints: Severe obstacles for routine
dental care, endodontic treatment, or fitting
dentures.
• Treatment and Management
• Physical therapy: Active facial stretching and passive
jaw exercises using specialized intraoral stretching
appliances.
• Orthotic devices: Use of dynamic or static mouth splints
to preserve or gradually increase the oral opening.
• Surgical correction: Commissurotomy or reconstructive
flap procedures
• (such as local Z-plasty or skin grafts) to release tight
scar bands and widen the aperture.
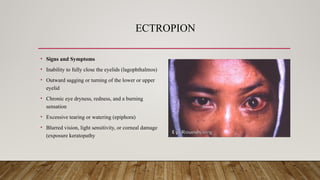
ECTROPION
• Ectropion: Eyelid scarring that pulls the lid outward, exposing and
endangering the eye.
• Ectropion occurs when facial burn scars shrink and pull the eyelid
outward. This exposes the eyeball, prevents complete eye closure, and
causes severe dryness, corneal ulcers, and potential vision loss. Treatment
requires urgent eye lubrication and surgical scar release with skin grafts.
ECTROPION
• Signs and Symptoms
• Inability to fully close the eyelids (lagophthalmos)
• Outward sagging or turning of the lower or upper
eyelid
• Chronic eye dryness, redness, and a burning
sensation
• Excessive tearing or watering (epiphora)
• Blurred vision, light sensitivity, or corneal damage
(exposure keratopathy
MANAGEMENT AND TREATMENT
• Eye Protection: Use frequent artificial tears, lubricating ointments, and
moisture chambers to protect the cornea from drying out.Temporary
Measures:
• Temporary procedures like tarsorrhaphy (partially sewing the eyelids
together) may be used to shield the eye before final reconstruction.
• Surgical Correction: The definitive treatment involves releasing the tight
scar tissue, repositioning the eyelid, and placing a full-thickness skin graft
(FTSG) or local tissue flap to restore missing eyelid skin length
SYNDACTYLY
• Fingers or toes sticking and healing together due to circumferential skin loss.
• Post-burn syndactyly is the abnormal fusing or webbing of adjacent fingers. It happens
when deep hand burns heal without proper skin grafts or splinting, causing raw skin
surfaces to stick together with tight scar tissue.
• This limits hand movement and grip.
POST-BURN SYNDACTYLY
• Causes
• Deep tissue damage: Full-thickness or deep
partial-thickness burns destroy the delicate skin
between the fingers.
• Improper healing: Fingers kept in a flat or
adducted position during recovery fuse as scars
tighten.
• Delayed grafting: Failing to cover raw areas with
skin grafts promptly lets adjacent granulating
surfaces stick and heal together.
TREATMENT AND MANAGEMENT
• Prevention: Early splinting in an
intrinsic-plus position (slight
wrist extension, flexed knuckles,
straight finger joints), proper
positioning, and early physical
therapy stop web spaces from
closing
• Treatment and Management
• Surgical release: Doctors carefully cut and separate the
fused scar tissue while protecting underlying nerves,
blood vessels, and tendons.
• Flap and graft reconstruction: Surgeons use local tissue
rearrangements—such as Z-plasties or specialized flip-
flaps—alongside full-thickness skin grafts to line the new
web spaces and prevent re-fusion.
• Rehabilitation: Intensive physical and occupational
therapy paired with custom splints ensures the fingers
maintain their full range of motion during recovery.
SURGICAL TREATMENTS
• Scar Release (Contracture Release): Cuts open or removes tight scar
tissue over joints.Z-Plasty: Rearranges small skin flaps in a "Z" pattern to
break up tight lines and ease tension.
• Skin Grafts: Uses thin or thick layers of healthy skin from another body
site to cover raw areas.
• Flap Surgery: Moves muscle, fat, and blood vessels along with skin to
cover exposed tendons or bone.
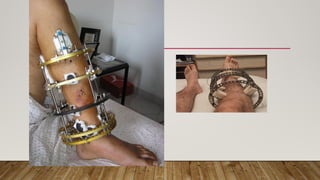
• Gradual Distraction: Employs specialized external devices like the
Ilizarov method for severe, long-standing joint contractures
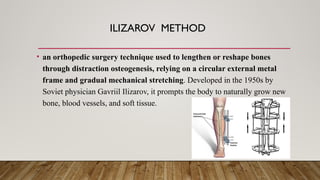
ILIZAROV METHOD
• an orthopedic surgery technique used to lengthen or reshape bones
through distraction osteogenesis, relying on a circular external metal
frame and gradual mechanical stretching. Developed in the 1950s by
Soviet physician Gavriil Ilizarov, it prompts the body to naturally grow new
bone, blood vessels, and soft tissue.
ILIZAROV APPARATUS
• The Ilizarov apparatus is a type of external fixation apparatus used in orthopedic
surgery to lengthen or to reshape the damaged bones of an arm or a leg; used as a limb-
sparing technique for treating complex fractures and open bone fractures; and used to
treat an infected non-union of bones, which cannot be surgically resolved. The Ilizarov
apparatus corrects angular deformity in a leg, corrects differences in the lengths of the
legs of the patient, and resolves osteopathic non- unions; further developments of the
Ilizarov apparatus progressed to the development of the Taylor Spatial Frame
ILIZAROV APPARATUS
• The Ilizarov apparatus is a specialized external fixator of modular
construction, composed of rings (stainless steel, titanium) that are
transfixed to healthy bone with Kirschner wires and pins of heavy-gauge
stainless steel, and immobilized in place with additional rings and threaded
rods that are attached with and through adjustable nuts. The circular
construction of the apparatus, the rods, and the controlled tautness of the
Kirschner wires immobilizes the damaged limb to allow healing
BONE DEFORMATION REPAIR
• The Ilizarov apparatus corrects deformed bones by way of the process of distraction osteogenesis, which reproduces
bone tissues. After an initial surgery during which the bone to repair is fractured, and the apparatus is attached to the limb of
the patient; once the fracture has been immobilised, the bone tissues begin to grow and eventually bridge the fracture with new
bone. In the course of the osteogenesis process, the bone grows and the physician extends the rods of the Ilizarov apparatus to
increase the space between the rings at each end of the apparatus.
• As the rings are installed at and connected to the opposite ends of the fracture site, the adjustment, done four times a day,
separates the healing fracture by approximately one millimeter per day; in due course, the millimetric adjustments lengthen the
bone of the damaged limb.
• Upon completing the bone-lengthening phase of treatment, the Ilizarov apparatus remains emplace for a period of osteopathic
consolidation, the ossification of the regenerated bone tissues. Using crutches, the patient is able to bear weight on the
damaged limb; once healed, the patient undergoes a second surgery to remove the Ilizarov apparatus from the repaired limb.
The result of the Ilizarov surgical treatment is a limb that is much longer than before the medical treatment.
THE PROCEDURE
• Surgery (Corticotomy): The surgeon cuts the targeted bone (such as the tibia or femur) while carefully
protecting the surrounding blood supply and soft tissues.
• Frame Application: An external circular metal ring fixator is attached to the limb using thin trans-osseous
wires and tensioned half-pins drilled straight through the bone.
• Distraction Phase: After a brief resting period, the patient or caregiver turns the threaded nuts on the
device a fraction of a millimeter daily (typically about 1 mm per day divided into four increments) to
slowly pull the bone ends apart.
• Consolidation Phase: Once the desired length or alignment is achieved, the frame stays locked in place for
several months without adjustments while the newly formed soft bone hardens and matures into solid bone
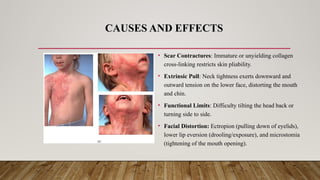
NECK AND FACE TIGHTNESS
• Neck and face tightness: Pulling the chin down to the chest or turning
down the eyelids and lips.
• Neck and face tightness in post-burn deformities stems from scar
contractures—thick, rigid bands of fibrous tissue that form as deep dermal
or full-thickness burns heal. This tightening pulls on surrounding skin and
structures, frequently restricting head and jaw movement, turning down
the lower lip, or pulling down the eyelids.
CAUSES AND EFFECTS
• Scar Contractures: Immature or unyielding collagen
cross-linking restricts skin pliability.
• Extrinsic Pull: Neck tightness exerts downward and
outward tension on the lower face, distorting the mouth
and chin.
• Functional Limits: Difficulty tilting the head back or
turning side to side.
• Facial Distortion: Ectropion (pulling down of eyelids),
lower lip eversion (drooling/exposure), and microstomia
(tightening of the mouth opening).
MANAGEMENT AND TREATMENT APPROACHES
• Surgical Release: Cutting or excising tight scar bands, prioritized by
addressing the neck first to relieve upward/downward facial tension.
• Reconstructive Coverage: Utilizing split or full-thickness skin grafts, local
flaps, tissue expanders, or microvascular free flaps to restore tissue laxity.
• Physical Therapy: Consistent stretching, positioning splints, and pressure
therapy garments to maintain gains achieved through surgery or prevent
worsening tightness.
• Multidisciplinary Care: Coordinated input from plastic surgeons,
maxillofacial specialists, and physical therapists.
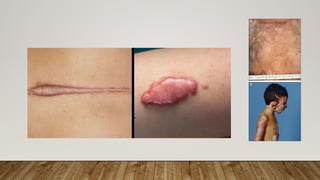
HYPERTROPHIC SCARS AND KELOIDS
• Hypertrophic scars and keloids: Thick, red, raised scars that grow past the original burn
line
• Hypertrophic scars and keloids are thick, raised fibrous growths caused by abnormal
healing after deep dermal burn injuries.
• Hypertrophic scars stay within the burn boundaries and often improve slowly, whereas
keloids grow past the original wound edges and rarely fade on their own. Both cause
itching, pain, and tight joint movement.
HYPERTROPHIC SCARS& KELOIDS
• Hypertrophic Scars:
• Raised, red, stay inside the injury line, and often shrink over time.
• Keloids: Thick, aggressive, grow past the injury line, and do not fade
without treatment.
• Burn Connection: Deep partial-thickness or full-thickness burns that take
weeks to close are high-risk
PREVENTION AND MANAGEMENT
• Pressure Therapy: Custom compression garments worn daily to flatten the tissue.
• Silicone Products: Gel sheets or topical silicone applied to soften and hydrate raised
skin.
• Injections: Steroid shots (corticosteroids) injected into the scar to lower inflammation
and shrink tissue.
• Advanced Care: Laser treatment, cryotherapy, or surgical revision if movement is
blocked.
TREATING A KELOID BURN SCAR
Treating a keloid burn scar involves methods to flatten,
soften, and shrink the raised tissue, as keloids extend beyond the
original burn wound.
Common approaches include steroid injections, silicone gel
sheets, cryotherapy, laser therapy, and combination surgeries.
Because keloids can return and sometimes grow larger after
removal, treatments are often paired together
PREVENTION AND CARE
• Early Closure: Quick surgical removal of dead tissue and skin grafting.
• Pressure Garments: Custom elastic pressure wear used daily after the skin heals.
• Silicone Sheets: Soft gel pads placed over the skin to flatten raised tissue.
• Medical Treatments
• Steroid Shots: Medicine injected into the scar to lower swelling.Laser Therapy: Light
treatments to fade redness, flatten tissue, and stop itching.
• Surgery: Cutting out the scar, often paired with other treatments to stop it from returning
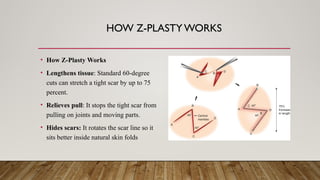
Z-PLASTY:
• Z-plasty: Changing the direction of skin tension to relax tight
scars in small areas.
• Z-plasty is a plastic surgery method used to fix tight burn scars.
A doctor makes a Z-shaped cut over the tight scar and swaps the
skin triangles. This makes the tight scar longer, eases pulling,
and moves the scar into natural skin folds
HOW Z-PLASTY WORKS
• How Z-Plasty Works
• Lengthens tissue: Standard 60-degree
cuts can stretch a tight scar by up to 75
percent.
• Relieves pull: It stops the tight scar from
pulling on joints and moving parts.
• Hides scars: It rotates the scar line so it
sits better inside natural skin folds
COMMON USES OF Z -PLASTY IN BURN CARE
• Joint movement: Frees tight scars across the neck, armpits,
elbows, and hands.
• Improving function: Helps patients move and stretch stiff areas
again.
• Better look: Breaks up harsh straight lines to make scars less
obvious
CONCLUSION
• Deformities due to burns happen when deep scars tighten and pull the skin, muscles, and
joints out of place.This is called a contracture. It limits movement, changes body shape,
and causes tight, raised scars.
PREVENTION AND MANAGEMENT OF POST BURN DEFORMITIES
• Early Intervention: Prompt wound care, early skin grafting,
proper positioning, and custom splinting during the acute phase
minimize scar tightening.
• Therapy: Aggressive physical and occupational therapy keeps
joints flexible and stretches healing skin.
• Surgical Release: Reconstructive surgery—including scar
release, skin grafts, or flap covers—is often required to restore
movement and function.
Comprehensive Overview of Post-Burn Deformities: Causes, Prevention, and Treatment