Comprehensive Overview of Pharmacokinetics: Absorption, Distribution, and Biotransformation of Drugs
Detailed exploration of drug absorption, membrane transport, types of absorption , bioavailability, distribution, biotransformation and excretion processes essential for understanding drug behavior in the body, including factors affecting absorption, bioavailability, distribution, and biotransformation.
ABSORPTION
13
Movement ofthe drug from its site of administration into the
circulation
It is the process by which unmetabolized drug enters into blood after
crossing biological barrier
Different biological barriers
GIT membrane
Nasal, Rectal mucosa
skin
5.
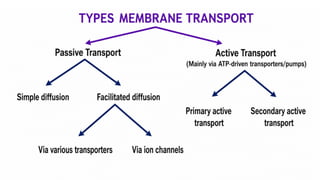
MEMBRANE TRANSPORT
Cell Membrane/The Plasma Membrane
The cell membrane physically surrounds the cell's contents and acts as a protective barrier
separating the inside of the cell from the outside environment.
It regulate what can enter from the extrinsic environment into the intrinsic environment of
the cell to cause an action or adverse reaction.
8.
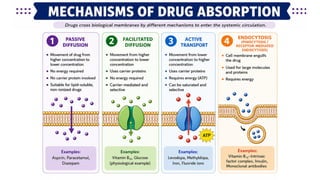
Drug walks across→ Passive diffusion
Carrier holds the drug's hand → Facilitated diffusion
ATP "gives energy" to the carrier → Active transport
Cell membrane surrounds the drug with arms → Endocytosis
9.
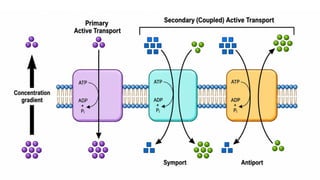
Active transport
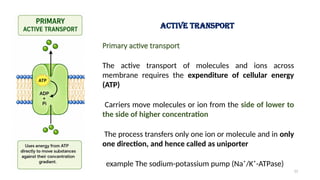
Primary activetransport
The active transport of molecules and ions across
membrane requires the expenditure of cellular energy
(ATP)
Carriers move molecules or ion from the side of lower to
the side of higher concentration
The process transfers only one ion or molecule and in only
one direction, and hence called as uniporter
example The sodium-potassium pump (Na⁺/K⁺-ATPase)
11
11.
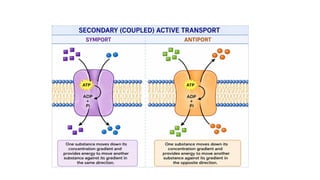
Secondary Active transport
•the energy to pump one solute is derived from the downhill movement of another
solute (mostly Na+)
•Symport or Cotransport :
both the solutes move in the same direction
example, the movement of glucose along with sodium ions.
Thiazide Diuretics act on the Na+/Cl- symporter in the distal convoluted tubule to
reduce sodium and chloride reabsorption.
•Antiport or Exchange transport:
both the solutes move in opposite directions
Eg. Na+,Cl – dependent neurotransmitter transporters
(NET, SERT) 11
13.
Bioavailability
Bioavailability means amountof drug which actually reaches the systemic
circulation or site of action from given dosage form after its administration .
It determines how much of a dose is actually usable by the body
It depends on Drug absorption and on first pass metabolism
IV route has 100 % bioavailability since the drug is directly loaded into the systemic
circulation
14.
On the otherhand The oral route will not bioavailability at Par with iv route since
the drug will have to pass to the GI track ,intestine and then pass the first pass
metabolism.
This will definitely decrease the actual drug reaching the site of absorption and
hence the bioavailability
16.
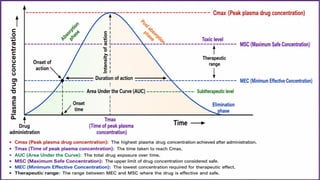
Absorption phase
The portionof the curve from the start to the peak (Tmax).
Here, the rate of absorption > the rate of elimination, so drug concentration
increases.
Elimination phase
The portion of the curve after the peak (Tmax).
Here, the rate of elimination > the rate of absorption, so drug concentration
decreases.
Onset of action
Time when plasma concentration first reaches MEC.
17.
Duration of action:
Timefor which plasma concentration remains above MEC.
Therapeutic range:
The range between MEC and MSC where the drug is effective and safe.
Toxic level:
Concentration above which adverse/toxic effects may occur.
18.
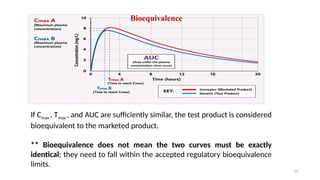
Bioequivalence
When the bioavailabilityof a drug from different formulation is the same then it is
called as bio equivalence
Two different preparations of a drug are considered bioequivalent when the rate
and extent of bioavailability of the active drug from them is not significantly
different under suitable test conditions
14
19.
14
Bioequivalence
If Cmax ,Tmax , and AUC are sufficiently similar, the test product is considered
bioequivalent to the marketed product.
** Bioequivalence does not mean the two curves must be exactly
identical; they need to fall within the accepted regulatory bioequivalence
limits.
20.
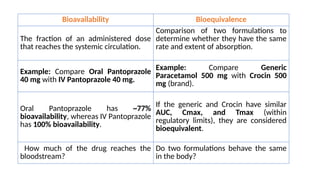
Bioavailability Bioequivalence
The fractionof an administered dose
that reaches the systemic circulation.
Comparison of two formulations to
determine whether they have the same
rate and extent of absorption.
Example: Compare Oral Pantoprazole
40 mg with IV Pantoprazole 40 mg.
Example: Compare Generic
Paracetamol 500 mg with Crocin 500
mg (brand).
Oral Pantoprazole has ~77%
bioavailability, whereas IV Pantoprazole
has 100% bioavailability.
If the generic and Crocin have similar
AUC, Cmax, and Tmax (within
regulatory limits), they are considered
bioequivalent.
How much of the drug reaches the
bloodstream?
Do two formulations behave the same
in the body?
21.
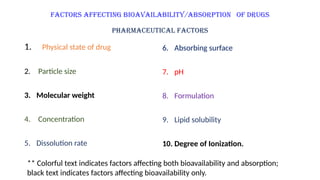
Factors affecting Bioavailability/Absorptionof drugs
Pharmaceutical factors
1. Physical state of drug
2. Particle size
3. Molecular weight
4. Concentration
5. Dissolution rate
6. Absorbing surface
7. pH
8. Formulation
9. Lipid solubility
10. Degree of Ionization.
** Colorful text indicates factors affecting both bioavailability and absorption;
black text indicates factors affecting bioavailability only.
23.
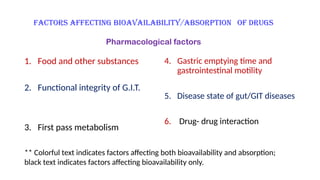
1. Food andother substances
2. Functional integrity of G.I.T.
3. First pass metabolism
4. Gastric emptying time and
gastrointestinal motility
5. Disease state of gut/GIT diseases
6. Drug- drug interaction
Factors affecting Bioavailability/Absorption of drugs
Pharmacological factors
** Colorful text indicates factors affecting both bioavailability and absorption;
black text indicates factors affecting bioavailability only.
25.
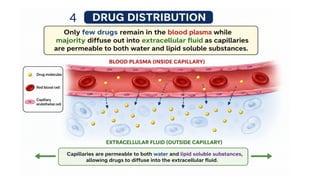
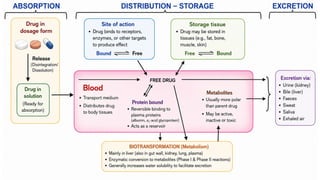
Distribution of drugs
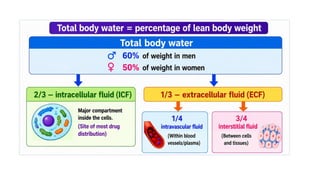
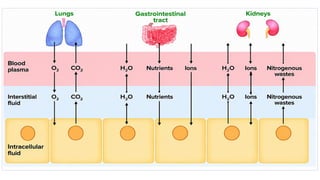
Afterabsorption drug passes through various fluid compartment such as
Plasma
interstitial fluid compartment
transcellular fluid compartment ( cerebrospinal fluid)
cellular fluid compartment
28.
Distribution of drugs
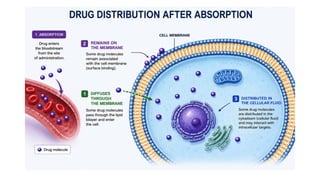
1.After absorption
some drugs diffuse through the cell membrane
some remain on the membrane itself
while some others are distributed in the cellular fluid
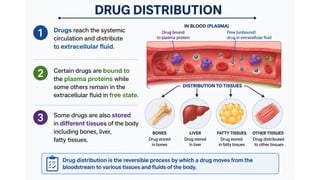
2. Certain drugs are bound to the plasma proteins while some others
remain in the extracellular fluid in free state .
3. Some drugs are also stored in different tissues of the body including
bones, liver, fatty tissues.
Distribution of drugs
Fatsoluble drugs --- stored in adipose tissue
Water soluble – distributed in extracellular space
Acidic Drugs--binds with plasma albumin
Basic drugs - --muscle cells, α1 acid glycoprotein, globulin
33.
Distribution of drugs
Lipid-solubledrugs cross cell membranes easily → distribute widely into ICF
Water-soluble drugs remain mainly in ECF (plasma and interstitial fluid)
Only the unbound (free) fraction of a drug distributes into body fluids and reaches
the site of action
Changes in body water (e.g., dehydration, edema) can alter volume of distribution
and drug levels.
34.
Highly plasma proteinbound drugs are largely restricted to the vascular compartment. The
bound fraction is not available for action. However, it is in equilibrium with the free drug in
plasma
High degree of protein binding generally makes the drug long acting. One drug can bind to
many sites on the albumin molecule
In hypoalbuminemia, binding may be reduced and high concentrations of free drug may be
attained
35.
Factors affecting drugsdistribution
Physiological factors
1. Cardiac Output
2. Regional Blood Flow
3. Capillary Permeability
4. Tissue Volume
5. Special Tissue Characteristics
Such As BBB
Physicochemical properties of
drug
1. binding to drug plasma
protein
2. binding to other tissues like
Fat, bone, liver
3. Affinity for tissue constituents
4. Tissue redistribution
36.
Factors affecting drugsdistribution
• Initially drug gets distributed to the organs which are highly perfused
(kidneys, liver, brain)
• Organs like muscles, Skin, and fat received less blood flow and hence
less drugs
• After initial quick distribution the second phase of distribution may
require minutes to several hours before equilibrium between tissue
concentration and blood concentration is achieved
37.
Physicochemical properties ofdrug
• Diffusion of drugs into tissue fluid occurs rapidly as the capillary
endothelium is highly permeable.
• However , this blood tissue partitioning depends on the binding
drug to plasma protein
• The fraction of total drugs bound with plasma protein depends on
concentration and affinity of binding sites of drug
38.
Physicochemical properties ofdrug
• Only free drug can diffuse out and available for pharmacological
effect
• While plasma bound drug remain in blood and this act as reservoir
of drug
• Fat tissue, bone, liver also act as reservoir of drug
39.
Biotransformation of drugs
•Biotransformation of drugs involves altering the physical and
chemical properties of drugs within the body.
• Biotransformation of drugs usually occurs in two phases.
1. Phase I is known for functionalization reactions
2. Phase II is defined by biosynthetic or conjugation reactions
40.
Purpose of biotransformation
ithelps convert toxic compounds such as xenobiotics into less harmful
substances readily excreted from the body.
It also aids in modifying substrates such as drugs into a form that the
body can easily use.
The most important function of biotransformation is to convert non-
ionised , lipid soluble drugs into more polar, water-soluble compounds
so that their elimination through the urine is easy
41.
Prodrugs: after pharmacologicaltransformation active compound may formed in
vivo.
After biotransformation
inactive substances may act as prodrugs
Castor oil- ricinolic acid
Diazepam-Oxazepam
Prednisone--Prednisolone
Active drug may be converted into toxic substance
Parathion - paraxon
42.
Non-Synthetic reactions (phase1 reactions)
• Enzyme carry out oxidation, reduction and hydrolysis reactions
• Includes introduce functional groups such as -OH, - COOH, - SH, -O- , NH2 etc
• Phase 1 reactions lead to inactivation of active drug
• In certain exceptions may lead to bio-activation of drug
• Phase 1 biotransformation is referred to as functionalization phase of drug
metabolism
• Cytochrome P450 isoenzymes , flavin containing monooxygenases (FMO) ,
epoxide hydrolases (EH)
43.
• Synthetic reactions(phase 2 reactions)
• Metabolite formed in phase 1 reactions form the substrate for
phase 2 reaction
• Metabolites of phase 2 reactions are more water soluble and
targeted either excrete in urine or bile
• UDP- Glucouronasyl transferases (UGT)- glucouronic acid
• Sulfotransferases – sulphate
• Glutathione –S- transferases -- Glutathione
44.
• Xenobiotics :drugs
• Extensively metabolised and eliminated so that they do not cause
harm to body
• Liver: major site of metabolism
• Endogeneous (cholesterol, steroids, fatty acids and proteins) and
Xenobiotics
45.
Factors influencing thedrug metabolism
1. Genetic factors
2. Environmental factors
3. Inhibition of metabolism
4. Induction of metabolism
5. Disease state of individual
6. Drug -drug interactions
7. Drug -food interaction
8. Nutritional status of individual
46.
Genetic factors
• Geneticmakeups play important role in drug metabolism
Acetylation is a Phase II conjugation reaction
Where the liver enzyme N-acetyltransferase 2 (NAT2) attaches an acetyl group to a
drug molecule to make it easier for the body to excrete
Due to inherited changes in the NAT2 gene sequence (genetic polymorphism),
The human population is divided into two major metabolic phenotypes:
Fast (Rapid) Acetylators and Slow Acetylators.
47.
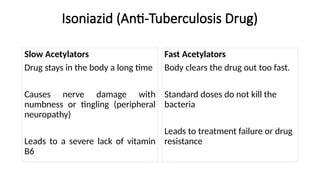
Isoniazid (Anti-Tuberculosis Drug)
SlowAcetylators
Drug stays in the body a long time
Causes nerve damage with
numbness or tingling (peripheral
neuropathy)
Leads to a severe lack of vitamin
B6
Fast Acetylators
Body clears the drug out too fast.
Standard doses do not kill the
bacteria
Leads to treatment failure or drug
resistance
48.
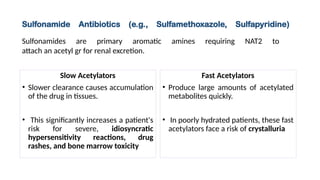
Slow Acetylators
• Slowerclearance causes accumulation
of the drug in tissues.
• This significantly increases a patient's
risk for severe, idiosyncratic
hypersensitivity reactions, drug
rashes, and bone marrow toxicity
Fast Acetylators
• Produce large amounts of acetylated
metabolites quickly.
• In poorly hydrated patients, these fast
acetylators face a risk of crystalluria
Sulfonamide Antibiotics (e.g., Sulfamethoxazole, Sulfapyridine)
Sulfonamides are primary aromatic amines requiring NAT2 to
attach an acetyl gr for renal excretion.
49.
Environmental factors
Drugs orEnvironmental toxins can induce hepatic microsomal
enzyme oxidising system or CYP450 resulting into rapid metabolism
and elimination of drug
The environmental pollutants like pesticides can induce metabolism
50.
Drug -food interaction
Causedby nutrients altering enzyme activity.
Tyramine present in cheese, banana may not be metabolised by MAO if MAOI
(MAO - inhibitor) is given and severe hypertensive crisis may result
When a person takes a Monoamine Oxidase Inhibitor (MAOI), the body cannot
break down dietary tyramine. This triggers a severe, life-threatening hypertensive
crisis, a phenomenon famously known in pharmacology as the "cheese reaction.“
51.
Grapefruit juice blocksintestinal CYP3A4 enzymes.
If you drink a glass of grapefruit juice, its constituent bind irreversibly and
deactivate the CYP3A4 enzymes in your gut.
Because the enzymes are disabled, almost the entire dose of simvastatin floods
into your bloodstream.
This mimics a massive drug overdose.
High blood levels of statins cause severe muscle toxicity, Kidney Failure
Severe Muscle Pain: Debilitating weakness and cramping.
52.
Nutritional status ofindividual
The drug oxidation rate is severely decreased in malnourished children and
elderly.
High protein diet act as metabolising enzymes inducers
Vitamin deficiencies impair crucial biochemical pathways
Low protein diets reduce enzyme synthesis
53.
Disease state ofindividual
In liver cirrhosis metabolism of drug is severely reduce resulting in drug
toxicity.
In kidney disease, decreased elimination of drug metabolites is
observed
54.
Inhibition of metabolism
Isoniazidinhibits the hydroxylation of diphenyl hydantoin and may cause
toxicity of diphenyl hydantoin
Induction of metabolism
Barbiturates stimulate microsomal enzyme system in the liver and thus
increases the metabolic degradation of other drugs like alcohol, phenytoin
55.
Drug -drug interactions
Simultaneousadministration of two drugs causing interactions may
show either inhibition of metabolism of one the drugs or induction of
metabolism
56.
Excretion of drugs
Kidneys:
Majority of drugs are excreted in urine.
Drugs in the urine are excreted by passive glomerular filtration, active tubular secretion
and passive diffusion across the wall of nephrons
Excretion of acidic and basic drugs depends on pHof urine
Weak acids are quickly excreted in alkaline urine and weak bases are quickly excreted
in acidic urine
Helpful in drug poisoning
57.
Lungs
Various gaseous inhalants
Generalanaesthetics , paraldehyde and alcohol
Intestine
Purgative like senna, cascara bark are partly excreted in the intestine
after desired action on large intestine.
Heavy metals
58.
Skin:
Arsenic and Leadare eliminated by skin in minute quantities
Arsenic gets deposited in the hair follicles
Milk:
Antibiotics , Morphine, thiourasil compounds, sulphonamides are excreted in milk
Bile:
Erythromicin and novobiocin are eliminated in the bile and reabsorbed again in
intestine
Prolong the action of drug by the enterohepatic circulation
60.
📖 Explore More:Pharmacokinetics
Video link Topic
Video 1
https://youtu.be/0d2F-GKSVYw Pharmacokinetics
Overview, Absorption &
Bioavailability
Video 2 https://youtu.be/Fzh8mOOYywo?si=QxBI
pOpLQUNtN79U
Drug Metabolism /
Biotransformation
Video 3
https://youtu.be/SZ3BZBBC-Qc?si=sVkhh
8YeFxkriNW6
Urine Formation, Kidney &
Nephron Function — useful
for understanding drug
excretion
Video 4
https://youtu.be/Y2N8iQ2Khxg?
si=bhxSfEawjfLZrhfx
Drug Distribution / How
Medications Reach Target
Sites




 Most read



 Most read