Comprehensive Overview of Oral Antidiabetic Agents for Type 2 Diabetes Management
Detailed insights into oral antidiabetic drugs, their classifications, mechanisms, dosing, adverse effects, and strategies for effective type 2 diabetes treatment.
ORAL ANTIDIABETIC AGENTS(OAA)
Oral antidiabetic drugs are used to treat type 2
DM when dietary modification and exercise can not
achieve the glycemic goals
OAA like Metformin and TZDs prevent DM in
prediabetic patients and used to treat insulin
resistant conditions like NAFLD and PCOS
Metformin may also be used in type 1 DM to
reduce the dose of insulin
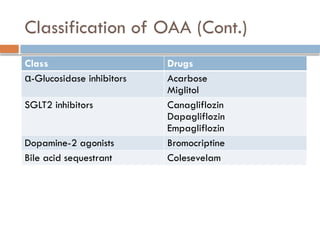
Classification of OAA(Cont.)
Class Drugs
α-Glucosidase inhibitors Acarbose
Miglitol
SGLT2 inhibitors Canagliflozin
Dapagliflozin
Empagliflozin
Dopamine-2 agonists Bromocriptine
Bile acid sequestrant Colesevelam
5.
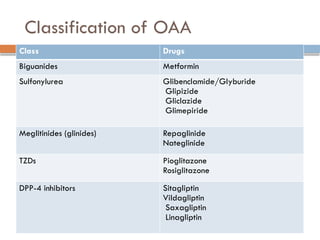
Biguanides
Metformin isthe only biguanide available in
Bangladesh
Phenformin and buformin remain available in some
countries
6.
Metformin
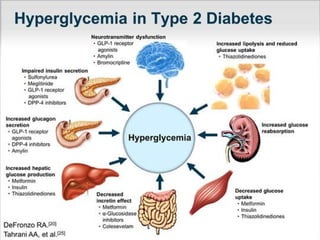
Metformin reducehepatic glucose production
Usually taken at least twice daily. Extended release
formulation can be given once daily.
Extended release metformin is associated with less
severe upper GIT symptoms.
Daily dose: 500-2000 mg
Adverse Effect: nausea, diarrhea, crampy
abdominal pain, dysgeusia, Vit B12 deficiency
7.
Metformin (Cont.)
Contraindication:circulatory shock, dehydration,
acidosis, hepatic and renal failure
Can be used if eGFR up to 30 ml/min/1.73m²
Max dose is 1000 mg when eGFR is between 30 to
45 ml/min
Safe in pregnancy (pregnancy category B)
8.
Sulfonylurea
First generationsulfonylurea: Tolbutamide,
tolazamide, acetohexamide and chlorpropamide.
Second generation sulfonylureas:
Glybenclamide(glyburide), glipizide, gliclazide and
glimepiride
9.
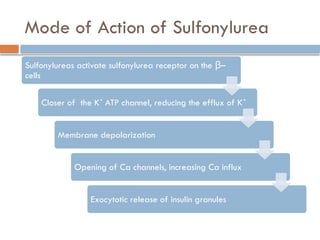
Mode of Actionof Sulfonylurea
Sulfonylureas activate sulfonylurea receptor on the –
β
cells
Closer of the K⁺ ATP channel, reducing the efflux of K⁺
Membrane depolarization
Opening of Ca channels, increasing Ca influx
Exocytotic release of insulin granules
10.
Sulfonylurea (Cont.)
AdverseEffect: Hypoglycaemia, weight gain (rarely
idiosyncratic reaction: skin rash, leukopenia,
thrombocytopenia)
Contraindication: Severe kidney and liver
impairment, pregnancy and lactation
11.
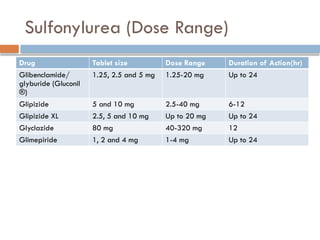
Sulfonylurea (Dose Range)
DrugTablet size Dose Range Duration of Action(hr)
Glibenclamide/
glyburide (Gluconil
®)
1.25, 2.5 and 5 mg 1.25-20 mg Up to 24
Glipizide 5 and 10 mg 2.5-40 mg 6-12
Glipizide XL 2.5, 5 and 10 mg Up to 20 mg Up to 24
Glyclazide 80 mg 40-320 mg 12
Glimepiride 1, 2 and 4 mg 1-4 mg Up to 24
12.
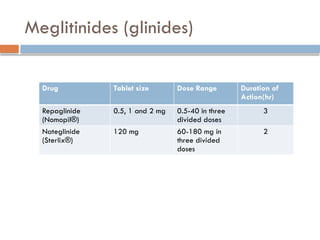
Meglitinides (glinides)
Theseare rapid acting secretagogues
Acts by binding to the sulfonylurea receptor
Adverse Effect: hypoglycemia and weight gain
Causes less hypoglycemia than sulfonylurea
Useful in renal impairment and elderly person
Taken 15 min before each meal
13.
Meglitinides (glinides)
Drug Tabletsize Dose Range Duration of
Action(hr)
Repaglinide
(Nomopil®)
0.5, 1 and 2 mg 0.5-40 in three
divided doses
3
Nateglinide
(Sterlix®)
120 mg 60-180 mg in
three divided
doses
2
14.
Advantages of Nateglinide
It has quicker onset and shorter duration of action
than repaglinide
Advantage: less hypoglycemia
Disadvantages: It lower postprandial plasma
glucose but repaglinide lower both fasting and
postprandial plasma glucose
Useful when FPG is modestly elevated in early
diabetes or in combination with insulin sensitizers or
long acting evening insulin
15.
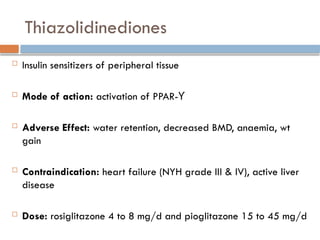
Thiazolidinediones
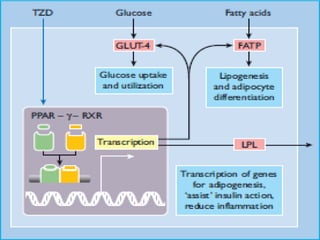
Insulin sensitizersof peripheral tissue
Mode of action: activation of PPAR-ϒ
Adverse Effect: water retention, decreased BMD, anaemia, wt
gain
Contraindication: heart failure (NYH grade III & IV), active liver
disease
Dose: rosiglitazone 4 to 8 mg/d and pioglitazone 15 to 45 mg/d
17.
Dipeptidyl Peptidase-4 Inhibitors
Mechanismof Action: enhance endogenous incretin activity by
preventing the degradation of the GIP and GLP-1. Incretin
causes:
1. Enhance glucose dependant insulin secretion
2. Suppress glucagon secretion
3. Create satiety
4. Slow gastric emptying
Advantages: No hypoglycemia, wt neutral
Adverse Effect: GI upset, pancreatitis, upper RTI
18.
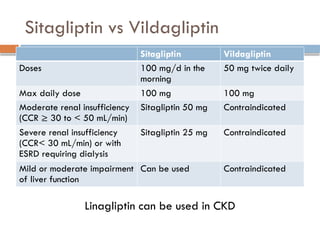
Sitagliptin vs Vildagliptin
SitagliptinVildagliptin
Doses 100 mg/d in the
morning
50 mg twice daily
Max daily dose 100 mg 100 mg
Moderate renal insufficiency
(CCR ≥ 30 to < 50 mL/min)
Sitagliptin 50 mg Contraindicated
Severe renal insufficiency
(CCR< 30 mL/min) or with
ESRD requiring dialysis
Sitagliptin 25 mg Contraindicated
Mild or moderate impairment
of liver function
Can be used Contraindicated
Linagliptin can be used in CKD
19.
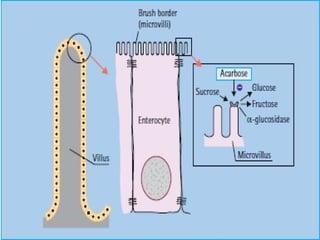
Alpha-glucosidase Inhibitors (AGI)
Drugs: acarbose and miglitol
Mechanism of Action: Inhibit intestinal brush border α-
glucosidases and thereby delay the absorption of
carbohydrate
Given with each meal (first mouthful of food ingested)
Advantages: No hypoglycemia or wt gain
Adverse effect: Flatulence, diarrhoea
21.
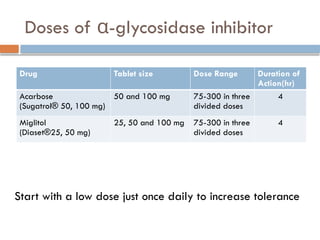
Doses of α-glycosidaseinhibitor
Start with a low dose just once daily to increase tolerance
Drug Tablet size Dose Range Duration of
Action(hr)
Acarbose
(Sugatrol® 50, 100 mg)
50 and 100 mg 75-300 in three
divided doses
4
Miglitol
(Diaset®25, 50 mg)
25, 50 and 100 mg 75-300 in three
divided doses
4
22.
SGLT2 inhibitors
Drugs:canagliflozin (Invokana®), dapagliflozin, empagliflozin
Mechanism of Action: Inhibits SGLT2 in the proximal nephron,
increasing glucosuria
Dose: 100 mg/day taken before the first meal of the day, may
increase dose to 300 mg/day
Adverse Effects: Genitourinary infections, polyuria, volume
depletion/hypotention/dizziness
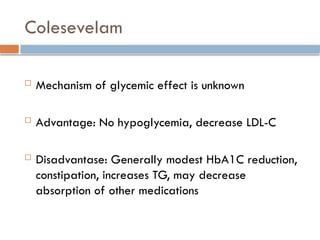
Colesevelam
Mechanism ofglycemic effect is unknown
Advantage: No hypoglycemia, decrease LDL-C
Disadvantase: Generally modest HbA1C reduction,
constipation, increases TG, may decrease
absorption of other medications
25.
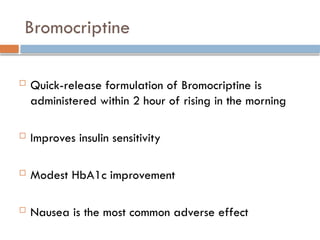
Bromocriptine
Quick-release formulationof Bromocriptine is
administered within 2 hour of rising in the morning
Improves insulin sensitivity
Modest HbA1c improvement
Nausea is the most common adverse effect
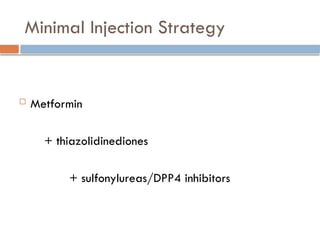
Minimal Effort Strategy
Once-a-day medications: metformin XR,
sulfonylurea, DPP4 inhibitor, or thiazolidinediones
Basal insulin or liraglutide injection may be
considered
35.
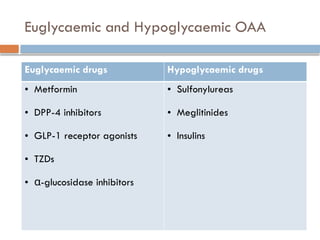
Hypoglycemia Avoidance Strategy
GLP1 receptor agonists, DPP4 inhibitors, and metformin are not
associated with hypoglycaemia
Secretagogues would be added last, their dose minimized, and
glybenclamide avoided
Nateglinide is the preferred secretagogues
Basal insulin are preferred than prandial insulin
Insulin detemir is preferred than NPH insulin and insulin glargine
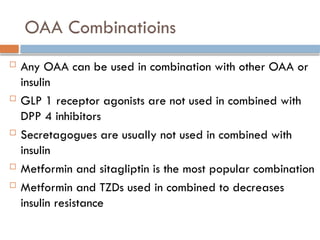
OAA Combinatioins
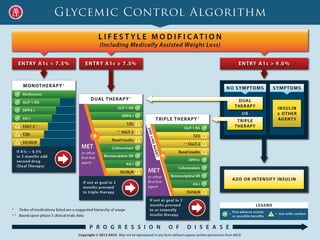
AnyOAA can be used in combination with other OAA or
insulin
GLP 1 receptor agonists are not used in combined with
DPP 4 inhibitors
Secretagogues are usually not used in combined with
insulin
Metformin and sitagliptin is the most popular combination
Metformin and TZDs used in combined to decreases
insulin resistance
41.
Prospect of OralInsulin
Oral insulin product would provide insulin in a more
physiologic manner [than injectable insulin], with a
resultant decrease in peripheral insulin concentrations,
and that it would more adequately 'insulinize' the liver
Oral insulin is safe, well tolerated, more effective than
placebo, and as effective as subcutaneous regular
insulin at controlling postprandial glycemia