Comprehensive Overview of Nystagmus: Mechanisms, Types, and Management
Detailed presentation covering definition, mechanisms, classification, causes, symptoms, evaluation, and treatment options for nystagmus, including congenital and acquired forms.
Definition
Mechanisms
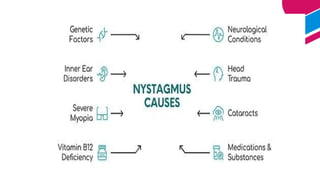
Causes
Symptoms
Classification
History taking
Evaluation
Management and Treatment
CONTENT
3.
DEFINITION
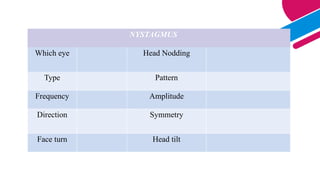
• Nystagmus isa regular, repetitive, involuntary movement of the eye whose
direction, amplitude and frequency is variable.
• It may be physiological or pathological or idiopathic
• May be early onset or later onset.
4.
MECHANISMS
Three mechanism maintainingfoveal centration of an object are -
• Fixation –The visual system detects drift in the foveating image (the image focused on the retina)
and signals corrective eye movements to refoveate the image. If this system is disrupted, it can
lead to involuntary eye movements
• Vestibulo-ocular reflex(VOR)-This reflex is crucial for stabilizing vision during head movements.
It allows the eyes to move in the opposite direction of head motion, maintaining a stable image on
the retina. Disruption in this reflex can lead to nystagmus.
• Neural integrators-This mechanism helps maintain eye position during eccentric gaze (looking
away from the center). If the neural integrator is impaired, it can result in difficulty holding the
gaze, contributing to nystagmus.
5.
• Saccades: Saccadesare rapid conjugate eye movements performed to bring the
image of an object quickly on the fovea.
Eg: reading, writing.
• Pursuits: Pursuits movement are made when tracking a moving object. It helps to
keep the image of a moving object on the fovea constantly.
Eg: it is performed while watching a bird which is moving right, left, up & down.
Normal eye movements
8.
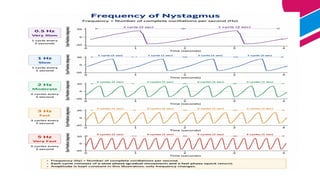
Frequency
Frequency is theno. of to and fro movement in one second.
Described as cycles/secs or Hertz(Hz)
Slow:1-2Hz
Medium:3-4Hz
Fast:5Hz or more
9.
Amplitude is theangular distance traveled during nystagmus (excursion of the
nystagmus)
• Low : less than 5 Degree
• Moderate: 5-15 Degree
• High: > 15 Degree
Amplitude
10.
It states thatthe amplitude of jerk nystagmus is largest in the gaze of direction of
fast component.
• 1 degree: nystagmus only in the direction of the fast component.
• 2 degree: nystagmus in primary gaze position.
• 3 degree: nystagmus in addition to above gazes, also present in the direction of the
slow component.
Alexander’s Law
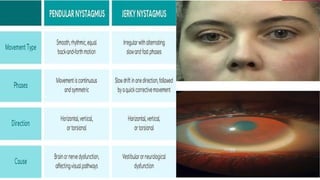
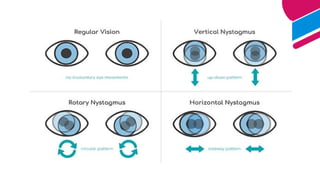
• Horizontal Nystagmus:
Itrefers to involuntary eye movements that occur side-to-side, along the horizontal plane.
It's one of the most common forms of nystagmus and is often seen in conditions like
vestibular disorders, neurological diseases, or as a medication response.
• Vertical Nystagmus:
In vertical nystagmus, the eyes move up and down. This type is less common and often
points to a central nervous system issue, such as brainstem or cerebellar lesions. It can be
upbeat (eyes drift down and jerk upwards) or downbeat (eyes drift up and jerk
downwards).
• Rotary nystagmus:
It is also known as circular or torsional nystagmus. when the eyes rotate around the
visual axis. It occurs with vestibular dysfunction or inner ear disturbances. Nystagmus
with a torsional component is frequently observed along with other types of nystagmus.
18.
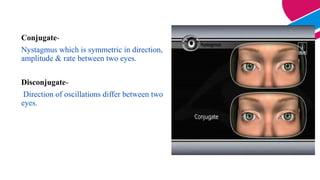
Conjugate-
Nystagmus which issymmetric in direction,
amplitude & rate between two eyes.
Disconjugate-
Direction of oscillations differ between two
eyes.
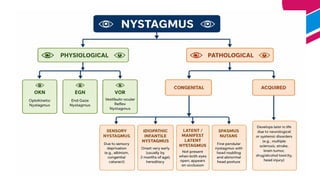
Physiological Nystagmus
This isfurther classified as-
OKN: it is physiological jerk nystagmus induced by presenting to gaze objects
serially in one direction, such as strips of a spinning optokinetic drum.
EGN: it is a fine jerk horizontal nystagmus seen in normal persons on extreme right
or left gaze.
VOR: it is a jerk nystagmus which can be elicited by stimulating the tympanic
membrane with hot or cold water. This is the basis of caloric test.
(COWS- cold opposite and warm same)
22.
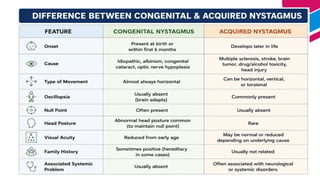
Congenital Nystagmus
These areclassified as:
A. Afferent or sensory nystagmus
B. Idiopathic infantile nystagmus
C. Latent/latent manifest nystagmus
D. Spasmus nutans
Pathological Nystagmus
23.
A. Afferent orSensory Nystagmus:
It is also known as congenital ocular nystagmus and is usually associated with sensory
deprivation due to:
• Ocular albinism
• Bilateral congenital cataract
• Aniridia
• Bilateral optic nerve hypoplasia.
B. Idiopathic infantile nystagmus:
It is also known as idiopathic congenital nystagmus. It is characterised by:
• Hereditary,
• Onset -very early, usually by two months of age.
24.
C. Latent/Manifest latentnystagmus:
It is not present when both eyes are open.
It is present only when one eye is closed.
It is a jerk nystagmus, with the rapid phase towards the uncovered eye.
Associated with congenital esotropia.
D. Spasm nutans:
It is a fine pendular horizontal nystagmus associated with head nodding and abnormal
head posture.
It’s onset is in infancy and self-resolves by the age of 3 years.
25.
Acquired Nystagmus
Acquired nystagmusdevelops later in life due to underlying medical issues. It can be
horizontal, vertical, or rotary and may worsen with certain activities or positions.
Neurological disorders (e.g., multiple sclerosis, stroke), head injuries, or drug and
alcohol intoxication are the most common causes of acquired nystagmus.
26.
Acquired Nystagmus
Acquired nystagmusdevelops later in life due to underlying medical issues. It can be
horizontal, vertical, or rotary and may worsen with certain activities or positions.
Neurological disorders (e.g., multiple sclerosis, stroke), head injuries, or drug and alcohol
intoxication are the most common causes of acquired nystagmus.





 Most read

 Most read
 Most read