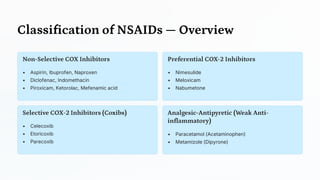
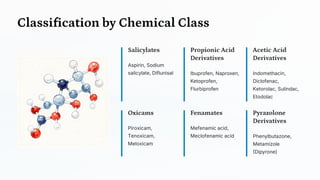
Comprehensive Overview of NSAIDs: Mechanisms, Uses, and Safety
Detailed insights into NSAIDs including their pharmacology, classification, mechanisms, clinical uses, adverse effects, contraindications, and drug interactions for effective and safe therapeutic application.
Comprehensive Overview of NSAIDs: Mechanisms, Uses, and Safety
1.
NSAIDs: Non -Steroidal
Anti-Inflammatory Drugs
Dr. Rumana Afroz
Associate Professor
Department of Pharmacology
Dhaka Medical College, Bangladesh
2.
Introduction to NSAIDs
WhatAre NSAIDs?
A chemically heterogeneous group of drugs sharing analgesic, antipyretic, and
anti-inflammatory properties
Primary Mechanism
Inhibit cyclooxygenase (COX) enzymes → reduce prostaglandin synthesis at
sites of injury and inflammation
Clinical Significance
One of the most widely used drug classes globally — available both OTC and on
prescription worldwide
Prototype Drug
Aspirin (acetylsalicylic acid), first synthesized by Felix Hoffmann in 1897 — the
cornerstone of NSAID pharmacology
3.
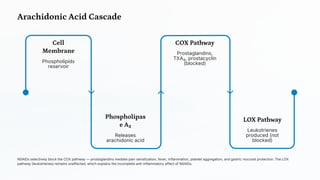
Arachidonic Acid Cascade
Phospholipas
eA₂
Releases
arachidonic acid
LOX Pathway
Leukotrienes
produced (not
blocked)
Cell
Membrane
Phospholipids
reservoir
COX Pathway
Prostaglandins,
TXA₂, prostacyclin
(blocked)
NSAIDs selectively block the COX pathway — prostaglandins mediate pain sensitization, fever, inflammation, platelet aggregation, and gastric mucosal protection. The LOX
pathway (leukotrienes) remains unaffected, which explains the incomplete anti-inflammatory effect of NSAIDs.
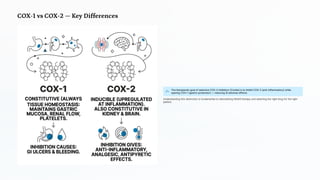
COX -1 vsCOX -2 — Key Differences
The therapeutic goal of selective COX-2 inhibitors (Coxibs) is to inhibit COX-2 (anti-inflammatory) while
sparing COX-1 (gastric protection) — reducing GI adverse effects.
Understanding this distinction is fundamental to rationalizing NSAID therapy and selecting the right drug for the right
patient.
7.
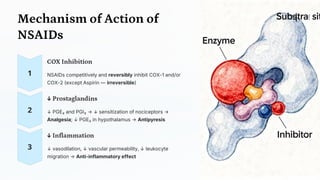
Mechanism of Actionof
NSAIDs
COX Inhibition
NSAIDs competitively and reversibly inhibit COX-1 and/or
COX-2 (except Aspirin — irreversible)
↓ Prostaglandins
↓ PGE₂ and PGI₂ → ↓ sensitization of nociceptors →
Analgesia; ↓ PGE₂ in hypothalamus → Antipyresis
↓ Inflammation
↓ vasodilation, ↓ vascular permeability, ↓ leukocyte
migration → Anti-inflammatory effect
8.
Aspirin — UniqueMechanism
Irreversible COX Inhibition
Aspirin irreversibly acetylates the serine residue at the active site of both
COX-1 and COX-2 — unlike all other NSAIDs which bind reversibly.
Why Platelets Are Special
Platelets lack a nucleus → cannot synthesize new COX enzyme →
antiplatelet effect lasts the entire platelet lifespan of 7–10 days
Dose -Dependent Effects
• Low dose (75–150 mg): Selective COX-1 inhibition → antiplatelet
• High dose (>300 mg): COX-2 inhibition → anti-inflammatory
9.
Pharmacological Actions —Analgesia
Types of Pain Relieved
Effective for mild to moderate pain: headache,
myalgia, arthralgia, dysmenorrhea, dental pain,
postoperative pain
Peripheral Action
↓ PG synthesis at site of injury → ↓ sensitization of
nociceptors → raises pain threshold locally
Central Action
↓ PG synthesis in spinal cord and brain → ↑ central
pain threshold
Advantage Over Opioids
Do NOT cause euphoria, dependence, or
respiratory depression — safer for long-term pain
management
10.
Pharmacological Actions —Antipyresis
↓ PGE₂
NSAIDs
Fever
↑ PGE₂
Pyrogens
Key Points
• NSAIDs reduce elevated body
temperature only — do NOT lower
normal temperature
• Act by resetting the hypothalamic
thermostat, not by cooling
• Increased heat dissipation: sweating,
vasodilation
Aspirin is contraindicated in
children with viral fever — risk
of Reye's syndrome. Use
Paracetamol instead.
11.
Pharmacological Actions —Anti -
Inflammation
↓ Vasodilation & Permeability
↓ PGE₂ → ↓ vasodilation and vascular permeability → ↓ redness (rubor) and swelling
(tumor)
↓ Pain Sensitization
↓ PGE₂ and PGI₂ at inflamed site → ↓ sensitization of pain receptors → ↓ dolor (pain)
Limitation: LOX Pathway Intact
NSAIDs do NOT inhibit leukotriene synthesis → incomplete anti-inflammatory effect;
may even shunt to LOX pathway
Symptomatic Only
Do NOT suppress the underlying disease process — unlike DMARDs or corticosteroids
in rheumatoid arthritis
12.
Pharmacological Actions —Other Effects
Antiplatelet
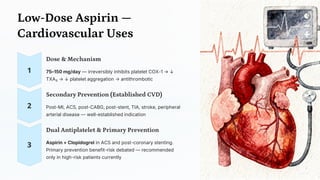
↓ TXA₂ via COX-1 → ↓ platelet aggregation. Aspirin
most potent (irreversible)
Renal Effects
↓ PGs → ↓ renal blood flow, ↓ GFR, Na⁺ and water
retention, edema
Uricosuric
High-dose Aspirin → ↑ uric acid excretion; Low-dose
Aspirin → ↑ uric acid retention
Ductus Arteriosus Closure
Indomethacin used in neonates with patent ductus
arteriosus (PDA) to promote closure
13.
Indications of NSAIDs
Pain
Management
Headache,dental
pain, postoperative
pain, dysmenorrhea,
musculoskeletal pain
Fever
Antipyresis in adults
(Paracetamol
preferred in children)
Inflammatory
Conditions
Rheumatoid arthritis,
osteoarthritis,
ankylosing
spondylitis, acute
gout
Cardiovascular
Low-dose Aspirin for MI
prophylaxis, stroke prevention,
ACS
Other Uses
PDA closure (Indomethacin),
Bartter's syndrome, pericarditis,
colon cancer prevention
14.
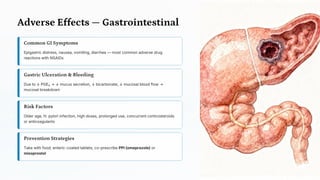
Adverse Effects —Gastrointestinal
Common GI Symptoms
Epigastric distress, nausea, vomiting, diarrhea — most common adverse drug
reactions with NSAIDs
Gastric Ulceration & Bleeding
Due to ↓ PGE₂ → ↓ mucus secretion, ↓ bicarbonate, ↓ mucosal blood flow →
mucosal breakdown
Risk Factors
Older age, H. pylori infection, high doses, prolonged use, concurrent corticosteroids
or anticoagulants
Prevention Strategies
Take with food; enteric-coated tablets; co-prescribe PPI (omeprazole) or
misoprostol
15.
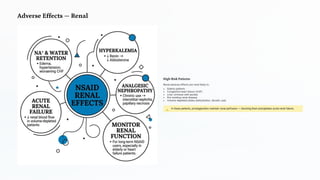
Adverse Effects —Renal
High -Risk Patients
Renal adverse effects are most likely in:
• Elderly patients
• Congestive heart failure (CHF)
• Liver cirrhosis with ascites
• Pre-existing renal disease
• Volume-depleted states (dehydration, diuretic use)
In these patients, prostaglandins maintain renal perfusion — blocking them precipitates acute renal failure.
16.
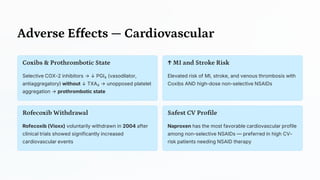
Adverse Effects —Cardiovascular
Coxibs & Prothrombotic State
Selective COX-2 inhibitors → ↓ PGI₂ (vasodilator,
antiaggregatory) without ↓ TXA₂ → unopposed platelet
aggregation → prothrombotic state
↑ MI and Stroke Risk
Elevated risk of MI, stroke, and venous thrombosis with
Coxibs AND high-dose non-selective NSAIDs
Rofecoxib Withdrawal
Rofecoxib (Vioxx) voluntarily withdrawn in 2004 after
clinical trials showed significantly increased
cardiovascular events
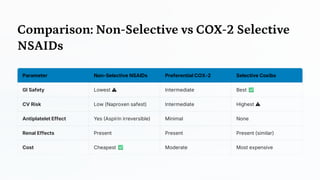
Safest CV Profile
Naproxen has the most favorable cardiovascular profile
among non-selective NSAIDs — preferred in high CV-
risk patients needing NSAID therapy
17.
Adverse Effects —Respiratory & Hypersensitivity
Samter's Triad (Aspirin -Sensitive Asthma)
• Asthma
• Nasal polyps
• Aspirin/NSAID hypersensitivity
Mechanism
↓ COX → ↑ arachidonic acid → shunted to LOX pathway → ↑ leukotrienes (LTC₄,
LTD₄) → bronchoconstriction
Other Hypersensitivity Reactions
• Urticaria, angioedema
• Anaphylaxis — especially with Aspirin
• Cross-sensitivity among NSAIDs is common in aspirin-sensitive patients
18.
Adverse Effects —Hematological & Hepatic
Antiplatelet & Bleeding
Prolonged bleeding time — avoid
NSAIDs before surgery. Aspirin
causes dose-dependent
irreversible inhibition of platelet
aggregation lasting 7–10 days
Hepatotoxicity
Diclofenac, Sulindac, Nimesulide
— elevated liver enzymes; rare but
serious hepatic failure reported
Nimesulide & Children
Nimesulide banned in children
<12 years in India due to
unacceptable hepatotoxicity risk;
also banned in several European
countries
19.
Adverse Effects —CNS & Others
Salicylism (Aspirin Toxicity)
Tinnitus, vertigo, headache, confusion — occur at
high therapeutic doses; reversible on dose reduction
Reye's Syndrome
Aspirin in children with viral illness (influenza,
varicella) → hepatic encephalopathy — rare but
potentially fatal; Aspirin is absolutely contraindicated
in children
Indomethacin CNS Toxicity
Severe headache, dizziness, psychosis, depression —
most CNS-toxic NSAID; limits its use despite potency
Obstetric Effects
↓ Prostaglandins involved in parturition → prolonged
gestation, delayed labor; premature closure of ductus
arteriosus in fetus (3rd trimester)
20.
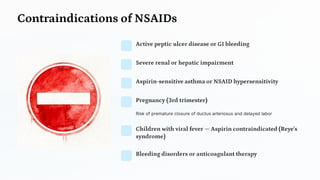
Contraindications of NSAIDs
Activepeptic ulcer disease or GI bleeding
Severe renal or hepatic impairment
Aspirin -sensitive asthma or NSAID hypersensitivity
Pregnancy (3rd trimester)
Risk of premature closure of ductus arteriosus and delayed labor
Children with viral fever —Aspirin contraindicated (Reye's
syndrome)
Bleeding disorders or anticoagulant therapy
21.
Drug Interactions ofNSAIDs
Interacting Drug Mechanism Clinical Effect
Warfarin Protein binding displacement +
antiplatelet effect
↑ Bleeding risk
Antihypertensives Na⁺ retention, ↓ PG-mediated
vasodilation
Blunted antihypertensive effect
Methotrexate ↓ Renal excretion of MTX ↑ Methotrexate toxicity
Lithium ↓ Renal clearance of lithium ↑ Lithium levels → toxicity
Corticosteroids Additive GI mucosal damage ↑↑ GI ulceration risk
22.
CHAPTER 2
Individual DrugProfiles
A systematic review of key NSAIDs — mechanisms, doses, clinical
uses, and adverse effects
23.
Aspirin (Acetylsalicylic Acid)
Mechanism
IrreversibleCOX-1 and COX-2 inhibition via acetylation of serine residue
Doses
• Analgesic/Antipyretic: 325–650 mg
• Anti-inflammatory: 3–6 g/day
• Antiplatelet: 75–150 mg/day
Uses
Fever, pain, RA, MI prophylaxis, ACS, stroke prevention, Kawasaki disease
ADRs
GI irritation, salicylism, Reye's syndrome, bleeding, hypersensitivity reactions
24.
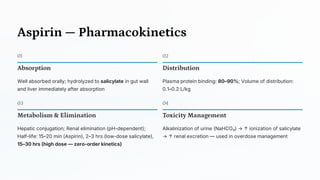
Aspirin — Pharmacokinetics
01
Absorption
Wellabsorbed orally; hydrolyzed to salicylate in gut wall
and liver immediately after absorption
02
Distribution
Plasma protein binding: 80–90%; Volume of distribution:
0.1–0.2 L/kg
03
Metabolism & Elimination
Hepatic conjugation; Renal elimination (pH-dependent);
Half-life: 15–20 min (Aspirin), 2–3 hrs (low-dose salicylate),
15–30 hrs (high dose — zero-order kinetics)
04
Toxicity Management
Alkalinization of urine (NaHCO₃) → ↑ ionization of salicylate
→ ↑ renal excretion — used in overdose management
25.
Ibuprofen
Class
Propionic acid
derivative; reversible
non-selectiveCOX
inhibitor
Dose
400–800 mg TDS; OTC
dose: 200–400 mg
Uses
Mild-moderate pain,
fever, RA, OA,
dysmenorrhea, juvenile
arthritis
ADRs
GI upset, edema, rash — least GI toxicity among NSAIDs
Ibuprofen has the best GI tolerability
among NSAIDs — considered the
safest NSAID for OTC use
26.
Naproxen
Class & Dosing
Propionicacid derivative; long-acting. Dose: 250–500
mg BD — twice-daily dosing improves patient
compliance
Clinical Uses
Arthritis, acute gout, dysmenorrhea, musculoskeletal
pain, migraine prophylaxis
Key Advantage
Most favorable cardiovascular safety profile among
all NSAIDs — preferred when CV risk is a concern
ADRs
GI effects, photosensitivity, peripheral edema — similar
to other propionic acid derivatives
27.
Diclofenac
Class
Phenylacetic acid derivative;preferential COX-2 inhibitor
Dose
50 mg TDS or 75 mg SR BD; topical gel also available for local musculoskeletal
conditions
Uses
RA, OA, ankylosing spondylitis, postoperative pain, dysmenorrhea, renal colic
Unique Feature
Also inhibits phospholipase A₂ and lipoxygenase → broader anti-inflammatory action
beyond COX inhibition alone
ADRs
Hepatotoxicity (monitor LFTs), GI effects, cardiovascular risk at higher doses
28.
Indomethacin
Class & Potency
Indoleacetic acid derivative; most
potent non-selective COX inhibitor.
Dose: 25–50 mg TDS; SR 75 mg BD
Clinical Uses
Acute gout (DOC), ankylosing
spondylitis, PDA closure in
neonates, Bartter's syndrome,
pericarditis
Toxicity Profile
Most toxic NSAID: severe
headache, dizziness, GI ulcers,
psychosis, depression, bone marrow
suppression
Despite its toxicity, Indomethacin remains the drug of choice for acute gout and the only NSAID used for PDA
closure in neonates.
29.
Ketorolac
Class
Pyrrolizine carboxylic acidderivative; potent parenteral analgesic
Dose & Route
10–30 mg IM/IV; 10 mg oral; maximum 5 days use only — strictly short-term
Uses
Short-term management of moderate-to-severe postoperative pain, renal colic,
opioid-sparing analgesia
Key Advantage
Analgesic potency comparable to Morphine 10 mg IM — without opioid side effects
(no respiratory depression, no dependence)
ADRs
GI bleeding, renal impairment — NOT for chronic use; strict 5-day limit
30.
Piroxicam
Class
Oxicam derivative; long-acting
non-selectiveCOX inhibitor
Dose & Half -life
20 mg once daily; very long t½:
45–50 hours — among the
longest of all NSAIDs
Clinical Uses
RA, OA, ankylosing spondylitis,
acute gout, dysmenorrhea
Advantage
Once-daily dosing → excellent patient compliance
ADRs
Highest GI toxicity among oxicams, photosensitivity,
peripheral edema — long half-life means effects
(including toxicity) persist longer
31.
Mefenamic Acid
Class
Fenamate (anthranilicacid
derivative)
Dose
500 mg loading, then 250
mg QID; max 7 days
Uses
Dysmenorrhea (DOC),
menorrhagia, mild-
moderate pain
ADRs
Diarrhea (characteristic), hemolytic anemia, GI irritation; avoid in renal disease
Dual mechanism: Inhibits COX and directly
antagonizes prostaglandin receptors —
explaining its superior efficacy in
dysmenorrhea
32.
Nimesulide
Class
Sulfonanilide; preferential COX-2inhibitor — popular in
India
Dose & Use
100 mg BD (adults only); used for pain, fever, OA,
dysmenorrhea
Advantages
Better GI tolerability; also inhibits PAF (platelet activating
factor) and free radicals — additional anti-inflammatory
mechanisms
Hepatotoxicity Warning
Banned in children <12 years in India and several European
countries due to serious hepatotoxicity risk
33.
Meloxicam
Class
Oxicam derivative; preferentialCOX-2 inhibitor
Dose
7.5–15 mg once daily
Uses
OA, RA, ankylosing spondylitis — first-line in arthritis management
Advantages vs Piroxicam
• Better GI tolerability than piroxicam
• Once-daily dosing (good compliance)
• Lower cardiovascular risk than true coxibs
ADRs
GI effects (less than piroxicam), peripheral edema, renal effects at higher doses
34.
Celecoxib
Class & Dose
Diarylsubstituted pyrazole; selective COX-2 inhibitor
(Coxib). Dose: 100–200 mg BD
Clinical Uses
OA, RA, ankylosing spondylitis, familial adenomatous
polyposis (FAP), acute pain
Key Advantages
No GI ulceration (spares COX-1); no antiplatelet
effect → safer in patients on anticoagulants; safe in
aspirin-sensitive patients
ADRs & Cautions
↑ Cardiovascular risk (MI, stroke), edema,
hypertension; sulfonamide allergy cross-reactivity —
check allergy history before prescribing
35.
Etoricoxib
Why Etoricoxib StandsOut
Etoricoxib is the most selective COX-2 inhibitor currently available — providing maximum GI protection among coxibs.
However, this high selectivity also confers the highest cardiovascular risk among coxibs — it is contraindicated in
established cardiovascular disease.
Never prescribe Etoricoxib to patients with established CVD, uncontrolled hypertension, or heart failure.
36.
Paracetamol (Acetaminophen)
Class &Mechanism
Para-aminophenol derivative. Inhibits COX-3 (central); acts on endocannabinoid
system. Does NOT significantly inhibit peripheral COX → no anti-inflammatory
action peripherally
Dose
500 mg–1 g TDS/QID; max 4 g/day (adults); 2 g/day in liver disease
Uses
Drug of choice for fever in children; mild-moderate pain, OA, headache; safest
NSAID-equivalent in pregnancy
Advantages
No GI irritation, no antiplatelet effect, no renal effects at therapeutic doses —
best-tolerated analgesic-antipyretic
37.
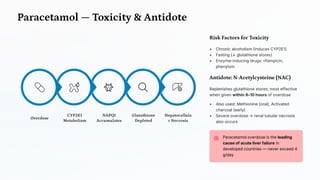
Paracetamol — Toxicity& Antidote
Hepatocellula
r Necrosis
Glutathione
Depleted
NAPQI
Accumulates
CYP2E1
Metabolism
Overdose
Risk Factors for Toxicity
• Chronic alcoholism (induces CYP2E1)
• Fasting (↓ glutathione stores)
• Enzyme-inducing drugs: rifampicin,
phenytoin
Antidote: N -Acetylcysteine (NAC)
Replenishes glutathione stores; most effective
when given within 8–10 hours of overdose
• Also used: Methionine (oral), Activated
charcoal (early)
• Severe overdose → renal tubular necrosis
also occurs
Paracetamol overdose is the leading
cause of acute liver failure in
developed countries — never exceed 4
g/day
38.
Phenylbutazone
Class
Pyrazolone derivative; potentnon-selective COX inhibitor
Historical Uses
Ankylosing spondylitis (limited), acute gout — now largely obsolete due to severe
toxicity
Why It Was Abandoned
• Agranulocytosis & aplastic anemia — life-threatening
• Peptic ulceration
• Sodium and water retention
• Hepatotoxicity
Current Status
Banned for human use in many countries; still used in veterinary medicine (horse
racing injuries)
39.
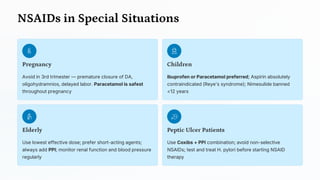
NSAIDs in SpecialSituations
Pregnancy
Avoid in 3rd trimester — premature closure of DA,
oligohydramnios, delayed labor. Paracetamol is safest
throughout pregnancy
Children
Ibuprofen or Paracetamol preferred; Aspirin absolutely
contraindicated (Reye's syndrome); Nimesulide banned
<12 years
Elderly
Use lowest effective dose; prefer short-acting agents;
always add PPI; monitor renal function and blood pressure
regularly
Peptic Ulcer Patients
Use Coxibs + PPI combination; avoid non-selective
NSAIDs; test and treat H. pylori before starting NSAID
therapy
40.
NSAIDs in RheumatoidArthritis
Role of NSAIDs in RA
NSAIDs provide symptomatic relief (pain, morning stiffness, swelling) but do
NOT modify disease progression — they address symptoms, not the underlying
autoimmune process.
Adjuncts to DMARDs
Used alongside Disease-Modifying Anti-Rheumatic Drugs:
• Methotrexate (first-line DMARD)
• Hydroxychloroquine
• Sulfasalazine
Preferred NSAIDs in RA
• Indomethacin, Diclofenac, Naproxen — commonly used
• Coxibs preferred in patients with GI risk factors
41.
NSAIDs in Gout
AcuteGout — Treatment
Indomethacin (DOC), Naproxen,
Etoricoxib — reduce PG-mediated
inflammation at the joint and
inhibit leukocyte migration to the
crystal deposit
Aspirin — Avoid in Gout
Low-dose Aspirin → ↑ uric acid
retention (blocks tubular
secretion); High-dose uricosuric
but impractical — Aspirin should
be avoided in gout
Alternatives When NSAIDs
Contraindicated
Colchicine (inhibits leukocyte
migration) and corticosteroids
(intra-articular or systemic) — use
when NSAIDs are contraindicated
(renal failure, GI bleeding)
42.
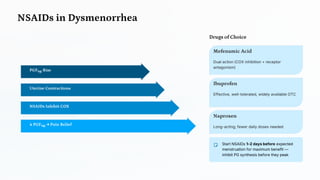
NSAIDs in Dysmenorrhea
↓PGF₂α → Pain Relief
NSAIDs Inhibit COX
Uterine Contractions
PGF₂ α Rise
Drugs of Choice
Mefenamic Acid
Dual action (COX inhibition + receptor
antagonism)
Ibuprofen
Effective, well-tolerated, widely available OTC
Naproxen
Long-acting; fewer daily doses needed
Start NSAIDs 1–2 days before expected
menstruation for maximum benefit —
inhibit PG synthesis before they peak
GI Protection Strategieswith NSAIDs
Proton Pump
Inhibitors (PPIs)
— First Choice
Omeprazole,
Pantoprazole — most
effective
gastroprotection; co-
prescribed with NSAIDs
in all high-risk patients
(elderly, prior PUD,
concurrent steroids)
Misoprostol —
Prostaglandin
Analogue
PGE₁ analogue that
replaces depleted
mucosal
prostaglandins;
effective but commonly
causes diarrhea and
cramping
H₂ Blockers
Ranitidine — less
effective than PPIs;
useful for prevention of
duodenal ulcers but
inadequate for gastric
ulcer protection
Formulation Strategies
Enteric-coated/SR formulations — reduce local GI irritation but do NOT prevent
systemic GI effects (which are mechanism-based)