Comprehensive Overview of Neonatal Birth Injury: Causes, Classification, and Management
Detailed insights into birth injury types, predisposing factors, recognition, and management strategies for neonatal birth trauma during labor and delivery.
Comprehensive Overview of Neonatal Birth Injury: Causes, Classification, and Management
1.
Birth Injury
PREDISPOSING FACTORS,CLASSIFICATION , RECOGNITION ,
INVESTIGATION AND MANAGEMENT OF NEONATAL BIRTH TRAUMA
PRESENTED BY:-
SHASHANK PANDEY
BAMS FINAL PROFF
GAMC REWA
2.
Definition and Terminology:-
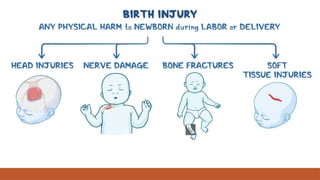
Birthinjury (birth trauma) is any structural destruction or functional deterioration of fetal
tissues/organs resulting from mechanical forces (compression, traction, shear) or hypoxic insult
sustained during labor and delivery.
EASY UNDERSTANDING:-
• Compression – Pressure on fetal
tissue
• Traction-Pulling force
• Shear- Opposite forces causing
tissue damage
• Hypoxic insult: Reduced oxygen
supply
3.
Avoidable Birth injury:-
Avoidablebirth injuries are injuries that occurs due to preventable factors such as improper
obstetric care , delayed intervention or inadequate intrapartum care , these injuries an be
minimized or prevented with skilled obstetric management.
COMMON CAUSES:-
Excessive traction during delivery
Improper use of forceps and vaccum extractor
Delay in recognizing fetal distress
Delayed caesarean section when indicated.
Inappropriate management of shoulder dystocia.
Unavoidable Birth Injury:-
Unavoidablebirth injuries are injuries that occur despite appropriate and timely obstetric care
they result from unavoidable maternal or fetal factors and cannot always be protected.
COMMON CAUSE:-
Macrosomia{large body}
Shoulder dystocia despite correct management
Breech presentation
Prolonged or obstructed labour
Prematurity and fragile fetal issue
6.
Unavoidable Birth Injury:-
EXAMPLE:-
Claviclefracture during difficult delivery.
Minor cephalohematoma after prolonged labour.
Soft tissue bruising in a difficult vaginal delivery.
NOTE:-
Birth injury is Distinct from 'birth asphyxia', though
the two can frequently coexist.
Birth Injury Distinct from congenital malformation,
which predates labor entirely.
7.
EPIDEIMOLOGY &INCIDENCE OFBIRTH INJURY
OVERALL INCIDENCE: 2-7 per 1000 live births and incidence varies with obstetrics practice,
mode of delivery and reporting methods.
COMMON BIRTH INJURIES:-
Soft tissue injury is among the most frequent birth injuries which include caput succedaneum,
bruises , abrasions and cephalohematoma, these injuries are usually self limiting and resolv without
treatment.
Clavicle fracture is most common bone injury ; incidences increases in macrosomia and shoulder
Dystocia {up to 1.5–3% of vaginal deliveries with shoulder dystocia}
Brachial plexus injury occurs in approximately 0.1 -0.3% of live births commonly associated with
shoulder dystocia and excessive lateral traction{recovery is spontaneous}
Trend over time:Overall incidence has fallen with improved intrapartum monitoring, but
instrumental-delivery-related injury persists
8.
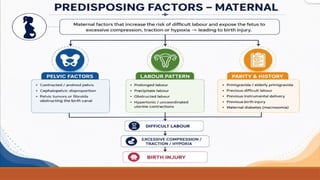
PREDISPOSING FACTORS-MATERNAL
Maternal factorsincrease the risk of difficult labour and may expose the fetus to excessive
compression ,traction or hypoxia, thereby increasing the likelihood of birth injury.
PELVIC FACTORS-
Abnormal maternal pelvic anatomy may interfere with the normal passage of the fetus through
the birth canal , resulting in difficult delivery and increased mechanical trauma
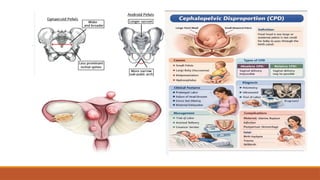
Contracted or android pelvis.
Cephalopelvic disproportion
Pelvic tumors and uterine abnormalities obstruvting the birth canal
10.
PREDISPOSING FACTORS-MATERNAL
LABOUR PATTERN:-
Abnormallabour increases the duration or force of delivery, predisposing the fetus to
compression ,traction and hypoxic injury
Prolonged first and second stage of labour
Precipitate {very rapid} labour
Obstructed labour
Hypertonic or uncoordinated uterine contractions.
11.
PREDISPOSING FACTORS-MATERNAL
PARITY &OBSTETRIC HISTORY:-
Certain maternal characteristics and previous obstetrics events increase the likelihood of difficult
delivery and birth trauma.
Primigravida {first pregnancy} and Elderly primigravida [pregnancy>30 years}
Previous difficult labour and instrumental delivery
Previous birth injury
Maternal diabetes with Fetal macrosomia
Previous obstetric complications.
13.
PREDISPOSING FACTORS- FETAL
Certainfetal characterstics increase the suspectibility to birth injuries by making labor and
vaginal delivery more difficult orby increasing the fragility of fetal tissues
SIZE & GROWTH:-
Excessive fetal size or immature tissues increase the likelihood of mechanical trauma during
birth.
Macrosomia{Bt wt. >4kg}
Large fetal head circumference
Prematurity [Fragile bones and blood vessels]
IUGR/low birth weight
14.
PREDISPOSING FACTORS- FETAL
PRESENTATIONAND LIE:-
Abnormal fetal presentation or lie may lead to difficult labor and increase the need for
instrumental or operative delivery.
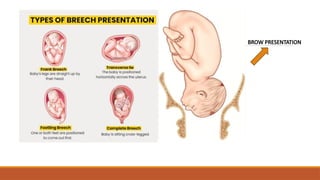
Breech presentation
Face or brow presentation
Transverse lie
Persistent Occipito posterior position
Shoulder dystocia
PREDISPOSING FACTORS- FETAL
STRUCTURALAND MEDICAL FACTORS:-
Congenital abnormalities and certain fetal disorders predispose the new born to trauma even
during uncoplicated delivery.
Congenital anomalies {hydrocphalus}
Multiple gestation
Skeletal Dysplasia
Bleeding disorders [haemophilia ,thrombocytopenia]
Connective tissue disorder
17.
PREDISPOSING FACTORS –INTRAPARTUM AND
INSTRUMENTAL
Obstetric interventions and difficult intrapartum events acan increase the risk ofbirth injury ,
particularly when excessive traction or improper techniques are required
INSTRUMENTAL DELIVERY:-
Instrument assisted vaginal delivery may cause fetal trauma,especially when difficult extraction
or repeated attempts are needed.
Forceps delivery[particularly mid cavity forceps]
Vaccum vent house extraction
Combined use of forceps and vacuum
18.
PREDISPOSING FACTORS –
INTRAPARTUMAND INSTRUMENTAL
MANIPULATIVE PROCEDURE:-
Certain obstetrics maneuvers performed to correct fetal position or facilitate delivery may
increase the risk of injury.
Internal or External Cephalic Version
Breech extraction
Manual rotation of fetal head
19.
PREDISPOSING FACTORS –
INTRAPARTUMAND INSTRUMENTAL
EMERGENCY SITUATIONS:
Emergency deliveries often require rapid intervention ,increasing the possibility of fetal trauma
Shoulder dystocia requiring obstetric maneuvers.
Rapid delivery due to fetal distress.
Excessive traction or inexperienced operator.
20.
PATHOPHYSIOLOGY OF BIRTHINJURY
Birth injury occurs due to mechanical trauma during labour and delivery , often worsened by
fetal hypoxia .The main mechanisms are:
Compression: Pressure on fetal tissues causes edema , ischemia and nerve injury.
Traction : Excessive pulling stretches or tears nerves , muscles and blood vessels.
Rotation: Forceful twisting may injure the cervical spine or intracranial structures.
Hypoxia: Reduced oxygen supply weakens tissues and increases the severity of injury.
SOFT TISSUE INJURY
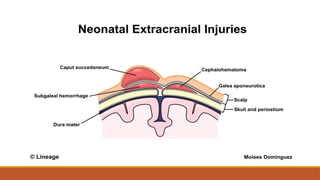
Softtissue injury — scalp edema
DEFINITION: Diffuse edematous swelling of the scalp from pressure of the presenting part
against the dilating cervix
LOCATION: Scalp, over the presenting part — often crosses the midline
Borders: Crosses suture lines (extraperiosteal / subcutaneous plane)
Onset : Present at birth; may enlarge slightly over first hours
Consistency: Soft, pitting edema; may show overlying petechiae or bruising
Resolution: Spontaneous, within 2–3 days
Management: Reassurance only — no active intervention needed
24.
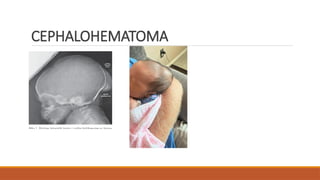
CEPHALHEMATOMA
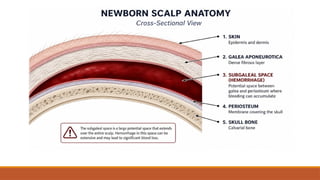
DEFINITION: Subperiosteal collectionof blood over one (occasionally both) cranial bones, most
often parietal
BORDERS: Strictly LIMITED by suture lines — periosteum is firmly attached at sutures.
Onset: Appears hours after birth (absent at birth); enlarges over 1–2 days
Complications: Hyperbilirubinemia from RBC breakdown; rarely infection or underlying linear
fracture
Resolution: Weeks to months; may leave a firm calcified rim palpable for months
Management : Conservative — AVOID aspiration/incision (introduces infection risk); monitor
serum bilirubin
subperiosteal hemorrhage
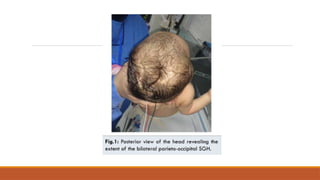
Subgaleal Hemorrhage
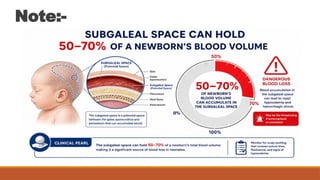
Bleeding intothe potential space between the galea aponeurotica and periosteum — a large,
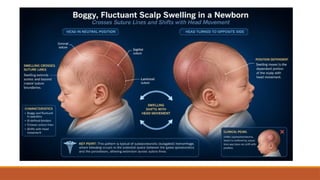
distensible space with no anatomical boundary, allowing blood to spread across the entire scalp
and track into the neck.
Cause: Strongly associated with vacuum (ventouse) extraction — shearing of emissary veins
connecting scalp and dural sinuses
Extent: NOT limited by sutures — diffuse, boggy swelling that can extend from eyebrows to the
nape of the neck.
Volume risk: The subgaleal space can accommodate a newborn's ENTIRE circulating blood
volume
Onset: Typically apparent within the first 6 hours after a difficult/instrumental delivery,
progressively enlarging
29.
Subgaleal Hemorrhage :
Recognitionand Management
Subgaleal hemmorhage is a life threatning neonatal emergency caused by bleeding into the
subgaleal space . Early recognition and prompt management are essential to prevent
hypovolemic shock and reduce mortality.
RECOGNITION:
Rapidly enlarging boggy , fluctuant scalp swelling that crosses suture lines and shift with head
movement
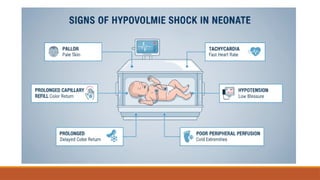
Signs of Hypovolemic shock include pallor , tachycardia, prolonged capillary refill ,
hypotensionand poor peripheral perfusion
Head circumference should be measured every 15-30 minutes to detect progressive bleeding.
Laboratory findings may show falling haemoglobin/hematocrit and coagulopathy{prolonged
PT/APTT thrombocytopenia}
31.
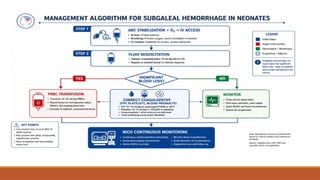
Subgaleal Hemorrhage :Management
Immediate ABC stabilization with oxygen and intravenous access
Start fluid Resuscitation followed by packed red blood cell transfusion if significant blood loss is
present.
Correct coagulopathy using fresh frozen plasma[FPP],Platelets or other blood products as
indicated
Continuous monitoring of vital signs ,head circumference , urine output and hemoglobinin the
NICU until the infant is haemodynamically stable.
OTHER SOFT TISSUEINJURIES
Bruising & Petechiae:-
Superficial ecchymoses over the presenting part (face in face presentation, buttocks in breech).
Petechiae may follow a tight nuchal cord. Usually resolve within a week without treatment;
extensive bruising warrants a bilirubin check.
Abrasions & Lacerations:-
Superficial scalp lacerations from fetal scalp electrodes, scalp pH sampling, or scalpel injury
during Cesarean section. Manage with simple wound care; rarely need suturing.
Subcutaneous Fat Necrosis:-
Firm, well-circumscribed, erythematous/violaceous nodules or plaques appearing days to weeks
after a traumatic delivery, typically over pressure points. Can rarely cause hypercalcemia —
monitor calcium if extensive.
36.
SKELETAL INJURIES:-
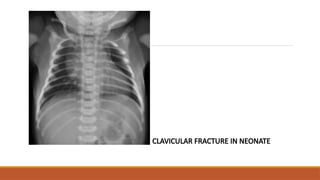
CLAVICLE FRACTURE:
Themost common significant bony birth injury
Clinical Features:
Mechanism: compression of the shoulder against the pubic symphysis during shoulder dystocia, or
excessive traction on the shoulder
• Asymmetric / decreased Moro reflex on affected side
• • Crepitus and irregularity palpable over the clavicle
• • Pseudoparalysis — infant avoids moving the arm
• • Local tenderness, swelling, occasional visible deformity
• • Often initially missed; picked up on day 2–3 as a palpable callus
Management & Prognosis
Excellentprognosis — heals rapidly with abundant callus formation within 7–10 days.
• • Gentle handling; avoid traction on the affected arm
• • Pin the sleeve to clothing or apply a figure-of-8 bandage for comfort in select cases
• • Analgesia rarely required beyond gentle handling
• • Reassure parents — remodels completely, no long-term deformity
• • Always examine for an associated brachial plexus injury
39.
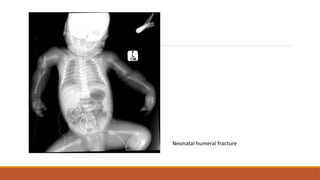
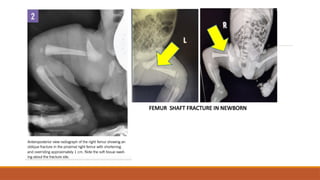
Humerus & FemurFractures
Humerus fracture: Occurs with a trapped/extended arm during breech extraction or during
difficult delivery of the arm in cephalic presentation
Femur fracture:Occurs during breech extraction, particularly with a footling breech or excessive
traction on the leg
Clinical signs Pain on passive movement, swelling, deformity or angulation, pseudoparalysis of
the limb, palpable crepitus.
Management: Splinting / immobilization (e.g., Velpeau bandage for humerus, splint/traction for
femur)
Prognosis: Excellent — neonatal bones heal rapidly with abundant callus; remodeling is
complete even with child angulation
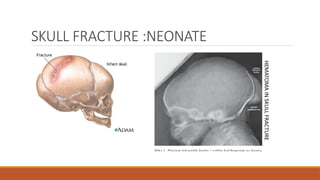
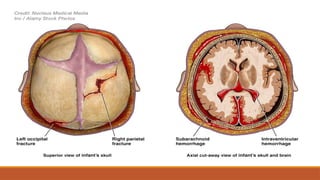
Skull Fractures
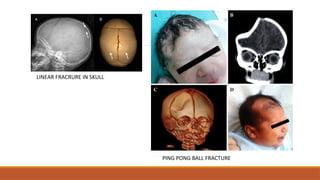
Linear Fracture
Mostcommon type of skull fracture at birth.
• • Usually asymptomatic, incidental finding
• • Often discovered on skull X-ray done for another indication
• • Underlies some cephalhematomas — always suspect if the swelling is unusually large or
tense
• • No treatment necessary in the vast majority of cases
• • Heals spontaneously with normal bone remodeling
43.
Skull Fractures
Depressed ('Ping-PongBall') Fracture:
Caused by forceps blade pressure or in-utero compression against the maternal pelvis/sacral
promontory.
• • Visible/palpable indentation of the skull, resembling a dented ping-pong ball
• • Neuroimaging (CT) to assess for underlying hemorrhage
• • Many resolve spontaneously or with gentle manual/vacuum elevation
• • Neurosurgical elevation reserved for significant depression or neurological signs
RareSkeletalInjuries
Uncommon fractures encounteredin difficult deliveries
Rib Fractures:
Occasionally seen after difficult manual extraction or vigorous chest compressions during
resuscitation. Usually asymptomatic; heal without intervention. Rarely, may cause respiratory
distress if multiple/flail segment.
Vertebral Injury:
Rare, associated with excessive traction/hyperextension in breech delivery. May coexist with spinal
cord injury — always assess neurological function of all four limbs when suspected.
Facial Bone / Mandible Fracture:
Extremely rare; associated with severe forceps trauma. May cause feeding difficulty or asymmetry.
Usually managed conservatively with close feeding support.
47.
Peripheral Nerve Injuries
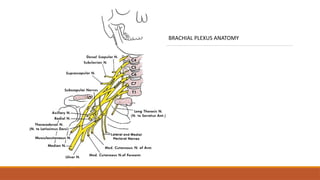
BRACHIALPLEXUS RELEVENT ANATOMY:
Brachial plexus is formed by C5–T1 ventral rami.
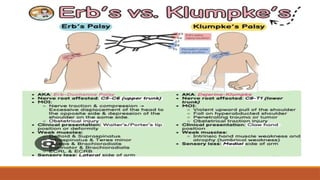
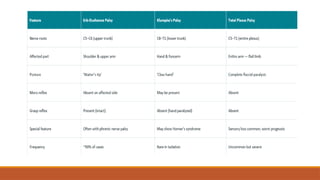
Upper trunk (C5–C6): Supplies shoulder and elbow muscles → injury causes Erb's palsy.
Lower trunk (C8–T1): Supplies intrinsic hand muscles → injury causes Klumpke's palsy.
T1 sympathetic fibers: Injury may cause Horner's syndrome.
Mechanism: Excessive lateral traction between the baby's head/neck and shoulder stretches or
tears the plexus.
Clinical importance: Site of injury determines the type and severity of paralysis.
Erb-Duchenne Palsy (UpperBrachial
Plexus Injury)
Mechanism
Erb-Duchenne palsy is the most common neonatal brachial plexus injury, caused by injury to
the C5–C6 nerve roots (upper trunk).
It occurs due to excessive lateral traction between the fetal head and shoulder during difficult
delivery, particularly in shoulder dystocia, breech extraction, forceps/vacuum delivery, and fetal
macrosomia.
The injury may range from neuropraxia to nerve root avulsion.
50.
Clinical Features
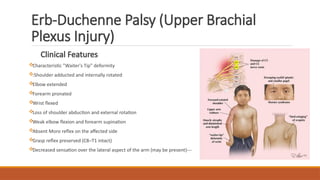
Characteristic "Waiter'sTip" deformity
:Shoulder adducted and internally rotated
Elbow extended
Forearm pronated
Wrist flexed
Loss of shoulder abduction and external rotation
Weak elbow flexion and forearm supination
Absent Moro reflex on the affected side
Grasp reflex preserved (C8–T1 intact)
Decreased sensation over the lateral aspect of the arm (may be present)---
Erb-Duchenne Palsy (Upper Brachial
Plexus Injury)
51.
Erb-Duchenne Palsy:Management and
Prognosis:-
Management
Conservativetreatment is the first-line approach.
Immobilization of the affected limb for 7–10 days.
Gentle passive range-of-motion exercises and physiotherapy to prevent contractures.
Regular neurological assessment and follow-up.
Microsurgical nerve repair, grafting, or nerve transfer is indicated if there is no biceps function
by 3–6 months or evidence of severe nerve injury.
52.
Klumpke's Palsy (LowerBrachial Plexus
Injury)
Klumpke's palsy is caused by injury to the C8–T1 nerve roots (lower trunk) of the brachial
plexus.
It occurs due to excessive upward traction on the infant's arm during difficult delivery,
particularly in breech extraction or forceful delivery of the upper limb.
The injury may vary from neuropraxia to nerve root avulsion. In severe cases, involvement of T1
sympathetic fibers may lead to Horner's syndrome.
53.
Clinical Features
.Weakness or paralysis of the intrinsic muscles of the hand.
Claw hand deformity due to paralysis of lumbricals and interossei
Weak finger flexion and impaired grip strength.
Grasp reflex absent or weak
Sensory loss over the medial aspect of the forearm and hand.
Horner's syndrome (ptosis, miosis, anhidrosis) if T1 sympathetic fibers are involved.
54.
Management & Prognosis
Conservativetreatment is the initial approach.
Gentle immobilization for 7–10 days.
Passive range-of-motion exercises and physiotherapy.
Occupational therapy to maintain hand function.
Microsurgical nerve repair, grafting, or nerve transfer if there is no neurological recovery by 3–6 months
or in severe nerve injury.
Prognosis is less favorable than Erb's palsy because lower trunk injuries are more often associated with
nerve root avulsion.
Mild neuropraxia usually recovers completely.Severe injuries may result in persistent hand weakness,
claw hand deformity, and muscle wasting.
Presence of Horner's syndrome indicates a poor prognosis.
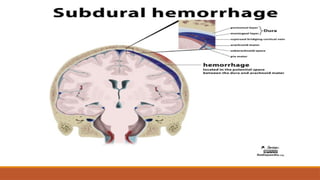
Subdural Hemorrhage
Subdural hemorrhage(SDH) is the collection of blood between the dura mater and arachnoid mater,
caused by tearing of the bridging veins during difficult or traumatic delivery. It is the most common
intracranial hemorrhage associated with birth trauma.
Etiology / Mechanism
Subdural hemorrhage occurs due to rupture of bridging veins caused by excessive compression, traction, or
rotational forces on the fetal head during delivery. It is commonly associated with:
Instrumental delivery (forceps/vacuum)
Prolonged or difficult labor
Breech delivery
Cephalopelvic disproportion (CPD)
Macrosomia
59.
Subdural Hemorrhage
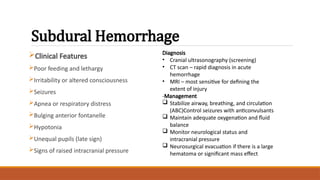
Clinical Features
Poorfeeding and lethargy
Irritability or altered consciousness
Seizures
Apnea or respiratory distress
Bulging anterior fontanelle
Hypotonia
Unequal pupils (late sign)
Signs of raised intracranial pressure
Diagnosis
• Cranial ultrasonography (screening)
• CT scan – rapid diagnosis in acute
hemorrhage
• MRI – most sensitive for defining the
extent of injury
-Management
Stabilize airway, breathing, and circulation
(ABC)Control seizures with anticonvulsants
Maintain adequate oxygenation and fluid
balance
Monitor neurological status and
intracranial pressure
Neurosurgical evacuation if there is a large
hematoma or significant mass effect
61.
Intraventricular Hemorrhage (IVH)
Intraventricularhemorrhage is bleeding into the cerebral ventricles arising from the fragile germinal matrix, seen
predominantly in preterm infants; it is one of the most important causes of neonatal neurological morbidity.
Etiology / Risk Factors
Extreme prematurity (<32 weeks) with fragile germinal matrix vasculature
Fluctuating cerebral blood flow (hypoxia, hypercarbia, rapid volume infusion)
Birth asphyxia and respiratory distress syndrome
Difficult or traumatic vaginal/instrumental delivery
Coagulopathy
Clinical Features
May be silent/asymptomatic in mild cases (Grade I-II)
Sudden deterioration - apnea, bradycardia, falling hematocrit in severe bleed (Grade III-IV)
Bulging anterior fontanelle, seizures
Hypotonia and lethargy
62.
Subarachnoid Hemorrhage (SAH)
Subarachnoidhemorrhage is bleeding into the subarachnoid space and is the most common type of intracranial hemorrhage in term infants,
usually arising from small bridging or leptomeningeal vessels.
Etiology
Hypoxic-ischemic injury
Traumatic delivery - instrumental or precipitate labour
Coagulopathy
Extension from an adjoining subdural or intraventricular bleed
Clinical Features & Management
Often asymptomatic - an incidental finding on imaging
Classic presentation - seizures on day 2 of life with a well infant in between episodes
Lethargy and poor feeding in some infants
Diagnosis confirmed on CT/MRI; management mainly supportive with anticonvulsants for seizures
Prognosis excellent in the majority of cases
64.
Spinal Cord Injury
Spinalcord injury is a rare but serious birth injury caused by excessive traction, hyperextension or rotation of the fetal spine
during delivery, most often involving the cervical region.
Mechanism
Excessive longitudinal traction during breech extraction
Hyperextension of the fetal head and neck
Forceful rotation while managing shoulder dystocia
Most common site - cervico-thoracic junction
Clinical Features
Flaccid paralysis below the level of injury
Absent deep tendon reflexes initially (spinal shock)
Diaphragmatic breathing/respiratory distress in high cervical lesions
Loss of bladder and bowel control; absent response to pain below the lesion
65.
Spinal Cord Injury:Management
Management
Immediate stabilization of the spine and cautious, gentle handling
Respiratory support where diaphragmatic involvement is present
MRI spine is the investigation of choice
Multidisciplinary rehabilitation - physiotherapy and long term follow up
Prognosis
Guarded, and depends largely on the level and severity of injury
High cervical lesions carry the poorest outcome due to respiratory compromise
66.
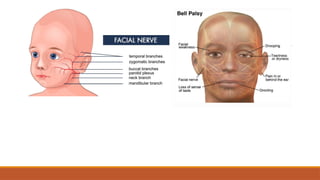
Facial Nerve Palsy
Facialnerve palsy is the most common cranial nerve injury at birth, caused by compression of the facial nerve as it
exits the stylomastoid foramen.
Mechanism
Pressure from the forceps blade, particularly with outlet forceps
Compression against the maternal sacral promontory in utero
Prolonged pressure during a difficult vaginal delivery
Clinical Features
Facial asymmetry, more obvious on crying
Affected side shows a smooth forehead, open eye, flattened nasolabial fold and drooping angle of mouth
Forehead wrinkling preserved in peripheral type; absent forehead sparing suggests a central lesion
Feeding difficulty with milk dribbling from the angle of the mouth on the affected side
68.
Facial Nerve Palsy:Management & Prognosis
Management
Mostly conservative - eye protection with lubricant drops or a patch to prevent corneal drying
Gentle feeding support
Physiotherapy if recovery is delayed
Surgical exploration rarely needed - reserved for cases with no improvement over several weeks
Prognosis
Peripheral (traumatic) type - excellent, recovers spontaneously within days to weeks in most infants
Central type (nuclear agenesis/ CNS injury) - poorer recovery, needs further neurological evaluation
Palsy persisting beyond 3 weeks needs nerve conduction studies and specialist referral
69.
Visceral Birth Injuries
Visceralinjuries are rare but serious birth injuries involving trauma to abdominal or thoracic organs, occurring due to excessive
compression or manipulation during a difficult delivery.
Organs Commonly Involved
Liver - most commonly injured organ (subcapsular hematoma or rupture)
Spleen - subcapsular hematoma, especially in breech delivery
Adrenal gland - adrenal hemorrhage, more common on the right side
Kidney - rare, usually associated with a pre-existing renal anomaly
Risk Factors
Breech delivery and difficult manual extraction
Macrosomia and precipitate labour
Hepatosplenomegaly (e.g., due to hemolytic disease)
Coagulopathy or bleeding disorder
70.
Visceral Birth Injuries:Recognition & Management
Clinical Features
Often silent initially - subcapsular hematoma may go unnoticed for 24-48 hours
Sudden pallor, tachycardia, abdominal distension and shock if the hematoma ruptures
A palpable abdominal mass or flank/scrotal discoloration may be present
Falling hematocrit with no obvious external blood loss should raise suspicion
Diagnosis
High index of suspicion in predisposed infants (breech, macrosomia)
Abdominal ultrasound - investigation of choice for hepatic/splenic/adrenal hemorrhage
Serial hematocrit and vital sign monitoring
Management
Conservative management with close monitoring for a stable subcapsular hematoma
Correction of coagulopathy and blood transfusion for significant blood loss
Emergency laparotomy if free rupture with hemoperitoneum and hemodynamic instability
71.
INVESTIGATION OF BIRTHINJURY
A systematic approach combining careful clinical examination with targeted investigations is essential to confirm the diagnosis,
assess severity and guide management of birth injury.
Imaging
Cranial ultrasonography - bedside screening for intracranial/intraventricular hemorrhage
X-ray - to confirm suspected fracture of clavicle, humerus, femur or skull
CT scan - rapid assessment of acute intracranial bleed
MRI - most sensitive for defining extent of nerve, soft tissue and spinal injury
Laboratory
Complete blood count and hematocrit - to detect significant blood loss/anemia
Coagulation profile (PT/APTT, platelet count) if a bleeding disorder is suspected
Serum bilirubin - to monitor hemolysis related jaundice with hematoma resorption
Nerve conduction studies/EMG for peripheral nerve injury not showing recovery
72.
GENERAL PRINCIPLES OFMANAGEMENT
Management of birth injury is largely supportive and individualized, aimed at stabilizing the infant,
preventing complications and promoting recovery.
Prompt recognition and accurate assessment of the type and severity of injury
Stabilization of airway, breathing and circulation in significant injury
Gentle handling of the affected part - avoid unnecessary traction or manipulation
Correction of anemia/coagulopathy where indicated
Close monitoring - vital signs, neurological status and serial imaging as needed
Early physiotherapy for nerve and skeletal injuries
Referral to specialist (neurosurgery/orthopedics/neurology) for severe or non-resolving injury
Parental counselling and reassurance - most birth injuries carry a good prognosis
73.
PREVENTION OF BIRTHINJURY
Most avoidable birth injuries can be minimized through careful antenatal assessment, skilled
intrapartum care and timely decision making.
Accurate antenatal assessment of fetal size, growth and presentation
Careful selection of mode of delivery in suspected macrosomia or malpresentation
Judicious use of instrumental delivery, performed only by an experienced operator
Timely recognition of fetal distress with prompt intervention
Adequate management protocol for shoulder dystocia
Continuous intrapartum monitoring of maternal and fetal status
Avoiding excessive traction or force at every stage of delivery
74.
SUMMARY
Birth injury resultsfrom mechanical trauma and/or hypoxia sustained during labour and
delivery
May be avoidable, due to preventable factors, or unavoidable, despite optimal obstetric care
Ranges from minor soft tissue injury to major intracranial or spinal cord damage
Predisposing factors are broadly maternal, fetal and intrapartum/instrumental
Early recognition, targeted investigation and prompt supportive management improve
outcome
The majority of birth injuries carry a good prognosis with timely and appropriate care
75.
REFERENCES
1. Akangire G,Carter B. Birth Injuries in Neonates. Pediatrics in Review. 2016;37(11):451-462.
2. Rosenberg AA. Traumatic Birth Injury. NeoReviews. 2003;4(10):e270-e276.
3. Birth Trauma. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2025.
4. Kliegman RM, St. Geme JW, Schuh AM, et al., eds. Nelson Textbook of Pediatrics. 22nd ed.
Philadelphia: Elsevier; 2024.
5. Eichenwald EC, Hansen AR, Martin CR, Stark AR, eds. Cloherty and Stark's Manual of Neonatal
Care. 9th ed. Philadelphia: Wolters Kluwer; 2023.
6. Paul VK, Bagga A, eds. Ghai Essential Pediatrics. 10th ed. New Delhi: CBS Publishers & Distributors;
2023.
7. Konar H. DC Dutta's Textbook of Obstetrics Including Perinatology and Contraception. 11th ed.
New Delhi: Jaypee Brothers Medical Publishers; 2026.

 Most read