Comprehensive Overview of Menopause: Definition, Symptoms, and Management
Detailed insights into menopause including its definition, endocrinology, symptoms, organ changes, diagnosis, and treatment options including hormone therapy and lifestyle modifications.
DEFINITION
Menopause means permanentcessation of menstruation at the end of
reproductive life due to loss of ovarian follicular activity.
The clinical diagnosis is confirmed following stoppage of menstruation (amenorrhea)
for twelve consecutive months without any other pathology. As such, a woman is
declared to have attained menopause only retrospectively.
Menopause transition is the period during which a woman passes from reproductive
to the non-reproductive stage. It covers 4–7 years on either side of menopause. This
transition is associated with elevated serum FSH levels and variable length of
menstrual cycle and/or missed menses.
3.
CLINICAL IMPORTANCE
Due toincreased life expectancy, about one-third of life span will be spent as
estrogen deficiency stage with long-term symptomatic and metabolic
complications.
Age at which menopause occurs is genetically predetermined. It is not related to
the number of pregnancies, race, socioeconomic conditions, education, height,
weight, age at menarche or age of last childbirth.
Thinner women, cigarette smoking and severe malnutrition may cause early
menopause. The age of menopause ranges between 45–55 years, average being
50 years.
4.
ENDOCRINOLOGY OF MENOPAUSALTRANSITION
AND MENOPAUSE
Few years prior to menopause, the ovarian follicles gets depleted and become resistant
to pituitary gonadotropins. Hence, folliculogenesis is impaired with diminished
estradiol production [50–300 pg/mL before menopause to 10–20 pg/mL after
menopause].
This decreases negative feedback effect on HPA resulting in increase in FSH and LH
subsequently. Disturbed folliculogenesis during this period, results in anovulation,
oligoovulation, premature corpus luteum.
The mean cycle length also shortens due to shortening of the follicular phase. Luteal
phase remains constant. In late menopausal transition, there is accelerated rate of
follicular depletion. Estradiol production drops down to the optimal level of 20 pg/mL
no endometrial growth absence of menstruation.
→ →
5.
Estrogens :
Following menopause,the predominant estrogen is estrone and to a lesser extent estradiol.
The major source of estrone is peripheral conversion (aromatization) of androgens from adrenals
(mainly) and ovaries.
With times, the sources fail to supply the precursors of estrogen and about 5–10 years after
menopause, there is a sharp fall in estrogen and also the trophic hormones. The woman is said to
be in a state of true menopause.
Androgens :
After menopause, the stromal cells of the ovary continue to produce androgens because of
increase in LH. The main androgens are androstenedione and testosterone.
The peripheral levels are reduced due to conversion of androgens to estrone.However, the
cumulative effect is decrease in—estrogen:androgen ratio.
This results in increased facial hair growth and change in voice.
6.
Progesterone:
A trace amountof progesterone detected is probably adrenal
in origin.
Gonadotropins:
During menopause, there is fall in the level of prolactin and inhibin.
This lead to increase in the level of FSH from the pituitary.
Ultimately, due to physiologic aging GnRH and both FSH,LH decline along with
decline of estrogens.
7.
ORGAN CHANGES
Ovaries :Shrink in size, become wrinkled and white with thinning of the cortex.
There is abundance of stromal cells which have got secretory activity.
Fallopian Tubes: Show feature of atrophy with thinning of muscle coat,
disappearance of cilia.
The Uterus : Becomes smaller and the ratio between the body and the cervix reverts
to the 1:1 ratio.
The endometrium becomes thin and atrophic. In women with high endogenous
estrogens, the endometrium may be proliferative or even hyperplastic.
The cervical secretion becomes scanty.
8.
The Vagina :becomes narrower due to gradual loss of elasticity,the vaginal
epithelium becomes thin.
The rugae progressively flatten. Doderlein’s bacillus is absent. The vaginal pH
becomes alkaline.
Maturation index (parabasal, intermediate and superficial cells) is 10/85/5.
The vulva : shows features of atrophy. The labia becomes flattened and the pubic
hair becomes scantier.
Breast : Become flat and pendulous due to reabsorption of fat and atrophy of the
glands,also the nipple size decreases.
9.
Bone Metabolism :
Followingmenopause, there is a loss of bone mass by 3–5% per year which is
due to estrogen deficiency
Osteoporosis is a condition where there is reduction in bone mass but bone
mineral to matrix ratio is normal. Osteoporosis is defined when the T-Score
(normal -1.0 and -2.5) is <2.5 and risk of fracture is high.
Parathyroid hormone (PTH) and interleukin-I (IL-I) are involved in osteoporosis
whereas estrogen prevents osteoporosis
Cardiovascular System :
Risk of cardiovascular disease is high in postmenopausal women due to
deficiency of estrogen
Estrogen increases HDL (particularly HDL2) and decreases LDL and total
cholesterol.
It inhibits platelet and macrophage (foam cell) aggregation at the vascular intima
10.
MENSTRUATION PATTERN PRIORTO
MENOPAUSE
Any of the following patterns are observed:
Gradual decrease in both amount and duration.
Irregular with or without excessive bleeding.
Abrupt cessation of menstruation (rare).
11.
MENOPAUSAL SYMPTOMS
The importantsymptoms and the health concerns of menopause:
Vasomotor symptoms
Urogenital atrophy
Osteoporosis and fracture
Cardiovascular disease
Cerebrovascular diseases
Psychological changes
Skin and hair
Sexual dysfunction
Dementia and cognitive decline.
12.
Vasomotor Symptoms:
The characteristicsymptom of menopause is ‘hot flash’. Hot flash is characterized by sudden
feeling of heat followed by profuse sweating
The physiologic changes with hot flashes are perspiration and cutaneous vasodilation
Hot flash coincides with GnRH pulse secretion with increase in serum LH level. It may last for
1–10 minutes, with disturbed sleep due to night sweats.
Genital and urinary symptoms :
Estrogen plays an important role to maintain the epithelium of vagina, urinary bladder and
the urethra.
Estrogen deficiency produces atrophic epithelial changes in these organs.
This may cause dyspareunia and dysuria.
Sexual dysfunction :
Estrogen deficiency is often associated with decreased sexual desire.
This may be due to psychological changes (depression anxiety) as well asatrophic changes of
the genitourinary system.
13.
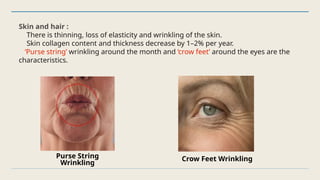
Skin and hair:
There is thinning, loss of elasticity and wrinkling of the skin.
Skin collagen content and thickness decrease by 1–2% per year.
‘Purse string’ wrinkling around the month and ‘crow feet’ around the eyes are the
characteristics.
Purse String
Wrinkling
Crow Feet Wrinkling
14.
Osteoporosis and fracture:
Following meno-pause there is decline in collagenous bone matrix resulting in osteoporotic
changes
Osteoporosis may be primary (Type 1) due to estrogen loss, age, deficient nutrition
(calcium, vitamin D) or hereditary.
Secondary (Type 2) due to endocrine abnormalities (parathyroid, diabetes) or medication
Osteoporosis may lead to back pain, loss of height and kyphosis.
Fracture may involve the vertebral body, femoral neck or distal forearm (Colles’ fracture).
Cardiovascular and cerebrovascular effects :
Oxidation of LDL and foam cell formation cause vascular endothelial injury, cell death and
smooth muscle proliferation
These women develop insulin resistance and central (android) obesity.
All these lead to vascular atherosclerotic changes, vasoconstriction and thrombus
formation
Risks of ischemic heart disease, coronary artery disease and strokes are also increased
15.
DIAGNOSIS OF MENOPAUSE
Cessationof menstruation for consecutive 12 months.
Average age of menopause: 50 years.
Appearance of menopausal symptoms ‘hot flash’ and ‘night sweats’.
Vaginal cytology—showing maturation index of at least 10/85/5 (features of low estrogen)
Serum estradiol: < 20 pg/mL
Serum FSH and LH: > 40 mlU/mL (three values at weeks interval required).
MANAGEMENT
PREVENTION
Spontaneous menopause is unavoidable. However, artificial menopause induced by
surgery (bilateral oophorectomy) or radiation (gonadal) or chemotherapy during
reproductive period can to some extent be prevented or delayed.
Every woman with postmenopausal symptoms should be adequately explained about the
physiologic events. This will remove her fears and minimize or dispel the symptoms of
anxiety, depression and insomnia.
16.
TREATMENT
NON HORMONAL TREATMENT
Lifestylemodifications : This includes physical activity (weight bearing), reducing
high coffee intake, smoking and excessive alcohol. There should be adequate
calcium intake (300 mL of milk), reducing medications that causes bone loss
(corticosteroids).
Nutritious diet : Balanced diet with calcium and protein is helpful.
Exercise : Weight bearing exercises, walking and jogging.
Bisphosphonates : Prevent osteoclastic bone resorption.
It improves bone density and prevents fracture.
Calcitonin : Inhibits bone resorption by inhibiting osteoclasts.
Should be given along with calcium and vitamin D.
17.
Selective estrogen receptormodulators (SERMs) :
SERMs, such as raloxifene has shown to increase bone mineral density, reduce serum
LDL and to raise HDL2 level.
It inhibits the estrogen receptors at the breast and endometrial tissues, thus
reducing the risk of breast cancer and endometrial cancer.
Clonidine :
It may be used to reduce the severity and duration of hot flashes.
It is helpful where estrogen is contraindicated (hypertension).
Side effects are hypotension, dry mouth and constipation.
Paroxetine :
It is a selective serotonin reuptake inhibitor, which is effective to reduce hot flashes
(both the frequency and severity).
Phytoestrogens containing isoflavones are found to lower the incidence of vasomotor
symptoms, osteoporosis and cardiovascular disease.
18.
HORMONE THERAPY (HT)
Indications:
Relief of menopausal symptoms
Relief of vasomotor symptoms
Prevention of osteoporosis
To maintain the quality of life in menopausal years.
Special group of women to whom HT should be prescribed:
Premature ovarian failure
Gonadal dysgenesis
Surgical or radiation menopause
19.
HORMONAL THERAPY [HT]
HTprevents bone loss and stimulate new bone formation.
Estrogen plays direct role, as it’s receptors are found in the osteoblasts.
Women receiving HT should be given an extra 500 mg of calcium daily. Total
daily requirement of Ca in postmenopausal women is 1.5 g.
HT is cardiovascular protective. Estrogen prevents oxidation of LDL. LDL on
oxidation produces vascular endothelial changes leading to intimal smooth
muscle proliferation and atherosclerosis.
In postmenopausal women, there is some amount of insulin resistance and
hyperinsulinemia, as estrogen improves glucose metabolism.
20.
The principal hormoneused in HT is estrogen.
This is ideal for a woman who had her uterus removed (hysterectomy), but in
a woman with an intact uterus, only estrogen therapy leads to endometrial
hyperplasia and even endometrial carcinoma.
Addition of progestins for last 12–14 days each month can prevent this
problem.
Commonly used estrogens : conjugated estrogen or micronized estradiol
Commonly used progestins : medroxyprogesterone
acetate(MPA),micronized progesterone or dydrogesterone.
Hormone therapy should be used with the lowest effective dose and for a
short period of time.
21.
Therapy Options :
OralEstrogen: CEE 0.3–0.625 mg (only in hysterectomized women)
Estrogen + Cyclic Progestin: For women with intact uterus
Continuous Estrogen + Progestin: Prevents hyperplasia
Transdermal Estrogen: Bypasses first-pass metabolism, safer for
thrombotic risk
Other Delivery Methods :
Percutaneous Gel, Transdermal Patch, Vaginal Cream
Other Drugs in Menopausal HT :
Tibolone
Testosterone
Parathyroid hormone (PTH)
22.
Risks of HormoneTherapy:
Endometrial cancer
Breast cancer
Venous thromboembolism (VTE)
Coronary Heart Disease (CHD)
Dementia
Alzheimer’s
23.
ABNORMAL MENOPAUSE
Premature Menopause:
Menopause at or below the age of 40
It may be familial
Treated with hormone replacement therapy
Delayed Menopause :
Menopause fails to occur even beyond 55 years
Common causes are constitutional, uterine fibroids, diabetes mellitus and
estrogenic tumor of the ovary.
24.
Artificial menopause:
Permanent cessationof ovarian function done by artificial means, e.g.
surgical removal of ovaries by radiation or chemotherapy is called artificial
menopause.
Surgical menopause:
Menopausal symptoms seen in women who have bilateral oophorectomy.
Radiation menopause:
Suppression of the ovarian function by external gamma radiation in
women below the age of 40.
This is not permanent.
Intracavity introduction of radium can cause castration effect by
destroying the endometrium and also by depressing the ovarian function.