Headache
Unit- Neurological Disorder
Subject - AHN , B.Sc. Nursing 4th Semester
By. Mr Govinda
Bsc nursing MSc Nursing MA clinical Psychology
Assistant Professor MTCN
Headache or cephalgia
The world Cephalgia come from the Greek word
“ Kephale” - meaning - Head
“Algos”- meaning - Pain.
Headache means pain or discomfort in the head, scalp, or
neck region.
Introduction
Headache is one of the most common neurological symptoms and a frequent
reason for seeking medical care. It is defined as pain or discomfort in any
part of the head, scalp, face, or upper neck resulting from stimulation of
pain-sensitive structures such as blood vessels, meninges, cranial nerves,
muscles, and periosteum. Headache is not a disease itself but a symptom of
many underlying conditions, ranging from primary headache disorders (such
as migraine, tension-type headache, and cluster headache) to secondary
causes (such as infection, hypertension, head injury, brain tumors, or
intracranial hemorrhage). A careful assessment of the headache's onset,
location, duration, severity, associated symptoms, and triggering factors is
essential for accurate diagnosis and appropriate management. Early
identification and treatment can reduce complications and improve the
patient's quality of life.
Definition:- MediLexicon's medical dictionary
headache is defined as pain in any part of the head,
including the inside of the head, scalp, upper neck,
and face.
Definition:-
Headache means pain in various parts of the head,
not confirmed to the area of distribution of any area.
Definition:- A/C Anil Sharma
Headache is defined as pain in the
head or upper neck. It can manifest as
a cluster headache, migraine, or
tension-type headache.
Incidence
India: According to population-based studies,
approximately 63.9% of Indian adults suffer
from headache disorders annually. Migraine
affects about 25.2% and tension-type
headache affects about 35.1% of the adult
population, making headache one of the most
common neurological disorders in India.
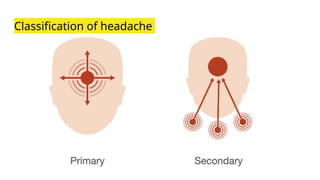
Classification And etiology of headache
According to the International Headache Society,
headache is classified into (ICHD 3):
Part one – Primary
Part two – Secondary
Part three – Painful Cranial Neuropathies, Other Facial
Pain, and Other Headaches.
Types of headache
Headaches are broadly divided into three main
categories:
1. Primary Headache
2. Secondary Headache
3. Painful Cranial Neuropathies, Other Facial Pains, and
Other Headaches
Classification of headache
1.Primary Headache
● A Primary Headache is one for which no organic cause can be identified
Or no any underlying medical condition.
● It is believed to occur due to dysfunction or overactivity of pain-
sensitive structures in the brain and is often associated with a genetic
predisposition.
● Primary headaches are disorders in themselves rather than symptoms
of another disease.
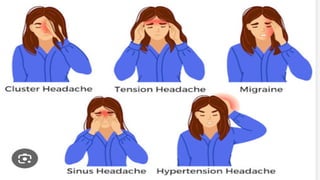
● The major types of primary headache include:
1. Migraine headache
2. Tension-type headache
3. Cluster headache
4. Other primary headache disorders
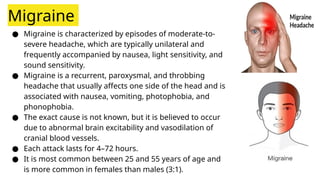
Migraine
● Migraine is characterized by episodes of moderate-to-
severe headache, which are typically unilateral and
frequently accompanied by nausea, light sensitivity, and
sound sensitivity.
● Migraine is a recurrent, paroxysmal, and throbbing
headache that usually affects one side of the head and is
associated with nausea, vomiting, photophobia, and
phonophobia.
● The exact cause is not known, but it is believed to occur
due to abnormal brain excitability and vasodilation of
cranial blood vessels.
● Each attack lasts for 4–72 hours.
● It is most common between 25 and 55 years of age and
is more common in females than males (3:1).
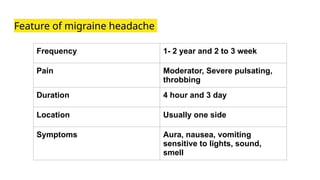
Feature of migraine headache
Frequency 1- 2 year and 2 to 3 week
Pain Moderator, Severe pulsating,
throbbing
Duration 4 hour and 3 day
Location Usually one side
Symptoms Aura, nausea, vomiting
sensitive to lights, sound,
smell
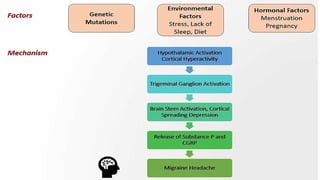
Etiology of Migrane
● Genetic Predisposition
Strong family history of migraine.
Gene mutations affecting ion channels and neurotransmitter regulation increase susceptibility.
● Neurovascular Dysfunction
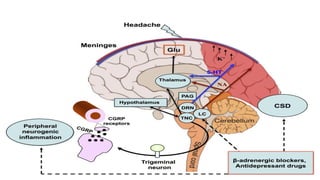
Abnormal activation of the trigeminovascular system.
Release of vasoactive neuropeptides, especially Calcitonin Gene-Related Peptide (CGRP),
leading to vasodilation, neurogenic inflammation, and pain.
● Cortical Spreading Depression (CSD)
A wave of neuronal and glial depolarization that spreads across the cerebral cortex.
Responsible for migraine aura and activation of pain pathways.
● Neurotransmitter Imbalance
Dysregulation of serotonin (5-HT).
Altered dopamine and CGRP activity also contribute to migraine attacks.
Etiology of Migrane
● Hormonal Factors
Fluctuations in estrogen and progesterone, particularly during menstruation,
pregnancy, and menopause.
Explains the higher prevalence of migraine in women.
● Environmental and Lifestyle Triggers
Emotional stress and anxiety.
Sleep deprivation or irregular sleep.
Fasting or skipping meals.
Dehydration.
Bright lights, loud noises, and strong odors.
Weather or barometric pressure changes.
Certain foods and drinks such as caffeine, alcohol (especially red wine),
chocolate, aged cheese, processed foods, monosodium glutamate (MSG), and
Risk factors
1. Caffeine Use or Withdrawal
Excessive intake of coffee, tea, or energy drinks may trigger migraine.
Sudden withdrawal from regular caffeine consumption can also precipitate an attack.
2. Excess Chocolate
Chocolate contains caffeine and phenylethylamine, which may trigger migraine in sensitive individuals.
3. Bright Lights and Loud Noise
Exposure to bright sunlight, flashing lights, computer/mobile screens, or loud sounds can stimulate the
brain and trigger migraine.
4. Strong Odors
Perfumes, incense, cigarette smoke, paint fumes, petrol, and certain chemicals may provoke migraine
attacks.
5. Smoking
Active smoking and exposure to secondhand smoke can irritate blood vessels and increase the risk of
migraine.
6. Emotional Stress
Anxiety, tension, depression, excitement, anger, and mental stress are common migraine triggers.
Migraine may also occur after stress is relieved ("weekend migraine").
7. Sleep Disturbances
Lack of sleep, excessive sleep, irregular sleep schedules, shift work, or poor sleep quality can trigger
migraine episodes.
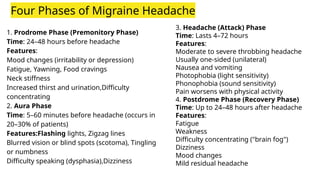
Four Phases of Migraine Headache
● Prodrome (Premonitory) Phase
● Aura Phase
● Headache (Attack) Phase
● Postdrome (Recovery) Phase
1. Prodrome Phase (Premonitory Phase)
Time: 24–48 hours before headache
Features:
Mood changes (irritability or depression)
Fatigue, Yawning, Food cravings
Neck stiffness
Increased thirst and urination,Difficulty
concentrating
2. Aura Phase
Time: 5–60 minutes before headache (occurs in
20–30% of patients)
Features:Flashing lights, Zigzag lines
Blurred vision or blind spots (scotoma), Tingling
or numbness
Difficulty speaking (dysphasia),Dizziness
3. Headache (Attack) Phase
Time: Lasts 4–72 hours
Features:
Moderate to severe throbbing headache
Usually one-sided (unilateral)
Nausea and vomiting
Photophobia (light sensitivity)
Phonophobia (sound sensitivity)
Pain worsens with physical activity
4. Postdrome Phase (Recovery Phase)
Time: Up to 24–48 hours after headache
Features:
Fatigue
Weakness
Difficulty concentrating ("brain fog")
Dizziness
Mood changes
Mild residual headache
Four Phases of Migraine Headache
2. Tension-Type Headache –
● Mild to moderate, pressing or tightening pain on both sides
of the head; often related to stress or muscle tension.
● Tension-type headache, also known as muscle contraction
headache, results from prolonged and sustained contraction
of the scalp and neck muscles (frontal, temporal, occipital,
and cervical muscles).
● It is the most common type of primary headache, especially
in adolescents and middle-aged adults, and is more common
in women.
● The pain is typically dull, pressing, or tightening in nature
and is often described as a tight band around the head.
● It is usually bilateral (affecting both sides of the head) and
ranges from mild to moderate in intensity.
● It is generally not associated with nausea or vomiting,
although sensitivity to light or sound may occasionally occur.
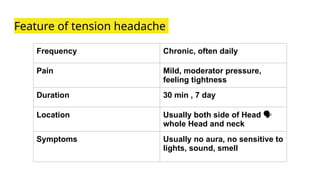
Feature of tension headache
Frequency Chronic, often daily
Pain Mild, moderator pressure,
feeling tightness
Duration 30 min , 7 day
Location Usually both side of Head
️ 🗣️
whole Head and neck
Symptoms Usually no aura, no sensitive to
lights, sound, smell
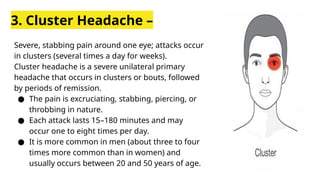
3. Cluster Headache –
Severe, stabbing pain around one eye; attacks occur
in clusters (several times a day for weeks).
Cluster headache is a severe unilateral primary
headache that occurs in clusters or bouts, followed
by periods of remission.
● The pain is excruciating, stabbing, piercing, or
throbbing in nature.
● Each attack lasts 15–180 minutes and may
occur one to eight times per day.
● It is more common in men (about three to four
times more common than in women) and
usually occurs between 20 and 50 years of age.
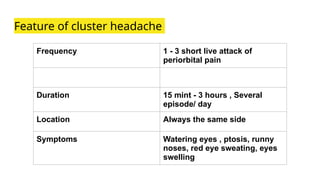
Feature of cluster headache
Frequency 1 - 3 short live attack of

periorbital pain
Duration 15 mint - 3 hours , Several
episode/ day
Location Always the same side
Symptoms Watering eyes , ptosis, runny
noses, red eye sweating, eyes
swelling
2.Secondary Headache
A Secondary Headache is caused by another
condition that triggers pain-sensitive areas in
the neck and head. Secondary headaches can
be a warning sign of a more serious
underlying condition including:
(the continuation likely lists conditions such
as infection, trauma, hypertension, etc.)
Causes / Types of Secondary Headache:
1. Head or neck trauma (e.g., post-traumatic headache)
2. Vascular disorders (e.g., stroke, hypertension,
aneurysm)
3. Non-vascular intracranial disorders (e.g., brain tumor,
intracranial pressure)
Painful Cranial Neuropathies, Other Facial Pains, and Other Headaches
3️
3️
⃣
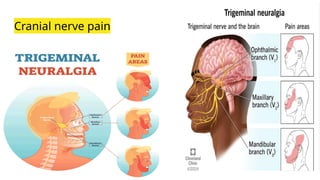
● This group includes headaches caused by nerve disorders or facial
pain syndromes.
● Cranial nerve pain, also known as cranial neuralgia, is a type of
headache or facial pain caused by irritation, inflammation, or
compression of one or more cranial nerves. It is characterized by
sudden, severe, sharp, stabbing, or electric shock-like pain along
the distribution of the affected nerve.
● Trigeminal neuralgia
● Occipital neuralgia
● Glossopharyngeal neuralgia
● Central or primary facial pain syndromes
Cranial nerve pain
4. Other Primary Headaches –
● Primary stabbing headache● Primary cough headache
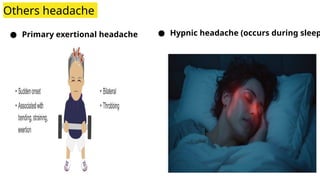
Others headache
● Primary exertional headache ● Hypnic headache (occurs during sleep
Other ……..
4. Substance use or withdrawal (e.g., alcohol,
caffeine)
5. Infection (e.g., meningitis, sinusitis)
6. Disorder of homeostasis (e.g., high blood
pressure, low oxygen)
7. Disorders of the skull, neck, eyes, ears, nose,
sinuses, teeth, or mouth
Trigeminal
The trigeminal ganglion, also known as the semilunar or
Gasserian ganglion, is the sensory ganglion of the fifth
cranial nerve (trigeminal nerve).
Function
It is the main sensory relay point for the face, transmitting
sensations of touch, pain, and temperature to the brain.
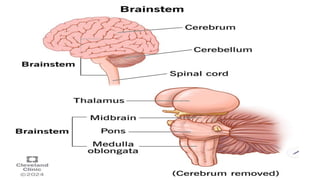
Brain stem
The three main parts of the brainstem are the midbrain, pons, and medulla
oblongata. These parts are located in descending order, connecting the
spinal cord to the forebrain and controlling vital functions like breathing,
heart rate, and blood pressure.
Midbrain: The most superior (uppermost) section of the brainstem.
Pons: Located below the midbrain.
Medulla oblongata: The most inferior (lowest) and narrowest part, which
connects to the spinal cord.
CgRP
Substance P and CGRP (calcitonin gene-
related peptide) are neuropeptides co-
released from sensory nerve fibers that play
roles in pain signaling and neurogenic
inflammation.
History
• Location / Duration
• Severity
• Onset: Sudden or gradual
• Quality: Throbbing, constant, pressure-like, intermittent
• Aggravating & Relieving Factors: Time of day, sleep, light, sound, activity
• Previous Headaches: Comparison with past
• Periodicity and Temporal Relationship (e.g., menstrual cycle)
• Response to Treatments
• Headache Diary / Trigger Tracker
Assessment and Diagnostic Findings
History
Drug history:- medication history, alcohol,
and drug use and smoking history.
Medical history:- asthma, peptic ulcer, Head
injury, anxiety stress etc .
Family history:-
History of headache and other medical
problems.
1. General appearance:
Observe for distress, anxiety, or photophobia.
2. Vital signs:
Check temperature, blood pressure, and pulse.
Fever infection; high BP hypertensive headache.
→ →
3. Head and scalp:
Inspect and palpate for tenderness (temporal arteritis, trauma, sinusitis).
4. Eyes:
Check vision, pupils, fundus (papilledema raised intracranial pressure).
→
5. Neck:
Check neck stiffness (meningitis, subarachnoid hemorrhage).
6. Neurological examination:
Assess cranial nerves, motor, sensory, reflexes, and coordination.
7. ENT examination:
Sinus tenderness, ear or throat infection.
Physical Examination
2. Diagnostic Investigations
Erythrocyte Sedimentation Rate (ESR): Detects
inflammation
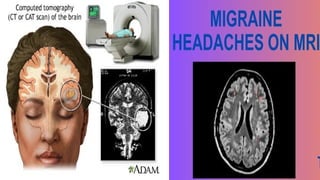
MRI: Detects structural or inflammatory brain changes
CT Scan: Evaluates brain structure and possible bleeding
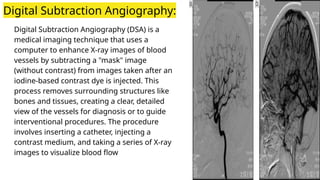
Digital Subtraction Angiography:
Digital Subtraction Angiography (DSA) is a
medical imaging technique that uses a
computer to enhance X-ray images of blood
vessels by subtracting a "mask" image
(without contrast) from images taken after an
iodine-based contrast dye is injected. This
process removes surrounding structures like
bones and tissues, creating a clear, detailed
view of the vessels for diagnosis or to guide
interventional procedures. The procedure
involves inserting a catheter, injecting a
contrast medium, and taking a series of X-ray
images to visualize blood flow
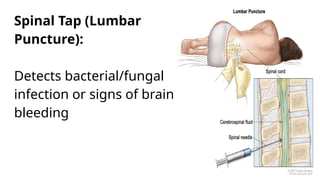
Spinal Tap (Lumbar
Puncture):
Detects bacterial/fungal
infection or signs of brain
bleeding
3. Key Points for Clinical Evaluation
Identify type of headache: Primary vs. Secondary
Assess relation to stress, sleep, and lifestyle
Document any neurological symptoms (e.g., visual
changes, weakness)
Rule out serious conditions (e.g., meningitis,
hemorrhage, tumor)
Treatment of headache
1. Pharmacology Management
2. Non pharmacology Management
3. Nursing Management
Pharmacology Management
A. For Mild Headache (Tension type or simple headache):
Paracetamol (Acetaminophen) – 500–1000 mg orally
Mechanism of action: Inhibits prostaglandin synthesis in the central nervous system, reducing
pain and fever.
Indications: Mild to moderate headache and fever.
NSAIDs (Nonsteroidal Anti-inflammatory Drugs):
Ibuprofen 200–400 mg
Mechanism of action: Inhibits cyclooxygenase (COX-1 and COX-2), reducing prostaglandin
production.
Indications: Mild to moderate headache, muscle pain, and inflammation.
Aspirin 300–600 mg
Naproxen 250–500 mg
Mechanism of action: Inhibits cyclooxygenase (COX-1 and COX-2), providing analgesic and anti-
inflammatory effects.
Indications: Tension-type headache, migraine, and musculoskeletal pain.
B. For Migraine:
NSAIDs or Paracetamol for mild attacks
Paracetamol (Acetaminophen)
Dose: 500–1000 mg orally
Action: Relieves pain by inhibiting prostaglandin synthesis in the
central nervous system.
Side effects: Liver toxicity in overdose.
Triptans (Serotonin agonists) – e.g. for migraine
Sumatriptan
Rizatriptan
Triptans (Serotonin Receptor Agonists)
Triptans are serotonin receptor agonists that provide relief from
migraines by constricting blood vessels and altering nerve signals in
the brain.
Sumatriptan
Dose: 50–100 mg orally at onset of migraine (may repeat after 2
hours if needed; maximum 200 mg/day).
Rizatriptan
Dose: 5–10 mg orally at onset (may repeat after 2 hours; maximum
30 mg/day).
Mechanism of Action
● Constrict dilated cranial blood vessels.
● Inhibit release of inflammatory neuropeptides (e.g., CGRP).
● Block transmission of pain signals through the trigeminal
nerve.
Indications
Acute moderate to severe migraine.
Migraine not relieved by simple analgesics.
Antiemetics for nausea – e.g. Metoclopramide, Domperidone
antiemetics work by blocking these receptors, preventing signals from the chemoreceptor
trigger zone (CTZ) and the vomiting center (nucleus tractus solitarius) from triggering nausea
and vomiting.
Metoclopramide 10 mg orally/IV
Domperidone 10 mg orally
Why are they given?
Relieve nausea and vomiting associated with migraine.
Ergotamine
Ergot Alkaloid (Antimigraine agent)
Mechanism of Action
Acts as a serotonin (5-HT1) receptor agonist.
Causes constriction of dilated cranial blood vessels.
Inhibits the release of inflammatory neuropeptides and reduces
pain transmission through the trigeminal nerve.
Indications
Acute migraine attacks
Cluster headache (less commonly used)
Most effective when taken at the beginning of a migraine attack.
Dose
Ergotamine: 1–2 mg orally or sublingually at the onset of
migraine.
May repeat as prescribed.
Maximum dose: 6 mg/day and 10 mg/week.
Pharmacology agent for migraine prophylaxis
Beta blockers: Propranolol
Dose: 40–160 mg/day orally in 2 divided doses (maximum 240 mg/day)
Calcium channel blockers: Verapamil
Dose: 80–120 mg orally three times daily or sustained-release 120–240 mg once daily.
Antidepressants: Amitriptyline
Dose: Start with 10–25 mg at bedtime; gradually increase to 25–75 mg/day.
Anticonvulsants: Topiramate,
Dose: Start with 25 mg at night; increase gradually to 50–100 mg twice daily. Valproate
Dose: 250–500 mg orally twice daily.
Calcitonin Gene-Related Peptide (CGRP) Monoclonal Antibodies
Erenumab- Dose: 70 mg subcutaneous injection once monthly (may be increased to
140 mg once monthly).
Mechanism: Blocks the action of CGRP, a protein involved in migraine pain and
inflammation, thereby reducing the frequency of migraine attacks.
Indication: Used for patients with frequent or chronic migraine who do not respond
adequately to conventional preventive medicines.
C. For Cluster Headache:
Acute attack:
100% oxygen inhalation
Sumatriptan injection
Prevention:
Verapamil, Lithium, or Prednisolone (short course)
Sinusitis antibiotics - Amoxicillin–Clavulanate
→
875/125 mg orally twice daily for 5–7 days
Hypertension antihypertensives- Amlodipine 5–10 mg
→
orally once daily; Labetalol 20 mg IV initially (emergency)
Meningitis antibiotics- Ceftriaxone 2 g IV every 12
→
hours + Vancomycin 15–20 mg/kg IV every 8–12 hours;
Ampicillin 2 g IV every 4 hours if indicated
Non pharmacology Management
Nursing management
Nursing Diagnosis: Acute/chronic pain (headache) related to intracerebral arterial vasoconstriction as
evidenced by visual analog scale (pain score 8) and facial grimacing.
Expected Outcome: The pain of the patient will be reduced to some extent as evidenced by visual analog scale
(pain score 3).
Nursing Interventions
● Assess pain intensity, location, duration, and characteristics using the Visual Analog Scale (VAS) regularly.
● Monitor vital signs and neurological status (level of consciousness, pupils, motor and sensory function).
● Provide a quiet, dark, and calm environment to reduce sensory stimulation.
● Encourage bed rest during severe headache episodes and minimize physical activity.
● Position the patient comfortably with the head elevated about 30° unless contraindicated.
● Administer prescribed medications (analgesics, NSAIDs, triptans, antiemetics, or prophylactic drugs) and
monitor for effectiveness and adverse effects.
● Apply a cold compress to the forehead or neck if tolerated to help reduce pain.
● Encourage relaxation techniques such as deep-breathing exercises, guided imagery, or meditation.
● Identify and avoid headache triggers (stress, bright light, loud noise, fasting, dehydration, certain foods).
● Maintain adequate hydration and encourage small, frequent meals if nausea is present.
● Reassess pain 30–60 minutes after interventions and document the patient's response.
● Educate the patient about medication adherence, lifestyle modifications, sleep hygiene, stress
management, and when to seek immediate medical care for severe or unusual headaches.
Nursing management
Nursing diagnosis: Disturbed sleep pattern related to pain, discomfort from recurrent
headaches as evidenced by difficulty falling asleep and daytime fatigue.
Expected outcome: The sleeping pattern will be improved as evidenced by reporting
fewer awakenings and feeling more rested upon waking.
Nursing Interventions
● Assess sleep pattern, duration, and factors disturbing sleep.
● Assess pain intensity regularly and provide pain relief before bedtime.
● Provide a quiet, dark, and comfortable environment for sleep.
● Encourage a regular sleep schedule and bedtime routine.
● Teach relaxation techniques such as deep breathing or meditation before sleep.
● Limit caffeine, nicotine, and heavy meals in the evening.
● Minimize nighttime disturbances and cluster nursing care.
● Administer prescribed analgesics or sleep medications as ordered.
● Encourage adequate daytime activity and avoid long daytime naps.
● Monitor sleep quality and document improvement.
Nursing management
Anxiety related to recurrent headache episodes and fear of pain recurrence.
Goal:
Patient will report reduced anxiety and demonstrate effective coping
strategies.
Nursing Interventions:
● Assess anxiety level.
● Provide reassurance and emotional support.
● Explain the disease and treatment plan.
● Encourage expression of feelings.
● Teach stress management and relaxation techniques.
● Encourage family support if appropriate.
Nursing management
Nursing Diagnosis
Deficient Knowledge related to lack of information about headache and its management as
evidenced by asking questions about the disease, treatment, and prevention.
Goal
Patient will verbalize understanding of headache, its treatment, and preventive measures before
discharge.
Nursing Interventions
● Assess the patient's current knowledge about headache.
● Explain the cause, symptoms, and treatment in simple language.
● Teach the correct use of prescribed medications.
● Educate about avoiding headache triggers (stress, lack of sleep, dehydration, certain foods).
● Encourage adequate hydration, balanced diet, and regular sleep.
● Teach relaxation and stress-management techniques.
● Instruct the patient to maintain a headache diary.
● Advise when to seek immediate medical care (sudden severe headache, weakness, confusion,
vision changes, seizures, or persistent vomiting).
Complications of Headache
● Status migrainosus – Migraine lasting >72 hours.
● Medication-overuse (rebound) headache due to frequent use of
analgesics.
● Chronic migraine/chronic daily headache.
● Persistent migraine aura without infarction.
● Migraine infarction (ischemic stroke associated with migraine).
● Migraine-triggered seizure (migralepsy).
● Sleep disturbances and fatigue.
● Anxiety and depression, leading to reduced quality of life.