Mr. SATENDRA PRADHAN
Assistant Professor
Department of Pharmacology
COP, SVITS, Bilaspur
Mr. SATENDRA PRADHAN
Assistant Professor
Department of Pharmacology
COP, SVITS, Bilaspur
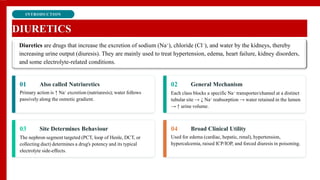
INTRODUCTION
DIURETICS
Diuretics are drugs that increase the excretion of sodium (Na⁺), chloride (Cl⁻), and water by the kidneys, thereby
increasing urine output (diuresis). They are mainly used to treat hypertension, edema, heart failure, kidney disorders,
and some electrolyte-related conditions.
01 Also called Natriuretics
Primary action is ↑ Na⁺ excretion (natriuresis); water follows
passively along the osmotic gradient.
02 General Mechanism
Each class blocks a specific Na⁺ transporter/channel at a distinct
tubular site → ↓ Na⁺ reabsorption → water retained in the lumen
→ ↑ urine volume.
03 Site Determines Behaviour
The nephron segment targeted (PCT, loop of Henle, DCT, or
collecting duct) determines a drug's potency and its typical
electrolyte side-effects.
04 Broad Clinical Utility
Used for edema (cardiac, hepatic, renal), hypertension,
hypercalcemia, raised ICP/IOP, and forced diuresis in poisoning.
INTRODUCTION
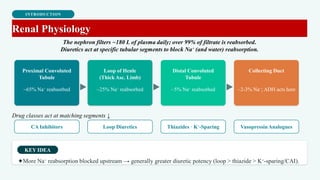
Renal Physiology
The nephron filters ~180 L of plasma daily; over 99% of filtrate is reabsorbed.
Diuretics act at specific tubular segments to block Na⁺ (and water) reabsorption.
Proximal Convoluted
Tubule
~65% Na⁺ reabsorbed
Loop of Henle
(Thick Asc. Limb)
~25% Na⁺ reabsorbed
Distal Convoluted
Tubule
~5% Na⁺ reabsorbed
Collecting Duct
~2-3% Na⁺; ADH acts here
Drug classes act at matching segments ↓
CA Inhibitors Loop Diuretics Thiazides · K⁺-Sparing VasopressinAnalogues
KEY IDEA
✦More Na⁺ reabsorption blocked upstream → generally greater diuretic potency (loop > thiazide > K⁺-sparing/CAI).
DIURETICS
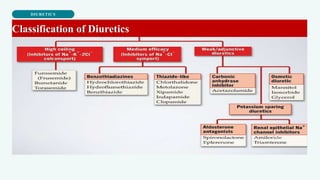
Classification of Diuretics
DIURETICS
Classification of Diuretics
Carbonic Anhydrase Inhibitors
Acetazolamide
Loop Diuretics
Furosemide, Bumetanide,
Torsemide
Thiazide Diuretics
Hydrochlorothiazide,
Chlorthalidone, Indapamide
K⁺-Sparing — Aldosterone
Antagonists
Spironolactone, Eplerenone
K⁺-Sparing — ENaC Blockers
Amiloride, Triamterene
Osmotic Diuretics
Mannitol
DIURETICS
Site of Action Along the Nephron
PCT
CA Inhibitors
Acetazolamide
Thick Ascending Limb
Loop Diuretics
Furosemide
Early DCT
Thiazides
Hydrochlorothiazide
Late DCT / Collecting Duct
K⁺-Sparing
Spironolactone, Amiloride
Mannitol (osmotic) acts throughout the tubule wherever it is freely filtered but not reabsorbed — PCT, descending limb & collecting duct
CLINICAL RULE OF THUMB
✦Proximal blockade (loop diuretics) = most Na⁺ escapes downstream reabsorption → most potent diuresis.
✦Distal blockade (thiazides, K⁺-sparing) = downstream segments have limited reabsorptive reserve → milder, ceiling effect.
✦Site of action also predicts electrolyte side-effects: loop & thiazide → hypokalemia; K⁺-sparing → hyperkalemia.
CLASS 1
Carbonic Anhydrase Inhibitors
Carbonic anhydrase inhibitors are diuretics that inhibit the enzyme carbonic anhydrase in the proximal
convoluted tubule (PCT), reducing the reabsorption of sodium and bicarbonate and increasing the excretion of
bicarbonate, sodium, potassium, and water.
Weakest diuretic class — self-limiting due to metabolic acidosis
PROTOTYPE DRUG
✦Acetazolamide (oral / IV)
✦Dorzolamide, Brinzolamide — topical, used only in
glaucoma
✦Site of action: Proximal Convoluted Tubule (PCT)
✦Sulfonamide derivative — caution in sulfa allergy
FEATURES
✦Only ~2-3% of filtered Na⁺ escapes reabsorption — mild
diuresis
✦Produces alkaline, bicarbonate-rich urine
✦Effect wanes after a few days as metabolic acidosis develops
✦Non-diuretic uses exploit carbonic anhydrase inhibition
elsewhere (eye, CNS, altitude)
CLASS 1 · MECHANISM
Carbonic Anhydrase Inhibitors — MOA
Acetazolamide inhibits carbonic anhydrase in PCT cells & luminal brush
border
↓ Conversion of CO₂ + H₂O ⇌ H₂CO₃ → H⁺ + HCO₃⁻
↓ H⁺ available for the luminal Na⁺/H⁺ antiporter (NHE3)
↓ Na⁺ reabsorption and ↓ HCO₃⁻ reabsorption into blood
Na⁺, HCO₃⁻, K⁺ and water remain in the tubular lumen
Mild Diuresis with alkaline, bicarbonate-rich urine
QUICK NOTES
✦Net effect: natriuresis + bicarbonaturia, NOT
chloriuresis
✦Chronic use → self-limiting hyperchloremic
metabolic acidosis
✦Same enzyme inhibition in the eye ↓ aqueous
humor formation
✦Same mechanism in choroid plexus ↓ CSF
formation (altitude sickness)
CLASS 1 · CLINICAL
Carbonic Anhydrase Inhibitors
Drugs: Acetazolamide, Dorzolamide, Brinzolamide
CLINICAL USES
✦Open-angle & acute angle-closure glaucoma (↓ aqueous
humor)
✦Prophylaxis & treatment of acute mountain sickness
✦Correction of metabolic alkalosis
✦Urinary alkalinization — cystine & uric acid stones
✦Adjunct in epilepsy (absence seizures)
✦Idiopathic intracranial hypertension
SIDE EFFECTS
✦Hyperchloremic metabolic acidosis
✦Hypokalemia
✦Drowsiness, paresthesia, fatigue
✦Renal calcium-phosphate stone formation
✦Sulfonamide hypersensitivity reactions
✦Contraindicated in hepatic cirrhosis (↑ ammonia →
encephalopathy)
CLASS 2
Loop Diuretics
Loop diuretics are high-potency diuretics that act on the thick ascending limb of the loop of Henle by inhibiting
the Na⁺–K⁺–2Cl⁻ (NKCC2) cotransporter, causing marked excretion of sodium, chloride, potassium, calcium,
magnesium, and water.
The most potent class — “High-Ceiling” Diuretics
PROTOTYPE DRUGS
✦Furosemide, Bumetanide, Torsemide (sulfonamide-derived)
✦Ethacrynic acid — non-sulfonamide, used if sulfa-allergic
✦Site of action: Thick Ascending Limb of Loop of Henle
✦Given orally or IV; rapid onset
FEATURES
✦Block ~25% of filtered Na⁺ reabsorption — no ceiling to
dose-response until max effect
✦Abolish the medullary concentration gradient
✦Increase Ca²⁺ and Mg²⁺ excretion (opposite of thiazides)
✦Short half-life — usually dosed multiple times daily
CLASS 2 · MECHANISM
Loop Diuretics — MOA
Furosemide secreted into PCT lumen via organic anion transporters, carried
to thick ascending limb
Binds & inhibits the Na⁺-K⁺-2Cl⁻ (NKCC2) cotransporter on the luminal
membrane
↓ Reabsorption of Na⁺, K⁺ and 2Cl⁻
Loss of lumen-positive potential → ↓ paracellular Ca²⁺ & Mg²⁺
reabsorption
↓ Medullary interstitial hypertonicity → impaired urinary concentration
Marked excretion of Na⁺, K⁺, Cl⁻, Ca²⁺, Mg²⁺ & water —
Powerful Diuresis
QUICK NOTES
✦“High-ceiling” = diuresis increases with dose,
unlike thiazides
✦Also causes venodilation (↓ preload) — fast
relief in pulmonary edema, even before
diuresis begins
✦Ototoxic — risk rises with high IV doses or
concurrent aminoglycosides
✦Effective even in reduced GFR (unlike
thiazides)
CLASS 2 · CLINICAL
Loop Diuretics
Drugs: Furosemide, Bumetanide, Torsemide, Ethacrynic acid
CLINICAL USES
✦Acute pulmonary edema (rapid preload reduction)
✦Congestive heart failure
✦Chronic edema — hepatic, renal, cardiac origin
✦Hypertension with renal impairment
✦Hypercalcemia (with saline infusion)
✦Hyperkalemia & acute renal failure — to maintain urine
flow
SIDE EFFECTS
✦Hypokalemia & hypomagnesemia
✦Hypocalcemia
✦Metabolic (hypochloremic) alkalosis
✦Ototoxicity (dose-related, reversible)
✦Hyperuricemia — may precipitate gout
✦Dehydration, hypotension; sulfonamide hypersensitivity
CLASS 3
Thiazide & Thiazide-like Diuretics
Thiazide diuretics are moderately potent diuretics that act on the distal convoluted tubule by blocking the sodium–
chloride (Na⁺–Cl⁻) cotransporter, increasing sodium and water excretion while enhancing calcium reabsorption.
Moderate potency — first-line agents for hypertension
PROTOTYPE DRUGS
✦Hydrochlorothiazide (HCTZ), Chlorothiazide
✦Thiazide-like: Chlorthalidone, Indapamide, Metolazone
✦Site of action: Early Distal Convoluted Tubule (DCT)
✦Oral only; long duration of action
KEY FEATURES
✦Block only ~5% of filtered Na⁺ — moderate, “flat” dose-
response (ceiling effect)
✦Increase Ca²⁺ reabsorption (opposite of loop diuretics)
✦Lose efficacy when GFR falls below ~30 mL/min (except
metolazone)
✦Widely combined with other antihypertensives
CLASS 3 · MECHANISM
Thiazide Diuretics — MOA
Thiazide reaches the early Distal Convoluted Tubule (DCT) via organic
anion secretion in PCT
Binds & inhibits the Na⁺-Cl⁻ symporter (NCC) on the luminal membrane
↓ Na⁺ and Cl⁻ reabsorption at the DCT
Mild volume contraction → compensatory ↑ proximal Na⁺ & Ca²⁺
reabsorption via Na⁺/Ca²⁺ exchanger
Increased Na⁺, Cl⁻ and water excretion; Ca²⁺ excretion decreases —
Moderate Diuresis
QUICK NOTES
✦Mnemonic: “thiazide = calcium sparing”,
“loop = calcium losing”
✦Also directly vasodilates — contributes to
antihypertensive effect beyond diuresis
✦Metolazone remains effective even with poor
renal function — often combined with loop
diuretics for synergy
✦Slow onset, long duration — suited to chronic
BP control
CLASS 3 · CLINICAL
Thiazide Diuretics
Drugs: Hydrochlorothiazide, Chlorthalidone, Indapamide, Metolazone
CLINICAL USES
✦Mild-to-moderate essential hypertension (first-line)
✦Chronic heart failure (mild, adjunct)
✦Nephrolithiasis — idiopathic hypercalciuria
✦Nephrogenic diabetes insipidus (paradoxical antidiuretic
effect)
✦Adjunct in osteoporosis (↓ urinary Ca²⁺ loss)
SIDE EFFECTS
✦Hypokalemia & hyponatremia
✦Hyperglycemia (impairs insulin release)
✦Hyperuricemia — may precipitate gout
✦Hyperlipidemia (mild, dose-related)
✦Hypercalcemia
✦Photosensitivity; erectile dysfunction
CLASS 4
Potassium-Sparing Diuretics
Potassium-sparing diuretics are diuretics that act on the late distal tubule and collecting duct to increase sodium and water
excretion while conserving potassium by either blocking aldosterone receptors or inhibiting epithelial sodium (ENaC) channels.
Weakest natriuretic effect — valued for conserving K⁺
Two distinct sub-mechanisms converge on the same principal cell target
4a. Aldosterone Antagonists
Spironolactone, Eplerenone
Competitively block the mineralocorticoid receptor —
indirect action
4b. ENaC Blockers
Amiloride, Triamterene
Directly plug the epithelial Na⁺ channel — aldosterone-
independent
SHARED SITE & EFFECT
✦Both act on principal cells of the late DCT / collecting duct — the site aldosterone normally acts
✦Both ↓ Na⁺ reabsorption while ↓ K⁺ and H⁺ secretion → mild diuresis with potassium conservation
✦Main risk with both: hyperkalemia, especially combined with ACE inhibitors, ARBs or renal impairment
CLASS 4A · MECHANISM
Aldosterone Antagonists — MOA
Spironolactone / Eplerenone diffuse into principal cells of the collecting
duct
Competitively block the cytoplasmic mineralocorticoid receptor
Prevent aldosterone from inducing its target gene products
↓ Synthesis of ENaC channels & Na⁺/K⁺-ATPase pumps
↓ Na⁺ reabsorption; ↓ K⁺ and H⁺ secretion into lumen
Mild Natriuresis with potassium & acid retention
QUICK NOTES
✦Onset is slow (2-3 days) — needs new protein
synthesis to be blocked
✦Spironolactone also blocks androgen &
progesterone receptors → endocrine side
effects
✦Eplerenone is more receptor-selective —
fewer hormonal effects
✦Proven mortality benefit in heart failure
(independent of diuresis)
CLASS 4A · CLINICAL
Aldosterone Antagonists
Drugs: Spironolactone, Eplerenone
CLINICAL USES
✦Primary hyperaldosteronism (Conn syndrome)
✦Resistant hypertension (add-on therapy)
✦Heart failure with reduced ejection fraction (mortality
benefit)
✦Hepatic cirrhosis with ascites
✦Female hirsutism (spironolactone — antiandrogenic)
SIDE EFFECTS
✦Hyperkalemia (danger with ACEI/ARB or renal
impairment)
✦Gynecomastia & menstrual irregularities (spironolactone)
✦GI upset, peptic ulceration
✦Eplerenone: fewer endocrine effects but similar K⁺ risk
CLASS 4B · MECHANISM
ENaC Blockers — MOA
Amiloride / Triamterene enter principal cells of the late DCT & collecting
duct
Directly block epithelial Na⁺ channels (ENaC) on the luminal membrane
↓ Na⁺ entry into the cell — independent of aldosterone
Lumen becomes less electronegative → ↓ driving force for K⁺ & H⁺
secretion
Na⁺ excreted in urine while K⁺ is conserved — Mild Diuresis
QUICK NOTES
✦Action is direct & rapid — unlike aldosterone
antagonists, no gene transcription required
✦Effective even when aldosterone is absent or
receptor-blocked
✦Amiloride blocks the same channel lithium
uses to enter principal cells — useful in
lithium-induced nephrogenic DI
✦Often combined with thiazide/loop diuretics to
offset K⁺ loss
CLASS 4B · CLINICAL
ENaC Blockers
Drugs: Amiloride, Triamterene
CLINICAL USES
✦Combined with K⁺-wasting diuretics (thiazide/loop) to
prevent hypokalemia
✦Liddle syndrome (amiloride — blocks constitutively active
ENaC)
✦Lithium-induced nephrogenic diabetes insipidus
(amiloride)
✦Ascites of hepatic cirrhosis (adjunct)
SIDE EFFECTS
✦Hyperkalemia (especially with renal impairment,
ACEI/ARB)
✦Nausea, vomiting, leg cramps
✦Triamterene: renal stone formation, crystalluria, acute
kidney injury (esp. with NSAIDs)
CLASS 5 · MECHANISM
Osmotic Diuretics
Osmotic diuretics are agents that increase the osmotic pressure of the glomerular filtrate, preventing water reabsorption
in the renal tubules and thereby increasing urine output.
Prototype: Mannitol (IV infusion)
Site of action: throughout the tubule (PCT, descending limb, collecting duct)
Mannitol infused IV — freely filtered at the glomerulus
Poorly reabsorbed by the tubular epithelium — remains in the lumen
Raises the osmolarity of tubular fluid along the nephron
Osmotically retains water in the lumen, limiting passive water & Na⁺
reabsorption
↑ Urine volume; pulls water from tissues into plasma —
↓ Intracranial & Intraocular Pressure
QUICK NOTES
✦Does not act on a specific transporter —
purely a physical osmotic effect
✦Expands plasma volume transiently before
diuresis begins
✦Contraindicated in anuria and congestive heart
failure (volume overload risk)
✦Also used to promote excretion of toxins in
overdose (“forced diuresis”)
CLASS 5 · CLINICAL
Osmotic Diuretics
Drugs: Mannitol
CLINICAL USES
✦↓ Raised intracranial pressure (cerebral edema)
✦↓ Raised intraocular pressure (acute angle-closure
glaucoma, pre-op)
✦Maintain urine flow — prevent oliguric acute renal failure
✦Promote excretion of toxins in poisoning / overdose
SIDE EFFECTS
✦Transient plasma volume expansion → pulmonary edema
risk in CHF
✦Dilutional hyponatremia, followed by dehydration
✦Headache, nausea, vomiting
✦Contraindicated in anuria and congestive heart failure
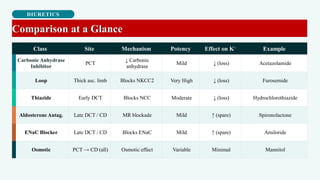
DIURETICS
Comparison at a Glance
Class Site Mechanism Potency Effect on K⁺ Example
Carbonic Anhydrase
Inhibitor
PCT
↓ Carbonic
anhydrase
Mild ↓ (loss) Acetazolamide
Loop Thick asc. limb Blocks NKCC2 Very High ↓ (loss) Furosemide
Thiazide Early DCT Blocks NCC Moderate ↓ (loss) Hydrochlorothiazide
Aldosterone Antag. Late DCT / CD MR blockade Mild ↑ (spare) Spironolactone
ENaC Blocker Late DCT / CD Blocks ENaC Mild ↑ (spare) Amiloride
Osmotic PCT → CD (all) Osmotic effect Variable Minimal Mannitol
INTRODUCTION
ANTIDIURETICS
01 Goal: Conserve Body Water
Used mainly to treat polyuric states (diabetes insipidus)
where excessive dilute urine is lost.
02 Not All Act on ADH Directly
Some are true ADH analogues; others (thiazides, NSAIDs,
amiloride) work by indirect, paradoxical mechanisms.
03 Site of Action: Collecting Duct
Nearly all classes converge on the principal cells of the
collecting duct — the site where water permeability is
regulated.
04 Choice Depends on DI Type
Central DI responds to ADH analogues; nephrogenic DI
needs indirect agents since the kidney is ADH-resistant.
Antidiuretics are agents that reduce the rate of urine formation, chiefly by enhancing water reabsorption in the renal
collecting duct — either by mimicking ADH, potentiating its action, or indirectly limiting fluid delivery to the
diluting segments.
INTRODUCTION
ADH (Vasopressin) — Normal Physiology
ADH is synthesized in the hypothalamus, stored in the posterior pituitary, and released in response to ↑ plasma
osmolarity or ↓ blood volume/pressure.
↑ Plasma osmolarity or ↓ blood volume stimulates hypothalamic
osmoreceptors & baroreceptors
ADH (vasopressin) released from the posterior pituitary into circulation
ADH binds V2 receptors on the basolateral membrane of collecting duct
principal cells
Gs protein activates adenylate cyclase → ↑ cAMP → PKA activation
Aquaporin-2 (AQP2) channels inserted into the luminal membrane
↑ Water reabsorption → Concentrated urine, Restored Plasma
Osmolarity
KEY POINT
✦This V2 → cAMP → AQP2 pathway is the
exact target that Desmopressin mimics
pharmacologically
✦ADH also acts on V1 receptors on vascular
smooth muscle → vasoconstriction (a
separate, non-renal effect)
✦Failure anywhere in this pathway (secretion or
receptor response) causes diabetes insipidus
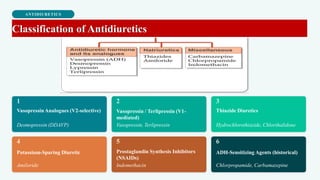
ANTIDIURETICS
Classification of Antidiuretics
VasopressinAnalogues (V2-selective)
Desmopressin (DDAVP)
Vasopressin / Terlipressin (V1-
mediated)
Vasopressin, Terlipressin
Thiazide Diuretics
Hydrochlorothiazide, Chlorthalidone
Potassium-Sparing Diuretic
Amiloride
Prostaglandin Synthesis Inhibitors
(NSAIDs)
Indomethacin
ADH-Sensitizing Agents (historical)
Chlorpropamide, Carbamazepine
CLASS 1
Vasopressin Analogues (V2-Selective)
First-line therapy for central diabetes insipidus
PROTOTYPE DRUG
✦Desmopressin (DDAVP) — synthetic analogue of ADH
✦Available as intranasal spray, oral tablet, sublingual &
IV/SC injection
✦Site of action: V2 receptors, collecting duct principal cells
✦Structural modification gives it high V2 selectivity & a
longer half-life than natural ADH
KEY FEATURES
✦Minimal V1 (vasoconstrictor) activity — far fewer pressor
effects than natural vasopressin
✦Duration of action 8-20 hours depending on route — allows
once/twice-daily dosing
✦Also used for its non-renal V2 effect: releasing stored vWF
& factor VIII from endothelium
✦Dose must be individualized — overtreatment risks water
intoxication
CLASS 1 · MECHANISM
Vasopressin Analogues — MOA
Desmopressin binds V2 receptors on the basolateral membrane of
collecting duct principal cells
Activates Gs protein → stimulates adenylate cyclase
↑ Intracellular cAMP → activates Protein Kinase A (PKA)
Aquaporin-2 (AQP2) vesicles translocate & fuse with the luminal
membrane
↑ Water permeability → water reabsorbed along the osmotic gradient
Concentrated urine & ↓ urine volume — Antidiuretic Effect
QUICK NOTES
✦Desmopressin is V2-selective — essentially no
V1 vasoconstrictor effect at therapeutic doses
✦Same V2/cAMP pathway on vascular
endothelium also triggers release of von
Willebrand factor & factor VIII
✦Requires functioning V2 receptors & AQP2 —
will NOT work in nephrogenic DI
✦Fluid intake must be restricted with dosing to
avoid dilutional hyponatremia
CLASS 1 · CLINICAL
Vasopressin Analogues
Drugs: Desmopressin (DDAVP)
CLINICAL USES
✦Central (neurogenic) diabetes insipidus — drug of choice
✦Nocturnal enuresis in children
✦Von Willebrand disease & mild Hemophilia A (releases
stored vWF/factor VIII)
✦Correction of prolonged bleeding time in uremia / pre-
operative bleeding disorders
✦Diagnostic water-deprivation / desmopressin stimulation
test
SIDE EFFECTS
✦Hyponatremia & water intoxication (can cause seizures if
severe)
✦Headache, facial flushing
✦Abdominal cramps, nausea
✦Nasal congestion / local irritation (intranasal form)
✦Rare: allergic reactions at injection site
CLASS 2 · MECHANISM
Vasopressin / Terlipressin — MOA
Prototype: Vasopressin (Pitressin), Terlipressin
Non-selective — significant V1 activity alongside V2
Vasopressin/Terlipressin bind V1 receptors on vascular smooth muscle
(splanchnic & systemic)
Activates Gq protein → phospholipase C → ↑ IP₃ & DAG
↑ Intracellular Ca²⁺ → smooth muscle contraction
Vasoconstriction — ↓ splanchnic/portal blood flow; ↑ systemic vascular
resistance
Weaker concurrent V2 activation on collecting duct gives a mild
Antidiuretic Effect
QUICK NOTES
✦Used mainly for its V1 vasoconstrictor effect
— not primarily as a urine-concentrating agent
✦Terlipressin is a long-acting prodrug of
vasopressin with more selective splanchnic
action & fewer systemic pressor effects
✦Vasopressin itself can still be used for central
DI when desmopressin is unavailable, but its
V1 effects limit use
CLASS 2 · CLINICAL
Vasopressin / Terlipressin
Drugs: Vasopressin (Pitressin), Terlipressin
CLINICAL USES
✦Septic shock — vasopressor, catecholamine-sparing agent
✦Esophageal variceal bleeding & other GI hemorrhage
(terlipressin preferred)
✦Hepatorenal syndrome (terlipressin)
✦Central diabetes insipidus (vasopressin, second-line to
desmopressin)
✦Historical use: pulseless cardiac arrest (ACLS, no longer
routinely recommended)
SIDE EFFECTS
✦Vasoconstriction-related: angina, myocardial infarction
✦Mesenteric & peripheral ischemia — risk of digital/skin
necrosis
✦Arrhythmias, hypertension
✦Hyponatremia & water intoxication (V2-mediated)
✦Local tissue injury on extravasation
CLASS 3
Thiazide Diuretics
A paradox: a diuretic used to treat polyuria
PROTOTYPE DRUGS
✦Hydrochlorothiazide (HCTZ), Chlorthalidone
✦Normally classified as diuretics — site of action: early
DCT (NCC transporter)
✦Mainstay treatment for nephrogenic diabetes insipidus
✦Often combined with amiloride for synergy & to offset K⁺
loss
KEY FEATURES
✦Effect is independent of ADH — works even when the
kidney cannot respond to ADH
✦Best combined with mild dietary Na⁺ restriction to potentiate
the antidiuretic response
✦Reduces urine volume by roughly 30-50% in nephrogenic DI
— partial, not complete, correction
✦Also useful as adjunct therapy in central DI alongside
desmopressin
CLASS 3 · MECHANISM
Thiazide Diuretics — Paradoxical MOA
Thiazide inhibits the Na⁺-Cl⁻ symporter (NCC) in the early DCT — its
usual diuretic action
Mild negative Na⁺ balance → slight extracellular volume contraction
↓ GFR & compensatory ↑ proximal tubule Na⁺ and water reabsorption
Less tubular fluid is delivered to the distal diluting segments & collecting
duct
Reduced capacity to form dilute urine, regardless of ADH activity
Net result: ↓ urine volume — A Paradoxical Antidiuretic Effect
QUICK NOTES
✦The effect does NOT depend on ADH
receptors or AQP2 — this is exactly why it
works in nephrogenic DI
✦Mechanism hinges on proximal compensation,
not on the distal NCC blockade itself
✦Low-salt diet enhances the effect by further
contracting volume and boosting proximal
reabsorption
✦Same mechanism explains why thiazides can
worsen hyponatremia in other contexts
CLASS 3 · CLINICAL
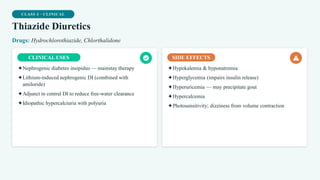
Thiazide Diuretics
Drugs: Hydrochlorothiazide, Chlorthalidone
CLINICAL USES
✦Nephrogenic diabetes insipidus — mainstay therapy
✦Lithium-induced nephrogenic DI (combined with
amiloride)
✦Adjunct in central DI to reduce free-water clearance
✦Idiopathic hypercalciuria with polyuria
SIDE EFFECTS
✦Hypokalemia & hyponatremia
✦Hyperglycemia (impairs insulin release)
✦Hyperuricemia — may precipitate gout
✦Hypercalcemia
✦Photosensitivity; dizziness from volume contraction
CLASS 4
Potassium-Sparing Diuretic — Amiloride
The specific antidote for lithium-induced nephrogenic DI
PROTOTYPE DRUG
✦Amiloride — epithelial Na⁺ channel (ENaC) blocker
✦Normally classified as a potassium-sparing diuretic
✦Site of action: principal cells of the late DCT / collecting
duct
✦Used specifically when lithium is the cause of
nephrogenic DI
KEY FEATURES
✦Lithium enters principal cells through ENaC and
accumulates, impairing AQP2 responsiveness to ADH
✦Amiloride physically blocks the same channel lithium uses
to enter the cell
✦Effect is preventive/protective rather than a direct pro-ADH
action
✦Frequently combined with a thiazide for additive antidiuretic
benefit
CLASS 4 · MECHANISM
Amiloride — MOA in Lithium-Induced NDI
Chronic lithium therapy — lithium enters collecting duct principal cells
through ENaC channels
Intracellular lithium inhibits GSK-3β signalling & downregulates
Aquaporin-2 expression
Principal cells become progressively resistant to ADH → nephrogenic
diabetes insipidus develops
Amiloride blocks the luminal ENaC channel — the same route lithium uses
to enter the cell
Reduced intracellular lithium accumulation preserves AQP2 expression &
ADH responsiveness
Partial restoration of urine-concentrating ability —
Reduced Urine Volume
QUICK NOTES
✦Unlike thiazides, amiloride's benefit here is
specific to lithium-induced NDI, not NDI in
general
✦Also spares K⁺ — useful when combined with
a K⁺-wasting thiazide
✦Does not reverse existing structural tubular
damage from long-standing lithium use
✦Lithium levels & renal function should still be
monitored regularly
CLASS 4 · CLINICAL
Potassium-Sparing Diuretic (Amiloride)
Drugs: Amiloride
CLINICAL USES
✦Lithium-induced nephrogenic diabetes insipidus — agent
of choice
✦Combined with thiazides in other forms of nephrogenic DI
✦Offsets hypokalemia caused by concurrent thiazide/loop
diuretic therapy
✦Adjunct in Liddle syndrome (unrelated indication, same
drug)
SIDE EFFECTS
✦Hyperkalemia — especially with renal impairment or
ACEI/ARB co-therapy
✦Nausea, vomiting, leg cramps
✦Should be avoided in significant renal insufficiency
✦Requires periodic monitoring of serum K⁺ and lithium
levels
CLASS 5
Prostaglandin Synthesis Inhibitors (NSAIDs)
An adjunct that works by removing a natural brake on ADH
PROTOTYPE DRUG
✦Indomethacin — potent, non-selective COX inhibitor
✦Other NSAIDs (ibuprofen, aspirin) share the mechanism
but are less potent antidiuretics
✦Site of action: renal cyclooxygenase (COX-1/COX-2) in
the medulla & collecting duct
✦Always used as adjunct therapy, never alone
KEY FEATURES
✦Most useful in nephrogenic DI, especially combined with a
thiazide ± amiloride
✦Also reduces urine volume in partial central DI by
potentiating residual ADH
✦Onset within hours; effect is dose-dependent and reversible
on stopping the drug
✦Renal & GI toxicity limit long-term use — requires careful
risk-benefit assessment
CLASS 5 · MECHANISM
NSAIDs (Indomethacin) — MOA
Indomethacin inhibits cyclooxygenase (COX) enzyme in the renal medulla
& collecting duct
↓ Synthesis of renal prostaglandins, chiefly PGE₂
PGE₂ normally antagonizes ADH by inhibiting adenylate cyclase in
principal cells
With PGE₂ synthesis reduced, this inhibitory brake on ADH signalling is
removed
Residual ADH action is potentiated → ↑ cAMP → ↑ AQP2 insertion
↑ Water reabsorption → Reduced Urine Volume
QUICK NOTES
✦Effect requires SOME residual ADH activity
or a partially responsive kidney — it
potentiates, it doesn't replace
✦Works well as an add-on in nephrogenic DI
even though the kidney is ADH-resistant,
because prostaglandins act independently of
receptor status
✦Also reduces renal blood flow & GFR — the
same prostaglandin-dependent pathway
explains its nephrotoxic potential
CLASS 5 · CLINICAL
Prostaglandin Synthesis Inhibitors
Drugs: Indomethacin (prototype), Ibuprofen, Aspirin
CLINICAL USES
✦Adjunct in nephrogenic diabetes insipidus (with thiazide ±
amiloride)
✦Partial central diabetes insipidus — potentiates residual
endogenous ADH
✦Reduces polyuria refractory to thiazide therapy alone
✦Used short-term given its toxicity profile
SIDE EFFECTS
✦GI ulceration & bleeding
✦Nephrotoxicity — interstitial nephritis, papillary necrosis,
acute kidney injury
✦Fluid retention & worsening hypertension
✦Increased cardiovascular risk with long-term use
✦Caution: can itself precipitate renal impairment, worsening
the underlying problem
CLASS 6
ADH-Sensitizing Agents (Historical)
Largely of historical interest — superseded by desmopressin
PROTOTYPE DRUGS
✦Chlorpropamide — a first-generation sulfonylurea (also an
oral hypoglycemic)
✦Carbamazepine — an anticonvulsant with an incidental
antidiuretic effect
✦Clofibrate — a lipid-lowering agent, occasionally used
similarly
✦None are true ADH analogues — they only work if some
endogenous ADH remains
KEY FEATURES
✦Only effective in partial (not complete) central DI
✦Chlorpropamide's antidiuretic effect was discovered
incidentally in diabetic patients
✦Risk of significant hypoglycemia (chlorpropamide) limits
practical use
✦Almost entirely replaced by desmopressin, which is safer
and more predictable
CLASS 6 · MECHANISM
ADH-Sensitizing Agents — MOA
Chlorpropamide/Carbamazepine act on collecting duct principal cells that
still receive some endogenous ADH
They sensitize the V2 receptor-adenylate cyclase coupling to circulating
ADH
A greater rise in cAMP is generated per unit of ADH present
Enhanced PKA activation → increased Aquaporin-2 insertion into the
luminal membrane
Increased water permeability of the collecting duct for the same ADH level
↑ Urine Volume — but only if some residual ADH secretion exists
QUICK NOTES
✦Useless in complete central DI (no ADH to
potentiate) and in nephrogenic DI
(receptor/AQP2 defect)
✦The exact molecular basis of chlorpropamide's
receptor-sensitizing effect is incompletely
understood
✦Chlorpropamide can itself cause SIADH-like
water retention & dilutional hyponatremia as a
side effect
✦Now largely of historical / academic interest
only
CLASS 6 · CLINICAL
ADH-Sensitizing Agents
Drugs: Chlorpropamide, Carbamazepine, Clofibrate
CLINICAL USES
✦Partial central diabetes insipidus (historical alternative to
desmopressin)
✦Occasionally used when desmopressin is unavailable or not
tolerated
✦Chlorpropamide also treats type 2 diabetes mellitus (dual-
purpose historically)
SIDE EFFECTS
✦Hypoglycemia (chlorpropamide — sulfonylurea action)
✦Hyponatremia / SIADH-like water retention
✦Hepatotoxicity, blood dyscrasias (chlorpropamide)
✦Carbamazepine: sedation, ataxia, hepatic enzyme induction,
blood dyscrasias
✦Largely replaced due to this unfavourable side-effect
profile
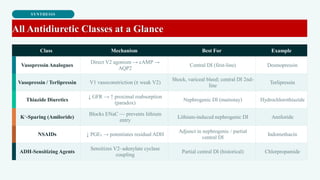
SYNTHESIS
All Antidiuretic Classes at a Glance
Class Mechanism Best For Example
VasopressinAnalogues
Direct V2 agonism → cAMP →
AQP2
Central DI (first-line) Desmopressin
Vasopressin / Terlipressin V1 vasoconstriction (± weak V2)
Shock, variceal bleed; central DI 2nd-
line
Terlipressin
Thiazide Diuretics
↓ GFR → ↑ proximal reabsorption
(paradox)
Nephrogenic DI (mainstay) Hydrochlorothiazide
K⁺-Sparing (Amiloride)
Blocks ENaC — prevents lithium
entry
Lithium-induced nephrogenic DI Amiloride
NSAIDs ↓ PGE₂ → potentiates residual ADH
Adjunct in nephrogenic / partial
central DI
Indomethacin
ADH-Sensitizing Agents
Sensitizes V2–adenylate cyclase
coupling
Partial central DI (historical) Chlorpropamide
SYNTHESIS
Diuretics vs Antidiuretics
DIURETICS ANTIDIURETICS
✦Goal: ↑ urine volume, ↓ body fluid & Na⁺
✦Block Na⁺ / water reabsorption at various nephron sites
✦Used in edema, hypertension, heart failure, raised ICP/IOP
✦Risk: dehydration, electrolyte imbalance (hypo/hyperkalemia)
✦Goal: ↓ urine volume, conserve body water
✦Enhance water reabsorption via ADH (V2) / AQP2 pathway
✦Used in diabetes insipidus, enuresis, bleeding disorders
(vWD)
✦Risk: water intoxication, hyponatremia
Comprehensive Overview of Diuretics and Antidiuretics