Comprehensive Overview of Diabetes Mellitus and Thyroid Disorders: Pathophysiology, Diagnosis, and Treatment
1.
Diabetes mellitus andThyroid
Ms. Sakshi Bajaj
Associate Professor ( Pharmacology)
Global Research Institute Of Pharmacy
2.
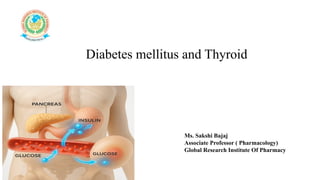
• Diabetes mellitus(DM) also known as simply diabetes, is a group of metabolic diseases in which there are high blood sugar
levels over a prolonged period .
• Symptoms
• frequent urination, increased thirst, and increased hunger. Untreated, diabetes can cause many complications.
• Acute complications include diabetic ketoacidosis and nonketotic hyperosmolar coma.
• Types of DM: There are three main types of diabetes mellitus:
• Type 1 DM results from the body's failure to produce enough insulin. This form was previously referred to as "insulin-
dependent diabetes mellitus" (IDDM) or "juvenile diabetes". The cause is unknown.
• Type 2 DM begins with insulin resistance, a condition in which cells fail to respond to insulin properly. As the disease
progresses a lack of insulin may also develop. This form was previously referred to as "non insulin-dependent diabetes
mellitus" (NIDDM) or "adult-onset diabetes".
• The primary cause is excessive body weight and not enough exercise. Gestational diabetes, is the third main form and occurs
when pregnant women without a previous history of diabetes develop a high blood glucose level. Prevention and treatment
involves a healthy diet, physical exercise, not using tobacco, and being a normal body weight. Blood pressure control and
proper foot care are also important for people with the disease.
• Type 1 diabetes must be managed with insulin injections. Type 2 diabetes may be treated with medications with or without
insulin. Insulin and some oral medications can cause low blood sugar.
Diabetes mellitus
3.
Risk factors
The developmentof type 2 diabetes has been linked to several risk factors.
Unmodifiable risk factors: include advancing population age, family history, and diabetes genetic variables in
some ethnic groups. The most common risk factors for the rising diabetes epidemiology, are variables linked to poor
food, inactivity, and smoking, Sedentary life style ,which typically result in being overweight, dyslipidaemia, high
blood pressure, and impaired glucose tolerance.
Diabetes development is influenced by environmental factors, including low socioeconomic position, physical
living conditions, stress levels, and exposure to mercury and arsenic .
Diabetes mellitus is diagnosed by measuring blood glucose levels or HbA1c (glycated hemoglobin). The commonly
used diagnostic tests are:
Fasting Plasma Glucose (FPG): Diabetes is diagnosed if the fasting blood glucose level is ≥126 mg/dL (7.0 mmol/L).
Oral Glucose Tolerance Test (OGTT): Diabetes is diagnosed if the 2-hour plasma glucose level is ≥200 mg/dL (11.1
mmol/L) after consuming a glucose solution.
HbA1c Test: An HbA1c value of ≥6.5% indicates diabetes. This test reflects the average blood glucose level over the
previous 2–3 months.
Random Plasma Glucose (RPG): A random blood glucose level ≥200 mg/dL (11.1 mmol/L) along with typical
symptoms of hyperglycemia (such as excessive thirst, frequent urination, and unexplained weight loss) is also diagnostic
of diabetes.
Diagnosis
4.
Complication of Diabetesmellitus
Pathophysiology of Diabetes Mellitus
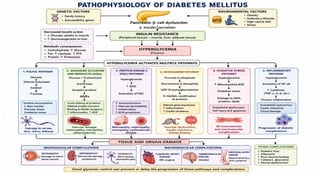
• Diabetes mellitus is a chronic metabolic disorder characterized by persistent hyperglycemia (high blood glucose levels)
resulting from impaired insulin secretion, insulin resistance, or both. Insulin, a hormone produced by the β-cells of the
pancreas, is essential for maintaining normal blood glucose levels by promoting glucose uptake into cells and regulating
carbohydrate, fat, and protein metabolism.
Normal Glucose Regulation
After a meal, blood glucose levels rise, stimulating pancreatic β-cells to release insulin. Insulin facilitates the uptake of glucose
into muscle and adipose tissues, promotes glycogen synthesis in the liver, and suppresses glucose production by the liver, thereby
maintaining normal blood glucose levels.
Pathophysiology of Type 1 Diabetes Mellitus
Type 1 diabetes mellitus is caused by autoimmune destruction of pancreatic β-cells, leading to an absolute deficiency of
insulin. The lack of insulin prevents glucose from entering cells, resulting in elevated blood glucose levels. Since cells cannot
utilize glucose for energy, the body breaks down fats and proteins, producing ketone bodies that may lead to diabetic
ketoacidosis (DKA) if untreated.
Pathophysiology of Type 2 Diabetes Mellitus
Type 2 diabetes mellitus develops due to insulin resistance and progressive β-cell dysfunction. Initially, body tissues such as
skeletal muscle, liver, and adipose tissue become less responsive to insulin. To compensate, the pancreas secretes more insulin
(hyperinsulinemia). Over time, β-cells become exhausted, insulin secretion decreases, and persistent hyperglycemia develops.
Metabolic Changes in Diabetes Mellitus
• Carbohydrate metabolism: Reduced glucose uptake by peripheral tissues and increased hepatic glucose production cause
hyperglycemia.
• Fat metabolism: Increased breakdown of fats (lipolysis) raises free fatty acid levels, leading to ketone body formation,
especially in type 1 diabetes.
• Protein metabolism: Increased protein breakdown results in muscle wasting and weight loss.
• .
5.
Development of DiabeticComplications
• Chronic hyperglycemia causes several biochemical changes that damage blood vessels
and nerves:
• Increased formation of Advanced Glycation End Products (AGEs).
• Activation of the polyol pathway, causing sorbitol accumulation.
• Increased oxidative stress due to excessive production of reactive oxygen species (ROS).
• Activation of protein kinase C (PKC) and inflammatory pathways.
• These changes lead to endothelial dysfunction, inflammation, and tissue damage,
resulting in:
• Microvascular complications: Diabetic retinopathy, nephropathy, and neuropathy.
• Macrovascular complications: Coronary artery disease, stroke, and peripheral arterial
disease
6.
Major Pathways Involvedin Diabetic Complications
1. Advanced Glycation End Products (AGEs) Pathway
Persistent high blood glucose causes glucose to bind non-enzymatically to proteins, lipids, and DNA, forming Advanced Glycation
End Products (AGEs). AGEs make blood vessels stiff, increase inflammation and oxidative stress, and damage the eyes, kidneys,
nerves, and heart.
2. Polyol Pathway
Excess glucose is converted into sorbitol by the enzyme aldose reductase. Sorbitol accumulates inside cells, causing osmotic stress
and reducing antioxidant levels, which leads to nerve, retinal, and kidney damage.
3. Protein Kinase C (PKC) Pathway
High glucose increases the production of diacylglycerol (DAG), which activates Protein Kinase C (PKC). PKC causes abnormal
blood vessel function, increased vascular permeability, inflammation, and reduced blood flow, contributing to diabetic complications.
4. Hexosamine Pathway
When glucose levels are high, excess glucose enters the hexosamine pathway, leading to abnormal modification of proteins and
altered gene expression. This increases inflammation and fibrosis, contributing to vascular and kidney damage.
5. Oxidative Stress Pathway
Hyperglycemia increases the production of reactive oxygen species (ROS). Excess ROS damages cellular proteins, lipids, and DNA,
resulting in endothelial dysfunction and accelerating diabetic complications.
6. Inflammatory Pathway
• Chronic hyperglycemia activates inflammatory mediators such as TNF-α, IL-6, and NF-κB. Persistent inflammation damages blood
vessels and tissues, worsening insulin resistance and promoting diabetic complications.
Thyroid Gland
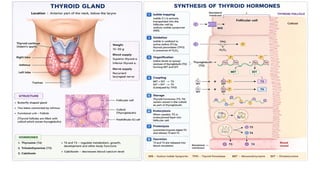
Synthesis ofThyroid Hormones
Iodide uptake by thyroid cells.
Oxidation of iodide.
Iodination of tyrosine residues.
Formation of T3 and T4.
Storage in thyroglobulin.
Release into circulation.
Butterfly-shaped endocrine gland located in the neck.
Produces:
Thyroxine (T4)
Triiodothyronine (T3)
Calcitonin
Regulated by the hypothalamic–pituitary–thyroid (HPT) axis
10.
Functions of ThyroidHormones
• Regulate basal metabolic rate (BMR).
• Increase oxygen consumption.
• Promote growth and development.
• Regulate carbohydrate, fat, and protein metabolism.
• Maintain cardiovascular and nervous system functions.
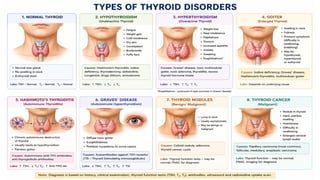
Hypothyroidism
Definition
Hypothyroidism is a disorder in which the thyroid gland produces insufficient amounts of T3 and T4 hormones, leading to a
reduction in the body's metabolic rate.
Causes
Hashimoto's thyroiditis (most common)
Iodine deficiency
Thyroid surgery (thyroidectomy)
Radioactive iodine therapy
Congenital hypothyroidism
Drugs (e.g., lithium, amiodarone)
Risk Factors
Female gender
Age >60 years
Autoimmune diseases
Family history
Previous thyroid surgery
12.
Pathophysiology of Hypothyroidism
•Thyroid gland damage or iodine deficiency
↓
Reduced T3 and T4 secretion
↓
Loss of negative feedback
↓
Increased TSH secretion
↓
Reduced basal metabolic rate
↓
Clinical manifestations
Effects
• Decreased energy production
• Slowed metabolism
• Reduced heart rate
• Cold intolerance
• Weight gain
• Dry skin and hair loss
• Constipation
• Mental slowing
Hyperthyroidism
Definition
Hyperthyroidism is adisorder in which the thyroid gland produces excessive amounts of T3 and T4
hormones, resulting in an increased metabolic rate.
Causes
• Graves' disease (most common)
• Toxic multinodular goiter
• Toxic adenoma
• Thyroiditis
Excess thyroid hormone intake
• Risk Factors
• Female gender
• Family history
• Autoimmune disorders
• Smoking (Graves' disease)
15.
Pathophysiology of Hyperthyroidism
•Autoimmune stimulation (Graves' disease) or thyroid nodule
↓
Excess secretion of T3 and T4
↓
Suppression of TSH
↓
Increased cellular metabolism
↓
Excess sympathetic activity
↓
Clinical manifestations
• Effects
• Increased basal metabolic rate
• Increased heart rate
• Weight loss
• Heat intolerance
• Tremors
• Nervousness
• Increased sweating
• Muscle weakness
16.
Clinical Features, Diagnosis& Treatment
Symptoms
• Weight loss
• Increased appetite
• Heat intolerance
• Tachycardia
• Tremors
• Anxiety
• Excessive sweating
• Exophthalmos (Graves' disease)
Diagnosis
• ↓ TSH
• ↑ Free T3 and T4
• Thyroid receptor antibodies (TRAb)
• Radioactive iodine uptake scan
• Thyroid ultrasound
Treatment
• Methimazole (first-line in most patients)
• Propylthiouracil (PTU) (preferred in the first trimester of pregnancy and thyroid storm)
• Propranolol for symptom control
• Radioactive iodine therapy
17.
• Goiter
• Definition
•Goiter is an abnormal enlargement of the thyroid gland.
• Causes
• Iodine deficiency
• Graves' disease
• Hashimoto's thyroiditis
• Thyroid nodules
• Symptoms
• Neck swelling
• Difficulty swallowing
• Hoarseness
• Breathing difficulty (large goiter)
• Treatment
• Depends on the cause:
• Iodine supplementation
• Levothyroxine
• Antithyroid drugs
• Surgery
19.
Pregnancy as aRisk Factor for Thyroid Disorders
• Increased thyroid hormone requirement during pregnancy
• Higher iodine requirement for hormone synthesis
• hCG stimulates the thyroid, causing temporary hyperthyroidism in some women
• Immune changes increase the risk of postpartum thyroiditis
• Untreated thyroid disorders may affect fetal growth and brain development
Female gender (5–8 times more common than in males)
Family history of thyroid disease
Autoimmune diseases (e.g., Type 1 diabetes, rheumatoid arthritis)
Iodine deficiency or excess
Increasing age (especially >60 years)
Radiation exposure to the head and neck
Pregnancy and postpartum period
Certain medications (e.g., lithium, amiodarone)
Smoking (particularly associated with Graves' disease)
Previous thyroid surgery or radioactive iodine therapy
Risk factors
20.
Effect of Lifestyleon Thyroid Health
• Balanced iodine intake supports normal thyroid hormone production.
• Healthy diet rich in selenium, zinc, and iron helps maintain thyroid function.
• Regular exercise improves metabolism and helps maintain a healthy body weight.
• Stress management may reduce the risk of thyroid dysfunction.
• Adequate sleep supports normal hormone regulation.
• Avoid smoking, as it increases the risk of Graves' disease and thyroid eye disease.
• Limit excessive alcohol consumption to support overall endocrine health.
• Regular health check-ups help in the early detection and management of thyroid
disorders.