Comprehensive Overview of Cryptorchidism: Causes, Types, Diagnosis, and Treatment
Detailed presentation on cryptorchidism covering its definition, etiology, types, clinical features, diagnostic methods, and treatment options including surgery and hormonal therapy.
Comprehensive Overview of Cryptorchidism: Causes, Types, Diagnosis, and Treatment
1.
Cryptorchidism
Pathology
Bsc nursing 4thsemester
By Govinda Gajbhiye
Bsc Nursing MSc Nursing M.A clinical psychologist
Assistant Professor
Department Medical Surgical Nursing
4.
Meaning of cryptorchidism
Cryptorchidismmeans "hidden testicle" from the
Greek words kryptos (hidden) and orchis (testicle). It
refers to an undescended testicle, where one or both
testicles fail to move down into the scrotum.
5.
Definition:-
Cryptorchidism (Undescended Testis)is a congenital
condition in which one or both testes fail to descend into
the scrotum before birth. The testis may remain in the
abdomen, inguinal canal, or just above the scrotum.
6.
Definition
Cryptorchidism is acongenital anomaly in which one or
both testes fail to descend into the scrotum by birth. The
undescended testis may be located in the abdomen,
inguinal canal, or just outside the external inguinal ring.
7.
Incidence
Cryptorchidism (undescended testicles)is a common
condition, affecting about 3% of full-term and up to 30%
of premature newborn boys.
However, many resolve on their own, leaving a true long-
term rate of about 1% in infants past three to six months
of age.
8.
Etiology and riskFactors
The exact cause of cryptorchidism is often unknown (idiopathic).
1. Prematurity
Testicular descent normally occurs during the last 2–3 months of pregnancy (third trimester).
Babies born before 37 weeks of gestation may not complete this process.
Therefore, the testes remain in the abdomen or inguinal canal.
Prematurity is one of the strongest risk factors for cryptorchidism.
2. Genetic Abnormalities
Certain gene mutations can interfere with normal testicular development and descent.
A positive family history increases the likelihood of the condition.
Cryptorchidism may occur with chromosomal or congenital disorders such as Down syndrome,
Prader–Willi syndrome, and disorders of sex development (DSD).
9.
Etiology
3. Hormonal Deficiency(Testosterone or INSL3)
Testosterone is essential for the second phase of testicular descent through the inguinal canal.
Insulin-like peptide 3 (INSL3), produced by fetal Leydig cells, is required for the first phase of
descent.
Deficiency or reduced action of these hormones prevents normal migration of the testes into
the scrotum.
4. Abnormal Gubernaculum Development
The gubernaculum is a fibrous cord that guides the testes from the abdomen into the scrotum.
If it is absent, short, poorly developed, or abnormally attached, the testes cannot descend
properly.
This results in an undescended testis.
10.
Etiology
5. Maternal Smokingor Alcohol Exposure
Smoking during pregnancy exposes the fetus to harmful chemicals such as nicotine, which can impair fetal
hormone production.
Alcohol consumption during pregnancy may interfere with fetal growth and endocrine function.
Both factors increase the risk of abnormal testicular descent.
6. Low Birth Weight
Infants weighing less than 2.5 kg at birth have a higher incidence of cryptorchidism.
Low birth weight is often associated with incomplete fetal growth and delayed maturation of the
reproductive system.
7. Family History
Boys with a father or brother who had cryptorchidism have an increased risk.
This suggests an inherited genetic predisposition affecting testicular development or hormonal regulation.
12.
Type of Cryptorchidism
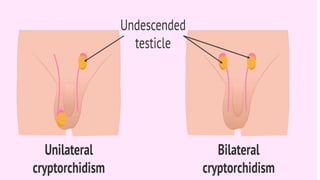
1.Unilateral Cryptorchidism
Only one testis fails to descend into the scrotum.
It is the most common type (about 80% of cases).
Usually affects the right testis more often than the left.
Fertility is usually preserved if treated early.
2. Bilateral Cryptorchidism
Both testes fail to descend into the scrotum.
Less common (about 20% of cases).
Associated with a higher risk of infertility and hormonal problems if
untreated.
Requires prompt evaluation and treatment.
13.
Type of Cryptorchidism
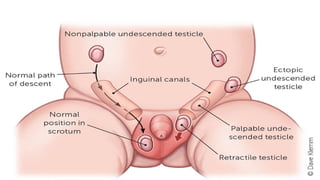
3.Palpable Cryptorchidism
The undescended testis can be felt during physical examination.
Usually located in the inguinal canal or just above the scrotum.
Treated by orchiopexy.
4. Non-Palpable Cryptorchidism
The testis cannot be felt on physical examination.
It may be:
Intra-abdominal (inside the abdomen)
Absent (vanishing testis syndrome)
Atrophic (underdeveloped)
Usually evaluated with laparoscopy, which can also be used for treatment.
14.
Type of Cryptorchidism
5.Ectopic Testis
The testis has descended outside its normal pathway.
Common ectopic sites include:
Superficial inguinal pouch
Perineum
Femoral region
Penile region
Requires surgical correction.
6. Retractile Testis (Not True Cryptorchidism)
The testis moves between the scrotum and groin because of an overactive
cremasteric reflex.
It can be brought into the scrotum and usually stays there temporarily.
Often resolves spontaneously by puberty.
Observation is usually sufficient unless it becomes an ascending testis.
15.
Clinical manifestations
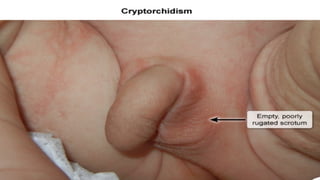
● Emptyor underdeveloped scrotum
● One or both testes absent from the scrotum
● Asymmetrical scrotum
● Usually painless
● Inguinal swelling may be present
● Infertility in adulthood if untreated
16.
Diagnostic Evaluation
● Physicalexamination (most important)
● Ultrasonography
● MRI (selected cases)
● Diagnostic laparoscopy (gold standard for non-
palpable testes)
● Hormonal evaluation when bilateral
● Genetic studies if associated abnormalities are present
17.
Treatment of Cryptorchidism
●Observation (Watchful Waiting)
● Hormonal Therapy
● Human Chorionic Gonadotropin (hCG)
● Orchiopexy (Surgical Treatment)
● Laparoscopic Surgery
● Orchidectomy (Removal of Atrophic Testis)
18.
Treatment
1. Observation
Recommended forinfants younger than 6 months, as
many undescended testes descend spontaneously.
If the testis remains undescended after 6 months,
treatment is indicated.
19.
Hormonal Therapy
Hormonal therapyis less effective than surgery
and is used only in selected cases.
1.Human Chorionic Gonadotropin (hCG)
Men and Boys: Treats hypogonadotropic
hypogonadism (low testosterone/infertility)
and prepubertal cryptorchidism (undescended
testes)
Routes: Given via subcutaneous or
intramuscular injection using single-use
disposable needles and syringes.
Dosing:single trigger doses of 5,000 to 10,000
20.
3. Surgical Treatment– Orchiopexy
(Treatment of Choice)
Orchidopexy (or orchiopexy) is a surgical operation that moves an undescended testicle
into the scrotum and fixes it there. It is commonly done for infant boys between 6 months
and 2 years old to protect future fertility and health.
The Surgical Steps
Anesthesia: General anesthesia is given so the patient sleeps and feels no pain.
Incision: The surgeon makes a small cut in the groin area and a second small cut in the
scrotum.
Mobilization: The testicle is found and gently freed from tight surrounding tissues and
any hernia sac.
Fixation: The testicle is pulled down into a special pouch inside the scrotum and stitched
in place so it cannot move back up.
Closure: The cuts are closed with dissolvable stitches or surgical glue. The operation
usually takes 30 to 60 minutes
21.
Laparoscopic Surgery forCryptorchidism
Laparoscopic surgery is the preferred method for the diagnosis and treatment of non-palpable intra-
abdominal undescended testes (cryptorchidism). It allows the surgeon to directly visualize the abdominal
cavity, accurately locate the testis, and perform the appropriate surgical procedure through small incisions.
Indications
Non-palpable undescended testis
Procedure
● The child is placed under general anesthesia.
● A small incision is made near the umbilicus (navel).
● A laparoscope (a thin tube with a camera and light source) is inserted into the abdomen.
● Carbon dioxide (CO₂) gas is introduced to inflate the abdomen, providing a clear view of the internal
organs.
● The surgeon identifies the location, size, and blood supply of the testis.
● If the testis is healthy and can be brought down without tension, laparoscopic orchiopexy is
performed by mobilizing the testis and fixing it in the scrotum.
● If the testis is high in the abdomen with short blood vessels, a staged Fowler–Stephens orchiopexy
may be performed.
● If the testis is severely atrophic or non-viable, orchiectomy (removal of the testis) may be indicated.
22.
Orchiectomy
● Removal ofthe testis is indicated when:
● The testis is atrophic or non-functional.
● Older adolescents or adults have an intra-
abdominal testis with a high risk of malignancy.
● A nonviable testis is found during surgery.