Comprehensive Overview of Congestive Heart Failure and Pharmacological Management Strategies
Detailed insights into CHF pathophysiology, classification, clinical features, and evidence-based drug therapies including diuretics, RAAS blockers, beta blockers, MRAs, ARNI, SGLT2 inhibitors, and cardiac glycosides.
Comprehensive Overview of Congestive Heart Failure and Pharmacological Management Strategies
1.
Congestive Heart Failure
andthe Drugs Used in Its Management
Mr. SATENDRA PRADHAN
Assistant Professor
Department of Pharmacology
COP, SVITS, Bilaspur
Ms. MANISHA SAHU
Assistant Professor
Department of Pharmacology
SCCP, Rajnandgaon
2.
OVERVIEW
What Is CongestiveHeart Failure?
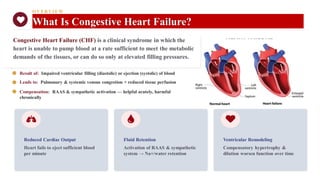
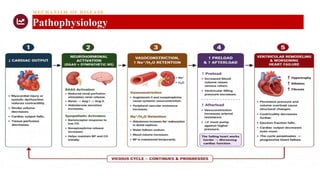
Result of: Impaired ventricular filling (diastolic) or ejection (systolic) of blood
Leads to: Pulmonary & systemic venous congestion + reduced tissue perfusion
Compensation: RAAS & sympathetic activation — helpful acutely, harmful
chronically
Congestive Heart Failure (CHF) is a clinical syndrome in which the
heart is unable to pump blood at a rate sufficient to meet the metabolic
demands of the tissues, or can do so only at elevated filling pressures.
Reduced Cardiac Output
Heart fails to eject sufficient blood
per minute
Fluid Retention
Activation of RAAS & sympathetic
system → Na+/water retention
Ventricular Remodeling
Compensatory hypertrophy &
dilation worsen function over time
CLASS 1 ·DIURETICS
Diuretics — Mechanism of Action
Loop & thiazide diuretics reduce preload by promoting salt & water excretion
Block Na⁺-K⁺-2Cl⁻
symporter
(thick ascending limb)
[Loop] or Na⁺-Cl⁻
cotransporter (DCT)
[Thiazide]
→
↓ Reabsorption of
Na⁺, Cl⁻, K⁺ →
↑ Osmotic gradient
→ ↑ Water excretion
(diuresis)
→
↓ Plasma volume
→ ↓ Venous return
(preload)
→
Relief of pulmonary
& systemic congestion
Net effect: reduced circulating volume lowers ventricular filling pressures, relieving dyspnea and peripheral edema — the fastest-acting
symptomatic therapy in CHF.
10.
CLASS 1 ·DIURETICS
Diuretics — Uses & Side Effects
Furosemide, Bumetanide (Loop) · Hydrochlorothiazide, Metolazone (Thiazide)
Therapeutic Uses
First-line for volume overload / congestion
Rapid relief of pulmonary edema (loop, IV in acute HF)
Reduce peripheral & pulmonary edema
Improve exercise tolerance by decreasing preload
Adjunct to RAAS/BB therapy — no proven mortality benefit
alone
Side Effects
Hypokalemia, hypomagnesemia
Hypotension & pre-renal azotemia
Ototoxicity (high-dose loop diuretics)
Hyperuricemia → gout flares
Metabolic alkalosis; hyperglycemia (thiazides)
11.
CLASS 2 ·RAAS BLOCKADE
ACE Inhibitors — Mechanism of Action
Interrupt the renin-angiotensin-aldosterone system at the conversion step
Inhibit ACE
(Angiotensin-
Converting
Enzyme)
→
↓ Angiotensin II
formation +
↑ Bradykinin
→
↓ Vasoconstriction
↓ Aldosterone
secretion
→
↓ Afterload
↓ Preload
(Na⁺/H₂O retention ↓)
→
↓ Cardiac remodeling
↑ Survival
By lowering angiotensin II, ACE inhibitors reduce both afterload (vasodilation) and preload (less aldosterone-driven fluid
retention), and blunt the maladaptive remodeling that drives HF progression — first-line, mortality-reducing therapy in
HFrEF.
12.
CLASS 2 ·RAAS BLOCKADE
ACE Inhibitors & ARBs — Uses & Side Effects
Enalapril, Lisinopril, Ramipril (ACEI) · Losartan, Valsartan, Candesartan (ARB, if ACEI-intolerant)
Therapeutic Uses
First-line in all stages of HFrEF (NYHA I–IV)
Reduce mortality & hospitalization
Slow / reverse ventricular remodeling
Also used in hypertension & diabetic nephropathy
ARBs substituted when ACEI causes cough/angioedema
Side Effects
Dry, persistent cough (bradykinin-mediated)
Hyperkalemia
Angioedema (rare but serious)
First-dose hypotension
Acute kidney injury, especially with renal artery stenosis
13.
CLASS 3 ·NEUROHORM ONA L BLOCKADE
Beta Blockers — Mechanism of Action
Counteract chronic sympathetic overactivation in CHF
Competitively block
β1-adrenergic
receptors in
myocardium
→
↓ Heart rate &
↓ Contractility
(acute)
→
↓ Renin release
↓ Myocardial O₂
demand
→
↓ Chronic sympathetic
toxicity on myocytes →
Reverse remodeling
↑ EF over months
Started at low dose in stable, euvolemic patients and up-titrated slowly — initial negative inotropy is offset by long-term
reduction in catecholamine-driven myocardial damage, improving survival.
14.
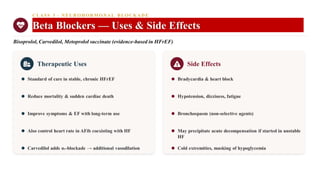
CLASS 3 ·NEUROHORM ONA L BLOCKADE
Beta Blockers — Uses & Side Effects
Bisoprolol, Carvedilol, Metoprolol succinate (evidence-based in HFrEF)
Therapeutic Uses
Standard of care in stable, chronic HFrEF
Reduce mortality & sudden cardiac death
Improve symptoms & EF with long-term use
Also control heart rate in AFib coexisting with HF
Carvedilol adds α₁-blockade → additional vasodilation
Side Effects
Bradycardia & heart block
Hypotension, dizziness, fatigue
Bronchospasm (non-selective agents)
May precipitate acute decompensation if started in unstable
HF
Cold extremities, masking of hypoglycemia
15.
CLASS 4 ·ALDOSTERONE ANTAGONIST S
Mineralocorticoid Receptor Antagonists — MOA
Block the end-organ effects of aldosterone directly
Competitively block
aldosterone receptors
in distal nephron
→
↓ Na⁺/H₂O
reabsorption
↑ K⁺ retention
→
Mild diuretic +
K⁺-sparing effect →
↓ Myocardial &
vascular fibrosis
(direct tissue effect)
→
↓ Remodeling
↑ Survival
Beyond their weak diuretic action, MRAs block aldosterone's direct pro-fibrotic effect on the heart and vasculature —
this tissue-level action is the main reason they reduce mortality in HFrEF.
16.
CLASS 4 ·ALDOSTERONE ANTAGONIST S
MRAs — Uses & Side Effects
Spironolactone, Eplerenone
Therapeutic Uses
Added to ACEI/ARB + BB in NYHA II–IV HFrEF
Reduce mortality & hospitalization (RALES, EMPHASIS-
HF)
Used post-MI with LV dysfunction
Also used for resistant hypertension
Eplerenone preferred if antiandrogenic effects unwanted
Side Effects
Hyperkalemia (monitor K⁺ & renal function)
Gynecomastia & menstrual irregularities (spironolactone)
Renal impairment, especially with ACEI/ARB combo
Rare: metabolic acidosis
Requires regular electrolyte monitoring
17.
CLASS 5 ·ARNI (Angi ote ns i n Receptor –N epril ys i n Inhibi tor)
Sacubitril/Valsartan — Mechanism of Action
Dual action: neprilysin inhibition + angiotensin receptor blockade
Sacubitril inhibits
neprilysin (degrades
natriuretic peptides)
→
↑ ANP, BNP levels
→ natriuresis &
vasodilation
→
Valsartan blocks
AT1 receptors
(as in ARBs)
→
Combined ↓ preload,
↓ afterload,
↓ fibrosis
→
Superior mortality
reduction vs ACEI
(PARADIGM-HF)
ARNI combines the beneficial natriuretic-peptide pathway (protective, but degraded by neprilysin) with angiotensin
blockade — now preferred over ACE inhibitors in eligible HFrEF patients.
18.
CLASS 5 ·ARNI
ARNI — Uses & Side Effects
Sacubitril + Valsartan (fixed-dose combination)
Therapeutic Uses
Replaces ACEI/ARB in symptomatic HFrEF
Reduces cardiovascular death & HF hospitalization
Recommended by current guidelines as preferred RAAS
agent
Improves symptoms and functional class
Not started same-day as ACEI — 36-hour washout
required
Side Effects
Hypotension (more common than ACEI)
Hyperkalemia
Angioedema (lower risk than ACEI, still possible)
Renal function decline
Contraindicated with concurrent ACEI use
19.
CLASS 6 ·NEWEST PILLAR OF GDM T
SGLT2 Inhibitors — Mechanism, Uses & Side Effects
Inhibit SGLT2
in proximal
renal tubule
→
↓ Glucose &
Na⁺ reabsorption →
Osmotic diuresis
+ natriuresis →
↓ Preload &
improved cardiac
metabolism
→
↓ HF hospitalization
(regardless of
diabetes status)
Uses — Dapagliflozin, Empagliflozin
Approved for HFrEF AND HFpEF, with or without diabetes
Reduce HF hospitalization & CV death
Added on top of standard 4-pillar GDMT
Additional renal-protective benefit
Side Effects
Genital mycotic infections (esp. in women)
Urinary tract infections
Volume depletion / hypotension
Rare: euglycemic diabetic ketoacidosis
20.
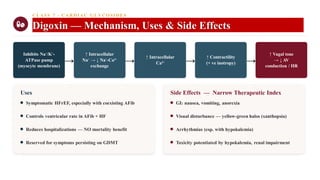
CLASS 7 ·CARDIAC GLYCOSIDES
Digoxin — Mechanism, Uses & Side Effects
Inhibits Na⁺/K⁺-
ATPase pump
(myocyte membrane)
→
↑ Intracellular
Na⁺ → ↓ Na⁺-Ca²⁺
exchange
→
↑ Intracellular
Ca²⁺ →
↑ Contractility
(+ ve inotropy) →
↑ Vagal tone
→ ↓ AV
conduction / HR
Uses
Symptomatic HFrEF, especially with coexisting AFib
Controls ventricular rate in AFib + HF
Reduces hospitalizations — NO mortality benefit
Reserved for symptoms persisting on GDMT
Side Effects — Narrow Therapeutic Index
GI: nausea, vomiting, anorexia
Visual disturbance — yellow-green halos (xanthopsia)
Arrhythmias (esp. with hypokalemia)
Toxicity potentiated by hypokalemia, renal impairment
21.
SUMMARY
The Four Pillarsof GDMT in HFrEF
1
ARNI / ACEI / ARB
RAAS blockade
2
Beta Blocker
Neurohormonal blockade
3
MRA
Aldosterone blockade
4
SGLT2 Inhibitor
Metabolic & diuretic effect
Added as needed:
Diuretics — for congestion / volume overload (symptom control, not mortality)
Digoxin — for persistent symptoms or rate control in AFib
Hydralazine + Nitrates — in select / ACEI-intolerant patients
Goal of therapy: relieve symptoms today, and modify neurohormonal disease biology for tomorrow.