Comprehensive Overview of Childhood Obesity: Causes, Assessment, and Management
Detailed insights into childhood obesity including causes, assessment methods, treatment options, prevention strategies, and the nurse's role in managing this growing public health issue.
Comprehensive Overview of Childhood Obesity: Causes, Assessment, and Management
1.
Children Obesity
Subject -nutritional
Bsc Nursing 2nd Sem
By Mr. Govinda Gajbhiye
Bsc Nursing, MSc Nursing, M.A clinical
psychologist
Assistant Professor
2.
Introduction
Childhood obesity isa major public health problem
worldwide. It is increasing rapidly among children
and adolescents due to unhealthy eating habits,
physical inactivity, and sedentary lifestyles. It
increases the risk of many chronic diseases later in
life.
Childhood obesity is a condition in which a child has
excessive body fat that negatively affects health and
well-being.
Incidence
Childhood obesity isone of the most serious public health
challenges of the 21st century. The problem is global and is
steadily affecting many low- and middle-income countries,
particularly in urban settings. The prevalence has increased at an
alarming rate. Globally in 2024, the number of overweight children
under the age of 5 years is estimated to have been over 35 million.
Almost half of all overweight children under 5 lived in Asia and one
quarter lived in Africa.
Regional Variations: Northern India records a higher pooled
obesity prevalence (8.58%) compared to Central India (5.63%), with
states like Arunachal Pradesh and Delhi showing higher
concentrated numbers.
5.
Cause- Trick- GUP,SSAM
Genetic factors – Children with one or both obese parents have a higher risk of
becoming obese due to inherited genetic traits.
Unhealthy diet – Frequent intake of energy-dense foods high in fat, sugar, and salt,
along with low consumption of fruits, vegetables, and other nutrient-rich foods.
Physical inactivity – Lack of regular exercise, sports, and outdoor activities reduces
energy expenditure.
Sedentary lifestyle – Excessive screen time (television, mobile phones, computers, and
video games) contributes to weight gain.
Social and environmental influences – Easy availability of high-calorie, highly palatable
foods, large portion sizes, frequent eating out, and social pressure to overeat.
Medical conditions (rare) – Hormonal disorders (e.g., hypothyroidism, Cushing
syndrome) and certain genetic disorders can lead to obesity.
8.
Assessment of childrenObesity
1.History Assessment
Dietary habits (high-fat, sugary
foods)
Physical activity and screen time
Family history of obesity
Medical and medication history
2 Anthropometric Assessment
A. Weight
Measure body weight accurately using a
calibrated weighing scale.
B. Height/Length
Measure standing height (children >2
years).
Measure recumbent length (children <2
years).
10.
2. Waist CircumferenceAssessment
Measures abdominal fat distribution.
Increased waist circumference indicates higher
metabolic risk.
Abnormal level:
Waist circumference 90th percentile for age and
≥
sex suggests central obesity.
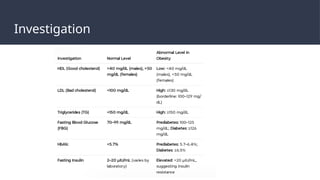
Abnormal Findings CommonlySeen in Obesity
HDL (good cholesterol)
↑ LDL (bad cholesterol)
↑ Triglycerides
↑ Blood glucose
↑ Insulin levels (hyperinsulinemia due to insulin resistance)
These abnormalities increase the risk of:
Type 2 diabetes mellitus
Hypertension
Cardiovascular disease
Metabolic syndrome
Non-alcoholic fatty liver disease (NAFLD)
14.
Treatment of Obesity
1.Dietary Management
Provide a balanced, calorie-appropriate diet.
Increase intake of fruits, vegetables, whole grains, and low-fat dairy products.
Reduce fast foods, fried foods, sweets, sugary drinks, and junk foods.
Encourage regular meal timings and healthy snacks.
2. Physical Activity
Encourage at least 60 minutes of moderate to vigorous physical activity daily.
Promote outdoor games, cycling, swimming, and sports.
Reduce sedentary activities.
3. Behavioral Therapy
Teach healthy eating habits.
Control portion size.
Avoid eating while watching TV or using mobile phones.
Set realistic weight-loss goals and reward healthy behaviors.
15.
Treatment
4. Family-Based Management
Involveparents and family members.
Encourage healthy eating and physical activity for the whole family.
Provide emotional support and motivation.
5. Reduce Screen Time
Limit TV, mobile phones, computers, and video games to less than 2
hours/day (except for schoolwork).
6. Medical Management
Treat associated conditions such as diabetes, hypertension,
dyslipidemia, and sleep apnea.
Anti-obesity medications may be considered only in selected
adolescents under specialist supervision when lifestyle measures are
insufficient.
16.
Treatment
7. Bariatric Surgery
Consideronly for severely obese adolescents with serious
obesity-related complications after failure of intensive
lifestyle treatment.
Performed only in specialized centers.
8. Health Education and Follow-up
Regular monitoring of weight, height, and BMI.
Nutrition counseling.
Regular follow-up to maintain healthy lifestyle changes.
17.
Prevention and Roleof the Nurse in Childhood Obesity
● Assess the child's height, weight, BMI, diet, and physical
activity.
● Identify children at risk of obesity.
● Educate children and parents about healthy eating and
exercise.
● Counsel families on behavior modification and weight
management.
● Encourage regular physical activity and reduced screen
time.
● Monitor growth, BMI, and progress during follow-up visits.
● Coordinate with doctors, dietitians, and other healthcare
professionals.
● Provide emotional support and motivate the child and