Mr. SATENDRA PRADHAN
Assistant Professor
Department of Pharmacology
COP, SVITS, Bilaspur
Dr. Sreeja PA
Professor and Head
Department of Pharmacy Practice
Dr. MGR University, Chennai
INTRODUCTION
Autocoids (Greek: autos = self, akos = remedy) are endogenous, biologically active substances locally
acting chemical mediators that are synthesized, released and act near their site of formation — hence
also called “local hormones.”
01 Produced On Demand
Unlike classical hormones, Autocoids are usually not pre-
formed in large stores — synthesized rapidly when needed
(exceptions: histamine, serotonin).
02 Act Locally (Paracrine/Autocrine)
They diffuse only short distances and act on nearby cells or
the cell of origin, unlike endocrine hormones that travel via
blood.
03 Short Biological Half-Life
Rapidly inactivated by local enzymes near the site of release
— action is brief and self-limiting.
04 Diverse Chemical Nature
Includes amines (histamine, serotonin), peptides (kinins,
angiotensin), lipid derivatives (eicosanoids) and a gas (nitric
oxide).
BASICS
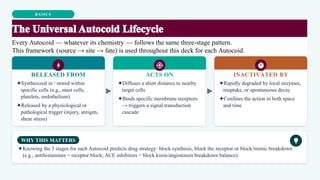
Every Autocoid — whatever its chemistry — follows the same three-stage pattern.
This framework (source → site → fate) is used throughout this deck for each Autocoid.
RELEASED FROM
✦Synthesized in / stored within
specific cells (e.g., mast cells,
platelets, endothelium)
✦Released by a physiological or
pathological trigger (injury, antigen,
shear stress)
ACTS ON
✦Diffuses a short distance to nearby
target cells
✦Binds specific membrane receptors
→ triggers a signal transduction
cascade
INACTIVATED BY
✦Rapidly degraded by local enzymes,
reuptake, or spontaneous decay
✦Confines the action in both space
and time
WHY THIS MATTERS
✦Knowing the 3 stages for each Autocoid predicts drug strategy: block synthesis, block the receptor or block/mimic breakdown
(e.g., antihistamines = receptor block; ACE inhibitors = block kinin/angiotensin breakdown balance).
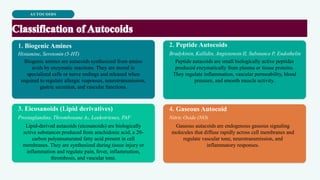
AUTOCOIDS
Biogenic Amines
Histamine, Serotonin (5-HT)
Peptide Autocoids
Bradykinin, Kallidin, Angiotensin II, Substance P, Endothelin
Eicosanoids (Lipid derivatives)
Prostaglandins, Thromboxane A₂, Leukotrienes, PAF
Gaseous Autocoid
Nitric Oxide (NO)
Biogenic amines are autacoids synthesized from amino
acids by enzymatic reactions. They are stored in
specialized cells or nerve endings and released when
required to regulate allergic responses, neurotransmission,
gastric secretion, and vascular functions.
Peptide autacoids are small biologically active peptides
produced enzymatically from plasma or tissue proteins.
They regulate inflammation, vascular permeability, blood
pressure, and smooth muscle activity.
Lipid-derived autacoids (eicosanoids) are biologically
active substances produced from arachidonic acid, a 20-
carbon polyunsaturated fatty acid present in cell
membranes. They are synthesized during tissue injury or
inflammation and regulate pain, fever, inflammation,
thrombosis, and vascular tone.
Gaseous autacoids are endogenous gaseous signaling
molecules that diffuse rapidly across cell membranes and
regulate vascular tone, neurotransmission, and
inflammatory responses.
AUTOCOID 1
Histamine is a biogenic amine derived from the amino acid histidine by the enzyme histidine decarboxylase.
A biogenic amine, pre-formed and stored — unlike most Autocoids
SYNTHESIS
✦Formed from the amino acid L-histidine
✦Enzyme: L-histidine decarboxylase (HDC)
✦One-step reaction — rapid synthesis when needed
✦Occurs mainly in mast cells, basophils & ECL cells
STORAGE SITES
✦Mast cells — skin, lungs, GI mucosa, connective tissue
(bound to heparin in granules)
✦Basophils — circulating blood
✦Enterochromaffin-like (ECL) cells — gastric mucosa
(regulate acid secretion)
✦Histaminergic neurons — tuberomammillary nucleus of
hypothalamus (CNS)
AUTOCOID 1
Histamine — Release, Site & Fate
RELEASED FROM
✦Pre-formed, stored in mast
cell/basophil secretory granules
bound to heparin
✦Released by IgE-antigen cross-
linking, trauma, cold, drugs
(morphine, tubocurarine), C3a/C5a
anaphylatoxins
ACTS ON
✦Diffuses to H1, H2, H3 & H4
receptors on smooth muscle,
vascular endothelium, gastric
parietal cells & nerve endings
INACTIVATED BY
✦Diamine oxidase (histaminase) —
oxidative deamination
✦Histamine-N-methyltransferase
(HNMT) — methylation
✦Plasma half-life ~1 minute
TRIGGER HIGHLIGHT
✦Type I hypersensitivity: allergen cross-links IgE on mast cell surface → receptor aggregation → degranulation → explosive
histamine release within minutes
✦Non-immunologic release (“histamine liberators”): opioids, radiocontrast media, certain antibiotics, physical trauma
Autocoid 1 · MECHANISM
Histamine — Mechanism of Action (H1 Pathway)
Histamine binds the H1 receptor (Gq-protein coupled) on target cell
membrane
Activates phospholipase C (PLC)
PLC cleaves PIP₂ into IP₃ and DAG
IP₃ releases Ca²⁺ from the endoplasmic/sarcoplasmic reticulum
↑ Intracellular Ca²⁺ → smooth muscle contraction (bronchi, gut) &
endothelial gap formation
Endothelium also releases NO → adjacent vascular smooth muscle
relaxes → Vasodilation & Flare
QUICK NOTES
✦H1 activation on endothelium and H1 activation
on smooth muscle produce opposite mechanical
effects — vasodilation vs bronchoconstriction —
both via Gq/Ca²⁺
✦H2 receptors instead couple to Gs → ↑ cAMP →
gastric acid secretion & mild cardiac stimulation
✦This combination (↑ permeability + vasodilation
+ smooth muscle spasm) produces the classic
“triple response of Lewis”: flush, flare, wheal
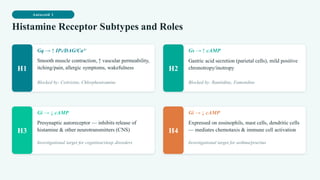
Autocoid 1
Histamine Receptor Subtypes and Roles
H1
Gq → ↑ IP₃/DAG/Ca²⁺
Smooth muscle contraction, ↑ vascular permeability,
itching/pain, allergic symptoms, wakefulness
Blocked by: Cetirizine, Chlorpheniramine
H2
Gs → ↑ cAMP
Gastric acid secretion (parietal cells), mild positive
chronotropy/inotropy
Blocked by: Ranitidine, Famotidine
H3
Gi → ↓ cAMP
Presynaptic autoreceptor — inhibits release of
histamine & other neurotransmitters (CNS)
Investigational target for cognition/sleep disorders
H4
Gi → ↓ cAMP
Expressed on eosinophils, mast cells, dendritic cells
— mediates chemotaxis & immune cell activation
Investigational target for asthma/pruritus
Autocoid 1
Histamine — Physiological & Pathological Roles
PHYSIOLOGICAL ROLES
✦Regulates gastric acid secretion (H2, basal & stimulated)
✦Neurotransmitter in CNS — wakefulness, appetite, arousal
(H1/H3)
✦Local vasodilator — contributes to regulation of
microcirculation
✦Mediator of the immediate (Type I) inflammatory response
✦Modulates immune cell chemotaxis (H4)
PATHOLOGICAL ROLES
✦Anaphylaxis — massive systemic release → hypotension,
bronchospasm, edema
✦Allergic rhinitis, urticaria, angioedema, atopic dermatitis
✦Bronchial asthma — contributes to bronchoconstriction
✦Peptic ulcer disease — excess H2-mediated acid secretion
✦Motion sickness & vertigo (CNS H1 pathway)
Autocoid 2
Serotonin is a biogenic amine synthesized from the amino acid tryptophan. It acts as both a neurotransmitter and
an autacoid, regulating mood, gastrointestinal motility, platelet aggregation and vascular tone.
~90% of body serotonin resides in the gut, not the brain
SYNTHESIS
✦Formed from the amino acid L-tryptophan
✦Step 1: Tryptophan hydroxylase → 5-hydroxytryptophan
(5-HTP)
✦Step 2: Aromatic L-amino acid decarboxylase → 5-HT
(serotonin)
✦Synthesized locally in enterochromaffin cells and CNS
neurons
STORAGE SITES
✦Enterochromaffin cells of the GI mucosa — largest store
(~90%)
✦Platelets — take up circulating 5-HT via active transport (do
NOT synthesize it) and store it in dense granules
✦CNS neurons — raphe nuclei of the brainstem, project
widely
✦Small amounts in mast cells of some species
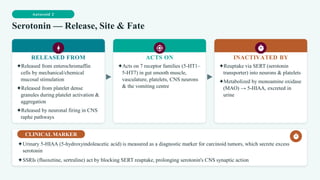
Autocoid 2
Serotonin — Release, Site & Fate
RELEASED FROM
✦Released from enterochromaffin
cells by mechanical/chemical
mucosal stimulation
✦Released from platelet dense
granules during platelet activation &
aggregation
✦Released by neuronal firing in CNS
raphe pathways
ACTS ON
✦Acts on 7 receptor families (5-HT1–
5-HT7) in gut smooth muscle,
vasculature, platelets, CNS neurons
& the vomiting centre
INACTIVATED BY
✦Reuptake via SERT (serotonin
transporter) into neurons & platelets
✦Metabolized by monoamine oxidase
(MAO) → 5-HIAA, excreted in
urine
CLINICAL MARKER
✦Urinary 5-HIAA (5-hydroxyindoleacetic acid) is measured as a diagnostic marker for carcinoid tumors, which secrete excess
serotonin
✦SSRIs (fluoxetine, sertraline) act by blocking SERT reuptake, prolonging serotonin's CNS synaptic action
Autocoid 2 · MECHANISM
Serotonin — Mechanism of Action
5-HT released locally can act via two distinct receptor mechanisms
Fast pathway: binds 5-HT₃ — a ligand-gated Na⁺/K⁺ ion channel → direct,
rapid membrane depolarization
Slow pathway: binds 5-HT₁/5-HT₂ GPCRs on smooth muscle & platelets
5-HT₂ (Gq) → PLC → IP₃/DAG → ↑ Ca²⁺ → smooth muscle contraction &
platelet aggregation
5-HT₁ (Gi) → ↓ cAMP → cranial vasoconstriction & presynaptic inhibition
Net effect depends on receptor mix in that tissue: motility,
vasoconstriction/dilation, platelet plug formation, or the vomiting reflex
QUICK NOTES
✦5-HT₃ is the only ionotropic (ligand-gated
channel) serotonin receptor — all others are
GPCRs
✦5-HT₃ receptors on vagal afferents in the gut &
chemoreceptor trigger zone mediate
nausea/vomiting — blocked by ondansetron
(antiemetic)
✦5-HT₁B/1D on cranial vessels mediate the
vasoconstrictor action exploited by triptans in
migraine treatment
Autocoid 2
Serotonin Receptor Subtypes
5-HT₁
Gi → ↓ cAMP
Cranial vasoconstriction, presynaptic autoreceptor,
CNS mood regulation
Triptans (migraine) act at 5-HT1B/1D
5-HT₂
Gq → ↑ IP₃/Ca²⁺
Smooth muscle contraction, platelet aggregation,
CNS behaviour/mood
Blocked by atypical antipsychotics
5-HT₃
Ligand-gated ion channel
Vagal afferents & CTZ — mediates nausea/vomiting
reflex; fast neuronal depolarization
Blocked by Ondansetron (antiemetic)
5-HT₄
Gs → ↑ cAMP
Enteric neurons — promotes GI motility &
secretion
Target of prokinetic drugs (e.g., prucalopride)
5-HT₅
Gi → ↓ cAMP
Regulates circadian rhythm, learning, memory, and
CNS functions (not fully understood)
No selective drugs in routine clinical use
5-HT₆
Gs → ↑ cAMP
Cognitive function, memory, learning,
neurotransmitter release
Investigational target for Alzheimer's disease and cognitive
disorders.
5-HT₇
Gs → ↑ cAMP
Circadian rhythm, thermoregulation, smooth
muscle relaxation, mood regulation
Potential target for depression, migraine, and sleep disorders
Autocoid 2
Serotonin — Physiological & Pathological Roles
PHYSIOLOGICAL ROLES
✦Regulates GI motility & secretion
✦Essential for primary hemostasis — promotes platelet
aggregation & local vasoconstriction at injury sites
✦Modulates vascular tone (constrictor or dilator depending
on receptor/vessel)
✦CNS neurotransmitter — mood, sleep-wake cycle, appetite,
temperature regulation
✦Mediates the vomiting reflex via CTZ & vagal afferents
PATHOLOGICAL ROLES
✦Carcinoid syndrome — tumor overproduction causes
flushing, diarrhea, bronchospasm
✦Migraine pathophysiology — cranial vessel tone changes
✦Depression & anxiety disorders — CNS serotonergic
dysfunction (target of SSRIs)
✦Serotonin syndrome — toxic excess from drug interactions
(hyperthermia, rigidity, autonomic instability)
✦Chemotherapy-induced nausea/vomiting — 5-HT₃-
mediated
Autocoid 3
All eicosanoids (prostaglandins, thromboxane, leukotrienes) originate from one precursor via two branching enzymatic
pathways.
Cell injury/stimulus activates phospholipase A2 on membrane phospholipids
Arachidonic acid is liberated from the cell membrane
Cyclooxygenase (COX-1/COX-2) pathway converts it to PGG2/PGH2 →
Prostaglandins, Prostacyclin, Thromboxane A2
5-Lipoxygenase (5-LOX) pathway converts it to 5-HPETE → Leukotrienes
(LTB4, LTC4, LTD4, LTE4)
These eicosanoids act locally on smooth muscle, platelets, and immune cells
Net result: Inflammation, Pain, Fever, Bronchoconstriction and Platelet
Aggregation
WHY THIS WORKS
This single cascade produces two families
of mediators through parallel enzymatic
branches. The COX branch and the LOX
branch are independent drug targets:
NSAIDs block the COX branch
(prostaglandins/thromboxane), while
leukotriene modifiers block the LOX
branch or its receptors - explaining why the
two drug classes have complementary, non-
overlapping effects, especially in asthma.
Drugs: Target of NSAIDs (COX) and
leukotriene modifiers (5-LOX)
Autocoid 3A
Prostaglandins are locally acting lipid mediators synthesized by the cyclooxygenase pathway from arachidonic
acid. They regulate inflammation, pain, fever, gastric protection, uterine contraction, and renal blood flow.
Never stored — synthesized fresh, on demand, everywhere
SYNTHESIZING ENZYMES
✦COX-1 — constitutive, “housekeeping”: gastric mucosa,
platelets, kidney, vascular endothelium
✦COX-2 — inducible by inflammation, cytokines, growth
factors (also constitutive in kidney & brain)
✦Tissue-specific terminal synthases determine which
prostaglandin (PGE synthase, PGF synthase, PGI
synthase) a cell makes
KEY FEATURES
✦Virtually every nucleated cell can synthesize some
prostaglandin — unlike histamine/serotonin's restricted cell
types
✦No storage granules — synthesis begins within seconds of
the triggering stimulus
✦Aspirin irreversibly acetylates COX; other NSAIDs
reversibly inhibit it — basis of anti-inflammatory therapy
Autocoid 3A
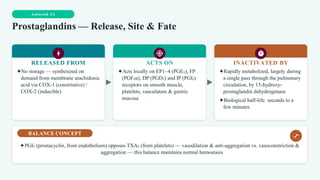
Prostaglandins — Release, Site & Fate
RELEASED FROM
✦No storage — synthesized on
demand from membrane arachidonic
acid via COX-1 (constitutive) /
COX-2 (inducible)
ACTS ON
✦Acts locally on EP1–4 (PGE₂), FP
(PGF₂α), DP (PGD₂) and IP (PGI₂)
receptors on smooth muscle,
platelets, vasculature & gastric
mucosa
INACTIVATED BY
✦Rapidly metabolized, largely during
a single pass through the pulmonary
circulation, by 15-hydroxy-
prostaglandin dehydrogenase
✦Biological half-life: seconds to a
few minutes
BALANCE CONCEPT
✦PGI₂ (prostacyclin, from endothelium) opposes TXA₂ (from platelets) — vasodilation & anti-aggregation vs. vasoconstriction &
aggregation — this balance maintains normal hemostasis
Autocoid 3A · MECHANISM
Prostaglandin E₂ — Mechanism of Action
PGE₂, synthesized locally, diffuses to nearby cells expressing EP receptors
Binds EP2/EP4 receptors (Gs-protein coupled) on target cell membrane
Activates adenylate cyclase → ↑ intracellular cAMP
Protein Kinase A (PKA) is activated → phosphorylates target proteins
In vascular/bronchial smooth muscle: relaxation → vasodilation /
bronchodilation
In gastric mucosa: ↑ mucus & bicarbonate secretion, ↓ acid secretion —
mucosal protection
QUICK NOTES
✦Different prostaglandins use different
receptors and can produce opposite effects:
PGF₂α via FP (Gq) contracts smooth muscle,
while PGE₂ via EP2/4 (Gs) relaxes it
✦This receptor diversity explains why
“prostaglandins” as a group can both raise and
lower blood pressure, and both stimulate and
inhibit uterine contraction depending on
subtype
✦NSAIDs blunt ALL of these effects at once by
inhibiting the shared COX enzyme upstream
Autocoid 3A
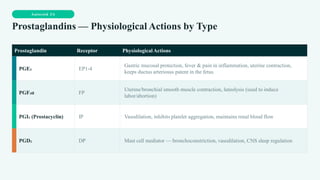
Prostaglandins — Physiological Actions by Type
Prostaglandin Receptor Physiological Actions
PGE₂ EP1-4
Gastric mucosal protection, fever & pain in inflammation, uterine contraction,
keeps ductus arteriosus patent in the fetus
PGF₂α FP
Uterine/bronchial smooth muscle contraction, luteolysis (used to induce
labor/abortion)
PGI₂ (Prostacyclin) IP Vasodilation, inhibits platelet aggregation, maintains renal blood flow
PGD₂ DP Mast cell mediator — bronchoconstriction, vasodilation, CNS sleep regulation
Autocoid 3B
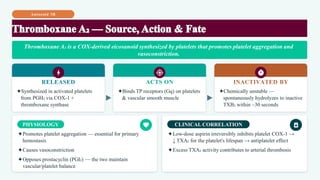
RELEASED
✦Synthesized in activated platelets
from PGH₂ via COX-1 +
thromboxane synthase
ACTS ON
✦Binds TP receptors (Gq) on platelets
& vascular smooth muscle
INACTIVATED BY
✦Chemically unstable —
spontaneously hydrolyzes to inactive
TXB₂ within ~30 seconds
PHYSIOLOGY
✦Promotes platelet aggregation — essential for primary
hemostasis
✦Causes vasoconstriction
✦Opposes prostacyclin (PGI₂) — the two maintain
vascular/platelet balance
CLINICAL CORRELATION
✦Low-dose aspirin irreversibly inhibits platelet COX-1 →
↓ TXA₂ for the platelet's lifespan → antiplatelet effect
✦Excess TXA₂ activity contributes to arterial thrombosis
Thromboxane A₂ is a COX-derived eicosanoid synthesized by platelets that promotes platelet aggregation and
vasoconstriction.
Autocoid 3C
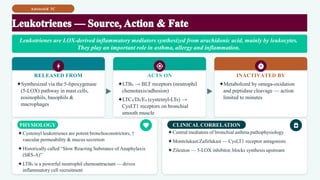
RELEASED FROM
✦Synthesized via the 5-lipoxygenase
(5-LOX) pathway in mast cells,
eosinophils, basophils &
macrophages
ACTS ON
✦LTB₄ → BLT receptors (neutrophil
chemotaxis/adhesion)
✦LTC₄/D₄/E₄ (cysteinyl-LTs) →
CysLT1 receptors on bronchial
smooth muscle
INACTIVATED BY
✦Metabolized by omega-oxidation
and peptidase cleavage — action
limited to minutes
PHYSIOLOGY
✦Cysteinyl leukotrienes are potent bronchoconstrictors, ↑
vascular permeability & mucus secretion
✦Historically called “Slow Reacting Substance of Anaphylaxis
(SRS-A)”
✦LTB₄ is a powerful neutrophil chemoattractant — drives
inflammatory cell recruitment
CLINICAL CORRELATION
✦Central mediators of bronchial asthma pathophysiology
✦Montelukast/Zafirlukast — CysLT1 receptor antagonists
✦Zileuton — 5-LOX inhibitor, blocks synthesis upstream
Leukotrienes are LOX-derived inflammatory mediators synthesized from arachidonic acid, mainly by leukocytes.
They play an important role in asthma, allergy and inflammation.
Autocoid 3
Whatever the pathway, eicosanoids share one defining trait: they act within seconds to minutes of formation and are destroyed almost
as quickly — true “hit-and-run” local mediators.
PGE₂ / PGF₂α Seconds–minutes
Degraded chiefly by 15-hydroxy-PG dehydrogenase during
first pass through the lungs
PGI₂ (Prostacyclin) ~2–3 minutes
Spontaneously hydrolyzes to inactive 6-keto-PGF₁α
TXA₂ ~30 seconds
Chemically unstable — spontaneously hydrolyzes to
inactive TXB₂
Leukotrienes Minutes
Inactivated by omega-oxidation and peptidase cleavage
Autocoid 4
Tissue injury/inflammation activates Factor XII (Hageman factor) →
converts prekallikrein to kallikrein
Plasma kallikrein acts on high-molecular-weight kininogen (HMWK) →
releases Bradykinin
Tissue kallikrein acts on low-molecular-weight kininogen (LMWK) →
releases Kallidin (Lys-bradykinin)
Aminopeptidase converts kallidin to bradykinin
Bradykinin diffuses locally to act on B1/B2 receptors on nearby cells
Rapidly degraded within seconds by kininases (kininase I & II)
QUICK NOTES
✦Kininase II is identical to Angiotensin-
Converting Enzyme (ACE) — the same
enzyme that forms Angiotensin II also
destroys bradykinin
✦This dual role explains why ACE inhibitors
both lower blood pressure (via less Ang II) and
potentiate bradykinin (cough, angioedema)
✦Unlike histamine/serotonin, kinins are peptides
formed by proteolytic cleavage, not stored pre-
formed
Autocoid 4
Bradykinin — Release, Site & Fate
RELEASED FROM
✦Formed from plasma/tissue
kininogen by kallikrein enzymes,
activated during tissue injury,
inflammation or Factor XII
activation
ACTS ON
✦B2 receptors — constitutive, most
tissues (vascular endothelium, smooth
muscle, sensory nerves)
✦B1 receptors — induced/upregulated
by tissue injury & inflammation
INACTIVATED BY
✦Degraded within seconds by
kininase I and kininase II (= ACE)
✦Among the shortest half-lives of all
Autocoids (~15 seconds)
POTENCY NOTE
✦Bradykinin is one of the most potent endogenous vasodilators known — roughly 10x more potent than histamine on a molar basis
for increasing vascular permeability
Bradykinin is a vasodilator peptide produced from kininogen by kallikrein. It is one of the most potent mediators
of pain and inflammation.
Autocoid 4 · MECHANISM
Bradykinin — Mechanism of Action
Bradykinin binds the B2 receptor (Gq-coupled, constitutive) on vascular
endothelial cells
Activates PLC → IP₃/DAG → ↑ intracellular Ca²⁺
Stimulates endothelial NO synthase (eNOS) and phospholipase A₂ (→
prostacyclin)
NO & PGI₂ diffuse to adjacent vascular smooth muscle → activate
guanylate/adenylate cyclase
Smooth muscle relaxation → pronounced vasodilation & increased
capillary permeability
Also directly stimulates sensory nerve endings → Pain
ROLES
✦Mediator of inflammatory edema and pain
✦Contributes to hypotension in septic shock
✦Regulates local blood flow in exocrine glands
(e.g., salivary, sweat glands) during active
secretion
✦ACE inhibitor side effects (dry cough,
angioedema) result directly from reduced
bradykinin breakdown
Autocoid 5
Nitric oxide is a gaseous autacoid synthesized from L-arginine by nitric oxide synthase (NOS) that acts as a
potent vasodilator.
The only gaseous Autocoid — needs no receptor to enter cells
SYNTHESIS
✦Formed from L-arginine + O₂ → NO + L-citrulline
✦Catalyzed by nitric oxide synthase (NOS) enzymes
✦Requires NADPH, FAD, FMN & tetrahydrobiopterin as
cofactors
THREE NOS ISOFORMS
✦eNOS — endothelium, constitutive, Ca²⁺/calmodulin-
dependent, activated by shear stress/ACh/bradykinin
✦nNOS — neurons, constitutive, Ca²⁺/calmodulin-dependent,
neurotransmission
✦iNOS — macrophages & inflammatory cells, inducible by
cytokines/LPS, Ca²⁺-independent, produces large sustained
amounts (host defense)
Autocoid 5 · MECHANISM
Nitric Oxide —Mechanism of Action
Shear stress, acetylcholine or bradykinin stimulate eNOS in endothelial
cells → NO synthesized from L-arginine
NO freely diffuses across the cell membrane (a gas — no transporter or
receptor needed) into adjacent smooth muscle
Activates soluble guanylate cyclase (sGC) → converts GTP to cGMP
↑ cGMP activates Protein Kinase G (PKG)
PKG lowers intracellular Ca²⁺ in smooth muscle → relaxation →
vasodilation
NO itself has a half-life of only seconds — rapidly oxidized to
nitrite/nitrate or bound by hemoglobin
QUICK NOTES
✦NO is unique among Autocoids: it diffuses
freely through membranes rather than binding
a surface receptor to signal
✦The same NO → cGMP pathway underlies
nitrate drugs (nitroglycerin, exogenous NO
donors) and PDE5 inhibitors (sildenafil, which
prevents cGMP breakdown)
✦Also inhibits platelet aggregation and
leukocyte adhesion to endothelium
Nitric Oxide 27
Autocoid 5
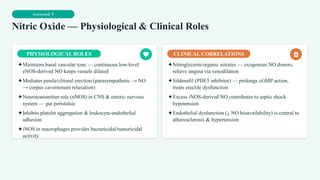
Nitric Oxide — Physiological & Clinical Roles
PHYSIOLOGICAL ROLES
✦Maintains basal vascular tone — continuous low-level
eNOS-derived NO keeps vessels dilated
✦Mediates penile/clitoral erection (parasympathetic → NO
→ corpus cavernosum relaxation)
✦Neurotransmitter role (nNOS) in CNS & enteric nervous
system — gut peristalsis
✦Inhibits platelet aggregation & leukocyte-endothelial
adhesion
✦iNOS in macrophages provides bactericidal/tumoricidal
activity
CLINICAL CORRELATIONS
✦Nitroglycerin/organic nitrates — exogenous NO donors,
relieve angina via venodilation
✦Sildenafil (PDE5 inhibitor) — prolongs cGMP action,
treats erectile dysfunction
✦Excess iNOS-derived NO contributes to septic shock
hypotension
✦Endothelial dysfunction (↓ NO bioavailability) is central to
atherosclerosis & hypertension
Autocoid 6
RELEASED FROM
✦Synthesized by platelets, neutrophils,
macrophages & endothelium via the
remodeling pathway (PLA₂ → lyso-
PAF → acetylation)
ACTS ON (SITE)
✦Binds a specific PAF receptor (Gq-
coupled GPCR) on platelets,
neutrophils & smooth muscle
INACTIVATED BY (TILL)
✦Inactivated by PAF-acetylhydrolase,
which removes the acetyl group
PHYSIOLOGY
✦Extremely potent — active at nanomolar concentrations,
roughly 1000-10,000x more potent than histamine by weight
✦Causes platelet aggregation, neutrophil activation, potent
bronchoconstriction & ↑ vascular permeability
CLINICAL CORRELATION
✦Implicated in the pathophysiology of bronchial asthma,
anaphylaxis & sepsis
✦Contributes to thrombosis via its platelet-activating effect
Platelet-Activating Factor (PAF) is a potent phospholipid-derived autocoid produced by various inflammatory
and immune cells. It acts through PAF receptors (PAFR), which are G-protein-coupled receptors (GPCRs) to
mediate inflammation, platelet aggregation, bronchoconstriction, and increased vascular permeability.
SYNTHESIS
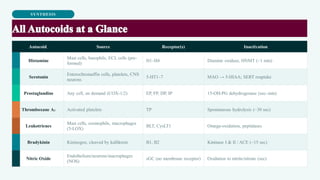
Autocoid Source Receptor(s) Inactivation
Histamine
Mast cells, basophils, ECL cells (pre-
formed)
H1–H4 Diamine oxidase, HNMT (~1 min)
Serotonin
Enterochromaffin cells, platelets, CNS
neurons
5-HT1–7 MAO → 5-HIAA; SERT reuptake
Prostaglandins Any cell, on demand (COX-1/2) EP, FP, DP, IP 15-OH-PG dehydrogenase (sec–min)
Thromboxane A₂ Activated platelets TP Spontaneous hydrolysis (~30 sec)
Leukotrienes
Mast cells, eosinophils, macrophages
(5-LOX)
BLT, CysLT1 Omega-oxidation, peptidases
Bradykinin Kininogen, cleaved by kallikrein B1, B2 Kininase I & II / ACE (~15 sec)
Nitric Oxide
Endothelium/neurons/macrophages
(NOS)
sGC (no membrane receptor) Oxidation to nitrite/nitrate (sec)
SYNTHESIS
Antihistamines
Block H1 (allergy) or H2 (peptic
ulcer) receptors
NSAIDs / Aspirin
Inhibit COX → ↓ prostaglandins &
thromboxane
Leukotriene modifiers
Montelukast (CysLT1 blocker),
Zileuton (5-LOX inhibitor) — asthma
Triptans
5-HT1B/1D agonists — cranial
vasoconstriction in migraine
Ondansetron
5-HT3 antagonist — antiemetic
(chemotherapy, post-op nausea)
ACE Inhibitors
↓ Angiotensin II & ↓ bradykinin
breakdown (cough/angioedema side
effect)
Organic Nitrates
Exogenous NO donors —
venodilation, relieve angina
PDE5 Inhibitors
Sildenafil — prolongs NO/cGMP
signal for erectile dysfunction
SSRIs
Block SERT — prolong serotonin
action in CNS synapses
INTRODUCTION
Drugs related to autocoids are pharmacological agents that mimic, block, enhance or inhibit the
synthesis, release, metabolism or receptor actions of endogenous autocoids.
01 Modify Autocoid Activity
These drugs either stimulate (agonists) or block (antagonists)
autocoid receptors, or alter the synthesis, release and
degradation of endogenous mediators to regulate physiological
responses.
02 Target Specific Receptors & Enzymes
Most drugs act on histamine (H₁–H₄), serotonin (5-HT₁–5-HT₇),
prostaglandin, leukotriene, bradykinin, endothelin, nitric oxide
and PAF receptors, or inhibit enzymes such as cyclooxygenase
(COX) and lipoxygenase (LOX).
03 Wide Therapeutic Applications
Autocoid drugs are extensively used in the management of
allergic disorders, bronchial asthma, peptic ulcer disease, pain,
inflammation, migraine, glaucoma, pulmonary hypertension,
chemotherapy-induced nausea and cardiovascular disorders.
AUTOCOIDS
H1 Antihistamines
Diphenhydramine, Cetirizine, Loratadine, Fexofenadine
→ block allergic/inflammatory histamine actions
H2 Antihistamines
Famotidine, Cimetidine, Ranitidine
→ reduce gastric acid secretion
5-HT3 Antagonists
Ondansetron, Granisetron, Palonosetron
→ potent antiemetics
NSAIDs (COX Inhibitors)
Aspirin, Ibuprofen, Diclofenac, Celecoxib
→ block prostaglandin synthesis
Leukotriene Modifiers
Montelukast, Zafirlukast, Zileuton
→ block the 5-LOX pathway or its receptors
PAF Antagonists
Rupatadine and investigational agents
→ block platelet-activating factor receptors
CLASS 1 · H1 BLOCKERS
H₁ antihistamines are drugs that competitively block (or act as inverse agonists at) H₁ histamine receptors, thereby
preventing the actions of histamine released during allergic reactions.
Drug competitively binds and blocks the H1 receptor (Gq-coupled) on target
tissues
Prevents histamine from activating the PLC → IP3/DAG signaling cascade
Blocks histamine-induced smooth-muscle contraction, vasodilation, and
capillary permeability
Suppresses the wheal-and-flare response and sensory-nerve-mediated itching
First-generation agents cross the blood-brain barrier → central H1 blockade →
sedation; second-generation agents are poor BBB penetrants (P-glycoprotein
substrates) and are largely non-sedating
Net Result: relief of Allergic Symptoms - Sneezing, Rhinorrhea, Itching
and Urticaria
WHY THIS WORKS
H1 receptors mediate the immediate
hypersensitivity (Type I) reaction through
the Gq/PLC/IP3 pathway. Because these
drugs are competitive receptor antagonists
rather than mediator-release blockers, they
work best when given prophylactically or
early, before extensive receptor occupation
by released histamine - explaining their
limited benefit once severe symptoms are
established.
Drugs: Cetirizine, Loratadine
CLASS 1 · H1 BLOCKERS
H1 Antihistamines - Uses & Adverse Effects
Examples:- 1st gen: Diphenhydramine, Chlorpheniramine
2nd gen: Cetirizine, Loratadine, Fexofenadine
Therapeutic Uses
✦ Allergic rhinitis, allergic conjunctivitis, urticaria
✦ Pruritus (insect bites, atopic dermatitis)
✦ Motion sickness and vertigo (1st generation agents)
✦ Adjunct in anaphylaxis (with epinephrine) and mild
sedation/sleep aid (1st generation)
Adverse Effects
✦ Sedation and psychomotor impairment (1st generation)
✦ Anticholinergic effects - dry mouth, blurred vision,
urinary retention (1st generation)
✦ Second-generation agents - less sedation; rare QT
prolongation with older non-selective agents (e.g.,
terfenadine, withdrawn)
✦ Paradoxical CNS stimulation in children (1st
generation)
CLASS 2 · H2 BLOCKERS
H2 Antihistamines - Mechanism of Action
H₂ antihistamines (H₂ receptor antagonists or H₂ blockers) are drugs that competitively block histamine H₂ receptors
on gastric parietal cells, thereby reducing gastric acid (HCl) secretion
Drug competitively blocks the H2 receptor (Gs-coupled) on gastric parietal
cells
Prevents histamine-stimulated activation of adenylyl cyclase
Intracellular cAMP levels fall, reducing protein kinase A activity
Reduced PKA activity decreases activation/insertion of the H+/K+-ATPase
(proton pump) at the canalicular membrane
Basal and stimulated gastric acid secretion is reduced - histamine normally
amplifies gastrin- and acetylcholine-driven acid secretion, so blocking it blunts
all three pathways
Net Result: Reduced Gastric Acidity, Allowing Mucosal Healing
WHY THIS WORKS
Histamine acts as the final common
amplifier of parietal cell acid secretion:
gastrin and vagal (ACh) stimulation both
partly act through local histamine release
from ECL cells. Blocking H2 receptors
therefore blunts acid output triggered by all
three secretagogues, which is why a single-
receptor blockade achieves broad
antisecretory efficacy.
Drugs: Famotidine, Cimetidine
CLASS 2 · H2 BLOCKERS
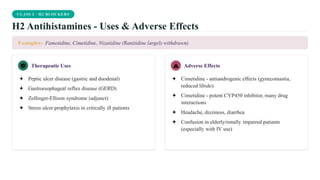
H2 Antihistamines - Uses & Adverse Effects
Examples:- Famotidine, Cimetidine, Nizatidine (Ranitidine largely withdrawn)
Therapeutic Uses
✦ Peptic ulcer disease (gastric and duodenal)
✦ Gastroesophageal reflux disease (GERD)
✦ Zollinger-Ellison syndrome (adjunct)
✦ Stress ulcer prophylaxis in critically ill patients
Adverse Effects
✦ Cimetidine - antiandrogenic effects (gynecomastia,
reduced libido)
✦ Cimetidine - potent CYP450 inhibitor, many drug
interactions
✦ Headache, dizziness, diarrhea
✦ Confusion in elderly/renally impaired patients
(especially with IV use)
CLASS 3 · ANTIEMETICS
5-HT3 Receptor Antagonists - Mechanism of Action
5-HT₃ receptor antagonists are drugs that selectively block serotonin (5-hydroxytryptamine) type-3 (5-HT₃) receptors located in the
chemoreceptor trigger zone (CTZ), nucleus tractus solitarius (NTS), vagal afferent nerves and gastrointestinal tract.
WHY THIS WORKS
5-HT3 receptors are ligand-gated cation
channels present both peripherally (vagal
afferents in the gut) and centrally (area
postrema). Chemotherapy-induced release of
serotonin from enterochromaffin cells is the
dominant trigger of acute emesis, so dual
peripheral-plus-central 5-HT3 blockade
gives near-complete control of the acute
emetic reflex arc.
Drugs: Ondansetron, Granisetron
Chemotherapy, radiation or surgery triggers serotonin release from
enterochromaffin cells in the gut mucosa
Drug competitively blocks 5-HT3 receptors on vagal afferent nerve terminals in
the gut wall
Blocks 5-HT3 receptors in the chemoreceptor trigger zone (area postrema) of
the brainstem as well
Peripheral vagal afferent signaling to the vomiting center is interrupted
Central relay of the emetic signal from the CTZ to the vomiting center is also
blocked
Net Result: Marked Suppression of Nausea and Vomiting
CLASS 3 · ANTIEMETICS
5-HT3 Receptor Antagonists - Uses & Adverse Effects
Examples:- Ondansetron, Granisetron, Palonosetron
Therapeutic Uses
✦ Chemotherapy-induced nausea and vomiting (CINV)
✦ Postoperative nausea and vomiting (PONV)
✦ Radiotherapy-induced emesis
✦ Severe hyperemesis gravidarum (selected cases, off-
label)
Adverse Effects
✦ Headache
✦ Constipation
✦ QT interval prolongation (dose-dependent, monitor in
cardiac risk patients)
✦ Dizziness; transient elevation of liver transaminases
CLASS 4 · COX INHIBITORS
NSAIDs (Prostaglandin Synthesis Inhibitors) - MOA
Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) are a group of drugs that inhibit the cyclooxygenase (COX-1 and/or COX-2)
enzymes, thereby reducing the synthesis of prostaglandins, prostacyclin (PGI₂), and thromboxane A₂ (TXA₂) from Arachidonic acid.
WHY THIS WORKS
COX is the rate-limiting, shared enzyme of
the entire prostaglandin/thromboxane branch
of the arachidonic acid cascade. Because
prostaglandins mediate the cardinal features
of inflammation and fever, blocking their
synthesis - rather than a single receptor -
gives NSAIDs broad antipyretic, analgesic,
and anti-inflammatory activity, while also
explaining their characteristic GI and renal
toxicity from loss of protective COX-1-
derived prostaglandins.
Drugs: Ibuprofen, Aspirin, Celecoxib
Tissue injury/stimulus activates phospholipase A2, releasing arachidonic acid
from membrane phospholipids
NSAID inhibits cyclooxygenase (COX-1 and/or COX-2), the enzyme
converting arachidonic acid to PGG2/PGH2
Downstream synthesis of prostaglandins (PGE2), prostacyclin (PGI2), and
thromboxane A2 is reduced
Reduced PGE2 at the hypothalamus lowers the febrile set-point - antipyretic
effect
Reduced PGE2/PGI2 sensitization of peripheral nociceptors - analgesic effect;
reduced PG-mediated vasodilation/permeability - anti-inflammatory effect
COX-1 inhibition also reduces protective gastric Mucosal Prostaglandins
and Platelet Thromboxane A2
CLASS 4 · COX INHIBITORS
NSAIDs - Uses & Adverse Effects
Examples:- Aspirin, Ibuprofen, Diclofenac, Naproxen (non-selective); Celecoxib (COX-2 selective)
Therapeutic Uses
✦ Mild-to-moderate pain and dysmenorrhea
✦ Fever reduction
✦ Inflammatory conditions - osteoarthritis, rheumatoid
arthritis
✦ Low-dose aspirin for antiplatelet/cardioprotective effect
Adverse Effects
✦ GI ulceration and bleeding (COX-1-related)
✦ Nephrotoxicity - reduced renal prostaglandin-mediated
perfusion
✦ Increased cardiovascular thrombotic risk (especially
COX-2 selective agents)
✦ Bronchospasm in aspirin-sensitive asthmatics; platelet
dysfunction with non-selective agents
CLASS 5 · LOX PATHWAY
Leukotriene Modifiers - Mechanism of Action
Leukotriene modifiers are drugs that inhibit the synthesis or block the actions of leukotrienes, thereby reducing
bronchoconstriction, airway inflammation, mucus secretion and eosinophil recruitment.
WHY THIS WORKS
Cysteinyl leukotrienes are markedly more
potent bronchoconstrictors than histamine
and are the principal mediators of the late-
phase asthmatic response. Because this
pathway runs parallel to, and independent of,
the COX/prostaglandin branch, leukotriene
modifiers provide benefit that complements
(rather than duplicates) inhaled
corticosteroids and beta-agonists, especially
in allergen- or exercise-triggered asthma.
Drugs: Montelukast, Zileuton
Arachidonic acid is metabolized via the alternate 5-lipoxygenase (5-LOX)
pathway to form LTA4, then cysteinyl leukotrienes (LTC4, LTD4, LTE4)
5-LOX inhibitors (e.g., zileuton) block the enzyme directly, halting leukotriene
synthesis at the source
Leukotriene receptor antagonists (e.g., montelukast, zafirlukast) instead block
the CysLT1 receptor on airway smooth muscle and immune cells
Either strategy prevents leukotriene-driven bronchoconstriction, mucus
hypersecretion, and airway wall edema
Eosinophil recruitment and airway inflammation are reduced
Net Result: Bronchodilation and Reduced Airway Inflammation,
particularly in Allergic and Exercise-induced Asthma
CLASS 5 · LOX PATHWAY
Leukotriene Modifiers - Uses & Adverse Effects
Examples:- Montelukast, Zafirlukast (receptor antagonists); Zileuton (5-LOX synthesis inhibitor)
Therapeutic Uses
✦ Chronic asthma - add-on/prophylactic therapy
✦ Exercise-induced bronchospasm
✦ Allergic rhinitis (montelukast)
✦ Aspirin-exacerbated respiratory disease (adjunct)
Adverse Effects
✦ Headache, GI upset
✦ Neuropsychiatric effects - mood changes, sleep
disturbance, vivid dreams (montelukast; boxed warning)
✦ Hepatotoxicity - especially zileuton; requires LFT
monitoring
✦ Churg-Strauss syndrome (rare, reported with steroid
tapering)
CLASS 6 · PAF BLOCKERS
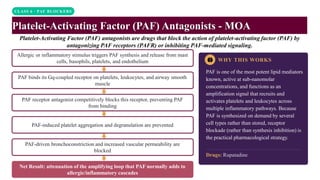
Platelet-Activating Factor (PAF) Antagonists - MOA
Platelet-Activating Factor (PAF) antagonists are drugs that block the action of platelet-activating factor (PAF) by
antagonizing PAF receptors (PAFR) or inhibiting PAF-mediated signaling.
WHY THIS WORKS
PAF is one of the most potent lipid mediators
known, active at sub-nanomolar
concentrations, and functions as an
amplification signal that recruits and
activates platelets and leukocytes across
multiple inflammatory pathways. Because
PAF is synthesized on demand by several
cell types rather than stored, receptor
blockade (rather than synthesis inhibition) is
the practical pharmacological strategy.
Drugs: Rupatadine
Allergic or inflammatory stimulus triggers PAF synthesis and release from mast
cells, basophils, platelets, and endothelium
PAF binds its Gq-coupled receptor on platelets, leukocytes, and airway smooth
muscle
PAF receptor antagonist competitively blocks this receptor, preventing PAF
from binding
PAF-induced platelet aggregation and degranulation are prevented
PAF-driven bronchoconstriction and increased vascular permeability are
blocked
Net Result: attenuation of the amplifying loop that PAF normally adds to
allergic/inflammatory cascades
CLASS 6 · PAF BLOCKERS
PAF Antagonists - Uses & Adverse Effects
Examples:- Rupatadine (dual PAF/H1 antagonist, clinically used); Modipafant, Apafant (investigational)
Therapeutic Uses
✦ Allergic rhinitis and chronic urticaria (rupatadine, via
combined PAF/H1 blockade)
✦ Investigational role in severe asthma
✦ Investigational role in sepsis and ischemia-reperfusion
injury
Adverse Effects
✦ Somnolence (mild, via residual H1 activity)
✦ Headache
✦ Fatigue
✦ Dry mouth (uncommon)
SYNTHESIS
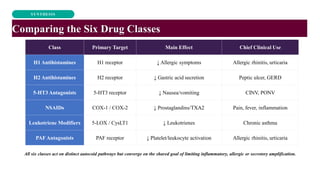
Comparing the Six Drug Classes
Class Primary Target Main Effect Chief Clinical Use
H1 Antihistamines H1 receptor ↓ Allergic symptoms Allergic rhinitis, urticaria
H2 Antihistamines H2 receptor ↓ Gastric acid secretion Peptic ulcer, GERD
5-HT3 Antagonists 5-HT3 receptor ↓ Nausea/vomiting CINV, PONV
NSAIDs COX-1 / COX-2 ↓ Prostaglandins/TXA2 Pain, fever, inflammation
Leukotriene Modifiers 5-LOX / CysLT1 ↓ Leukotrienes Chronic asthma
PAFAntagonists PAF receptor ↓ Platelet/leukocyte activation Allergic rhinitis, urticaria
All six classes act on distinct autocoid pathways but converge on the shared goal of limiting inflammatory, allergic or secretory amplification.
CLINICAL APPLICATION
Choosing the Right Drug
Allergic Rhinitis / Urticaria
Second-generation H1 antihistamine first-line; add
leukotriene modifier or rupatadine if refractory.
Peptic Ulcer / GERD
H2 antagonist for mild disease; proton pump inhibitors are
preferred for severe/erosive disease.
Chemotherapy-Induced Vomiting
5-HT3 antagonist ± NK1 antagonist and dexamethasone
for highly emetogenic regimens.
Pain, Fever, Inflammation
Non-selective NSAID for short-term use; COX-2 selective
agent if high GI bleeding risk.
Chronic / Allergic Asthma
Inhaled corticosteroid remains first-line; add leukotriene
modifier for allergen- or exercise-triggered symptoms.
Severe Allergic/Anaphylactic Reaction
Epinephrine is first-line; H1 (± H2) antihistamines are
adjuncts, not substitutes.
SAFETY
Monitoring & Precautions
✦ First-generation H1 antihistamines: caution with driving/operating machinery due to sedation; avoid in elderly (anticholinergic
burden)
✦ Cimetidine: review concurrent medications for CYP450-mediated interactions (e.g., warfarin, phenytoin)
✦ 5-HT3 antagonists: obtain baseline ECG in patients with cardiac risk factors before high-dose IV use (QT prolongation)
✦ NSAIDs: use lowest effective dose for shortest duration; co-prescribe a proton pump inhibitor in high GI-risk patients; monitor
renal function
✦ Zileuton: monitor liver function tests periodically; montelukast - counsel patients/families on mood and behavior changes
✦ Avoid NSAIDs in aspirin-sensitive asthma (risk of bronchospasm) and in the third trimester of pregnancy
✦ All patients: review for drug-allergy history before initiating any autocoid-related therapy
SUMMARY
Summary of Key Points
✦ Autocoids are locally-acting, rapidly-degraded endogenous mediators - histamine, serotonin, eicosanoids, kinins, and PAF - central
to allergy, inflammation, pain, and secretory physiology
✦ Six major drug classes act on distinct autocoid pathways: H1 and H2 antihistamines block histamine receptors; 5-HT3 antagonists
block serotonin receptors; NSAIDs block the COX branch and leukotriene modifiers block the 5-LOX branch of the arachidonic
acid cascade; PAF antagonists block a separate potent phospholipid mediator
✦ Understanding each mediator's receptor and signaling pathway explains both the therapeutic benefit and the characteristic adverse-
effect profile of each drug class
✦ NSAIDs and leukotriene modifiers are complementary, not redundant, because they target parallel branches of the same
arachidonic acid cascade
✦ Drug selection should always be guided by the specific clinical indication, the patient's risk profile, and appropriate monitoring
Thank You