Comprehensive Overview of Antihypertensive Drugs and Hypertension Management
This presentation provides a comprehensive and easy-to-understand overview of Hypertension (High Blood Pressure) and the pharmacology of antihypertensive drugs. It is designed for Pharmacy, Medical, Nursing, and Allied Health Science students, as well as healthcare professionals preparing for competitive examinations.
Comprehensive Overview of Antihypertensive Drugs and Hypertension Management
1.
Antihypertensive Drugs
Mr. SATENDRAPRADHAN
Assistant Professor
Department of Pharmacology
COP, SVITS, Bilaspur
Ms. MANISHA SAHU
Assistant Professor
Department of Pharmacology
SCCP, Rajnandgaon
2.
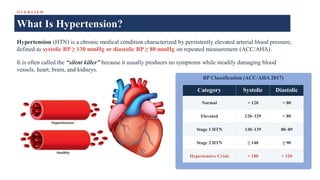
O V ER V IE W
What Is Hypertension?
Hypertension (HTN) is a chronic medical condition characterized by persistently elevated arterial blood pressure,
defined as systolic BP ≥ 130 mmHg or diastolic BP ≥ 80 mmHg on repeated measurement (ACC/AHA).
It is often called the “silent killer” because it usually produces no symptoms while steadily damaging blood
vessels, heart, brain, and kidneys.
BP Classification (ACC/AHA 2017)
Category Systolic Diastolic
Normal < 120 < 80
Elevated 120–129 < 80
Stage 1 HTN 130–139 80–89
Stage 2 HTN ≥ 140 ≥ 90
Hypertensive Crisis > 180 > 120
3.
B A CKG R O U N D
Epidemiology & Risk Factors
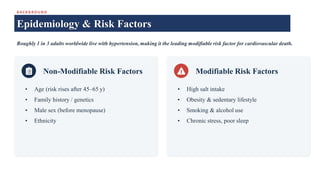
Roughly 1 in 3 adults worldwide live with hypertension, making it the leading modifiable risk factor for cardiovascular death.
Non-Modifiable Risk Factors
• Age (risk rises after 45–65 y)
• Family history / genetics
• Male sex (before menopause)
• Ethnicity
Modifiable Risk Factors
• High salt intake
• Obesity & sedentary lifestyle
• Smoking & alcohol use
• Chronic stress, poor sleep
4.
P A TH O P H Y S I O L O G Y
What Determines Blood Pressure?
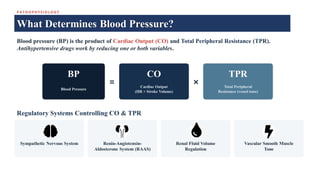
Blood pressure (BP) is the product of Cardiac Output (CO) and Total Peripheral Resistance (TPR).
Antihypertensive drugs work by reducing one or both variables.
BP
Blood Pressure
=
CO
Cardiac Output
(HR × Stroke Volume)
×
TPR
Total Peripheral
Resistance (vessel tone)
Regulatory Systems Controlling CO & TPR
Sympathetic Nervous System Renin-Angiotensin-
Aldosterone System (RAAS)
Renal Fluid Volume
Regulation
Vascular Smooth Muscle
Tone
5.
CO N SE Q U E N CE S
Untreated Hypertension: Target-Organ Damage
Brain
• Stroke
• Transient Ischemic Attack
• Vascular Dementia
Heart
• Left ventricular hypertrophy
• Heart failure
• CoronaryArtery Disease
• Myocardial Infraction
Kidneys
• Nephrosclerosis
• Chronic Kidney Disease
• Renal Failure
Eyes
• Hypertensive Retinopathy
• Vision Loss
Arteries
• Atherosclerosis
• Aortic Aneurysm/Dissection
• Peripheral Artery Disease
Sexual/Other
• Erectile Dysfunction
• Cognitive Decline
6.
P H AR M A CO L O G Y
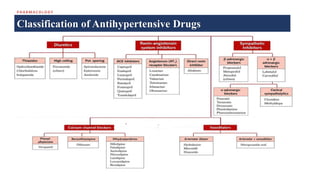
Classification of Antihypertensive Drugs
7.
P H AR M A CO L O G Y
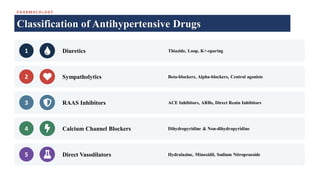
Classification of Antihypertensive Drugs
1 Diuretics Thiazide, Loop, K+-sparing
2 Sympatholytics Beta-blockers, Alpha-blockers, Central agonists
3 RAAS Inhibitors ACE Inhibitors, ARBs, Direct Renin Inhibitors
4 Calcium Channel Blockers Dihydropyridine & Non-dihydropyridine
5 Direct Vasodilators Hydralazine, Minoxidil, Sodium Nitroprusside
8.
M E CHA N I S M
Where Each Drug Class Acts
BLOOD PRESSURE = CO × TPR
↓ Cardiac Output ↓ Peripheral Resistance
Beta-Blockers
↓ HR & contractility
Diuretics
↓ Blood volume/preload
ACE Inhibitors / ARBs
↓ Angiotensin II action
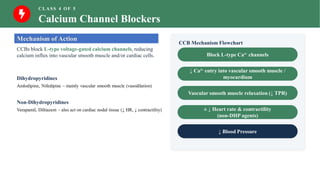
Calcium Channel Blockers
Vascular smooth muscle relax.
Direct Vasodilators / Alpha-Blockers
Direct/receptor-mediated relax.
7
9.
CLASS 1 OF5
Diuretics
Mechanism of Action
Diuretics lower BP primarily by reducing plasma &
extracellular fluid volume, which decreases venous return,
cardiac output, and (with chronic use) peripheral resistance.
Thiazide (e.g. Hydrochlorothiazide)
Inhibits Na⁺/Cl⁻ co-transporter in the distal convoluted tubule
Loop (e.g. Furosemide)
Inhibits Na⁺/K⁺/2Cl⁻ co-transporter in the thick ascending loop of Henle
K⁺-Sparing (e.g. Spironolactone)
Blocks aldosterone receptor / ENaC channels in the collecting duct
Diuretic Action Flowchart
Block Na⁺ / fluid reabsorption in renal tubule
↑ Na⁺ & water excretion in urine
↓ Extracellular & plasma volume
↓ Venous return → ↓ Cardiac output
↓ Blood Pressure
10.
CLASS 1 OF5
Diuretics
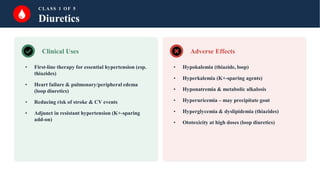
Clinical Uses
• First-line therapy for essential hypertension (esp.
thiazides)
• Heart failure & pulmonary/peripheral edema
(loop diuretics)
• Reducing risk of stroke & CV events
• Adjunct in resistant hypertension (K+-sparing
add-on)
Adverse Effects
• Hypokalemia (thiazide, loop)
• Hyperkalemia (K+-sparing agents)
• Hyponatremia & metabolic alkalosis
• Hyperuricemia – may precipitate gout
• Hyperglycemia & dyslipidemia (thiazides)
• Ototoxicity at high doses (loop diuretics)
11.
CLASS 2 OF5
Beta-Blockers
Mechanism of Action
Beta-blockers competitively antagonize β1-adrenergic
receptors in the heart and juxtaglomerular apparatus,
blunting sympathetic drive.
Cardioselective (β1)
Atenolol, Metoprolol, Bisoprolol
Non-selective (β1 & β2)
Propranolol, Nadolol
Combined α/β blockers
Carvedilol, Labetalol
Beta-Blockade Flowchart
Block β1 receptors in heart & kidney
↓ Heart rate & contractility
↓ Renin release from JG cells
↓ Cardiac Output & ↓ RAAS activity
↓ Blood Pressure
12.
CLASS 2 OF5
Beta-Blockers
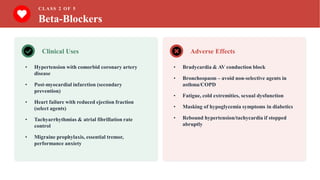
Clinical Uses
• Hypertension with comorbid coronary artery
disease
• Post-myocardial infarction (secondary
prevention)
• Heart failure with reduced ejection fraction
(select agents)
• Tachyarrhythmias & atrial fibrillation rate
control
• Migraine prophylaxis, essential tremor,
performance anxiety
Adverse Effects
• Bradycardia & AV conduction block
• Bronchospasm – avoid non-selective agents in
asthma/COPD
• Fatigue, cold extremities, sexual dysfunction
• Masking of hypoglycemia symptoms in diabetics
• Rebound hypertension/tachycardia if stopped
abruptly
13.
CLASS 3 OF5
ACE Inhibitors
Mechanism of Action
ACE inhibitors block Angiotensin-Converting Enzyme,
preventing conversion of Angiotensin I to the potent
vasoconstrictor Angiotensin II, and reducing bradykinin
breakdown.
Examples:
Enalapril, Lisinopril, Ramipril, Captopril
Note: ↑ Bradykinin contributes to the characteristic dry cough and
angioedema risk unique to this class.
RAAS Blockade Flowchart
Renin converts Angiotensinogen → Angiotensin I
ACE Inhibitors block conversion to Angiotensin II
↓ Vasoconstriction & ↓ Aldosterone secretion
↓ Peripheral resistance & ↓ Na⁺/water retention
↓ Blood Pressure
14.
CLASS 3 OF5
ACE Inhibitors
Clinical Uses
• First-line in hypertension with diabetes
(renoprotective)
• Heart failure with reduced ejection fraction
• Post-MI left ventricular dysfunction
• Diabetic & non-diabetic chronic kidney disease (↓
proteinuria)
Adverse Effects
• Dry, persistent cough (bradykinin-mediated)
• Angioedema – rare but potentially life-
threatening
• Hyperkalemia
• Acute kidney injury in bilateral renal artery
stenosis
• Contraindicated in pregnancy (fetotoxic)
15.
CLASS 3 OF5
Angiotensin Receptor Blockers (ARBs)
Mechanism of Action
ARBs directly block the AT₁ receptor, preventing Angiotensin
II from binding – regardless of how it was formed. Bradykinin
metabolism is unaffected, so cough is far less common than with
ACE inhibitors.
Examples:
Losartan, Valsartan, Telmisartan, Candesartan
ARB Mechanism Flowchart
Angiotensin II is formed
(via ACE or alternate pathways)
ARBs block AT₁ receptors on vascular smooth
muscle
Angiotensin II cannot exert vasoconstrictor
effect
↓ Vasoconstriction & ↓ Aldosterone release
↓ Blood Pressure
16.
CLASS 3 OF5
Angiotensin Receptor Blockers (ARBs)
Clinical Uses
• Hypertension – preferred when ACE inhibitors
cause cough
• Diabetic nephropathy (renoprotective)
• Heart failure (ACE-I intolerant patients)
• Stroke risk reduction in high-risk patients
Adverse Effects
• Hyperkalemia
• Hypotension, dizziness
• Acute kidney injury in renal artery stenosis
• Contraindicated in pregnancy (fetotoxic)
• Angioedema – rare (much less than ACE
inhibitors)
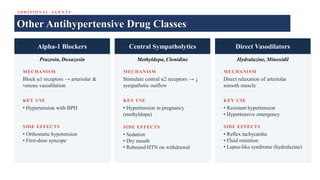
A D DIT IO N A L A G E N T S
Other Antihypertensive Drug Classes
Alpha-1 Blockers
Prazosin, Doxazosin
MECHANISM
Block α1 receptors → arteriolar &
venous vasodilation
KEY USE
• Hypertension with BPH
SIDE EFFECTS
• Orthostatic hypotension
• First-dose syncope
Central Sympatholytics
Methyldopa, Clonidine
MECHANISM
Stimulate central α2 receptors → ↓
sympathetic outflow
KEY USE
• Hypertension in pregnancy
(methyldopa)
SIDE EFFECTS
• Sedation
• Dry mouth
• Rebound HTN on withdrawal
Direct Vasodilators
Hydralazine, Minoxidil
MECHANISM
Direct relaxation of arteriolar
smooth muscle
KEY USE
• Resistant hypertension
• Hypertensive emergency
SIDE EFFECTS
• Reflex tachycardia
• Fluid retention
• Lupus-like syndrome (hydralazine)
20.
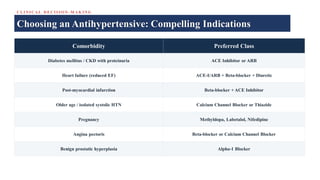
C L INIC A L D E C IS IO N - M A K IN G
Choosing an Antihypertensive: Compelling Indications
Comorbidity Preferred Class
Diabetes mellitus / CKD with proteinuria ACE Inhibitor or ARB
Heart failure (reduced EF) ACE-I/ARB + Beta-blocker + Diuretic
Post-myocardial infarction Beta-blocker + ACE Inhibitor
Older age / isolated systolic HTN Calcium Channel Blocker or Thiazide
Pregnancy Methyldopa, Labetalol, Nifedipine
Angina pectoris Beta-blocker or Calcium Channel Blocker
Benign prostatic hyperplasia Alpha-1 Blocker
21.
SUM M ARY
KeyTakeaways
Hypertension is defined & staged by BP thresholds (≥130/80 mmHg), and is a major driver of stroke, MI, heart
failure, and CKD.
Five major drug classes – Diuretics, Beta-blockers, ACE-I/ARBs, CCBs, and Vasodilators – lower BP by reducing
cardiac output and/or peripheral resistance.
RAAS inhibitors (ACE-I, ARBs) are preferred in diabetes & CKD; CCBs/thiazides favored in older adults; beta-
blockers favored post-MI or with CAD.
Each class carries characteristic adverse effects – know them to anticipate, monitor, and manage therapy safely.
Most patients ultimately require combination therapy to achieve BP control.