Comprehensive Overview of Anti-Diabetic Drugs and Insulin Therapies
Detailed insights into insulin types, delivery systems, and non-insulin antidiabetic drugs including mechanisms, effects, dosages, and adverse reactions for effective diabetes management.
INSULIN PREPARATIONS
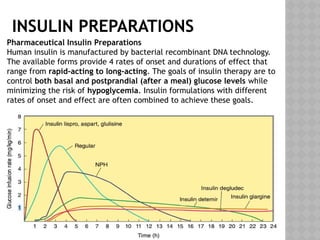
Pharmaceutical InsulinPreparations
Human insulin is manufactured by bacterial recombinant DNA technology.
The available forms provide 4 rates of onset and durations of effect that
range from rapid-acting to long-acting. The goals of insulin therapy are to
control both basal and postprandial (after a meal) glucose levels while
minimizing the risk of hypoglycemia. Insulin formulations with different
rates of onset and effect are often combined to achieve these goals.
12.
1. RAPID-ACTING
Three insulinanalogs:
insulin lispro,
insulin aspart,
insulin glulisine
have rapid onsets and early peaks of activity that permit
control of postprandial glucose levels. The 3 rapid-acting
insulins have small alterations in their primary amino acid
sequences that speed their entry into the circulation
without affecting their interaction with the insulin
receptor. The rapid-acting insulins are injected
immediately before a meal and are the preferred insulin
for continuous subcutaneous infusion devices. They also
can be used for emergency treatment of uncomplicated
diabetic ketoacidosis.
Adverse effects:
Hypoglycemia: dizziness, headache, hunger,
sweating, weakness, irritability, tremors, increased
heart rate, rapid breathing, blurred vision, trouble
concentrating, and loss of consciousness.
Inflammation at the site of injection
Increased appetite
Dosage:
With meals: The dosage for rapid-
acting insulin taken with a meal
typically is based on a ration of insulin
to carbohydrates in that meal—most
commonly, one unit of insulin per 12 to
15 grams of carbs.
To bring down overly high glucose
levels: In general, one unit of rapid-
acting insulin is needed to lower blood
sugar by 50 mg/dl.
13.
2. SHORT-ACTING
Regular insulinis used intravenously in emergencies (eg,
diabetic ketoacidosis) or administered subcutaneously in
ordinary maintenance regimens, alone or mixed with
intermediate- or long-acting preparations. Before the
development of rapid-acting insulins, it was the primary form of
insulin used for controlling postprandial glucose concentrations,
but it requires administration 1 h or more before a meal.
Adverse effects
common
Bumps, pits, swelling, redness or itching at the injection
site.
Muscle pain.
Weight gain.
Swelling of your arms and legs
Low blood sugar (hypoglycemia)
Injection site reactions: redness, swelling, itching
Serious
Severe low blood sugar.
Low blood potassium (hypokalemia)
Serious allergic reaction
Heart failure
Dosage:
Child dosage (ages 0–17 years)
- between 0.7 and 1 unit/kg per
day.
Adult dosage (ages 18–64 years)
- between 0.2 and 0.4 unit/kg
per day.
Senior dosage (ages 65 years and
older)
- lower dosage so that too much
of this drug doesn’t build up in
the body
14.
3. INTERMEDIATE-ACTING
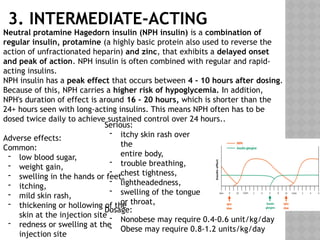
Neutral protamineHagedorn insulin (NPH insulin) is a combination of
regular insulin, protamine (a highly basic protein also used to reverse the
action of unfractionated heparin) and zinc, that exhibits a delayed onset
and peak of action. NPH insulin is often combined with regular and rapid-
acting insulins.
NPH insulin has a peak effect that occurs between 4 - 10 hours after dosing.
Because of this, NPH carries a higher risk of hypoglycemia. In addition,
NPH's duration of effect is around 16 - 20 hours, which is shorter than the
24+ hours seen with long-acting insulins. This means NPH often has to be
dosed twice daily to achieve sustained control over 24 hours..
Adverse effects:
Common:
- low blood sugar,
- weight gain,
- swelling in the hands or feet,
- itching,
- mild skin rash,
- thickening or hollowing of the
skin at the injection site
- redness or swelling at the
injection site
Dosage:
- Nonobese may require 0.4-0.6 unit/kg/day
- Obese may require 0.8-1.2 units/kg/day
Serious:
- itchy skin rash over
the
entire body,
- trouble breathing,
- chest tightness,
- lightheadedness,
- swelling of the tongue
or throat,
15.
4. LONG-ACTING
Insulinglargine,
insulin detemir,
insulin degludec
modified forms of human insulin that provide a peakless basal insulin level lasting more than 20 h,
which helps control basal glucose levels without producing hypoglycemia.
Adverse Effects:
low blood sugar (hypoglycemia): dizziness, Chills, blurred vision, Weakness, Headache,
fainting
pain, redness, or swelling at the injection site
insulin with thiazolidinediones increases the risk of fluid retention and heart failure.
Degludec: precautions may be necessary because of its long effect in the body
Dosage:
0.5 to 1.0 unit per kg per day. It can be administered once daily at bedtime or, ideally, twice daily
in addition to another type of insulin
16.
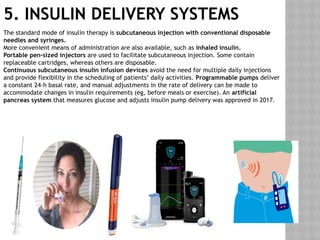
5. INSULIN DELIVERYSYSTEMS
The standard mode of insulin therapy is subcutaneous injection with conventional disposable
needles and syringes.
More convenient means of administration are also available, such as inhaled insulin.
Portable pen-sized injectors are used to facilitate subcutaneous injection. Some contain
replaceable cartridges, whereas others are disposable.
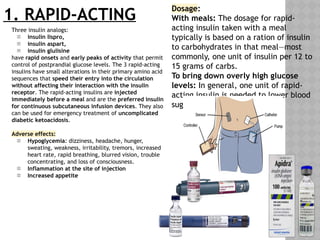
Continuous subcutaneous insulin infusion devices avoid the need for multiple daily injections
and provide flexibility in the scheduling of patients’ daily activities. Programmable pumps deliver
a constant 24-h basal rate, and manual adjustments in the rate of delivery can be made to
accommodate changes in insulin requirements (eg, before meals or exercise). An artificial
pancreas system that measures glucose and adjusts insulin pump delivery was approved in 2017.
17.
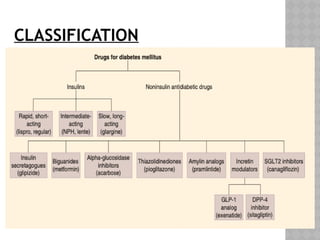
NON-INSULIN ANTIDIABETIC DRUGS
Severalgroups of oral antidiabetic drugs are used most commonly
to treat type 2 diabetes. These include
1. insulin secretagogues, (1*)
2. the biguanide metformin,
3. thiazolidinediones,
4. Incretins,
5. Alpha glucosidase inhibitors (2*)
6. renal glucose reuptake inhibitors (2*)
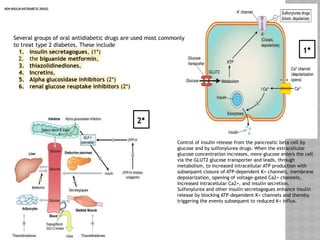
Control of insulin release from the pancreatic beta cell by
glucose and by sulfonylurea drugs. When the extracellular
glucose concentration increases, more glucose enters the cell
via the GLUT2 glucose transporter and leads, through
metabolism, to increased intracellular ATP production with
subsequent closure of ATP-dependent K+ channels, membrane
depolarization, opening of voltage-gated Ca2+ channels,
increased intracellular Ca2+, and insulin secretion.
Sulfonylurea and other insulin secretagogues enhance insulin
release by blocking ATP-dependent K+ channels and thereby
triggering the events subsequent to reduced K+ influx.
1*
2*
18.
SECRETAGOGUES
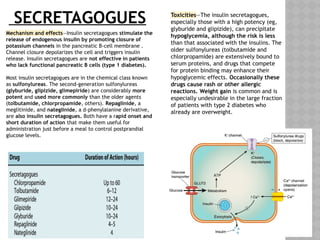
Mechanism and effects—Insulinsecretagogues stimulate the
release of endogenous insulin by promoting closure of
potassium channels in the pancreatic B-cell membrane .
Channel closure depolarizes the cell and triggers insulin
release. Insulin secretagogues are not effective in patients
who lack functional pancreatic B cells (type 1 diabetes).
Most insulin secretagogues are in the chemical class known
as sulfonylureas. The second-generation sulfonylureas
(glyburide, glipizide, glimepiride) are considerably more
potent and used more commonly than the older agents
(tolbutamide, chlorpropamide, others). Repaglinide, a
meglitinide, and nateglinide, a d-phenylalanine derivative,
are also insulin secretagogues. Both have a rapid onset and
short duration of action that make them useful for
administration just before a meal to control postprandial
glucose levels.
Toxicities—The insulin secretagogues,
especially those with a high potency (eg,
glyburide and glipizide), can precipitate
hypoglycemia, although the risk is less
than that associated with the insulins. The
older sulfonylureas (tolbutamide and
chlorpropamide) are extensively bound to
serum proteins, and drugs that compete
for protein binding may enhance their
hypoglycemic effects. Occasionally these
drugs cause rash or other allergic
reactions. Weight gain is common and is
especially undesirable in the large fraction
of patients with type 2 diabetes who
already are overweight.
19.
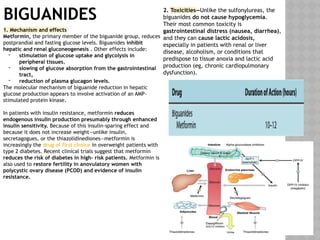
BIGUANIDES
1. Mechanism andeffects
Metformin, the primary member of the biguanide group, reduces
postprandial and fasting glucose levels. Biguanides inhibit
hepatic and renal gluconeogenesis . Other effects include:
- stimulation of glucose uptake and glycolysis in
peripheral tissues,
- slowing of glucose absorption from the gastrointestinal
tract,
- reduction of plasma glucagon levels.
The molecular mechanism of biguanide reduction in hepatic
glucose production appears to involve activation of an AMP-
stimulated protein kinase.
In patients with insulin resistance, metformin reduces
endogenous insulin production presumably through enhanced
insulin sensitivity. Because of this insulin-sparing effect and
because it does not increase weight—unlike insulin,
secretagogues, or the thiazolidinediones—metformin is
increasingly the drug of first choice in overweight patients with
type 2 diabetes. Recent clinical trials suggest that metformin
reduces the risk of diabetes in high- risk patients. Metformin is
also used to restore fertility in anovulatory women with
polycystic ovary disease (PCOD) and evidence of insulin
resistance.
2. Toxicities—Unlike the sulfonylureas, the
biguanides do not cause hypoglycemia.
Their most common toxicity is
gastrointestinal distress (nausea, diarrhea),
and they can cause lactic acidosis,
especially in patients with renal or liver
disease, alcoholism, or conditions that
predispose to tissue anoxia and lactic acid
production (eg, chronic cardiopulmonary
dysfunction).
21.
THIAZOLIDINEDIONES
Mechanism and effects—
Thethiazolidinediones, rosiglitazone and
pioglitazone, increase target tissue sensitivity to
insulin by activating the peroxisome proliferator-
activated receptor-gamma nuclear receptor (PPAR-γ
receptor). This nuclear receptor regulates the
transcription of genes encoding proteins involved in
carbohydrate and lipid metabolism. A primary effect
of the thiazolidinediones is increasing glucose uptake
in muscle and adipose tissue. They also inhibit
hepatic gluconeogenesis and have effects on lipid
metabolism and the distribution of body fat.
Thiazolidinediones reduce both fasting and
postprandial hyperglycemia. They are used as
monotherapy or in combination with insulin or other
oral antidiabetic drugs. Like metformin, the
thiazolidinediones have been shown to reduce the risk
of diabetes in high-risk patients. Pioglitazone also
lowers triglycerides and increases HDL.
Toxicities
When these drugs are used alone,
hypoglycemia is extremely rare.
Thiazolidinediones can cause fluid
retention, which presents as mild anemia
and edema and may increase the risk of
heart failure. Recent data have linked
rosiglitazone to increased risk of
myocardial infarction. The original
thiazolidinedione (troglitazone) was
removed from the market in several
countries because of hepatotoxicity.
Rosiglitazone and pioglitazone have not
been linked to serious liver dysfunction
but still require routine monitoring of
liver function. Female patients taking
thiazolidinediones appear to have an
increased risk of bone fractures.
Pioglitazone and troglitazone induce
cytochrome P450 activity (especially the
CYP3A4 isozyme) and can reduce the
serum concentrations of drugs that are
metabolized by these enzymes (eg, oral
contraceptives, cyclosporine).