Comprehensive Nursing Management of Hypertension in Adult Patients
Detailed overview of hypertension including pathophysiology, classification, risk factors, clinical presentation, diagnosis, and nursing management strategies for adult patients.
Comprehensive Nursing Management of Hypertension in Adult Patients
1.
ADULT HEALTH NURSING(NUR 232)
LEVEL II
HIGHER DIPLOMA IN GENERAL NURSING
• UNITVI
• Nursing Management Of Clients With Alterations In Cardio-vascular Function.
HYPERTENSION
Lesole. Isaac,
2.
INTRODUCTION
• "Hypertension isthe leading preventable cause of cardiovascular disease worldwide.“
• Otherwise known as “THE SILENT KILLER”
• Usually produces no symptoms
• Most people are unaware they have it
• Many patients with hypertension feel "fine" despite elevated readings
3.
GENERAL OBJECTIVE
By theend of this session, students will be able to understand the comprehensive concepts
of hypertension in adult patients, including its pathophysiology, clinical presentation,
diagnostic criteria, and evidence-based management strategies, in order to apply this
knowledge effectively in nursing practice.
4.
LEARNING OBJECTIVES
By theend of this session, students will be able to:
Review the anatomy and physiology of the cardiovascular system
Define hypertension and understand its classification
Identify the etiology, risk factors, and causes of hypertension
Explain the pathophysiology of hypertension
Recognize clinical manifestations and complications
Describe diagnostic approaches and management strategies
Apply nursing interventions for patients with hypertension
5.
REVIEW OF ANATOMYAND PHYSIOLOGY -THE HEART
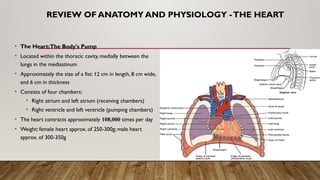
• The Heart:The Body's Pump
• Located within the thoracic cavity, medially between the
lungs in the mediastinum
• Approximately the size of a fist: 12 cm in length, 8 cm wide,
and 6 cm in thickness
• Consists of four chambers:
• Right atrium and left atrium (receiving chambers)
• Right ventricle and left ventricle (pumping chambers)
• The heart contracts approximately 108,000 times per day
• Weight: female heart approx. of 250-300g; male heart
approx. of 300-350g
6.
REVIEW OF ANATOMYAND PHYSIOLOGY - CIRCULATION
Pulmonary and Systemic Circuits
• Pulmonary Circuit:
• Right ventricle pulmonary arteries lungs (gas exchange) pulmonary veins left
→ → → →
atrium
Systemic Circuit:
• Left ventricle aorta body tissues superior/inferior vena cava right atrium
→ → → →
7.
REVIEW OF ANATOMYAND PHYSIOLOGY - BLOOD PRESSURE
Understanding Blood Pressure
Definition:
• Blood pressure is the force exerted by circulating blood on the walls of the arteries
Two Components:
Systolic BP (SBP): Maximum pressure when the heart contracts and pumps blood
Diastolic BP (DBP): Minimum pressure when the heart relaxes and fills with blood
Measurement:
Expressed in millimeters of mercury (mmHg)
Normal resting BP: 100-140 mmHg systolic and 60-90 mmHg diastolic
8.
DEFINITION OF HYPERTENSION
•Hypertension (HTN) is a chronic medical condition characterized
by persistently elevated arterial blood pressure.
According to the 2024 European Society of Cardiology (ESC) Guidelines:
"Hypertension is defined as systolic blood pressure of ≥140 mmHg and/or a diastolic
blood pressure of ≥90 mmHg, confirmed by repeated measurements.”
9.
ETIOLOGY OF HYPERTENSION
Primary(Essential) Hypertension (90-95% of cases) :
• No identifiable cause
Results from complex interaction of genetic and environmental factors
Develops gradually over many years
Secondary Hypertension (5-10% of cases) :
• Has an identifiable underlying cause
Often results from another systemic disease, usually nephrological or endocrine
10.
SPECIFIC CAUSES -PRIMARY HYPERTENSION
Causes and Contributing Factors in Primary Hypertension
Lifestyle Factors:
High salt intake
High saturated fat intake
Physical inactivity/sedentary lifestyle
Heavy alcohol consumption
Smoking
11.
SPECIFIC CAUSES -PRIMARY
HYPERTENSION
Metabolic Factors:
Obesity
Insulin resistance (common in obesity and metabolic syndrome)
Other Factors:
Stress and emotional factors
Low birth weight and early-life factors
SPECIFIC CAUSES -SECONDARY
HYPERTENSION
Other Causes:
• Obstructive sleep apnea
• Coarctation of the aorta
• Pregnancy (gestational hypertension)
• Certain medications (NSAIDs, oral contraceptives, corticosteroids)
15.
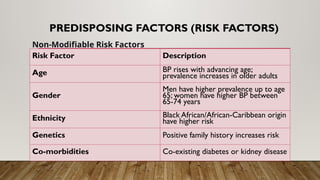
PREDISPOSING FACTORS (RISKFACTORS)
Risk Factor Description
Age BP rises with advancing age;
prevalence increases in older adults
Gender
Men have higher prevalence up to age
65; women have higher BP between
65-74 years
Ethnicity Black African/African-Caribbean origin
have higher risk
Genetics Positive family history increases risk
Co-morbidities Co-existing diabetes or kidney disease
Non-Modifiable Risk Factors
16.
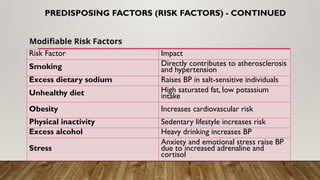
PREDISPOSING FACTORS (RISKFACTORS) - CONTINUED
Risk Factor Impact
Smoking Directly contributes to atherosclerosis
and hypertension
Excess dietary sodium Raises BP in salt-sensitive individuals
Unhealthy diet High saturated fat, low potassium
intake
Obesity Increases cardiovascular risk
Physical inactivity Sedentary lifestyle increases risk
Excess alcohol Heavy drinking increases BP
Stress
Anxiety and emotional stress raise BP
due to increased adrenaline and
cortisol
Modifiable Risk Factors
17.
INCIDENCE AND PREVALENCE
GlobalBurden:
• Affects approximately 1 in 3 adults aged 30-79 years worldwide
• Approximately 1.28 billion adults aged 30 to 79 years worldwide are living with hypertension.
• Contributes to over 10 million deaths annually worldwide
• The prevalence of hypertension rises markedly with age. In many countries, more than 50% of
adults aged 60 years and older have hypertension. Prevalence is also increasing in sub
Saharan Africa because of population ageing, urbanisation, unhealthy dietary patterns, obesity,
and reduced physical activity
18.
INCIDENCE AND PREVALENCE
Epidemiologicalmeasure Current estimate
Adults living with hypertension worldwide Approximately 1.28 billion
Age group most affected 30 to 79 years
Proportion in low and middle income countries About 66%
Adults unaware of their hypertension Approximately 46%
Adults receiving treatment Approximately 42%
Adults with controlled hypertension Approximately 21%
Global Epidemiological Summary
CLASSIFICATION OF BPIN ADULTS – BY
CAUSE
By Cause:
• Primary (Essential) - 90-95% of cases
• Secondary - 5-10% of case
21.
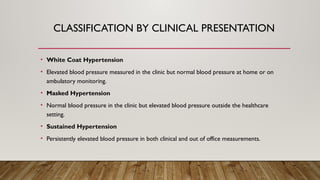
CLASSIFICATION BY CLINICALPRESENTATION
• White Coat Hypertension
• Elevated blood pressure measured in the clinic but normal blood pressure at home or on
ambulatory monitoring.
• Masked Hypertension
• Normal blood pressure in the clinic but elevated blood pressure outside the healthcare
setting.
• Sustained Hypertension
• Persistently elevated blood pressure in both clinical and out of office measurements.
22.
CLASSIFICATION BY CLINICALPRESENTATION
Resistant Hypertension
Blood pressure remains above target despite treatment with three antihypertensive
medications of different classes, including a diuretic, at optimal doses.
Refractory Hypertension
Blood pressure remains uncontrolled despite treatment with five or more
antihypertensive agents, including a long acting thiazide type diuretic (indapamide) and a
mineralocorticoid receptor antagonist like Spironolactone
23.
CLASSIFICATION BY SEVERITY
Ahypertensive crisis is a sudden, severe spike in blood pressure typically ≥
180/120 mm Hg. It is divided into two main categories depending on
whether the high blood pressure has caused acute damage to your body’s
vital organs
1. HYPERTENSIVE URGENCY
• Blood pressure usually ≥180/120 mmHg
No evidence of acute target organ damage
Requires prompt blood pressure reduction over hours
1. HYPERTENSIVE CRISIS
24.
CLASSIFICATION BY SEVERITY
11.HYPERTENSIVE EMERGENCY
Blood pressure usually ≥180/120 mmHg
Evidence of acute target organ damage, such as: Acute stroke ,Acute heart failure ,
Myocardial infarction ,Acute kidney injury ,Aortic dissection , Hypertensive
encephalopathy, Retinal haemorrhage or papilloedema
• Malignant Hypertension:A distinct clinical subset of a hypertensive emergency
distinguished by severe systemic microvascular injury (fibrinoid necrosis) and hallmark
retinal hemorrhages, exudates, or swelling of the optic nerve (papilledema).
25.
Classification Types
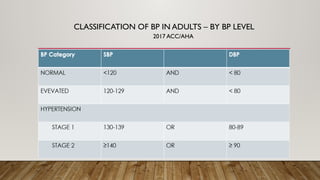
By bloodpressure level Normal, Elevated, Grade 1, Grade 2,
By cause Primary (Essential), Secondary
By clinical presentation White coat, Masked, Sustained, Resistant, Refractory
By severity Hypertensive urgency, Hypertensive emergency
SUMMARY OF CLASSIFICATIONS
26.
PATHOPHYSIOLOGY
• 1. Riskfactors
(Age, obesity, high salt intake, stress, diabetes, smoking etc )
• 2. Overactivation of the Sympathetic Nervous System (SNS)
• In many patients with hypertension, the sympathetic nervous system becomes
chronically overactive.This causes : Stimulation of renin release from the kidneys,
Peripheral vasoconstriction, Increased cardiac output …The sustained vasoconstriction
increases systemic vascular resistance, leading to persistent hypertension.
27.
PATHOPHYSIOLOGY
3. Activation ofthe Renin Angiotensin Aldosterone System (RAAS)
Reduced renal perfusion or increased sympathetic stimulation triggers the release of renin from the
juxtaglomerular cells of the kidneys.
The Step by Step RAAS Cascade:
• Renin converts angiotensinogen into angiotensin I.
• Angiotensin converting enzyme (ACE), converts angiotensin I into angiotensin II.
• Angiotensin II is a potent vasoconstrictor and stimulates aldosterone secretion from the adrenal cortex.
• Aldosterone promotes sodium and water reabsorption in the kidneys
The result is: Increased blood volume, Increased cardiac output, Increased systemic vascular resistance
and Persistent elevation of blood pressure
28.
PATHOPHYSIOLOGY
4. Renal SodiumandWater Retention
The kidneys regulate blood pressure by controlling sodium and water balance.
• When sodium excretion is impaired: Sodium accumulates in the body, water follows
sodium by osmosis, blood volume increases, cardiac output rises and blood pressure
increases.
Chronic volume expansion contributes significantly to sustained hypertension.
29.
PATHOPHYSIOLOGY
5. Endothelial Dysfunction
Thevascular endothelium normally produces substances that regulate vascular tone.
Vasodilator (Nitric oxide) & Vasoconstrictor (Endothelin).
In hypertension:
• Nitric oxide production decreases.
• Endothelin production increases.
Arteries remain chronically constricted.
This increases systemic vascular resistance.
30.
PATHOPHYSIOLOGY
6.Vascular Remodelling
• Persistenthigh blood pressure damages arterial walls.
Structural changes include:
• Smooth muscle hypertrophy
• Thickening of arterial walls
• Reduced arterial elasticity
• Narrowing of the vascular lumen
These changes further increase peripheral resistance and perpetuate hypertension.
31.
PATHOPHYSIOLOGY
7.Target Organ Damage(These are also complications)
Persistent hypertension damages several organs because of prolonged exposure to elevated
arterial pressure.
• Heart (Left ventricular hypertrophy, Coronary artery disease, Heart failure, Myocardial
infarction)
• Brain (Stroke ,Transient ischaemic attack, Hypertensive encephalopathy, Cognitive impairment)
• Kidneys (Chronic kidney disease, Hypertensive nephrosclerosis, Progressive renal failure)
32.
PATHOPHYSIOLOGY
7.Target Organ Damage( These are also complications)
• Eyes (Hypertensive retinopathy, Retinal haemorrhage, Papilloedema in severe
hypertension ,Visual impairment or blindness)
• BloodVessels (Atherosclerosis, Peripheral arterial disease,Aortic aneurysm ,Aortic
dissection)
33.
CLINICAL MANIFESTATION
• OftenAsymptomatic:
• Most people with hypertension experience no symptoms
• Blood pressure can be dangerously high without any warning signs
• May be discovered during routine health screening
• When Symptoms Occur,They May Include: , Blurred vision, dizziness, ear noise or
buzzing, irregular heartbeat, nocturia (frequent urination at night), nosebleed
DIAGNOSIS - HISTORY
HistoryTakingin Hypertension
Key History Components:
Personal History:
• Known chronic diseases (diabetes, CKD, CVD)
• Current medications (including OTC, herbal and traditional meds)
• Lifestyle factors (diet, exercise, smoking, alcohol)
Family History: ( Hypertension, Cardiovascular disease, Stroke, Renal disease)
36.
DIAGNOSIS - PHYSICALEXAMINATION
PHYSICAL EXAMINATION FOR HYPERTENSION
• Vital Signs:
• Accurate BP measurement in both arms.
• Heart rate and rhythm assessment
37.
DIAGNOSIS - PHYSICALEXAMINATION
• Physical Examination for Hypertension
• Cardiovascular:
• Palpate pulses
• Check for arrhythmias, especially atrial fibrillation
• Assess for signs of heart failure
• Abdominal:
• Check for masses
38.
DIAGNOSIS - INVESTIGATIONS
InvestigationDetails of the test
Blood tests HbA1c, electrolytes, creatinine,
eGFR
Lipid profile Total cholesterol and HDL
cholesterol
Urinalysis Proteinuria, haematuria
ECG (12-lead) Detect arrhythmias and left
ventricular hypertrophy
Fundoscopy Check for hypertensive
retinopathy
Recommended Investigations
39.
DIAGNOSIS - INVESTIGATIONS
Additionaltest include
• FBC
• Thyroid Function Test
• Cortisol levels
IMAGING – Abdominal ultrasound, KUB ultrasound, chest xray.
40.
PROGNOSIS
Hypertension is ahighly treatable condition
With EffectiveTreatment:
Significant reduction in cardiovascular events
Improved life expectancy
Reduced risk of stroke (40%), heart failure (50%), MI (25%)
Prevention of target organ damage progression
WithoutTreatment:
Progressive target organ damage
Increased morbidity and mortality
Shortened life expectancy
MANAGEMENT - PHARMACOLOGICALTREATMENT
Management- PharmacologicalTreatment
Step 1Treatment - Initiation
Who toTreat:
• All adults with persistent stage 2 hypertension (BP ≥160/100 mmHg)
• Stage 1 hypertension with risk factors (CVD, target organ damage, diabetes, or CVD risk ≥10%)
First-line Agents:
• ACE (Angiotensin-Converting Enzyme ) Inhibitors/ARBs ( Angiotensin II Receptor Blockers )
• Preferred for:
• People with type 2 diabetes
• People aged <55 years
• People with CKD
43.
MANAGEMENT - PHARMACOLOGICAL
TREATMENT
•Calcium Channel Blockers (CCBs):
• Preferred for:
• People aged ≥55 years
• People of Black African/African-Caribbean origin
• Thiazide-like Diuretics:
• Alternative if CCB not tolerated
• Indapamide preferred over conventional thiazides
44.
MANAGEMENT - PHARMACOLOGICALTREATMENT
StepwiseApproach to DrugTreatment
Step 2 (If BP not controlled on monotherapy):
• Add drug from a different class
• Example:ACEi/ARB + CCB or ACEi/ARB + thiazide-like diuretic
Step 3 (If BP not controlled on 2 drugs):
• Triple therapy:ACEi/ARB + CCB + thiazide-like diuretic
45.
MANAGEMENT - PHARMACOLOGICAL
TREATMENT
•Step 4 (Resistant Hypertension):
• BP not controlled on optimal doses of 3 drugs
• Add spironolactone (if K+ ≤4.5 mmol/L)
• Or alpha-blocker/beta-blocker
46.
NURSING MANAGEMENT -ASSESSMENT
Nursing Assessment of Hypertensive Patient
• Initial Assessment:
• Obtain accurate BP measurements
• Assess for signs of target organ damage
• Complete health history including risk factors
• Evaluate current symptoms or complications
47.
NURSING MANAGEMENT
Ongoing Monitoring:
•Vital signs at each visit
• Weight and BMI monitoring
• Adherence to medication regimen
• Review of lifestyle modifications
48.
NURSING MANAGEMENT
Health EducationAssessment:
• Patient's understanding of the condition
• Knowledge of treatment plan
• Awareness of complications
• Compliance with monitoring recommendations
49.
NURSING CARE PLANFOR A PATIENT WITH
HYPERTENSION
• PROBLEM 1
• Subjective: Patient complains of severe headache, dizziness, blurred vision or chest
discomfort. Objective: BP 180/120 mmHg or above, tachycardia, altered neurological status,
evidence of target organ damage.
• NURSING DIAGNOSIS : Ineffective Tissue Perfusion (Cerebral, Renal and Cardiac) related
to severely elevated systemic vascular resistance secondary to hypertensive crisis as evidenced
by BP ≥180/120 mmHg, headache, visual disturbances and altered neurological findings.
50.
NURSING CARE PLANFOR A PATIENT WITH
HYPERTENSION
INTERVENTIONS
Monitor blood pressure every 5 to 15 minutes during the acute phase.
Assess neurological status using Glasgow Coma Scale
Monitor urine output hourly.
Administer prescribed intravenous antihypertensives (e.g. labetalol).
Administer oxygen if indicated.
Prepare the patient for admission to a high dependency or intensive care unit if necessary.
51.
NURSING CARE PLANFOR A PATIENT WITH
HYPERTENSION
• Problem 2
Subjective: Patient complains of fatigue and decreased activity tolerance. Objective: BP above
140/90 mmHg
• NURSING DIAGNOSIS : Decreased Cardiac Output related to increased systemic vascular
resistance and impaired myocardial contractility secondary to uncontrolled hypertension as
evidenced by persistent blood pressure ≥140/90 mmHg, tachycardia, dyspnoea on exertion,
fatigue, diminished peripheral pulses, delayed capillary refill, and decreased activity tolerance.
52.
NURSING CARE PLANFOR A PATIENT WITH
HYPERTENSION
• Administer antihypertensive medications as prescribed, ensuring they are given at the
correct time and dose
• Assess for side effects and therapeutic effectiveness of medications.
• Monitor and document BP at prescribed intervals
• Monitor for signs of cardiac decompensation ( headache, shortness of breath) during
activity.
• Encourage periods of rest to reduce cardiac workload.
53.
NURSING CARE PLANFOR A PATIENT WITH
HYPERTENSION
Problem 3
• Patient consumes a high salt diet, is overweight, physically inactive and smokes cigarettes.
Blood pressure remains elevated despite medication.
• Nursing Diagnosis: Ineffective Health Maintenance related to unhealthy lifestyle
behaviours as evidenced by excessive sodium intake, sedentary lifestyle, obesity and
smoking.
54.
REFERENCES
• Colantonio, L.D.,Booth, J.N., Bress,A.P.,Whelton, P.K., Shimbo, D., Levitan, E.B., Howard, G., Safford, M.M. and Muntner, P.,
2018. 2017 ACC/AHA blood pressure treatment guideline recommendations and cardiovascular risk. Journal of the American
College of Cardiology, 72(11), pp.1187-1197.
• Hinkle, J.L. and Cheever, K.H. (2022) Brunner & Suddarth'sTextbook of Medical-Surgical Nursing. 15th edn. Philadelphia:Wolters
Kluwer.
• McEvoy, J.W., McCarthy, C.P., Bruno, R.M. et al. (2024) 2024 ESC Guidelines for the management of elevated blood pressure and
hypertension. European Heart Journal.Available at:
https://www.escardio.org/Guidelines/Clinical-Practice-Guidelines/Elevated-Blood-Pressure-and-Hypertension
• NANDA International (2024) NANDA International Nursing Diagnoses: Definitions and Classification 2024–2026. 13th edn. New
York:Thieme.
• Whelton, P.K., Carey, R.M.,Aronow,W.S. et al. (2018) 2017 ACC/AHA Guideline for the Prevention, Detection, Evaluation, and
Management of High Blood Pressure in Adults. Hypertension, 71(6), pp. e13 to e115.
https://doi.org/10.1161/HYP.0000000000000065
• World Health Organization (2025) Hypertension.Available at: https://www.who.int/news-room/fact-sheets/detail/hypertension



 Most read





 Most read