 FOGSI Representative to AOFOG –Asia Oceana
Federation of OB/GY
 FIGO Committee member for Climate Change and
Toxic Environmental Exposures (C2TE2) Committee
 Vice President National ISOPARB
 President –ISOPARB Vidarbha Chapter
 Chairperson Indian College of OB/GY 2022--2023
 National Corresponding Editor-JOGI 2018-2026
 National Corresponding Secretary- AMWI 2021-2026
 Member-SAFOG Education Committee
 Joint Secretary-Indian Menopause Society 2024
 Chairperson-Medical Education Committee IMS 21-23
 President-AMWN 2021-24
 President Menopause Society, Nagpur 2016-18
 Senior Vice President FOGSI 2012
 Chairperson HIV/AIDS Committee FOGSI 2007-09

 President Nagpur OB/GY Society 2005-06
Dr. Laxmi Shrikhande
MBBS; MD(OB/GY); FICOG;
FICMU; FICMCH; FIMS
Medical Director &
Senior Consultant -
Shrikhande Hospital &
Research Centre Pvt Ltd,
Nagpur, Maharashtra
Ph-9623459766
slaxmi2002@yahoo.com
 Fellow Hon. Causa by Royal
College of OB/GY, UK
 Nagpur Ratan Award at the
hands of Union Minister
Shri Nitinji Gadkari
 Received Bharat excellence
Award for women’s health
 Received appreciation letter
from Maharashtra
Government for her work in
the field of SAVE THE
GIRL CHILD
• Delivered 32 orations and
550 guest lectures
• Publications- 62 National &
31 International
• Conducted TOT for 1000
school teachers on
adolescent health issues
Awards
Positions
PMOS & Infertility
DR. LAXMI SHRIKHANDE
Medical Director-Shrikhande Fertility Clinic, Nagpur,
MBBS; MD(OB/GY); FICOG; FICMU; FIMS; FICMCH
PCOS and Infertility
 Polycystic Ovary Syndrome (PCOS) affects nearly 8–13% of women of
reproductive age worldwide and is responsible for almost 80% of
anovulatory infertility.
 Yet, PCOS is far more than an ovulation disorder.
 It is a complex endocrine and metabolic condition that influences
reproductive, metabolic, cardiovascular, and psychological health
throughout a woman's life.
PCOS and Infertility
Our goal is not merely to induce ovulation—it is to help every woman
achieve a healthy singleton pregnancy while safeguarding her lifelong
metabolic and reproductive health.
Algorithm
Step 1-Lifestyle intervention (3–6 months)
↓
Step 2-If ovulation does not occur
↓
Letrozole (first-line)
↓
Gonadotropins
↓
IVF
Lifestyle Modification in PCOS and Infertility
Current Guidelines (2023–2025)
 Lifestyle modification is the foundation of PCOS management and
should be recommended to all women with PCOS, irrespective of
BMI.
 It is the first-line intervention before ovulation induction and should
continue throughout fertility treatment.
Lifestyle Modification in PCOS and Infertility
Lifestyle intervention improves:
Ovulation
Endometrial receptivity
Oocyte quality
Pregnancy rates
Live birth
Response to letrozole
Response to gonadotropins
Lifestyle Modification in PCOS and Infertility
Components of Lifestyle Intervention
1. Healthy Nutrition- No single diet is superior.
Current guidelines recommend an individualized healthy eating pattern
that is:
 Calorie appropriate
 Nutritionally balanced
 Sustainable
Lifestyle Modification in PCOS and Infertility
2. Physical Activity
 At least 150–300 minutes/week of moderate-intensity aerobic
exercise
or
 75–150 minutes/week of vigorous exercise
PLUS
 Resistance training 2–3 days/week
Lifestyle Modification in PCOS and Infertility
3. Weight Reduction
 For overweight or obese women: Target: 5–10% weight loss
Benefits:
 ✓ Restoration of ovulation
 ✓ Improved menstrual regularity
 ✓ Reduced insulin resistance
 ✓ Lower androgen levels
 ✓ Improved pregnancy rates
 ✓ Better IVF outcomes
 Even 5% weight loss can significantly improve reproductive function.
Lifestyle Modification in PCOS and Infertility
4. Sleep Optimization
Recommend:
 7–9 hours of sleep/night
 Regular sleep schedule
 Screening for obstructive sleep apnea in obese women
Poor sleep worsens:
 Insulin resistance
 Weight gain
 Hyperandrogenism
Lifestyle Modification in PCOS and Infertility
5. Psychological Well-being
 Women with PCOS have higher rates of:
 Anxiety
 Depression
 Eating disorders
 Reduced quality of life
Guidelines recommend:
✔ Psychological assessment
✔ Cognitive behavioural therapy when indicated
✔ Stress reduction
✔ Mindfulness
Lifestyle Modification in PCOS and Infertility
6. Smoking & Alcohol
Advise:
 ✔ Smoking cessation
 ✔ Avoid vaping
 ✔ Limit alcohol
 Both adversely affect fertility and pregnancy outcomes.
Lifestyle Modification in PCOS and Infertility
Intervention Recommendation
Diet Mediterranean/DASH or any balanced healthy diet
Weight loss 5–10% of body weight (if overweight/obese)
Exercise 150–300 min/week moderate aerobic + resistance
training 2–3 days/week
Sleep 7–9 hours/night
Mental health
Screen and manage anxiety, depression, eating
disorders
Smoking Stop smoking and vaping
Alcohol Limit intake
Lifestyle Modification in PCOS and Infertility
• Avoid delaying fertility treatment unnecessarily in women of
advanced maternal age or diminished ovarian reserve;
• lifestyle optimization should occur alongside timely fertility
management.
Role of GLP-1 Receptor Agonists in PCOS and Infertility
Current Guideline Recommendations (2023)
 The 2023 International Evidence-Based Guideline for PCOS recommends that GLP-1 receptor
agonists may be considered, in addition to lifestyle intervention, for weight management in
adults with PCOS, following general obesity management recommendations.
Indications
 ✔ BMI ≥30 kg/m² or
 ✔ BMI ≥27 kg/m² with obesity-related comorbidities like-
 Prediabetes
 Type 2 diabetes
 Hypertension
 Dyslipidemia
 Obstructive sleep apnea
Role of GLP-1 Receptor Agonists in PCOS and Infertility
GLP-1 Receptor Agonists- Available Agents-
 Liraglutide (daily injection)
 Semaglutide (weekly injection)
 Dulaglutide (weekly injection)
 Tirzepatide (dual GIP/GLP-1 receptor agonist; promising but limited
PCOS-specific data)
Role of GLP-1 Receptor Agonists in PCOS and Infertility
Drug Suggested washout before conception*
Liraglutide At least 2 weeks
Semaglutide At least 2 months
Tirzepatide
At least 1 month (based on product
labeling/pharmacokinetics)
 Women should discontinue GLP-1 receptor agonists before conception
because pregnancy safety data are limited.
 Recommended washout periods:
*Follow the specific product label and local regulatory guidance.
Role of Bariatric Surgery in PCOS and Infertility
Current Guideline Recommendations
 Women with PCOS should be considered for bariatric surgery according to
general metabolic surgery guidelines, not solely because of infertility.
Eligibility
 ✔ BMI ≥40 kg/m² or
 ✔ BMI ≥35 kg/m² with obesity-related comorbidities
 Some guidelines also consider BMI 30–34.9 kg/m² in patients with
inadequately controlled type 2 diabetes after multidisciplinary evaluation.
Role of Bariatric Surgery in PCOS and
Infertility
Pregnancy After Bariatric Surgery--Delay conception
Current recommendations advise:
 Avoid pregnancy for 12–18 months after surgery (many experts recommend up to 24 months,
particularly after malabsorptive procedures).
Why?
 During rapid weight loss:
 Nutritional deficiencies
 Maternal catabolism
 Fetal growth concerns
 Greater risk of micronutrient deficiency
Role of Myo-Inositol in PCOS and Infertility
Myo-Inositol in PCOS: Current Evidence (2023–2025)
✔ May improve
 Insulin sensitivity
 Menstrual regularity
 Metabolic profile
 Possibly oocyte quality
✘ Evidence insufficient for
 Ovulation
 Clinical pregnancy
 Live birth
 Routine infertility treatment
Guideline message
 Can be considered based on patient preference and low risk.
 Not recommended as a routine fertility therapy.
Role of Myo-Inositol in PCOS and Infertility
Dose Used in Most Studies
 Although no specific formulation or dose is recommended by current
guidelines because of insufficient evidence.
Many commercial preparations combine:
 Myo-inositol + D-chiro-inositol in a 40:1 ratio, intended to mimic the
physiological plasma ratio.
 However, the guideline does not recommend one formulation or ratio
over another because evidence is inadequate.
Role of Metformin in Ovulation Induction and IUI
Current Guideline Recommendations
 Metabolic Benefits (Strong Recommendation)
 Metformin should be considered in women with PCOS, particularly
those with:
 BMI ≥25 kg/m² (may also benefit lean women)
 Insulin resistance
 Prediabetes
 Type 2 diabetes
 Metabolic syndrome
Role of Metformin in Ovulation Induction and IUI
Dose
 Start with 500 mg once daily with food
 Increase every 1–2 weeks according to tolerance.
 Maintenance Dose- 1500–2000 mg/day
Preconception Counselling
 Women with PCOS should be counselled on the adverse impact of
excess weight on clinical pregnancy, miscarriage, and live birth rates,
following infertility treatment.
 Chronic conditions, such as diabetes, high blood pressure, anxiety,
depression, and other mental health conditions, should be optimally
managed, and women should be counselled regarding the risk of
adverse pregnancy outcomes.
Preconception Care checklist:
BMI
HbA1c
Blood pressure
Thyroid
Folic acid
Vitamin D (if deficient)
Vaccination review
Smoking/alcohol cessation
Sleep apnea in obese women
Ovulation induction principles
 Pregnancy should be excluded prior to
ovulation induction.
 Unsuccessful, prolonged use of
ovulation induction agents should be
avoided, due to poor success rates.
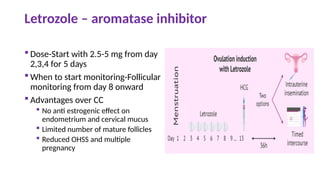
Letrozole – aromatase inhibitor
 Dose-Start with 2.5-5 mg from day
2,3,4 for 5 days
 When to start monitoring-Follicular
monitoring from day 8 onward
 Advantages over CC
 No anti estrogenic effect on
endometrium and cervical mucus
 Limited number of mature follicles
 Reduced OHSS and multiple
pregnancy
Second line
Gonadotrophins
LOD
Which Gonadotrophins in Non IVF cycles
 HMG
 Highly Purified HMG
 Urinary FSH
 Highly Purified FSH
 Recombinant FSH
Non IVF Gonadotrophin cycles – what should be the starting dose
 Age.
 Antral Follicle count.
 AMH
 Previous response.
Conventional gonadotropin protocol
 In this the starting dose of FSH is 150 international units/day.
 However, this regimen is associated with a multiple pregnancy rate of
up to 36%, and ovarian hyperstimulation occurs in up to 14% of
treatment cycles .
Fauser BC, Van Heusden
AM. Manipulation of human ovarian function: physiological concepts and clinical consequences.
Endocr Rev 1997; 18:71.
White DM, Polson DW, Kiddy D, et al. Induction of ovulation with low-dose gonadotropins in polycystic o
vary syndrome: an analysis of 109 pregnancies in 225 women. J
Clin Endocrinol Metab 1996; 81:3821.
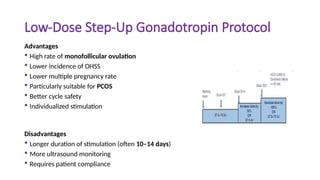
Low-Dose Step-Up Gonadotropin Protocol
 The low-dose step-up protocol is currently the preferred gonadotropin
regimen for women with PCOS and other high responders because it aims
to achieve monofollicular development, thereby minimizing the risks of
multiple pregnancy and ovarian hyperstimulation syndrome (OHSS).
Principle
 Start with a low dose of FSH and increase gradually only if there is no
ovarian response.
 This approach seeks to identify the individual's FSH threshold required for
follicular recruitment.
Low-Dose Step-Up Gonadotropin Protocol
Cycle Day Treatment Monitoring
Day 2–3 Baseline TVS ± AFC, exclude cysts
Record BMI, AMH, previous
response
Day 2/3 Start FSH 37.5–75 IU SC daily Continue same dose for 7 days
Day 7–8 First TVS (± serum E2 if needed) Assess follicular growth
If no follicle ≥10 mm Increase FSH by 25–37.5 IU/day Continue for another 7 days
Repeat every 7 days
Increase by 25–37.5 IU until
follicular growth begins
Avoid rapid dose escalation
Once follicle reaches 10–12 mm Maintain the same FSH dose Do not increase further
Trigger
hCG when 1–2 follicles reach 18–20
mm
Endometrium ≥7 mm
IUI 34–36 hours after trigger
Low-Dose Step-Up Gonadotropin Protocol
Advantages
 High rate of monofollicular ovulation
 Lower incidence of OHSS
 Lower multiple pregnancy rate
 Particularly suitable for PCOS
 Better cycle safety
 Individualized stimulation
Disadvantages
 Longer duration of stimulation (often 10–14 days)
 More ultrasound monitoring
 Requires patient compliance
Low-Dose Step-Down Gonadotropin Protocol
 The step-down protocol is designed to mimic the physiological decline in FSH
seen during a normal menstrual cycle.
 It begins with a higher FSH dose to recruit follicles and then reduces the dose
once a dominant follicle is established.
 Although effective, it is less commonly used than the low-dose step-up protocol
in women with PCOS because of a higher risk of multifollicular development and
OHSS.
 It may be considered in poor responders or women with a history of inadequate
response to low-dose stimulation.
Step up vs step down Gonadotropin Protocols
Feature Step-Up Step-Down
Starting dose 37.5–75 IU 150 IU
Dose change Gradually increase Gradually decrease
Best suited for PCOS, high responders
Poor responders, selected normo-
ovulatory women
Risk of OHSS Low Higher
Multiple pregnancy Lower Higher
Preferred for IUI Yes Selected cases only
Mild Ovarian Stimulation (MOS)
 Mild ovarian stimulation aims to recruit 1–3 mature follicles using the lowest
effective dose of ovulation induction agents, thereby maximizing safety while
maintaining acceptable pregnancy rates.
Candidates
 Young women with unexplained infertility
 Mild male factor infertility
 Minimal–mild endometriosis
 WHO Group II anovulation (PCOS after failure of oral agents)
 Women at increased risk of OHSS
 Couples preferring low-cost, low-burden treatment
Mild ovarian stimulation in IUI cycles
 Day 2–6-Letrozole 5 mg daily
 Day 7-TVS
 If the dominant follicle is <10 mm, start FSH 37.5–75 IU/day
 Day 10-TVS
 Continue or adjust FSH according to follicular growth
 Day 12-TVS
 Trigger when the leading follicle is 18–20 mm
 IUI 34–36 hours after hCG trigger
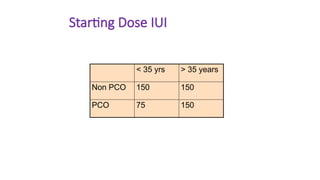
Starting Dose IUI
< 35 yrs > 35 years
Non PCO 150 150
PCO 75 150
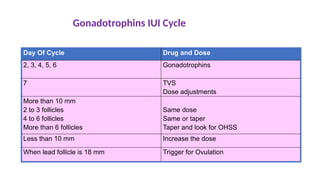
Gonadotrophins IUI Cycle
Day Of Cycle Drug and Dose
2, 3, 4, 5, 6 Gonadotrophins
7 TVS
Dose adjustments
More than 10 mm
2 to 3 follicles
4 to 6 follicles
More than 6 follicles
Same dose
Same or taper
Taper and look for OHSS
Less than 10 mm Increase the dose
When lead follicle is 18 mm Trigger for Ovulation
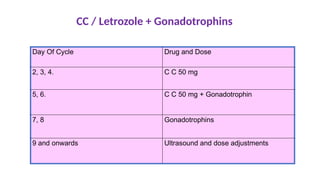
CC / Letrozole + Gonadotrophins
Day Of Cycle Drug and Dose
2, 3, 4. C C 50 mg
5, 6. C C 50 mg + Gonadotrophin
7, 8 Gonadotrophins
9 and onwards Ultrasound and dose adjustments
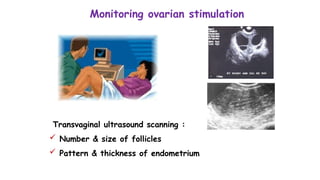
Monitoring ovarian stimulation
Transvaginal ultrasound scanning :
 Number & size of follicles
 Pattern & thickness of endometrium
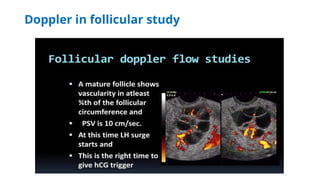
Doppler in follicular study
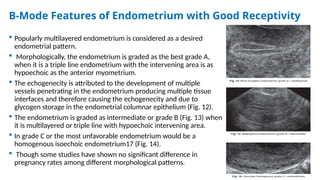
B-Mode Features of Endometrium with Good Receptivity
 Popularly multilayered endometrium is considered as a desired
endometrial pattern.
 Morphologically, the endometrium is graded as the best grade A,
when it is a triple line endometrium with the intervening area is as
hypoechoic as the anterior myometrium.
 The echogenecity is attributed to the development of multiple
vessels penetrating in the endometrium producing multiple tissue
interfaces and therefore causing the echogenecity and due to
glycogen storage in the endometrial columnar epithelium (Fig. 12).
 The endometrium is graded as intermediate or grade B (Fig. 13) when
it is multilayered or triple line with hypoechoic intervening area.
 In grade C or the most unfavorable endometrium would be a
homogenous isoechoic endometrium17 (Fig. 14).
 Though some studies have shown no significant difference in
pregnancy rates among different morphological patterns.
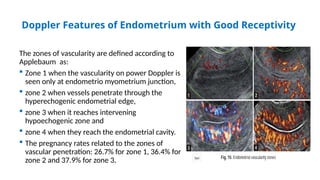
Doppler Features of Endometrium with Good Receptivity
The zones of vascularity are defined according to
Applebaum as:
 Zone 1 when the vascularity on power Doppler is
seen only at endometrio myometrium junction,
 zone 2 when vessels penetrate through the
hyperechogenic endometrial edge,
 zone 3 when it reaches intervening
hypoechogenic zone and
 zone 4 when they reach the endometrial cavity.
 The pregnancy rates related to the zones of
vascular penetration: 26.7% for zone 1, 36.4% for
zone 2 and 37.9% for zone 3.
Trigger-when ?
HCG at 18-20 mm (CC+Gn cycles)
HCG at 20-22 mm (CC cycles)
Dose- 5000 -10,000 IU
When Not to Trigger in IUI
When there are more than three mature follicles
Don’t forget
the
Luteal Phase !!!!
Is there any need ?
 Yes -gonadotropins cycles.
 No- CC / Letrozole cycles
Hill MJ Fertil Steril. 2013- a systematic review and meta-analysis.
Options in the Luteal Phase
 Vaginal Progesterone
 Capsules
 Vaginal Gel
 VT
 Intramuscular Progesterone
 Oral Dydrogesterone
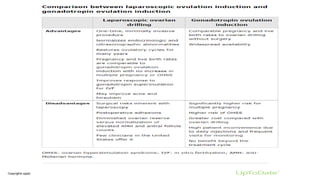
PCO drilling
A surgical solution for a medical problem ?
Reduces hyperandrogenism and improves the intraovarian
millieu
Lacks standardization in terms of indications, modality,
follow up
Which PCOS women will benefit ?
Best if < 3 years infertility, thin PCOS with high LH
LOD as first line ?
If laparoscopy is indicated for another reason
Risks should be explained to all women with PCOS
considering laparoscopic ovarian surgery.
All lap for infertility should always be combined with
Hysteroscopy
Copyrights apply
In-vitro fertilisation (IVF)
Women with PCOS undergoing IVF ± ICSI therapy should be
counselled prior to starting treatment about :
 Availability, cost and convenience
 Increased risk of ovarian hyperstimulation syndrome
 Options to reduce the risk of ovarian hyperstimulation
 Insufficient evidence to recommend specific FSH preparations.
 Exogenous r-LH should not be routinely used in combination with
FSH
Which Protocol ?
Antagonist Protocol
Agonist Trigger
Freeze all embryos
OHSS free clinic
Pregnancy Outcomes
Pregnant women with PCOS have an increased risk of the following:
 Higher gestational weight gain.
 Miscarriage.
 Gestational diabetes.
 Hypertension in pregnancy and preeclampsia.
 Intrauterine growth restriction, small for gestational age babies, and
low birth weight.
 Preterm delivery.
 Caesarean section.
Male Factor
 Never spend months treating PCOS while ignoring the semen analysis.
 Approximately 30–40% of infertile couples have a contributing male
factor.
PCOS - Late sequelae
 Diabetes mellitus x7
 Hypertension x4
 Dyslipidemia
 Endometrial hyperplasia
Concluding Remarks
 PCOS is a lifelong metabolic and reproductive disorder—not merely an ovulation disorder.
 Lifestyle modification remains the cornerstone of treatment and should be recommended
to every woman with PCOS, regardless of BMI.
 Letrozole has emerged as the first-line ovulation induction agent, offering superior live birth
rates compared with clomiphene citrate.
 Metformin, GLP-1 receptor agonists, myo-inositol, and bariatric surgery all have important
roles in carefully selected women, primarily for metabolic optimization rather than as
primary fertility treatments.
 Treatment should always be individualized, taking into account age, BMI, insulin resistance,
ovarian reserve, infertility duration, and the couple's reproductive goals.
 Finally, we should avoid unnecessary delays in escalating treatment and consider timely
referral for assisted reproductive technologies when appropriate.
 The future of PCOS management lies not in treating the ovaries alone but in addressing the
whole woman—her metabolic health, emotional well-being, reproductive aspirations, and
long-term quality of life.
References
 American Society for Reproductive Medicine 2025 Fertility Guideline
 European Society of Human Reproduction and Embryology
International PCOS Guideline (2023)
 FIGO Practice recommendations
 World Health Organization Obesity guidance
 Recent reviews from 2024–2026 on GLP-1 receptor agonists and PCOS
 ESHRE Guideline: Medically Assisted Reproduction (2023)
My World of sharing happiness!
My World of sharing
happiness!
Shrikhande Fertility Clinic
Ph- 91 9623459766
slaxmi2002@yahoo.com
The Art of Living
Anything that helps
you to become
unconditionally happy
and loving is what is
called spirituality.
H. H. Sri Sri Ravishakar