Comprehensive Health Screening Services: Methods, Roles, and Importance
Overview of health screening definitions, objectives, WHO guidelines, screening methods for blood pressure, blood sugar, lung function, cholesterol, and the pharmacist's role in early disease detection and prevention.
HEALTH SCREENING SERVICE
Definition
Objectives
WHO Screening Recommendations
Examples of Screening Services
Role of Pharmacists
Importance of Health Screening
Methods of Screening
Blood Pressure Screening
BLOOD SUGAR SCREENING
LUNG FUNCTION SCREENING
CHOLESTEROL SCREENING
3.
DEFINITION
Health screening servicesare the Preventive
measures for early detection of diseases or risk
factors that Targets apparently healthy individuals
which Enables timely medical intervention.
WHO SCREENING
RECOMMENDATIONS
Screeningshould be scientifically valid (based
on evidence).
The condition should be important to public
health.
There should be an acceptable treatment
available.
Facilities for diagnosis and treatment must be
accessible.
Screening should be cost-effective and
ethically acceptable
ROLE OF PHARMACISTS
Conduct basic screening in community
pharmacies.
Educate patients about risk factors and lifestyle
changes.
Refer patients to physicians for further
diagnosis/treatment.
Maintain records for follow-up and continuity of
care
8.
IMPORTANCE OF
HEALTH SCREENING
Early detection → Identifies diseases before symptoms
appear (e.g., hypertension, diabetes)
Prevention → Helps reduce risk factors through lifestyle
modification.
Cost effective
‑ ness → Saves healthcare costs by
preventing complications.
Improved prognosis → Early treatment improves survival
and quality of life.
Community awareness → Promotes health education
and responsible health behaviour.
1. Mass Screening
Large population groups screened
irrespective of risk.
Example: National immunization or TB
detection campaigns.
Advantage: Wide coverage.
Limitation: Expensive, less efficient
11.
2. Selective (High-risk)
Screening
Focused on individuals with risk factors
(e.g., smokers for lung cancer, obese
patients for diabetes).
Advantage: More cost-effective and
targeted
Limitations: Risk of inequity if vulnerable
populations are overlooked.
12.
3. Multiphasic Screening
Multiple tests conducted at once (e.g., BP, blood sugar,
cholesterol, BMI).
Saves time and resources.
Common in community pharmacy health camps
Advantages: Efficiency, Cost-effective &
Comprehensive health data.
Limitations: Overload of data, False positives/negatives
& Resource burden.
13.
4. Opportunistic Screening
Screening performed during routine healthcare
visits.
Example: Checking BP when a patient comes for
prescription refill.
Practical and widely used in pharmacies.
Advantages: Convenient, Cost-effective & Increases
coverage
Limitations: Unequal coverage & Inconsistent
implementation.
14.
5. Case-finding
Identifyingdisease in patients who
present with unrelated complaints.
Example: Detecting diabetes in a patient
visiting for minor illness
Advantages: More targeted, Cost-
effective & Improves early diagnosis and
treatment outcomes.
Limitations: healthcare access & Risk of
under-detection.
15.
Blood Pressure
Screening Methods
1.Manual (Auscultatory) Method
2. Digital (Oscillometric) Method
3. Ambulatory BP Monitoring (ABPM)
4. Home BP Monitoring (HBPM)
5. Community pharmacy camps
16.
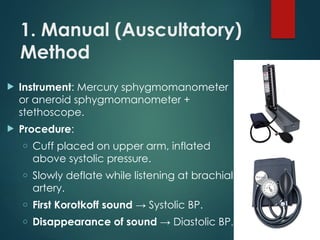
1. Manual (Auscultatory)
Method
Instrument: Mercury sphygmomanometer
or aneroid sphygmomanometer +
stethoscope.
Procedure:
o Cuff placed on upper arm, inflated
above systolic pressure.
o Slowly deflate while listening at brachial
artery.
o First Korotkoff sound → Systolic BP.
o Disappearance of sound → Diastolic BP.
17.
2. Digital (Oscillometric)
Method
Instrument: Electronic BP monitor.
Procedure:
o Cuff inflates/deflates automatically.
o Device detects oscillations in arterial wall.
o Provides systolic, diastolic, and pulse rate
digitally.
Advantages: Easy to use,
suitable for self screening
‑ .
18.
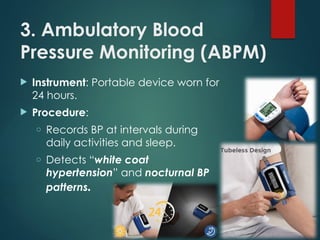
3. Ambulatory Blood
PressureMonitoring (ABPM)
Instrument: Portable device worn for
24 hours.
Procedure:
o Records BP at intervals during
daily activities and sleep.
o Detects “white coat
hypertension” and nocturnal BP
patterns.
19.
4. Home BloodPressure
Monitoring (HBPM)
Instrument: Digital BP monitors for self use.
‑
Procedure:
o Patients measure BP at home, usually twice
daily.
o Helps in long term monitoring and adherence
‑
20.
5. Community Pharmacy
ScreeningCamps
Method: Mass or opportunistic
screening during health camps.
Procedure:
o BP measured for walk in
‑
patients.
o Records maintained,
referrals made if abnormal
1. Fasting BloodGlucose
(FBG)
Procedure: Blood sample
taken after 8–12 hours of fasting.
Interpretation:
Normal: <100 mg/dL
Prediabetes: 100–125 mg/dL
Diabetes: ≥126 mg/dL
23.
2. Postprandial Blood
Glucose(PPBG)
Procedure: Blood sample taken 2 hours
after a meal.
Interpretation:
Normal: <140 mg/dL
Diabetes: ≥200 mg/dL
24.
3. Random BloodGlucose
(RBG)
Procedure: Blood sample taken
at any time, regardless of meals.
Interpretation:
≥200 mg/dL with symptoms →
Suggestive of diabetes.
6. Point ofCare Testing
‑ ‑
(POCT) / Glucometer
Procedure: Finger prick capillary
‑
blood tested using portable
glucometer.
Advantages: Quick,
convenient, suitable for
pharmacy and home use
28.
LUNG FUNCTION
SCREENING
1. Spirometry(FEV1, FVC)
2. Peak Expiratory Flow Rate (PEFR)
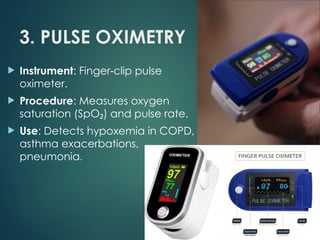
3. Pulse oximetry (SpO )
₂
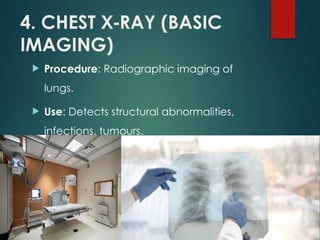
4. Chest X ray
‑
5. Questionnaire based screening
‑
29.
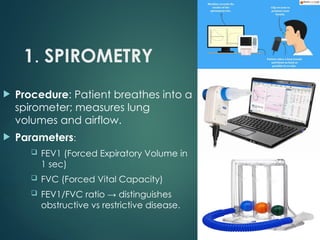
1. SPIROMETRY
Procedure:Patient breathes into a
spirometer; measures lung
volumes and airflow.
Parameters:
FEV1 (Forced Expiratory Volume in
1 sec)
FVC (Forced Vital Capacity)
FEV1/FVC ratio → distinguishes
obstructive vs restrictive disease.
5. QUESTIONNAIRE BASED
‑
SCREENING
Method: Standardized tools (e.g., COPD
Assessment Test, Asthma Control Test).
Use: Identifies patients at risk who should
undergo spirometry
34.
CHOLESTEROL
SCREENING METHODS
1. Totalcholesterol test
2. Lipid profile panel
3. Random cholesterol test
4. Portable cholesterol meters (POCT)
5. Advanced tests (ApoB, Non HDL
‑
cholesterol)
35.
1. TOTAL CHOLESTEROLTEST
Procedure: Blood sample (fasting or
non fasting).
‑
Interpretation:
Desirable: <200 mg/dL
Borderline: 200–239 mg/dL
High: ≥240 mg/dL
36.
2. LIPID PROFILE
(COMPREHENSIVEPANEL)
Procedure: Fasting blood sample (8–12 hours).
Parameters:
Total cholesterol
LDL (Low density lipoprotein)
‑
HDL (High density lipoprotein)
‑
Triglycerides
Interpretation:
LDL (“bad cholesterol”) should be <100 mg/dL.
HDL (“good cholesterol”) should be ≥40 mg/dL (men), ≥50 mg/dL
(women).
37.
3. RANDOM (NONFASTING)
‑
CHOLESTEROL TEST
Procedure: Blood sample taken anytime.
Use: Quick screening in pharmacy or
health camps
38.
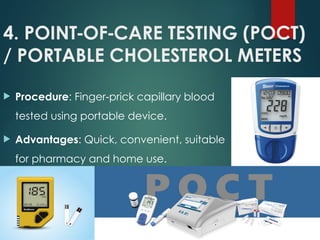
4. POINT OFCARE TESTING (POCT)
‑ ‑
/ PORTABLE CHOLESTEROL METERS
Procedure: Finger prick capillary blood
‑
tested using portable device.
Advantages: Quick, convenient, suitable
for pharmacy and home use.
39.
5. ADVANCED TESTS
(CONFIRMATORY/ MONITORING)
Apolipoprotein B (ApoB) → Reflects LDL particle number.
Non HDL cholesterol
‑ → Total cholesterol minus HDL.
Editor's Notes
#18 WHITE COAT HYPERTENSION: condition where blood pressure is elevated in a medical setting but normal at home.
NOCTURNAL BP PATTERNS: The normal decrease in blood pressure during sleep is a physiological response, but variations can indicate underlying health issues.
#29 Spirometry examines lung function by measuring the amount of air you can inhale and exhale, and the speed at which you exhale.
FEV1 – measures how much air you can exhale in the first second of a forced breath- to detect Asthma/COPD
FVC – measures Total Vol of air able to exhale , Obstructive lung disease makes it hard to exhale air from the lungs, while restrictive lung disease limits lung expansion and reduces the amount of air the lungs can hold.
#39 Apolipoprotein B (ApoB)- is a key protein that carries harmful cholesterol particles in the blood and serves as a strong predictor of cardiovascular disease risk.
Non‑HDL cholesterol -It measures cholesterol carried on LDLs, VLDLs and other particles known to cause plaque buildup.