Comprehensive Guide to the Neutral Zone in Prosthodontics for Denture Stability and Function
Explore the neutral zone concept in prosthodontics, including anatomy, muscle influence, denture design, advantages, limitations, and clinical techniques for improved denture stability and patient comfort.
Welcome to mypage on Facebook
Prof. Amal Kaddah Scientific Forum
Prof. Amal Kaddah Scientific
Forum
7.2k followers. 468 following
A professor of prosthodontics, Faculty of Dentistry, Cairo
University.
Public figure
5.
Outline
Introduction andDefinitions
The neutral zone concept
Nomenclatures
Indications, Advantages and disadvantages
Limitations and Constraints
Factors influencing the position of the neutral zone
Effect of Bone and Muscles on the neutral zone.
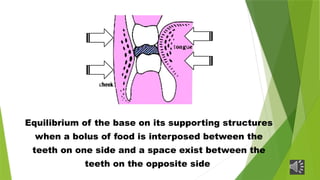
Importance and clinical significance of muscles in
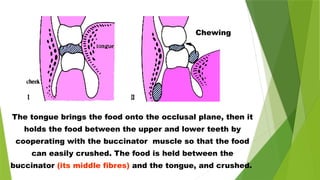
relation to denture construction
Technique in complete denture fabrication based on
neutral zone principle.
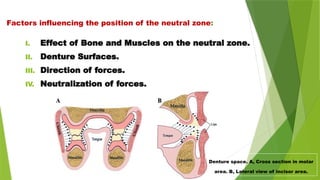
Neutral Zone Versus Biometrics concepts
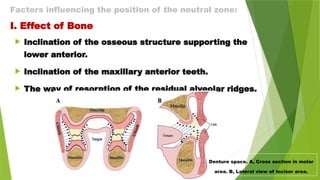
References
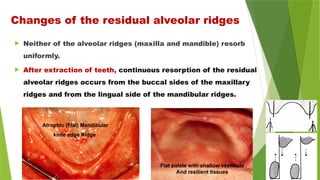
6.
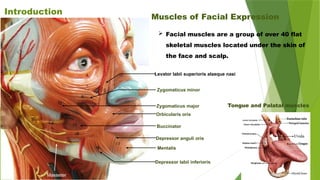
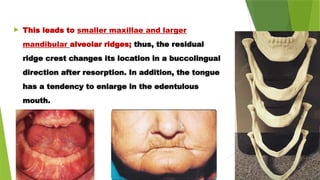
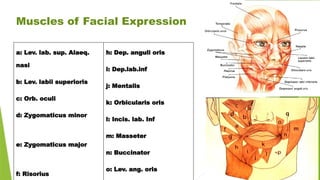
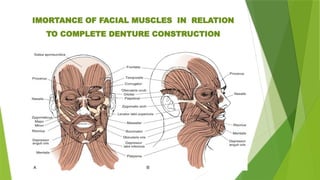
Levator labii superiorisalaeque nasi
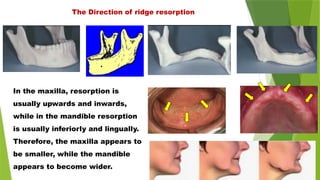
Orbicularis oris
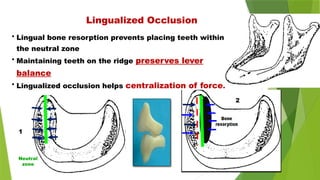
Depressor anguli oris
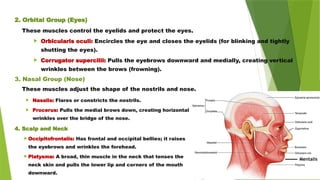
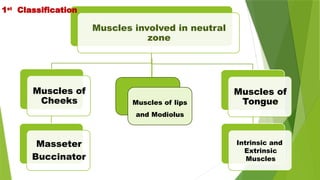
Depressor labii inferioris
Mentalis
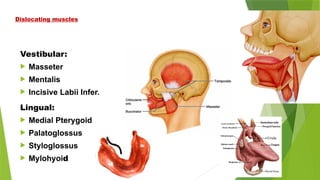
Zygomaticus major
Buccinator
Masseter
Muscles of Facial Expression
Zygomaticus minor
Tongue and Palatal muscles
Introduction
Facial muscles are a group of over 40 flat
skeletal muscles located under the skin of
the face and scalp.
7.
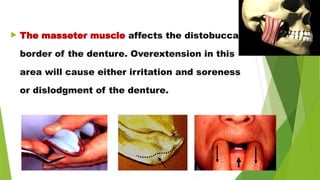
Introduction
Before lossof teeth, the neutral zone is
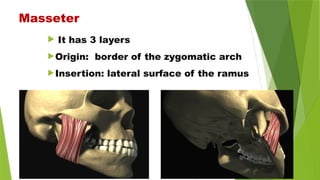
the zone occupied by the natural teeth.
During function, the forces of the
tongue pressing outward are neutralized
by the forces of the cheecks and lips
pressing inward.
8.
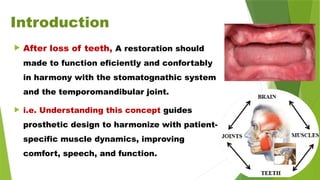
Introduction
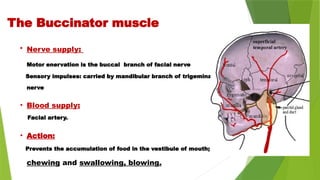
After lossof teeth, A restoration should
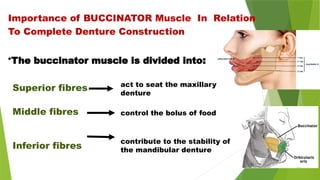
made to function eficiently and confortably
in harmony with the stomatognathic system
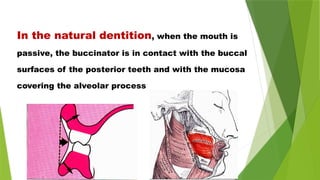
and the temporomandibular joint.
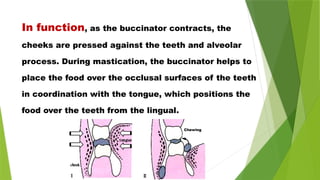
i.e. Understanding this concept guides
prosthetic design to harmonize with patient-
specific muscle dynamics, improving
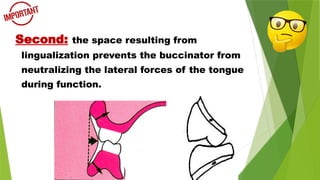
comfort, speech, and function.
9.
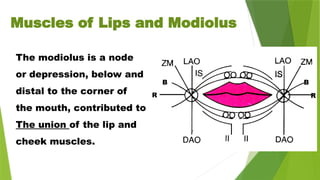
A, B: Denturespace. A, Cross section in molar area. B, occlusal view of incisor and
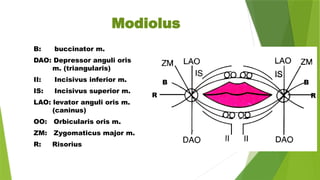
molar area.
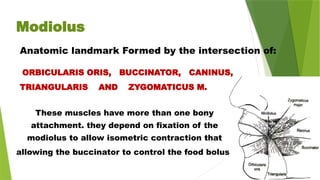
The neutral zone
Definitions
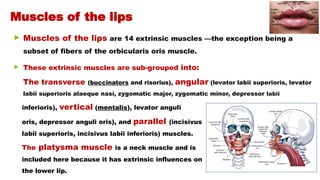
The neutral zone refers to that space in the oral cavity where the
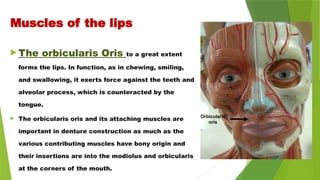
forces exerted by the musculature of the tongue are equal and
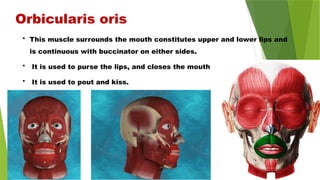
balanced with the forces exerted by the buccinator muscle of
the cheek laterally and the orbicularis oris muscle anteriorly.
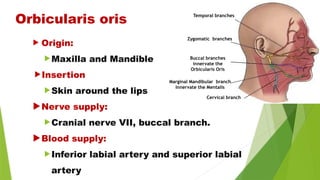
WIKIPEDIA
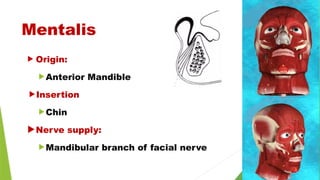
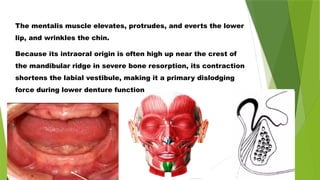
A B
10.
Denture space.
The neutralzone
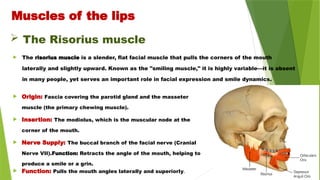
Definitions
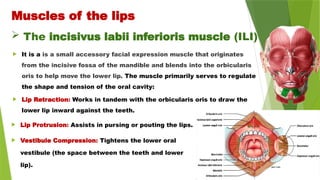
Is The potential space between the lips and cheeks on
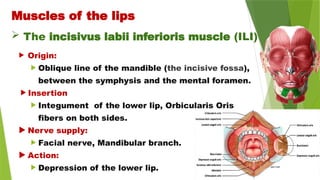
one side and the tongue on the other; that area or
position where the forces between the tongue and
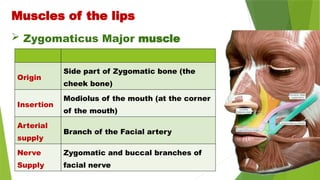
cheeks or lips are equal GPT 10
11.
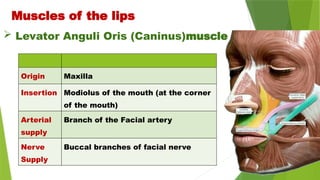
When allthe remaing natural teeth are
removed, the void that exists is called the
potential denture space:
It is the empty void in the mouth after natural
teeth are lost, bounded by the lips and cheeks
externally and the tongue internally.
Within this space lies the neutral zone
(JPD; 1976.2006)
A problem occurs when the neutral zone is
not where we want the teeth to be????
The neutral zone concept
12.
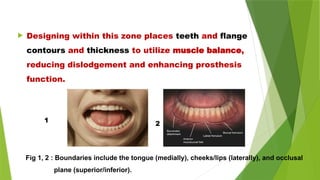
Designing withinthis zone places teeth and flange
contours and thickness to utilize muscle balance,
reducing dislodgement and enhancing prosthesis
function.
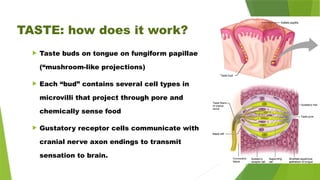
Fig 1, 2 : Boundaries include the tongue (medially), cheeks/lips (laterally), and occlusal
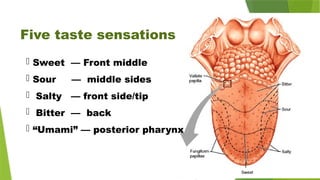
plane (superior/inferior).
1 2
13.
Dentures mustbe perfectly built
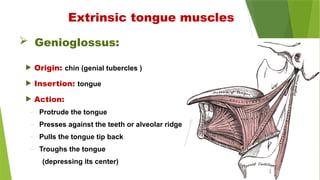
within this exact space. If artificial
teeth and denture borders are
positioned outside of it, the
surrounding muscles will continually
push and dislodge the appliance,
causing instability, soreness, and
difficulty eating or speaking.
14.
Is based onthe belief that the muscles
should functionally mold not only the
border and the artificial teeth but also the
entire polished surface facial and
lingual forces generated by the
musculature of the lips, cheeks and
tongue are balanced.
The neutral zone concept
15.
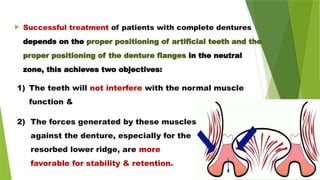
Successful treatmentof patients with complete dentures
depends on the proper positioning of artificial teeth and the
proper positioning of the denture flanges in the neutral
zone, this achieves two objectives:
2) The forces generated by these muscles
against the denture, especially for the
resorbed lower ridge, are more
favorable for stability & retention.
1) The teeth will not interfere with the normal muscle
function &
16.
Multiple names weregiven to this zone as:
The neutral zone (Fish 1931),
Zone of equilibrium. (Fish 1933),
Dead Zone (Fish 1933),
Potential denture space (Robert 1960),
Stable zone (Brill and Tryde 1965),
Biometric denture space (Watt and Mac Gregor 1986),
Zone of least interference (Wright1991)
Zone of minimal conflict,
The zone of soft tissue balance.
The neutral zone
Nom
enclatures
17.
Indications
The neutral zonetechnique is indicated in cases where there
has been:
Extensively resorbed mandibular ridge (minimal bone
available to support a denture)
Patients with neurological conditions
Patients who have previously had partial glossectomie,
mandibular resection and/or motor nerve damage to the
tongue
Where dental implants are not feasible.
WIKIPEDIA
1. Gupta, KL; Agarwal, S (Nov–Dec 2011). "Salvation of a severely resorbed mandibular ridge with a neutral zone technique". Indian Journal of Dental Research. 22 (6): 883. doi:
10.4103/0970-9290.94699. PMID 22484902.
2. Marc Geissberger (8 July 2013). Esthetic Dentistry in Clinical Practice. John Wiley & Sons, 2013. ISBN 9781118694930
18.
Improved Retentionand stability of complete dentures that become
more dependent on the correct positioning of the teeth and the
contours of the external or polished surfaces of the dentures.
(particularly lower complete dentures)
Function The neutral-zone philosophy is that Correct positioning of
posterior artificial teeth on the crest of the ridge as dictated by the
musculature, allows for sufficient tongue space
Prevent cheek/tongue biting.
Reduced food trapping (How ???)
Improved aesthetics due to facial support.
Advantages
19.
Equilibrium of thebase on its supporting structures
when a bolus of food is interposed between the
teeth on one side and a space exist between the
teeth on the opposite side
20.
The tongue bringsthe food onto the occlusal plane, then it
holds the food between the upper and lower teeth by
cooperating with the buccinator muscle so that the food
can easily crushed. The food is held between the
buccinator (its middle fibres) and the tongue, and crushed.
Chewing
21.
Second: Providing betterstability and retention and
help to determine the peripheral borders, tooth position
and the external contour of the dentures.
Therefore, a basic understanding of the anatomy and
physiology of the muscles is essential.
First: Providing better speech, mastication, swallowing, smiling
and prevent collapse of lips and therefore help in proper functioning
of The Orbicularis Oris muscle.
Thus, Positioning artificial teeth within the
neutral zone ensures two main objectives
22.
locating this areais a great way to stabilize complete dentures, its
primary limitations include:
Narrow Space and Crowding: The resultant neutral zone is often narrow and
sometimes positioned lingually, which can crowd the tongue and impair
speech or functional tongue movements.
Increased Lab Time and Cost: The functional impression technique requires
extra clinical appointments, greater chair time, and specialized laboratory
support to properly construct the dentures.
Material Viscosity Challenges: If the impression materials used are too
viscous, it becomes difficult for the oral muscles to mold them naturally into
the neutral zone.
Patient Fatigue: The procedure demands repetitive movements (swallowing,
speaking), which can be difficult or painful for geriatric patients or those
with compromised muscle tone.
Tooth Selection Constraints: The technique primarily dictates where the
teeth should be placed but offers little guidance on the selection of the
artificial teeth themselves.
Disadvantages and Limitations include
23.
Factors influencing theposition of the neutral zone:
I. Effect of Bone and Muscles on the neutral zone.
II. Denture Surfaces.
III. Direction of forces.
IV. Neutralization of forces.
Denture space. A, Cross section in molar
area. B, Lateral view of incisor area.
24.
Factors influencing theposition of the neutral zone:
I. Effect of Bone
Inclination of the osseous structure supporting the
lower anterior.
Inclination of the maxillary anterior teeth.
The way of resorption of the residual alveolar ridges.
Denture space. A, Cross section in molar
area. B, Lateral view of incisor area.
25.
Changes of theresidual alveolar ridges
Neither of the alveolar ridges (maxilla and mandible) resorb
uniformly.
After extraction of teeth, continuous resorption of the residual
alveolar ridges occurs from the buccal sides of the maxillary
ridges and from the lingual side of the mandibular ridges.
Atrophic (Flat) Mandibular
knife edge Ridge
Flat palate with shallow vestibule
And resilient tissues
26.
This leadsto smaller maxillae and larger
mandibular alveolar ridges; thus, the residual
ridge crest changes its location in a buccolingual
direction after resorption. In addition, the tongue
has a tendency to enlarge in the edentulous
mouth.
27.
The Direction ofridge resorption
In the maxilla, resorption is
usually upwards and inwards,
while in the mandible resorption
is usually inferiorly and lingually.
Therefore, the maxilla appears to
be smaller, while the mandible
appears to become wider.
28.
• Lingual boneresorption prevents placing teeth within
the neutral zone
• Maintaining teeth on the ridge preserves lever
balance
• Lingualized occlusion helps centralization of force.
Bone
resorption
Neutral
zone
Lingualized Occlusion
1
2
29.
II. Influence ofMuscle Forces
Muscles of Facial
Expression
1. Oral Group (Mouth)
2. Orbital Group (Eyes)
3. Nasal Group (Nose)
4. Scalp and Neck
Muscles involved in
neutral zone
Muscles of
Cheeks
Lips and
Tongue
30.
1. Oral Group(Mouth)
Risorius: Draws the corners of the mouth laterally (a "fake" smile).
Depressor anguli oris: Pulls the corners of the mouth downward.
Mentalis: Protrudes the lower lip and wrinkles the chin.
These muscles control lip movements, speech, eating, and expressions like
smiling or pouting.
Orbicularis oris: A sphincter muscle that closes and purses the lips (like
whistling).
Buccinator: Compresses the cheeks against the teeth (used in blowing
or whistling).
Zygomaticus major & minor: Elevate the corners of the mouth to
create a smile.
31.
2. Orbital Group(Eyes)
These muscles control the eyelids and protect the eyes.
Orbicularis oculi: Encircles the eye and closes the eyelids (for blinking and tightly
shutting the eyes).
Corrugator supercilii: Pulls the eyebrows downward and medially, creating vertical
wrinkles between the brows (frowning).
3. Nasal Group (Nose)
These muscles adjust the shape of the nostrils and nose.
Mentalis
Nasalis: Flares or constricts the nostrils.
Procerus: Pulls the medial brows down, creating horizontal
wrinkles over the bridge of the nose.
4. Scalp and Neck
Occipitofrontalis: Has frontal and occipital bellies; it raises
the eyebrows and wrinkles the forehead.
Platysma: A broad, thin muscle in the neck that tenses the
neck skin and pulls the lower lip and corners of the mouth
downward.
Muscles involved inneutral
zone
Muscles of
Cheeks
Masseter
Buccinator
Muscles of
Tongue
Intrinsic and
Extrinsic
Muscles
Muscles of lips
and Modiolus
1st
Classification
Muscular boundaries ofthe neutral
zone
The musculature of the denture space can be divided into two
groups:
1. Dislocating muscles: Those muscles which primarily dislocate
the denture during activity.
2. Fixing muscles: Those muscles that fix the denture by muscular
pressure on the polished surfaces.
These can then be further divided according to their location on
the vestibular (labial & buccal) side or lingual side of the
dentures.
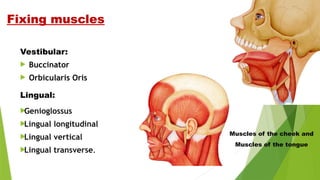
Fixing muscles
Vestibular:
Buccinator
Orbicularis Oris
Lingual:
Genioglossus
Lingual longitudinal
Lingual vertical
Lingual transverse.
Muscles of the cheek and
Muscles of the tongue
38.
Exerts outward pressure.The size, shape, and resting
posture of the tongue determine the lingual boundary of the
denture space.
The key muscles and structures involved around the neutral
zone include:
Extrinsic Muscles: Anchor the tongue to the surrounding
bones and affect its overall position. Important muscles
include the genioglossus, styloglossus, hyoglossus, and
1. Internal Forces (Tongue):
3rd
Classification
Intrinsic Muscles: Shape the tongue and alter its form during
chewing, swallowing, and speech.
39.
The key musclesand structures involved include:
2. External Forces (Cheeks and Lips):
Includes the orbicularis Oris, buccinator, and modiolus. These
muscles exert inward forces and dictate the buccal and labial
limits of the denture space.
Modiolus: A dense, dynamic knot of muscle at the corner of the mouth where several
facial muscles converge. It dictates the width of the denture in the premolar area and
requires careful clearance to avoid unseating the restoration
Buccinator: The main muscle of the cheek that exerts inward
pressure and positions food on the teeth.
Orbicularis Oris: The primary lip muscle that forms the anterior
boundary and affects front teeth stability.
40.
The key musclesand structures involved
3. Muscles that have no direct influence on determining
the "neutral zone“ but play an indirect and critical role in
the neutral zone.
a) Masseter Muscles
b) Muscles of the Floor of the Mouth
Muscles like the mylohyoid govern the depth and
contour of the lower denture's lingual flange.
c) The superior pharyngeal constrictor
Muscle of the pharynx Constricts the wall of the
pharynx during swallowing to propel the food bolus
downwards.
41.
The Massetermuscle, has no direct influence
on determining the "neutral zone"
However, It plays an indirect and critical role in the
neutral zone.
I. Muscles of the cheeks:
42.
The massetermuscle affects the distobuccal
border of the denture. Overextension in this
area will cause either irritation and soreness
or dislodgment of the denture.
43.
It actsas a major boundary-defining muscle that
dictates the outward limits of the distobuccal
(back-outer) border of the lower denture space,
helping to shape the contours of dental prostheses.
Shaping the Denture Space.
Preventing Denture Dislodgement.
Distobuccal Border Constraints.
Masseter
44.
Masseter
It has3 layers
Origin: border of the zygomatic arch
Insertion: lateral surface of the ramus
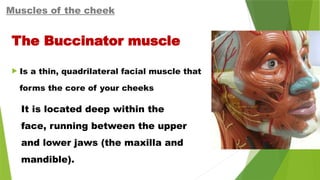
Is athin, quadrilateral facial muscle that
forms the core of your cheeks
Muscles of the cheek
The Buccinator muscle
It is located deep within the
face, running between the upper
and lower jaws (the maxilla and
mandible).
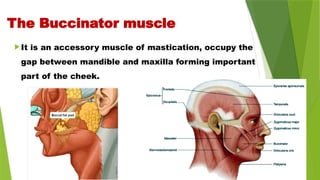
47.
It is anaccessory muscle of mastication, occupy the
gap between mandible and maxilla forming important
part of the cheek.
The Buccinator muscle
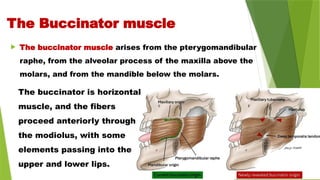
The buccinatormuscle arises from the pterygomandibular
raphe, from the alveolar process of the maxilla above the
molars, and from the mandible below the molars.
The Buccinator muscle
The buccinator is horizontal
muscle, and the fibers
proceed anteriorly through
the modiolus, with some
elements passing into the
upper and lower lips.
50.
• It compressesthe cheeks during chewing
and swallowing.
• Is used when blowing air from the cheek
under pressure.
The Buccinator muscle
• This muscle is the cheek muscle form the lateral wall of the
oral cavity Flattens the cheek to whistle or blow trumpet
51.
• Nerve supply:
Motorenervation is the buccal branch of facial nerve
Sensory impulses: carried by mandibular branch of trigeminal
nerve
• Blood supply:
Facial artery.
• Action:
Prevents the accumulation of food in the vestibule of mouth;
chewing and swallowing, blowing.
The Buccinator muscle
52.
Superior fibres
Middle fibres
Inferiorfibres
•The buccinator muscle is divided into:
Importance of BUCCINATOR Muscle In Relation
To Complete Denture Construction
act to seat the maxillary
denture
control the bolus of food
contribute to the stability of
the mandibular denture
53.
While themiddle fibres contract, controlling the bolus, the inferior
fibres relax to form a pouch capable of storing food until needed to
form another bolus.
Extension of a concave denture base into this pouch allows the
cheek to lie over the flange.
The nature of buccinator was not able to changes to contour of the
denture base. Because learning and adaptation appear to be
limited, the denture contours should be designed to harmonise
with exiting buccinator muscle function.
Importance of BUCCINATOR Muscle In Relation
To Complete Denture Construction
54.
In the naturaldentition, when the mouth is
passive, the buccinator is in contact with the buccal
surfaces of the posterior teeth and with the mucosa
covering the alveolar process
55.
In function, asthe buccinator contracts, the
cheeks are pressed against the teeth and alveolar
process. During mastication, the buccinator helps to
place the food over the occlusal surfaces of the teeth
in coordination with the tongue, which positions the
food over the teeth from the lingual.
Chewing
56.
In the oralcavity, inward forces by the orbicularis oris and the buccinator muscle
get balanced by the outward forces of the tongue. While making an impression for a
completely edentulous patient, molding must be done by muscle function in such a
manner that it is in harmony with the surrounding musculature.
Buccinator along with orbicularis oris and pharyngeal constrictor forms a functional
unit (buccinator mechanism) which is essential for orofacial functions (swallowing,
sucking, whistling, chewing, vowel pronunciation). If buccinator is weakened or
paralyzed, food tends to accumulate in the vestibule during chewing.
Buccinator muscle plays a role in stabilizing the denture by gripping the polished
surface of the denture. Also, the longitudinal fibers hold the bolus of food between
the teeth during mastication. The maxillary bundle of this muscle tends to raise the
upper denture, whereas the mandibular bundle of this muscle depresses the lower
denture, thus aiding in denture stability and retention.
Source: https://www.ncbi.nlm.nih.gov/books/NBK546678/
Clinical Implication in Prosthodontics
57.
Therefore, The buccinatorplays a very
important role in establishing the
neutral zone, but the muscle in
contraction will not cause dislodgment
of the denture because it runs parallel
to the ridge.
58.
Lingualization ofocclusion creates a space
between the cheek and the teeth and the external
surface of the denture.
Food tends to accommodate in this space, and it
becomes more difficult for the cheek to place the
food back onto the occlusal surfaces of the teeth.
The common practice of centralization, or
lingualization of occlusion, prevents the buccinator
from performing its proper function in two ways;
First:
59.
Second: the spaceresulting from
lingualization prevents the buccinator from
neutralizing the lateral forces of the tongue
during function.
60.
The modiolus isa node
or depression, below and
distal to the corner of
the mouth, contributed to
The union of the lip and
cheek muscles.
B B
R R
Muscles of Lips and Modiolus
61.
Modiolus
B: buccinator m.
DAO:Depressor anguli oris
m. (triangularis)
II: Incisivus inferior m.
IS: Incisivus superior m.
LAO: levator anguli oris m.
(caninus)
OO: Orbicularis oris m.
ZM: Zygomaticus major m.
R: Risorius
B B
R R
62.
Modiolus
Anatomic landmark Formedby the intersection of:
ORBICULARIS ORIS, BUCCINATOR, CANINUS,
TRIANGULARIS AND ZYGOMATICUS M.
These muscles have more than one bony
attachment. they depend on fixation of the
modiolus to allow isometric contraction that
allowing the buccinator to control the food bolus
63.
IMORTANCE and CLINICALSIGNIFICANCE OF
MODIOLUS IN RELATION
TO COMPLETE DENTURE CONSTRUCTION
As situated at the corner of the mouth it
is in strategic position to unseat the
lower denture and sometimes the upper
denture too.
This may occur if the arch form is too
wide and restricts the movements of the
modiolus
64.
Muscles ofthe lips are 14 extrinsic muscles —the exception being a
subset of fibers of the orbicularis oris muscle.
These extrinsic muscles are sub-grouped into:
The transverse (buccinators and risorius), angular (levator labii superioris, levator
labii superioris alaeque nasi, zygomatic major, zygomatic minor, depressor labii
inferioris), vertical (mentalis), levator anguli
oris, depressor anguli oris), and parallel (incisivus
labii superioris, incisivus labii inferioris) muscles.
The platysma muscle is a neck muscle and is
included here because it has extrinsic influences on
the lower lip.
Muscles of the lips
65.
Muscles of thelips
The orbicularis Oris to a great extent
forms the lips. In function, as in chewing, smiling,
and swallowing, it exerts force against the teeth and
alveolar process, which is counteracted by the
tongue.
The orbicularis oris and its attaching muscles are
important in denture construction as much as the
various contributing muscles have bony origin and
their insertions are into the modiolus and orbicularis
at the corners of the mouth.
Orbicularis
oris
66.
Orbicularis oris
• Thismuscle surrounds the mouth constitutes upper and lower lips and
is continuous with buccinator on either sides.
• It is used to purse the lips, and closes the mouth
• It is used to pout and kiss.
67.
It is activewhen the lips are pressed against the teeth,
like buccinator ORBICULARIS ORIS muscle
rhythmically contracts during chewing, sucking and
swallowing.
Proper shaping of the labial and buccal flanges - to be
concave rather than convex- is necessary to support
the lips, cheeks and tongue, and will allow them and
to seat the denture.
Importance of ORBICULARIS ORIS muscle in relation to
complete denture construction
68.
Origin:
Maxilla andMandible
Insertion
Skin around the lips
Nerve supply:
Cranial nerve VII, buccal branch.
Blood supply:
Inferior labial artery and superior labial
artery
Orbicularis oris
Buccal branches
innervate the
Orbicularis Oris
Zygomatic branches
Cervical branch
Marginal Mandibular branch
Innervate the Mentalis
Temporal branches
69.
Mentalis
• This muscleis found around the
chin
• It raises the lower lip, causing the
chin to wrinkle
• It will give a doubt facial
expression
The mentalis muscleelevates, protrudes, and everts the lower
lip, and wrinkles the chin.
Because its intraoral origin is often high up near the crest of
the mandibular ridge in severe bone resorption, its contraction
shortens the labial vestibule, making it a primary dislodging
force during lower denture function
72.
Contraction ofthe mentalis m. raise a soft
tissues of the chin, thus reducing the width
and depth of the sulcus.
If there has been marked resorption of the
underlying bone, this muscle can exert
Clinical significance of MENTALIS muscle in relation
to complete denture construction
considerable pressure on the labial flange of the denture, resulting in
posterior and upward displacement (denture instability).
The denture must be relieved over, and contoured around them.
Because it raises the lower lip, causing the chin to wrinkle its Contraction
indicates high V.D. of the denture
73.
The Risoriusmuscle
The risorius muscle is a slender, flat facial muscle that pulls the corners of the mouth
laterally and slightly upward. Known as the "smiling muscle," it is highly variable—it is absent
in many people, yet serves an important role in facial expression and smile dynamics.
Origin: Fascia covering the parotid gland and the masseter
muscle (the primary chewing muscle).
Insertion: The modiolus, which is the muscular node at the
corner of the mouth.
Nerve Supply: The buccal branch of the facial nerve (Cranial
Nerve VII).Function: Retracts the angle of the mouth, helping to
produce a smile or a grin.
Function: Pulls the mouth angles laterally and superiorly.
Muscles of the lips
74.
It isa is a small accessory facial expression muscle that originates
from the incisive fossa of the mandible and blends into the orbicularis
oris to help move the lower lip. The muscle primarily serves to regulate
the shape and tension of the oral cavity:
Lip Retraction: Works in tandem with the orbicularis oris to draw the
lower lip inward against the teeth.
Muscles of the lips
The incisivus labii inferioris muscle (ILI)
Lip Protrusion: Assists in pursing or pouting the lips.
Vestibule Compression: Tightens the lower oral
vestibule (the space between the teeth and lower
lip).
75.
Muscles of thelips
Origin:
Oblique line of the mandible (the incisive fossa),
between the symphysis and the mental foramen.
Insertion
Integument of the lower lip, Orbicularis Oris
fibers on both sides.
Nerve supply:
Facial nerve, Mandibular branch.
Action:
Depression of the lower lip.
The incisivus labii inferioris muscle (ILI)
76.
The incisivuslabii inferioris muscle (ILI)
Muscles of the lips
Clinical Significance:
Contraction of the muscle can reduce the
denture space.
In action it pulls the Modioli forward and
tenses the buccinator thereby applying
pressure on the polished surface.
77.
Zygomaticus MajorMuscle
Is a facial expression muscle that pulls the corner of
the mouth upward and outward to create a smile
Muscles of the lips
Clinical Significance:
Smiling and Laughing: It acts as the primary
"laughing muscle" by pulling the lip corners up
and back.
Dimples: A split or divided form of this muscle
can create a cheek dimple when a person smiles.
78.
Zygomaticus Majormuscle
Muscles of the lips
Origin
Side part of Zygomatic bone (the
cheek bone)
Insertion
Modiolus of the mouth (at the corner
of the mouth)
Arterial
supply
Branch of the Facial artery
Nerve
Supply
Zygomatic and buccal branches of
facial nerve
79.
Also calledthe Caninus muscle, is a
small facial expression muscle that
lifts the corner of the mouth to help a
person smile.
It lies deep in the cheek near the
upper jaw
Muscles of the lips
Levator Anguli Oris (Caninus) muscle
Levator Anguli Oris
muscle
80.
Levator AnguliOris (Caninus)muscle
Muscles of the lips
Origin Maxilla
Insertion Modiolus of the mouth (at the corner
of the mouth)
Arterial
supply
Branch of the Facial artery
Nerve
Supply
Buccal branches of facial nerve
81.
Pulls theangle of the mouth upward and slightly
inward.
In swallowing: It Helps to pull the lips forward,
thus exerting forces on the teeth and alveolar
process.
Expression: Used heavily during smiling, sneering,
and talking.
Issues: Weakness or damage to the facial nerve
can stop this muscle from working, leading to a
drooping mouth on the affected side.
Levator Anguli Oris (Caninus) muscle
Clinical Significance and Action of the
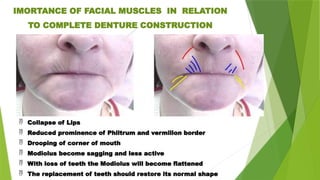
Collapse ofLips
Reduced prominence of Philtrum and vermilion border
Drooping of corner of mouth
Modiolus become sagging and less active
With loss of teeth the Modiolus will become flattened
The replacement of teeth should restore its normal shape
IMORTANCE OF FACIAL MUSCLES IN RELATION
TO COMPLETE DENTURE CONSTRUCTION
84.
Although it isa jaw-closing muscle, its
contraction pushes the superior
pharyngeal constrictor forward, further
defining the boundaries of this
space.
Medial Pterygoid Muscle
The medial pterygoid muscle is one of the four
muscles of mastication. It is a powerful elevator of the
mandible and is particularly active in chewing.
85.
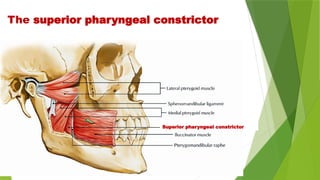
The superior pharyngealconstrictor
Muscle is the uppermost and thinnest of the three circular muscles lining the pharynx. Its primary function is
to contract during swallowing, squeezing the food bolus downward into the esophagus. The superior
pharyngeal constrictor is a muscle of the pharynx. It is the uppermost of the pharyngeal constrictors and is
located within the oropharynx.
Attachments: Originates from the pterygomandibular ligament, alveolar process of the mandible, medial
pterygoid plate and pterygoid hamulus of the sphenoid bone. It inserts posteriorly onto the pharyngeal
tubercle of the occipital bone and the pharyngeal raphe.
Action: Constricts the wall of the pharynx during swallowing to propel the food bolus downwards.
Innervation: Vagus nerve
Blood supply:
Pharyngeal branch of ascending pharyngeal artery
with contributions from the tonsillar branch of facial artery.
The superior constrictormuscle plays a critical role in complete
denture fabrication, specifically in defining the distolingual (back
and tongue-side) border of the mandibular denture.
How It Influences the Denture
Denture Space Boundary: The superior constrictor (along
with the buccinator) forms the external/lateral limit of the
denture space.
Border Molding: When a patient moves their tongue or
protrudes it during the border molding/impression process, it
activates the superior constrictor muscle, which shapes and
molds the distolingual border of the lower denture.
88.
Clinical Significance
Overextensionor incorrect contouring of the
denture in this area will cause the contracting muscle to
press the denture into the mucosa, leading to severe
pain and ulceration.
Properly capturing this area (often alongside the
retromolar pad and mylohyoid muscle), Provoke stability
and retention: Constructing the denture in harmony with
this muscle allows the denture to function without
interference, creating an excellent seal and stabilizing
the prosthesis during swallowing and speaking.
89.
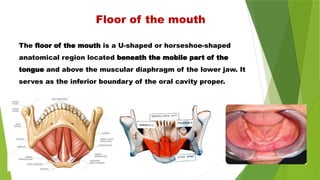
The floor ofthe mouth is a U-shaped or horseshoe-shaped
anatomical region located beneath the mobile part of the
tongue and above the muscular diaphragm of the lower jaw. It
serves as the inferior boundary of the oral cavity proper.
Retromylohyoid
eminence
Mylohyoid
ridge
Floor of the mouth
90.
Anatomy & Boundaries
Thefloor of the mouth acts as a muscular diaphragm separating
the oral cavity from the neck spaces below.
Superior Boundary: The oral mucosa beneath the tongue.
Inferior Boundary: The mylohyoid muscle sling, which creates
the main floor structural support.
Anterior & Lateral Boundaries: The inner surface of the
mandible bone (lower jaw) and its gingiva.
Posterior Boundary: The base of the anterior tonsillar pillars.
Retromylohyoid
eminence
Mylohyoid
ridge
Floor of the mouth
DLA deep lingual artery, GHM geniohyoid muscle, HB hyoid
bone, HGM hyoglossus muscle, LA lingual artery, MHM mylohyoid
muscle, PB perforating branch from submental artery, SHM stylohyoid
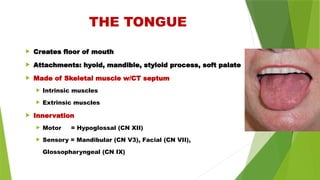
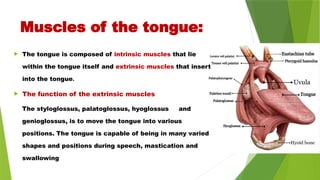
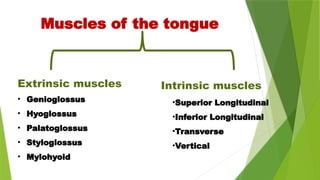
Muscles of thetongue:
The tongue is composed of intrinsic muscles that lie
within the tongue itself and extrinsic muscles that insert
into the tongue.
The function of the extrinsic muscles
The styloglossus, palatoglossus, hyoglossus and
genioglossus, is to move the tongue into various
positions. The tongue is capable of being in many varied
shapes and positions during speech, mastication and
swallowing
94.
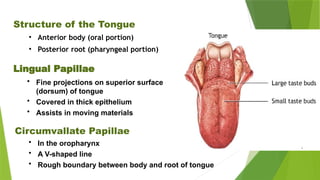
Structure of theTongue
• Anterior body (oral portion)
• Posterior root (pharyngeal portion)
Lingual Papillae
• Fine projections on superior surface
(dorsum) of tongue
• Covered in thick epithelium
• Assists in moving materials
• In the oropharynx
• A V-shaped line
• Rough boundary between body and root of tongue
Circumvallate Papillae
95.
TASTE: how doesit work?
Taste buds on tongue on fungiform papillae
(“mushroom-like projections)
Each “bud” contains several cell types in
microvilli that project through pore and
chemically sense food
Gustatory receptor cells communicate with
cranial nerve axon endings to transmit
sensation to brain.
96.
Five taste sensations
Sweet — Front middle
Sour — middle sides
Salty — front side/tip
Bitter — back
“Umami” — posterior pharynx
Extrinsic Muscles
1.Genioglossus: Protrudes(sticks out),
depresses, and pulls the tongue downward.
2.Hyoglossus: Depresses (pulls down) and
retracts the sides of the tongue.
3.Styloglossus: Retracts and elevates the tongue,
creating a trough to aid in swallowing.
4.Palatoglossus: Elevates the posterior (back)
part of the tongue and closes the oropharyngeal
isthmus to initiate swallowing
99.
These muscles arelocated entirely within the tongue and alter its shape
(e.g., curling, flattening, narrowing) for fine articulation.
Superior Longitudinal: Shortens the tongue and curls the tip and
edges upward.
Inferior Longitudinal: Shortens the tongue and curls the tip downward.
Transverse: Lengthens and narrows the tongue.
Vertical: Flattens and broadens the tongue.
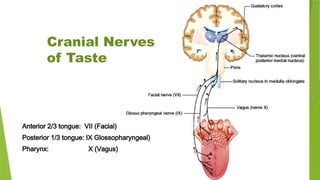
Innervation
Almost all tongue muscles are innervated by the Hypoglossal Nerve
(Cranial Nerve XII).
The only exception is the palatoglossus, which is innervated by the
Vagus Nerve (Cranial Nerve X)
Intrinsic Muscles
100.
Genioglossus:
Extrinsic tonguemuscles
Origin: chin (genial tubercles )
Insertion: tongue
Action:
– Protrude the tongue
– Presses against the teeth or alveolar ridge
– Pulls the tongue tip back
– Troughs the tongue
(depressing its center)
#49 Origin: alveolar bone of the upper and lower three molars and pterygomandibular ligament .
Course and insertion ;
Upper fibers inserted into upper lip,
Lower fibers inserted into lower lip,
Middle fibers decussate at the angle of the mouth, the upper fibers pass to lower lip while the lower fibers pass to the upper lip .
#74 Pouting: Helps create expressions like pouting or protruding the lower lip.
Daily Actions: Assists with eating, speaking, and making facial expressions
#116 Use special trays and functional movements (swallowing, speaking, chewing).
#143 The digitalization of the neutral zone technique integrates digital scanning and CAD/CAM software to identify the precise area in the oral cavity where opposing muscle forces (the tongue vs. the lips and cheeks) are neutralized. This creates a highly stable, functional denture or implant prosthesis that muscle actions will not dislodge. [1, 2, 3, 4, 5]
The transition from conventional to digital workflows streamlines the process, significantly reducing chair time and laboratory iterations.














































![Divyknckascnas;lmsalsam[slmas'lmsa'[a jc 2.pptx](https://cdn.slidesharecdn.com/ss_thumbnails/divyajc2-250501083105-03593cf6-thumbnail.jpg?width=640&height=640&fit=bounds)


