LESSON OBJECTIVES
• Atthe end of the lesson, you should be able to
demonstrate understanding of:
– What nutrition intervention (NI) and nutrition
prescription are
– What dietary modification is
– The routine diets used in the hospital setting
– Applications of modified diets in the hospital
setting
– Medical food supplements
3.
INTRODUCTION
• Nutrition Interventions(NI)
– They are actions taken to treat nutrition problems by resolving the
etiology and/or reducing/managing the related signs and
symptoms
– It involves two steps: planning & implementation
– Nutrition intervention, whenever possible, should target the
etiology identified during the assessment step
– When the registered dietitian (RD) cannot treat the etiology of
the nutrition diagnosis (ND) directly, the treatment should focus
on reducing/managing the signs & symptoms of the diagnosis
– The planning phase of the NI needs the RD, client and others to
collaborate and identify GOALS that will signify success of
intervention. A significant part of the plan is the nutr prescription
4.
INTRODUCTION
• Pt-centred goalsare set first & then implementation begins
• Nutrition interventions include
– Food & nutrition therapies, nutrition education, counselling, or
coordination of care like providing referral to for financial or food
resources
• Nutrition Prescription
– A detailed description of the nutrient needs of a particular client
– Typically, it includes recommended needs of energy, protein, and
fluid but may also include nutrients pertinent to the client’s
condition such as sodium needs in hypertension, carbohydrate
needs in diabetes etc.
– It’s written by RD after diagnosing the nutrition problems
5.
MODIFICATIONS OF THE
NORMALDIET
• Normal nutrition is the foundation on which therapeutic diet
modifications are based
• Regardless of the type of diet prescribed, the purpose of the diet
is to supply needed nutrients to the body in a form it can handle
• Therefore, therapeutic diet (dietary modification)
‒ Refers to the changes made to a normal diet to supply the
various nutrient needs of the body in disease states.
‒ It is a normal diet, qualitatively & quantitatively, modified
as per the patient's special need & in line with the general
principles of meal planning
‒ It is the CORE of dietetic practice and requires enormous
skills since no two situations requiring dietary intervention
is exactly the same 5
6.
QUESTION
– ASSIGNMENT
• Innot more than 1 page, write on the
principles of meal planning.
• SUBMISSION DATE: Tuesday, 30th August, ’22
via email: jasare@uhas.edu.gh
7.
MODIFICATIONS OF THE
NORMALDIET
‒ Modern dietetic practice have long moved from a period
where standard dietary advice were given to standard
disorders to a period where patients are now encouraged to
be actively involved in their own health care management as
well as take part in the decision making process.
‒ The role of a registered dietitian here becomes the
“ENABLER” i.e. someone who helps people to make
appropriate dietary changes, NOT the “DICTATOR” i.e. telling
people what to do.
7
8.
DIET THERAPY
• Itmeans the use of diet (food and drink) not only in the
care of the sick, but also in the prevention of disease &
the maintenance of health
• Diet therapy is accomplished by changing the patient’s
normal diet in order to meet the altered requirements
resulting from disease or injury
• Therapeutic diets are normally requested by a doctor
attending to a patient in the hospital, and are planned &
prescribed by registered dietitians 8
9.
OBJECTIVES OF DIET
THERAPY/THERAPEUTICDIETS
• To maintain a good nutritional status
• To correct nutrition deficiencies or surplus
• To afford rest to the whole body or to specific organs affected
by disease
• To adjust the diet to the body’s ability to metabolize the
nutrients during a disease state. E.g. CHO modifications in DM
• To bring about changes in body weight whenever necessary
9
10.
FACTORS TO CONSIDERIN
PLANNING THERAPEUTIC DIETS
• The underlying disease condition which needs a change in diet
• The possible duration of the disease
• The factors in the diet which must be altered to overcome the
disease condition
• The patients’ tolerance for food by mouth
• Patients economic status, food preferences & occupation
10
11.
SOME ROUTINE HOSPITALDIETS
The Diet Manual
• Contains all hospitals’ diets
• Describes the diet, rational for its use, foods allowed/not
allowed, nutritional adequacy and sample menu
• Approved by hospital administration, physician, nursing and
clinical dietician
• Different facilities have different diet manuals
11
12.
SOME ROUTINE HOSPITALDIETS
1. The Regular Hospital Diet
• Aka General Diet, House Diet or Routine Diet
‒ No restrictions & used when the client’s medical condition does not
warrant any limitations
‒ It approx. provides 1600 to 2200 kcal and usually contains 60 to 80
g protein, 80 to 100 g fat and 180 to 300 g of carbohydrate
‒ Although there are no particular food restrictions, some facilities
have instituted regular diets that are low in saturated fat, sugar &
salt to follow the dietary recommendations for the general
population
‒ Should provide a well-balanced diet capable of maintaining a
good nutritional status
‒ Recent developments in health care food service include use of
“room service” similar to hotel room service model
12
13.
SOME ROUTINE HOSPITALDIETS
2. NPO (nil per os)
• Patients are put on this diet prior to surgery or a
diagnostic test so that nothing is in the GI tract
13
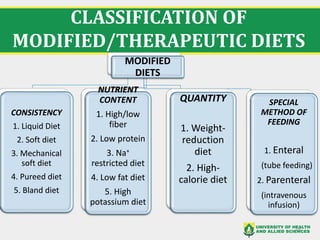
MODIFICATIONS IN
CONSISTENCY
NORMAL DIET-
•A normal diet is defined as one which consist of any and
all food eaten by the person in health.
• It is planned keeping the basic food groups in mind so
that optimum amounts of all nutrients are provided.
• When the patient is hospitalized or at bed rest, a
reduction of 10% (activity factor of 1.1) in energy intake
should be made.
15
16.
MODIFICATIONS IN
CONSISTENCY
1. LIQUID(FLUID) DIETS-
• Consist of foods that are liquid at room temperature &
are used in;
– febrile states (acute fever)
– post-operative conditions or whenever the patient is unable to
tolerate solid foods.
• Liquid diet are of two types depending upon nutritional
adequacy-
– Clear liquid (fluid) diet
– Full liquid (fluid) diet
16
17.
MODIFICATIONS IN CONSISTENCY:
CLEARLIQUID DIET
17
• CONSIST OF ONLY CLEAR LIQUIDS
– The diet is free from any solids, even those found in
milk.
– The clear liquid diet is inadequate in all nutrients &
use only for 1-2 days. It may be high in simple
sugars & need to be modified for diabetic patients.
• Use
– as the first step to restarting of oral feeding after
surgery or abdominal procedure
– to prevent dehydration & relieve thirst
– to replace fluid & electrolyte in people with
severe diarrhoea or acute vomiting
• AMOUNT OF FLUID GIVEN - initially 40 -
80ml/hour, which is then gradually increased to
100-120 ml/hr.
• Average clear liquid diet contains only 500-600
kcal, 5 to 10 g protein, 120-130 g CHO & min fat
FOODS INCLUDED:-
• Fruit juices w/o pulp–
apple/grape juices
• Cereal water - barley,
arrowroot water,
• Soups - clear soups,
fat-free broths
• Beverages - tea, coffee
with lime & sugar (no
milk), lime juice,
coconut water,
sugarcane juice
• Flavored gelatin (Jell-
O)
18.
MODIFICATIONS IN CONSISTENCY:
FULLLIQUID DIET
18
• A diet consisting of all beverages allowed on clear
liquid diets with addition of milk, ice cream and liquid
nutritional supplements.
– prescribed to individuals who are unable to chew,
swallow or tolerate mechanical soft diet or solid foods.
– given after clear liquid diet & before starting solid
diet (transition between clear liquids & solid food)
– composed of foods that are liquid at room
temperature.
– It is free from cellulose & irritating condiments or
spices.
– It is well planned to meet most of the RDA’s
– prescribed during acute infections, gastritis, after
surgery, & for people too ill to eat solid foods
• Diet provides - approx. 1500-2000 kcal, 55-65 g
protein and adequate minerals and vitamins
FOODS INCLUDED-
• Cream soups,
whipped potatoes.
• Milk shakes, plain
ice cream,
yoghurt, custard.
• Oat meal with
milk.
• Soya-milk,
complan, Ensure
and Boost
20.
MODIFICATIONS IN CONSISTENCY:
2.SOFT DIET
20
• Soft diet is a nutritionally adequate
diet.
– It is soft in consistency & easy to chew
– Made up of simple, easily digested foods
– It is moderately low in cellulose
• Prescribed in- conditions where
mechanical ease in both eating or
digestion are desired.
– Given during - acute infections, GI disorders,
chewing problems & after surgery.
• SOFT DIET SUPPLIES- 1800-2000
kcal, 55-65g protein.
FOODS INCLUDED-
• Refined cereals
• Washed pulses- form of soups & in
combination of cereals & veggies.
• Milk & milk products.
• Eggs & lean meats.
• Soft fruits like papaya, banana,
mango etc.
• Fats like butter, cream, vegetable
oils.
• Salt & sugar in moderation.
FOODS TO AVOID-
• Spicy, highly seasoned & fried foods
• Raw vegetables & fruits.
• Whole grain cereals & their product
• Dried fruits & nuts.
21.
MODIFICATIONS IN CONSISTENCY:
3.MECHANICAL SOFT DIET
21
• Also called dental diet. Used when there are chewing &
swallowing problems
• It is for people with poor dental conditions, missing
teeth or no teeth or a condition called dysphasia
• It includes foods which are easy to chew & swallow.
• No restriction on seasoning or method of preparation.
• Food may be modified by:
– mechanical processing such as mashing, grinding,
blenderizing, or chopping.
22.
MODIFICATIONS IN CONSISTENCY:
4.PUREED DIET
22
• Changes the regular diet by pureeing it to a smooth liquid
consistency
• Pureed foods are soft, moist & smooth. They have the look &
texture of a pudding and they hold together. They should not be
lumpy, thin or runny.
• Indicated for people with wired jaws extremely poor dentition in
which chewing is inadequate
• It’s also for people with chewing or swallowing difficulties or
with dysphasia condition
• Avoid nuts, seeds, raw vegetables and dried fruits, hard candy.
Allowed: boneless fish, all smooth cooked cereals, pureed pancake
23.
MODIFICATIONS IN CONSISTENCY:
5.BLAND DIET
23
• A diet consisting of foods
that are generally soft, low
in fiber, cooked rather than
raw & not spicy.
• In effect it includes foods
that are mechanically,
chemically & thermally
non irritating
• PRESCRIBED FOR:
– individuals suffering from
gastric or duodenal ulcers,
gastritis, & ulcerative colitis.
FOODS INCLUDED:
• Milk & milk products.
• Refined cereals & rice.
• Cream, butter
• Cooked fruits & vegetables
without peel & seed.
• All egg preparations except
omelet's & fried eggs.
FOODS AVOIDED:
• Strong tea, coffee, alcoholic
beverages, condiments & spices.
• High fiber foods & hot soups &
beverages.
• Fried foods.
24.
MODIFICATIONS IN NUTRIENT
CONTENT
•The nutrient content of the diet is modified to treat
deficiencies, change body weight, or control diseases such
as hypertension, dyslipidemia, diabetes etc.
• Fiber, sodium & fat content are modified in some conditions.
1. MODIFICATION IN FIBER:- bulk & fiber has been used for
all indigestible polysaccharides which remains after digestion
of food.
• Fiber can be modified in two ways:
‒ High fiber diet: used to prevent & treat constipation & high
cholesterol. Prescribed in obesity to increase bulk (volume) of food
‒ Low fiber diet: prescribed during acute infections of GI tract, e.g.
severe diarrhoea, ulcerative colitis. Fruits & veggies without skin
24
25.
MODIFICATIONS IN NUTRIENT
CONTENT
2.HIGH-CALORIE DIET:- This is a normal diet with an
increase in the calorie level to 2000 or more. If appetite is poor,
small servings of highly reinforced foods are given.
• The diet may be modified in consistency and flavour,
according to specific needs.
• Excessive amounts of foods that have a low calorific value
and fried foods which disturb the appetite should be
avoided.
• This diet is prescribed for conditions such as:
‒ Burns
‒ Fever
‒ Hyperthyroidism
‒ Malnutrition (underweight)
25
26.
MODIFICATIONS IN NUTRIENT
CONTENT
3.LOW-CALORIE DIET:- This diet controls calories
(carbohydrates, proteins and fat) intake in balanced amount to
meet the nutritional needs & control blood sugar and weight.
• This is a normal diet with energy values reduced to 1500 or
1200 calories.
̶ Protein levels should be at 65 to 100g.
̶ Supplements of Vitamin A and thiamine are usually required for
diets below 1000 calories.
• This diet is prescribed for reducing body weight in:
‒ Diabetes mellitus
‒ Cardiovascular diseases
‒ Hypertension
‒ Gout
‒ Preceding surgery
26
27.
MODIFICATIONS IN NUTRIENT
CONTENT
4.HIGH PROTEIN DIET:- This is a diet which is high in
plant & animal proteins
• Used to treat malnutrition or to increase muscle mass
• High protein diet of ≥ 2 g/kg body wt may be prescribed
for a variety of conditions like:
‒ Burns
‒ Fever
‒ Hyperthyroidism
‒ Post surgery
27
28.
MODIFICATIONS IN NUTRIENT
CONTENT
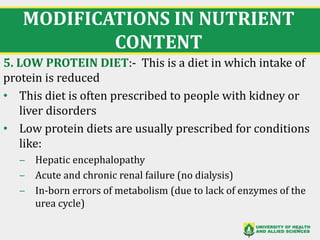
5.LOW PROTEIN DIET:- This is a diet in which intake of
protein is reduced
• This diet is often prescribed to people with kidney or
liver disorders
• Low protein diets are usually prescribed for conditions
like:
‒ Hepatic encephalopathy
‒ Acute and chronic renal failure (no dialysis)
‒ In-born errors of metabolism (due to lack of enzymes of the
urea cycle)
28
29.
MODIFICATIONS IN NUTRIENT
CONTENT
6.FAT CONTROLLED DIET:- This type of diet regulates
the amount and type of fat allowed
• Limits fat to 50 g or no more than 20-30% calories
derived from fats with about 7% from saturated fats
and approximately 250 mg cholesterol
• Usually fat controlled diets are prescribed for;
‒ Diseases of the Gall bladder, Liver & pancreas
‒ Atherosclerosis
‒ Dyslipidemia
‒ Myocardial infarction
29
30.
MODIFICATIONS IN NUTRIENT
CONTENT
6.LOW SODIUM DIET:- The mineral content of the diet
may also be modified. Four levels of sodium restriction are
used — 250, 500, 1000 and 2400 mg.
• The diet excludes excess salty foods and salt in cooking
and at the table
• This diet is used both to prevent and treat oedema
• Therefore, it is prescribed for;
‒ Congestive cardiac failure
‒ Hypertension
‒ Liver and renal diseases
30
31.
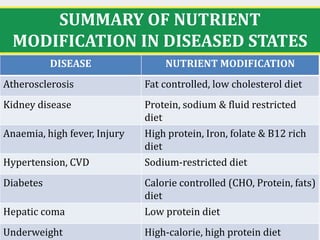
SUMMARY OF NUTRIENT
MODIFICATIONIN DISEASED STATES
31
DISEASE NUTRIENT MODIFICATION
Atherosclerosis Fat controlled, low cholesterol diet
Kidney disease Protein, sodium & fluid restricted
diet
Anaemia, high fever, Injury High protein, Iron, folate & B12 rich
diet
Hypertension, CVD Sodium-restricted diet
Diabetes Calorie controlled (CHO, Protein, fats)
diet
Hepatic coma Low protein diet
Underweight High-calorie, high protein diet
32.
MODIFICATIONS IN QUANTITY
•The quantity of food served to the patient needs to
be modified to:-
‒ check tolerance,
‒ control nutrient levels (i.e., CHO, Prot. & Fats)
‒ control weight
• Example - in a diabetic diet, the quantity of CHO in
each meal is as important as the quantity of CHO
consumed in a day (portion control is used at
mealtimes as prescribed by RD using exchange list for
meal planning)
32
33.
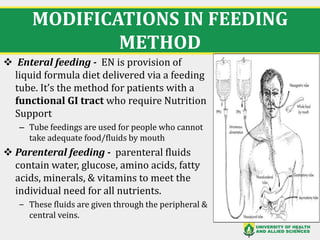
MODIFICATIONS IN FEEDING
METHOD
❖Enteral feeding - EN is provision of
liquid formula diet delivered via a feeding
tube. It’s the method for patients with a
functional GI tract who require Nutrition
Support
– Tube feedings are used for people who cannot
take adequate food/fluids by mouth
❖ Parenteral feeding - parenteral fluids
contain water, glucose, amino acids, fatty
acids, minerals, & vitamins to meet the
individual need for all nutrients.
‒ These fluids are given through the peripheral &
central veins.
33
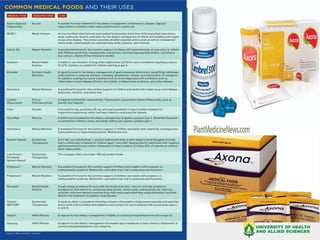
MEDICAL FOOD SUPPLEMENTS:
ModifiedFoods & Beverages
• Medical foods are specially formulated products defined and
regulated by the FDA as follows:
‒ Medical foods aren’t regular foods. They’re orally administered
dietary products formulated for the management of diseases for
which specific nutritional requirements have been established.
‒ Medical foods aren’t drugs or dietary supplements and are
monitored separately by the FDA.
‒ All efficacy claims for medical foods must be based on
recognized scientific principles and sound laboratory and
clinical data.
‒ Medical foods must be comprised of components designated
as “Generally Regarded as Safe”
‒ Ingredients in medical foods must be listed on the product
label in descending order of content.
‒ Medical foods may be used only under medical supervision
35
37.
MEDICAL FOOD SUPPLEMENTS:
ModifiedFoods & Beverages
• Oral intake may be increased by supplementing a balanced
diet with between-meal or evening snacks of nutrient-
dense foods acceptable to the individual patient
• For these snacks, traditional foods such as fruits, crackers,
sandwiches, milk shakes, custard or pudding may be served.
• For individuals with decreased appetite, increasing nutrient
density without actually increasing volume is advised.
‒ For e.g. instead of using skim milk, the patient could receive whole
milk with 2 tablespoons of dry milk powder to boost both kcal &
protein
‒ Adding peanut butter to toasted bread for breakfast is great for
increasing both kcal & protein
37
38.
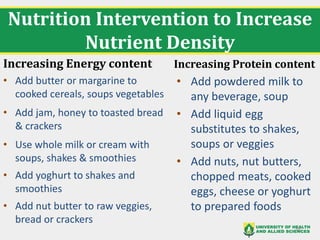
Nutrition Intervention toIncrease
Nutrient Density
Increasing Energy content
• Add butter or margarine to
cooked cereals, soups vegetables
• Add jam, honey to toasted bread
& crackers
• Use whole milk or cream with
soups, shakes & smoothies
• Add yoghurt to shakes and
smoothies
• Add nut butter to raw veggies,
bread or crackers
Increasing Protein content
• Add powdered milk to
any beverage, soup
• Add liquid egg
substitutes to shakes,
soups or veggies
• Add nuts, nut butters,
chopped meats, cooked
eggs, cheese or yoghurt
to prepared foods
38
39.
Modified Foods andBeverages
• Another means to modify foods is to add single nutrients like
protein or fiber through the use of modular products.
• A CHO modular supplement like Polycose, provides glucose
polymers and generally does not alter the taste of food to
which it is added.
• Protein modular like ProMod or Beneprotein (powder) can be
added to both foods & beverages but must be mixed well.
‒ There is a slight change in taste and consistency
• Lipid modular supplements like medium-chain triglyceride
(MCT) also has a slight change in taste and consistency.
‒ E.g. MCT oil, MCT fuel, MCT power. 1 Tbs gives 6 g of MCT & 50 kcal
• Generally, modular foods are not cost-efficient relative to other
types of supplements
39
MEDICAL FOOD SUPPLEMENT:
CommercialBeverages
• Liquid meal replacement formulas may provide a convenient
alternative to between-meal snacks.
• These products provide 250 to 350 kcal with 7 to 15 g of protein
in 250 ml and come in various flavours
• They are lactose free and some contain fiber with others being
more calorically dense or higher in protein
– Examples include Ensure, Boost, Mighty shakes, Resource Health shake,
and Carnation instant breakfast
• Some of these products are available in liquid form, as puddings
or as cereal-type bars
• Many of these products are for specific medical conditions like
wound healing or diabetes
41
MEDICAL FOOD SUPPLEMENT:
CommercialBeverages
• Commercial supplements are popular because of their
convenience and also because patients and caregivers may
be familiar with them due to marketing via the media
• However, acceptability and intake are individual.
• Patients receiving oral supplements frequently develop
“taste fatigue” a few days after initiation of supplement
intake
• Note: merely providing supplemental feeding will not
increase appetite; in fact many pts complain that extra
portions, frequent meals & supplemental snacks are
overwhelming & reduce appetite, hence, the need to
involve the patient in the decision making
44.
MEDICAL FOOD SUPPLEMENT:
CommercialBeverages
• Provide supplement taste tests to help patient decide
which supplement they would prefer to add to their diet
• Develop a rotation for snacks or supplements and set
portion size goals with the patient to improve acceptance
• Regular follow-up and monitoring are necessary in order to
coordinate successful interventions and minimize waste
associated with unused products
45.
DIETARY SUPPLEMENTS:
Definition
• Aproduct intended for ingestion that, among other
requirements, contains a “dietary ingredient” intended to add
nutritional value to the diet (FDA, 2022)
• The term “dietary ingredients” includes:
– Amino acids (e.g., Leucine, isoleucine, tryptophan, glutamine etc)
– Vitamins and minerals (e.g., biotin & iron)
– Herbs and botanicals (e.g., Ginseng, cinnamon, ginger, garlic etc.)
– Dietary substances that are part of the food supply, e.g., enzymes
(e.g., lactase) & live microbials (commonly called probiotics)
– Concentrate, metabolite, extract, or a combination of any dietary
ingredient from the others listed above
46.
DIETARY SUPPLEMENTS:
Definition
• Dietarysupplements come in many forms, including;
– Pills, tablets, capsules, powders, liquids, teas etc.
• They are intended to be a supplement to the diet
• Intended to be taken by mouth; this excludes other routes
of administration, such as intranasal, transdermal, &
suppository
• Benefits of dietary supplements:
– Help improve or maintain overall health
– Help meet daily requirements of essential nutrients
47.
VITAMIN AND MINERAL
SUPPLEMENTS
•Nutrition assessment may reveal that a patient’s diet is
inadequate to meet the standard recommended amounts of
essential vitamins and minerals.
– Such a patient should be prescribed supplements of the deficient
nutrients
• Also, many medical conditions interfere with digestion,
absorption, or utilization of micronutrients
• Therefore, making appropriate, evidence-based
recommendations for supplementation of vitamin and minerals
is an expected step in nutrition intervention.
– E.g. for an osteopenia pt, you would recommend supplementation with
Adequate Intake (AI) for calcium according to the age and gender
– And provide instructions on appropriate sources of supplements
49.
BIOACTIVE SUBSTANCE
SUPPLEMENTS
• Bioactivesubstances are defined as food
substances added to a food product or taken as a
supplement that have a specific intended health
purpose.
– Example, a patient with hyperlipidaemia may be
instructed to consume stanol esters as a supplement.
The RD would instruct the patient on the amount of
stanol esters recommended for the intended reduction
of lipid levels
– The RD would describe the current products available
for purchase and assist the patient with the
incorporation of the products into their dietary plan
– Other examples of bioactive substance include pro-
/prebiotics