RESPONDINGTO
SYMPTOMS OF MINOR
AILMENTS
CONCEPT
 Minor ailments are common, self-limiting conditions
that can be managed with simple advice, OTC medicines,
or lifestyle modifications.
 Examples: Headache, fever, common cold, indigestion,
diarrhea, constipation, minor skin infections, mouth ulcers.
 Pharmacist’s role: First point of contact, providing safe,
effective, and accessible care
COMMON DRUGTHERAPY &
PATHOPHYSIOLOGY
1. Pain
2. GI disturbances (Nausea,Vomiting,
Dyspepsia, diarrhea, constipation)
3. Pyrexia
4. Ophthalmic symptoms
5. worms infestations.
1. PAIN
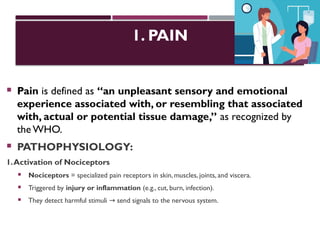
 Pain is defined as “an unpleasant sensory and emotional
experience associated with, or resembling that associated
with, actual or potential tissue damage,” as recognized by
the WHO.
 PATHOPHYSIOLOGY:
1.Activation of Nociceptors
 Nociceptors = specialized pain receptors in skin, muscles, joints, and viscera.
 Triggered by injury or inflammation (e.g., cut, burn, infection).
 They detect harmful stimuli send signals to the nervous system.
→
2. Chemical Mediators Sensitization
→
 Tissue damage releases pro pain chemicals
‑ :
 Prostaglandins lower threshold of nociceptors.
→
 Bradykinin directly excites nociceptors.
→
 Substance P enhances pain transmission and causes vasodilation.
→
 Result: sensitization (nociceptors become hyper responsive even mild stimuli feel
‑ →
painful).
3.Transmission Pathway
 Pain signals travel via afferent nerve fibers (A delta, C fibers).
‑
 Enter spinal cord (dorsal horn) synapse with secondary neurons.
→
 Ascend via spinothalamic tract reach
→ thalamus (relay station).
 Finally, signals go to the cerebral cortex conscious perception of pain.
→
TYPES OF PAIN
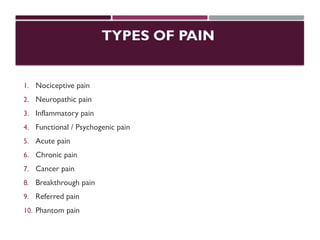
1. Nociceptive pain
2. Neuropathic pain
3. Inflammatory pain
4. Functional / Psychogenic pain
5. Acute pain
6. Chronic pain
7. Cancer pain
8. Breakthrough pain
9. Referred pain
10. Phantom pain
DRUGTHERAPY
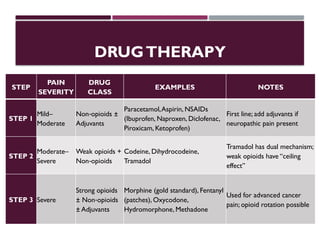
STEP
PAIN
SEVERITY
DRUG
CLASS
EXAMPLES NOTES
STEP 1
Mild–
Moderate
Non opioids ±
‑
Adjuvants
Paracetamol,Aspirin, NSAIDs
(Ibuprofen, Naproxen, Diclofenac,
Piroxicam, Ketoprofen)
First line; add adjuvants if
neuropathic pain present
STEP 2
Moderate–
Severe
Weak opioids +
Non opioids
‑
Codeine, Dihydrocodeine,
Tramadol
Tramadol has dual mechanism;
weak opioids have “ceiling
effect”
STEP 3 Severe
Strong opioids
± Non opioids
‑
± Adjuvants
Morphine (gold standard), Fentanyl
(patches), Oxycodone,
Hydromorphone, Methadone
Used for advanced cancer
pain; opioid rotation possible
CLASSIFICATION
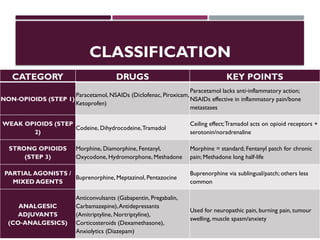
CATEGORY DRUGS KEY POINTS
NON OPIOIDS (STEP 1)
‑
Paracetamol, NSAIDs (Diclofenac, Piroxicam,
Ketoprofen)
Paracetamol lacks anti inflammatory action;
‑
NSAIDs effective in inflammatory pain/bone
metastases
WEAK OPIOIDS (STEP
2)
Codeine, Dihydrocodeine,Tramadol
Ceiling effect;Tramadol acts on opioid receptors +
serotonin/noradrenaline
STRONG OPIOIDS
(STEP 3)
Morphine, Diamorphine, Fentanyl,
Oxycodone, Hydromorphone, Methadone
Morphine = standard; Fentanyl patch for chronic
pain; Methadone long half life
‑
PARTIAL AGONISTS /
MIXED AGENTS
Buprenorphine, Meptazinol, Pentazocine
Buprenorphine via sublingual/patch; others less
common
ANALGESIC
ADJUVANTS
(CO ANALGESICS)
‑
Anticonvulsants (Gabapentin, Pregabalin,
Carbamazepine),Antidepressants
(Amitriptyline, Nortriptyline),
Corticosteroids (Dexamethasone),
Anxiolytics (Diazepam)
Used for neuropathic pain, burning pain, tumour
swelling, muscle spasm/anxiety
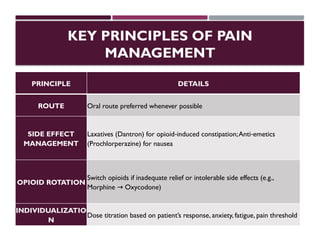
KEY PRINCIPLES OF PAIN
MANAGEMENT
PRINCIPLE DETAILS
ROUTE Oral route preferred whenever possible
SIDE EFFECT
MANAGEMENT
Laxatives (Dantron) for opioid induced constipation;Anti emetics
‑ ‑
(Prochlorperazine) for nausea
OPIOID ROTATION
Switch opioids if inadequate relief or intolerable side effects (e.g.,
Morphine Oxycodone)
→
INDIVIDUALIZATIO
N
Dose titration based on patient’s response, anxiety, fatigue, pain threshold
2. GI DISTURBANCES
a) Nausea &Vomiting
 Pathophysiology:
 Triggered by chemoreceptor trigger zone (dopamine, serotonin), vestibular
system (histamine, acetylcholine), or GI vagal afferents.
 Drug therapy:
 5 HT3 antagonists:
‑ Ondansetron.
 D2 antagonists: Metoclopramide, domperidone.
 Antihistamines/anticholinergics: Promethazine, meclizine (motion
sickness).
 Pharmacist role: Identify cause, advise hydration, caution
on side effects (EPS with metoclopramide).
b) Dyspepsia
 Pathophysiology:
 Excess gastric acid, impaired mucosal protection,
H. pylori infection.
 Drug therapy:
 Antacids: Magnesium hydroxide, calcium carbonate.
 H2 blockers: Famotidine.
 PPIs: Omeprazole, pantoprazole.
 Pharmacist role: Short term OTC relief,
‑
refer if alarm symptoms (bleeding, weight
loss).
c) Diarrhea
 Pathophysiology:
 Increased intestinal secretion (toxins, infection),
decreased absorption.
 Drug therapy:
 ORS + zinc (WHO standard).
 Loperamide (non infective adult diarrhea).
‑
 Antibiotics only for confirmed bacterial causes.
 Pharmacist role: Emphasize ORS, hygiene,
refer if bloody stools or dehydration
d) Constipation
 Pathophysiology:
 Slow colonic transit, low fiber/fluid intake, drug induced (opioids).
‑
 Drug therapy:
 Bulk forming:
‑ Psyllium.
 Osmotic: Lactulose, PEG.
 Stimulant: Bisacodyl, senna (short term).
‑
 Pharmacist role: Counsel on diet, fluids, exercise; avoid
chronic stimulant use.
3. PYREXIA (FEVER)
 PATHOPHYSIOLOGY:
1. Trigger (Pyrogens)
 Substances called pyrogens start the process.
 They can be exogenous (from outside, e.g., bacterial toxins like LPS) or endogenous (from inside, e.g., cytokines
like IL 1, IL 6,TNF ).
‑ ‑ ‑α
2. Signal to Brain
 These pyrogens act on the hypothalamus (the body’s thermostat).
 The hypothalamus raises the set point
‑ for body temperature.
3. Body Response
 To reach the new set point, the body generates heat:
‑
 Shivering (muscle activity heat).
→
 Vasoconstriction (less heat loss through skin).
 Result: temperature rises fever
→ .
4. Control (Cryogens)
 Other substances called cryogens (like anti pyretic cytokines) prevent the temperature from going too high.
‑
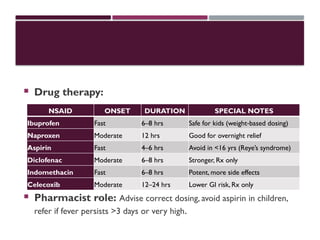
 Drug therapy:
 Pharmacist role: Advise correct dosing, avoid aspirin in children,
refer if fever persists >3 days or very high.
NSAID ONSET DURATION SPECIAL NOTES
Ibuprofen Fast 6–8 hrs Safe for kids (weight based dosing)
‑
Naproxen Moderate 12 hrs Good for overnight relief
Aspirin Fast 4–6 hrs Avoid in <16 yrs (Reye’s syndrome)
Diclofenac Moderate 6–8 hrs Stronger, Rx only
Indomethacin Fast 6–8 hrs Potent, more side effects
Celecoxib Moderate 12–24 hrs Lower GI risk, Rx only
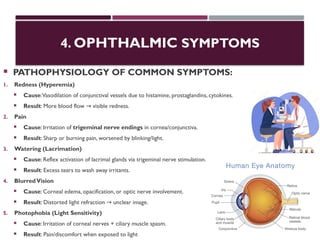
4. OPHTHALMIC SYMPTOMS
 PATHOPHYSIOLOGY OF COMMON SYMPTOMS:
1. Redness (Hyperemia)
 Cause:Vasodilation of conjunctival vessels due to histamine, prostaglandins, cytokines.
 Result: More blood flow visible redness.
→
2. Pain
 Cause: Irritation of trigeminal nerve endings in cornea/conjunctiva.
 Result: Sharp or burning pain, worsened by blinking/light.
3. Watering (Lacrimation)
 Cause: Reflex activation of lacrimal glands via trigeminal nerve stimulation.
 Result: Excess tears to wash away irritants.
4. BlurredVision
 Cause: Corneal edema, opacification, or optic nerve involvement.
 Result: Distorted light refraction unclear image.
→
5. Photophobia (Light Sensitivity)
 Cause: Irritation of corneal nerves + ciliary muscle spasm.
 Result: Pain/discomfort when exposed to light
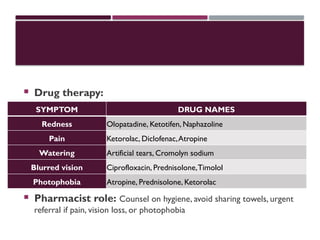
 Drug therapy:
 Pharmacist role: Counsel on hygiene, avoid sharing towels, urgent
referral if pain, vision loss, or photophobia
SYMPTOM DRUG NAMES
Redness Olopatadine, Ketotifen, Naphazoline
Pain Ketorolac, Diclofenac,Atropine
Watering Artificial tears, Cromolyn sodium
Blurred vision Ciprofloxacin, Prednisolone,Timolol
Photophobia Atropine, Prednisolone, Ketorolac
5.WORM INFESTATIONS (HELMINTHS)
 Worm infestation (helminthic infection) occurs when parasitic worms enter the
human body, usually through contaminated food, water, or soil, and cause symptoms
by damaging tissues, consuming nutrients, and triggering immune responses.The
pathophysiology involves invasion, migration, and chronic effects like anemia,
malnutrition, and organ damage.
 PATHOPHYSIOLOGY OF WORM INFESTATION
1. ENTRY &TRANSMISSION
 Feco oral route
‑ : Ingestion of eggs/larvae from contaminated food, water, or dirty hands (e.g., Ascaris,
Trichuris, Enterobius).
 Skin penetration: Hookworm larvae penetrate skin (often bare feet).
 Intermediate hosts:Tapeworms via undercooked meat/fish (Taenia, Diphyllobothrium).
2. LARVAL MIGRATION
o After entry, larvae migrate through bloodstream to organs:
 Ascaris lungs coughed up swallowed intestines.
→ → → →
 Hookworms lungs swallowed intestines.
→ → →
3. INTESTINAL COLONIZATION
 Adult worms settle in the small or large intestine.
 They attach to mucosa, consume nutrients, or suck blood.
 Leads to abdominal pain, diarrhea, malabsorption, anemia.
4. IMMUNE &TISSUE RESPONSE
 Worm antigens trigger eosinophilia and IgE mediated immune reactions.
‑
 Chronic inflammation mucosal damage, villous atrophy, ulceration.
→
 Skin manifestations (itch, rash) from larval penetration.
5. CHRONIC EFFECTS
 Iron deficiency anemia (hookworm sucking blood).
 Malnutrition & growth retardation (nutrient diversion).
 Failure to thrive, irritability, pot belly in children.
 Organ damage: Hydatid cysts (liver, brain, lungs), neurocysticercosis (seizures).
KEY RISKS
 Children: Growth retardation, poor school performance.
 Pregnant women: Severe anemia maternal mortality risk.
→
 Heavy infestations: Intestinal obstruction, biliary colic, seizures.
PRACTICALTAKEAWAY
 Pathophysiology = Entry Migration Intestinal colonization Immune
→ → →
response Chronic effects.
→
 Treatment: Albendazole, Mebendazole, Pyrantel pamoate, Praziquantel
(depending on worm type).
 Prevention: Hand hygiene, safe water, footwear, deworming programs.
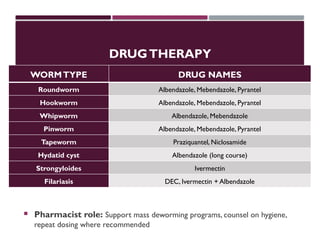
DRUGTHERAPY
 Pharmacist role: Support mass deworming programs, counsel on hygiene,
repeat dosing where recommended
WORMTYPE DRUG NAMES
Roundworm Albendazole, Mebendazole, Pyrantel
Hookworm Albendazole, Mebendazole, Pyrantel
Whipworm Albendazole, Mebendazole
Pinworm Albendazole, Mebendazole, Pyrantel
Tapeworm Praziquantel, Niclosamide
Hydatid cyst Albendazole (long course)
Strongyloides Ivermectin
Filariasis DEC, Ivermectin + Albendazole
THANKYOU !