Comprehensive Guide to Iron Supplementation in Pregnancy and Anemia Management
Overview of iron supplementation, requirements during pregnancy, administration routes, pharmacokinetics, toxicity, adverse effects, and nursing roles in managing iron-deficiency anemia.
Comprehensive Guide to Iron Supplementation in Pregnancy and Anemia Management
1.
Iron Supplementation
By GovindaGajbhiye Bsc Nursing MSc Nursing
MA clinical psychologist
Assistant Professor
Subject - Pharmacology
Bsc Nursing 4th semester students
2.
Introduction
Iron deficiency ismore common in pregnant women, infants, and rapidly
growing children because their iron requirements are increased.
During pregnancy, iron is required for expansion of maternal blood volume,
formation of the placenta, and growth of the fetus.
Adequate iron supplementation helps prevent iron-deficiency anemia,
maternal complications, low birth weight, and impaired fetal growth.
Although iron deficiency is the most common cause of anemia, other factors
such as infections, genetic disorders, chronic diseases, and nutritional
deficiencies can also cause anemia.
3.
Introduction
Iron supplementation isthe administration of iron preparations to prevent or
treat iron-deficiency anemia. Iron is an essential mineral required for the
formation of hemoglobin, myoglobin, and several enzymes. When dietary
iron is insufficient or iron requirements are increased, supplementation helps
restore hemoglobin levels and replenish body iron stores.
4.
Iron Requirement inPregnancy
● The total additional iron requirement during pregnancy is approximately
1,000 mg. This iron is mainly needed for:
● Increased maternal RBC mass
● Fetal growth and development
● Placental development
● Blood loss during delivery
● Iron supplementation during pregnancy is important to prevent and
treat iron-deficiency anemia and to maintain adequate maternal and
fetal iron stores.
5.
Iron deficiency generallydevelops in three
progressive stages:
● Depletion of iron stores – body iron stores decrease, but hemoglobin
remains normal.
● Iron-deficient erythropoiesis – iron supply to the bone marrow becomes
inadequate for normal RBC production.
● Iron-deficiency anemia – hemoglobin and hematocrit decrease,
producing clinical anemia.
6.
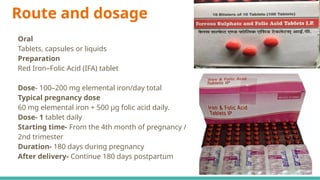
Route and dosage
Oral
Tablets,capsules or liquids
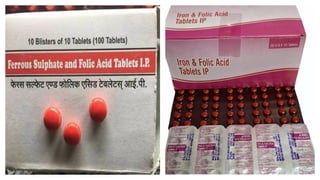
Preparation
Red Iron–Folic Acid (IFA) tablet
Dose- 100–200 mg elemental iron/day total
Typical pregnancy dose
60 mg elemental iron + 500 µg folic acid daily.
Dose- 1 tablet daily
Starting time- From the 4th month of pregnancy /
2nd trimester
Duration- 180 days during pregnancy
After delivery- Continue 180 days postpartum
8.
Vitamin C Given
●Role of Vitamin C in Iron Absorption
● Vitamin C increases the absorption of iron
from the intestine.
● It converts ferric iron (Fe³⁺) into ferrous iron
(Fe²⁺).
● Ferrous iron (Fe²⁺) is absorbed more easily
in the intestine.
● Therefore, taking iron with vitamin C or
citrus juice (e.g., lemon/orange juice) can
improve iron absorption.
9.
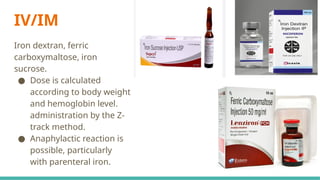
IV/IM
Iron dextran, ferric
carboxymaltose,iron
sucrose.
● Dose is calculated
according to body weight
and hemoglobin level.
administration by the Z-
track method.
● Anaphylactic reaction is
possible, particularly
with parenteral iron.
10.
Indications
● Prevention ofiron-deficiency anemia during pregnancy
● Iron-deficiency anemia
● Increased iron requirements during pregnancy, infancy, childhood and
adolescence
● Iron deficiency due to chronic blood loss — e.g., heavy menstrual bleeding
● Postpartum iron deficiency/anemia
● Iron deficiency due to inadequate dietary intake or poor absorption
● Iron deficiency after significant blood loss, when iron replacement is
required
11.
Contraindications
● Hypersensitivity/allergy tothe iron preparation
● Anemia not caused by iron deficiency (e.g., hemolytic anemia or anemia
of certain chronic diseases where iron is not indicated)
● Iron overload or iron-storage disorders, such as
hemochromatosis/hemosiderosis
12.
Pharmacokinetics of Iron
●Absorption: Mainly in the duodenum and upper jejunum.
● Distribution: Transported in blood by transferrin.
● Storage: Stored as ferritin and hemosiderin in liver, spleen
and bone marrow.
● Utilization: Used mainly for hemoglobin and RBC
formation.
● Excretion: Very little iron is excreted; mainly lost through
feces and shedding of cells.
13.
Mechanism of action:
●Iron is absorbed mainly in the duodenum and jejunum.
● It enters the blood and binds to transferrin for transport.
● Iron is delivered to the bone marrow.
● It is incorporated into hemoglobin during formation of red
blood cells.
● Increased hemoglobin improves the oxygen-carrying
capacity of blood.
● Iron also replenishes body iron stores (mainly ferritin).
14.
Iron Toxicity
● Common:Nausea, vomiting, abdominal pain, constipation
or diarrhea.
● Severe toxicity: Gastrointestinal bleeding, metabolic
acidosis, shock, liver injury and organ failure.
● Acute overdose: Particularly dangerous in children.
● Treatment: Severe poisoning may require deferoxamine
(iron chelator) and supportive management.
15.
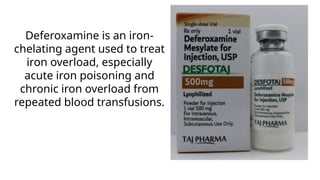
Deferoxamine is aniron-
chelating agent used to treat
iron overload, especially
acute iron poisoning and
chronic iron overload from
repeated blood transfusions.
16.
Adverse Effects ofIron Supplementation
Oral Iron
Nausea and vomiting
Abdominal pain/discomfort
Constipation — common
Diarrhea
Heartburn
Metallic taste
Black/dark stools
Teeth staining — particularly with
liquid iron preparations
2. Injectable Iron
Common:
Pain, redness or swelling at injection site
Headache
Dizziness
Nausea
Flushing
Muscle/joint pain
Serious:
Hypersensitivity/allergic reaction
Anaphylaxis — rare but potentially life-
threatening
Hypotension, particularly with rapid IV
administration
17.
Role of Nursein Iron Supplementation
● Administer IM or IV iron when oral iron is poorly absorbed or not tolerated.
● For IM iron, follow the prescribed protocol for any required test dose/sensitivity precautions
and observe for anaphylaxis or other allergic reactions.
● Advise the patient to take oral iron about 1 hour before meals for maximum absorption.
● If gastric irritation occurs, advise taking iron with meals temporarily; return to between-meal
dosing when symptoms improve.
● Explain that iron supplements may cause dark green or black stools.
● Advise patients taking liquid iron to use a straw and rinse the mouth with water afterward to
prevent tooth staining.
● Monitor hemoglobin (Hb), hematocrit (Hct), RBC count, and reticulocyte count to assess
response to therapy.
● Educate the patient about energy-conservation techniques, adequate rest, and avoiding
excessive exertion when anemia causes fatigue.
● Encourage adherence to the prescribed iron therapy and follow-up investigations.