Comprehensive Guide to Conducting a Mental Status Examination in Psychiatry
Detailed overview of the Mental Status Examination (MSE) including its sections, assessment methods, and diagnostic examples to aid psychiatric diagnosis and treatment planning.
Comprehensive Guide to Conducting a Mental Status Examination in Psychiatry
1.
MENTAL STATUS EXAMINATION
•It is a standard part of any psychiatric interview
• Much of the information is obtained in the course of the interview through
informal observation
• Although some aspects that need formal questioning.
• The data obtained in the MSE will help in the process of making a diagnosis and
treatment plan as well as help provide a baseline for future reference
Mental Status Exam Sections
1. Appearance
2. Behavior
3. Mood
4. Affect
5. Speech
6. Thought Process
7. Thought Content
8. Cognition
9. Judgment
10. Insight
Where interview for MSE can be done? 1. Hospital room 2. Waiting room 3. Out-
patient clinic office 4. Emergency Room Etc.
2.
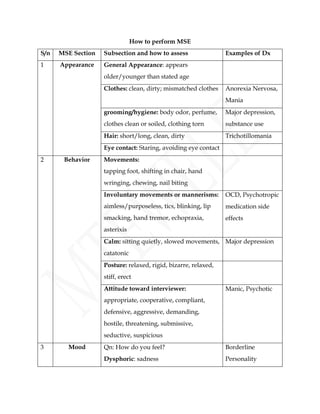
How to performMSE
S/n MSE Section Subsection and how to assess Examples of Dx
1 Appearance General Appearance: appears
older/younger than stated age
Clothes: clean, dirty; mismatched clothes Anorexia Nervosa,
Mania
grooming/hygiene: body odor, perfume,
clothes clean or soiled, clothing torn
Major depression,
substance use
Hair: short/long, clean, dirty Trichotillomania
Eye contact: Staring, avoiding eye contact
2 Behavior Movements:
tapping foot, shifting in chair, hand
wringing, chewing, nail biting
Involuntary movements or mannerisms:
aimless/purposeless, tics, blinking, lip
smacking, hand tremor, echopraxia,
asterixis
OCD, Psychotropic
medication side
effects
Calm: sitting quietly, slowed movements,
catatonic
Major depression
Posture: relaxed, rigid, bizarre, relaxed,
stiff, erect
Attitude toward interviewer:
appropriate, cooperative, compliant,
defensive, aggressive, demanding,
hostile, threatening, submissive,
seductive, suspicious
Manic, Psychotic
3 Mood Qn: How do you feel?
Dysphoric: sadness
Borderline
Personality
3.
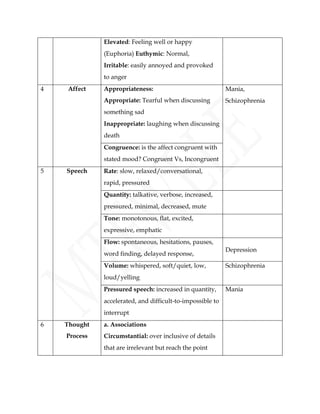
Elevated: Feeling wellor happy
(Euphoria) Euthymic: Normal,
Irritable: easily annoyed and provoked
to anger
4 Affect Appropriateness:
Appropriate: Tearful when discussing
something sad
Inappropriate: laughing when discussing
death
Mania,
Schizophrenia
Congruence: is the affect congruent with
stated mood? Congruent Vs, Incongruent
5 Speech Rate: slow, relaxed/conversational,
rapid, pressured
Quantity: talkative, verbose, increased,
pressured, minimal, decreased, mute
Tone: monotonous, flat, excited,
expressive, emphatic
Flow: spontaneous, hesitations, pauses,
word finding, delayed response,
Depression
Volume: whispered, soft/quiet, low,
loud/yelling
Schizophrenia
Pressured speech: increased in quantity,
accelerated, and difficult-to-impossible to
interrupt
Mania
6 Thought
Process
a. Associations
Circumstantial: over inclusive of details
that are irrelevant but reach the point
4.
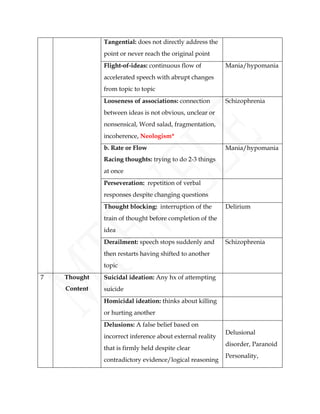
Tangential: does notdirectly address the
point or never reach the original point
Flight-of-ideas: continuous flow of
accelerated speech with abrupt changes
from topic to topic
Mania/hypomania
Looseness of associations: connection
between ideas is not obvious, unclear or
nonsensical, Word salad, fragmentation,
incoherence, Neologism*
Schizophrenia
b. Rate or Flow
Racing thoughts: trying to do 2-3 things
at once
Mania/hypomania
Perseveration: repetition of verbal
responses despite changing questions
Thought blocking: interruption of the
train of thought before completion of the
idea
Delirium
Derailment: speech stops suddenly and
then restarts having shifted to another
topic
Schizophrenia
7 Thought
Content
Suicidal ideation: Any hx of attempting
suicide
Homicidal ideation: thinks about killing
or hurting another
Delusions: A false belief based on
incorrect inference about external reality
that is firmly held despite clear
contradictory evidence/logical reasoning
Delusional
disorder, Paranoid
Personality,
5.
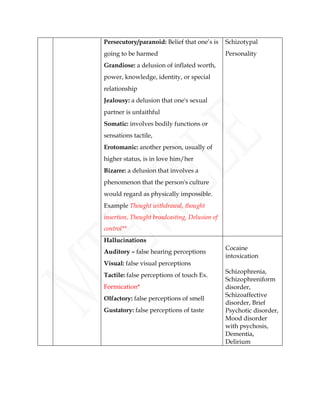
Persecutory/paranoid: Belief thatone’s is
going to be harmed
Grandiose: a delusion of inflated worth,
power, knowledge, identity, or special
relationship
Jealousy: a delusion that one's sexual
partner is unfaithful
Somatic: involves bodily functions or
sensations tactile,
Erotomanic: another person, usually of
higher status, is in love him/her
Bizarre: a delusion that involves a
phenomenon that the person's culture
would regard as physically impossible.
Example Thought withdrawal, thought
insertion, Thought broadcasting, Delusion of
control**
Schizotypal
Personality
Hallucinations
Auditory – false hearing perceptions
Visual: false visual perceptions
Tactile: false perceptions of touch Ex.
Formication*
Olfactory: false perceptions of smell
Gustatory: false perceptions of taste
Cocaine
intoxication
Schizophrenia,
Schizophreniform
disorder,
Schizoaffective
disorder, Brief
Psychotic disorder,
Mood disorder
with psychosis,
Dementia,
Delirium
6.
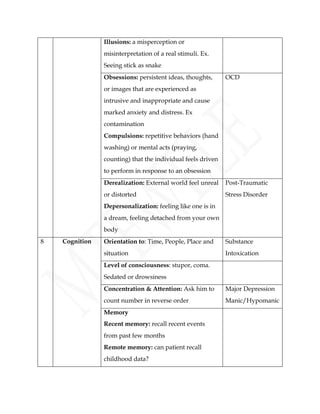
Illusions: a misperceptionor
misinterpretation of a real stimuli. Ex.
Seeing stick as snake
Obsessions: persistent ideas, thoughts,
or images that are experienced as
intrusive and inappropriate and cause
marked anxiety and distress. Ex
contamination
Compulsions: repetitive behaviors (hand
washing) or mental acts (praying,
counting) that the individual feels driven
to perform in response to an obsession
OCD
Derealization: External world feel unreal
or distorted
Depersonalization: feeling like one is in
a dream, feeling detached from your own
body
Post-Traumatic
Stress Disorder
8 Cognition Orientation to: Time, People, Place and
situation
Substance
Intoxication
Level of consciousness: stupor, coma.
Sedated or drowsiness
Concentration & Attention: Ask him to
count number in reverse order
Major Depression
Manic/Hypomanic
Memory
Recent memory: recall recent events
from past few months
Remote memory: can patient recall
childhood data?
7.
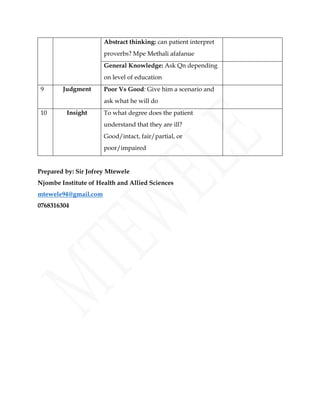
Abstract thinking: canpatient interpret
proverbs? Mpe Methali afafanue
General Knowledge: Ask Qn depending
on level of education
9 Judgment Poor Vs Good: Give him a scenario and
ask what he will do
10 Insight To what degree does the patient
understand that they are ill?
Good/intact, fair/partial, or
poor/impaired
Prepared by: Sir Jofrey Mtewele
Njombe Institute of Health and Allied Sciences
mtewele94@gmail.com
0768316304